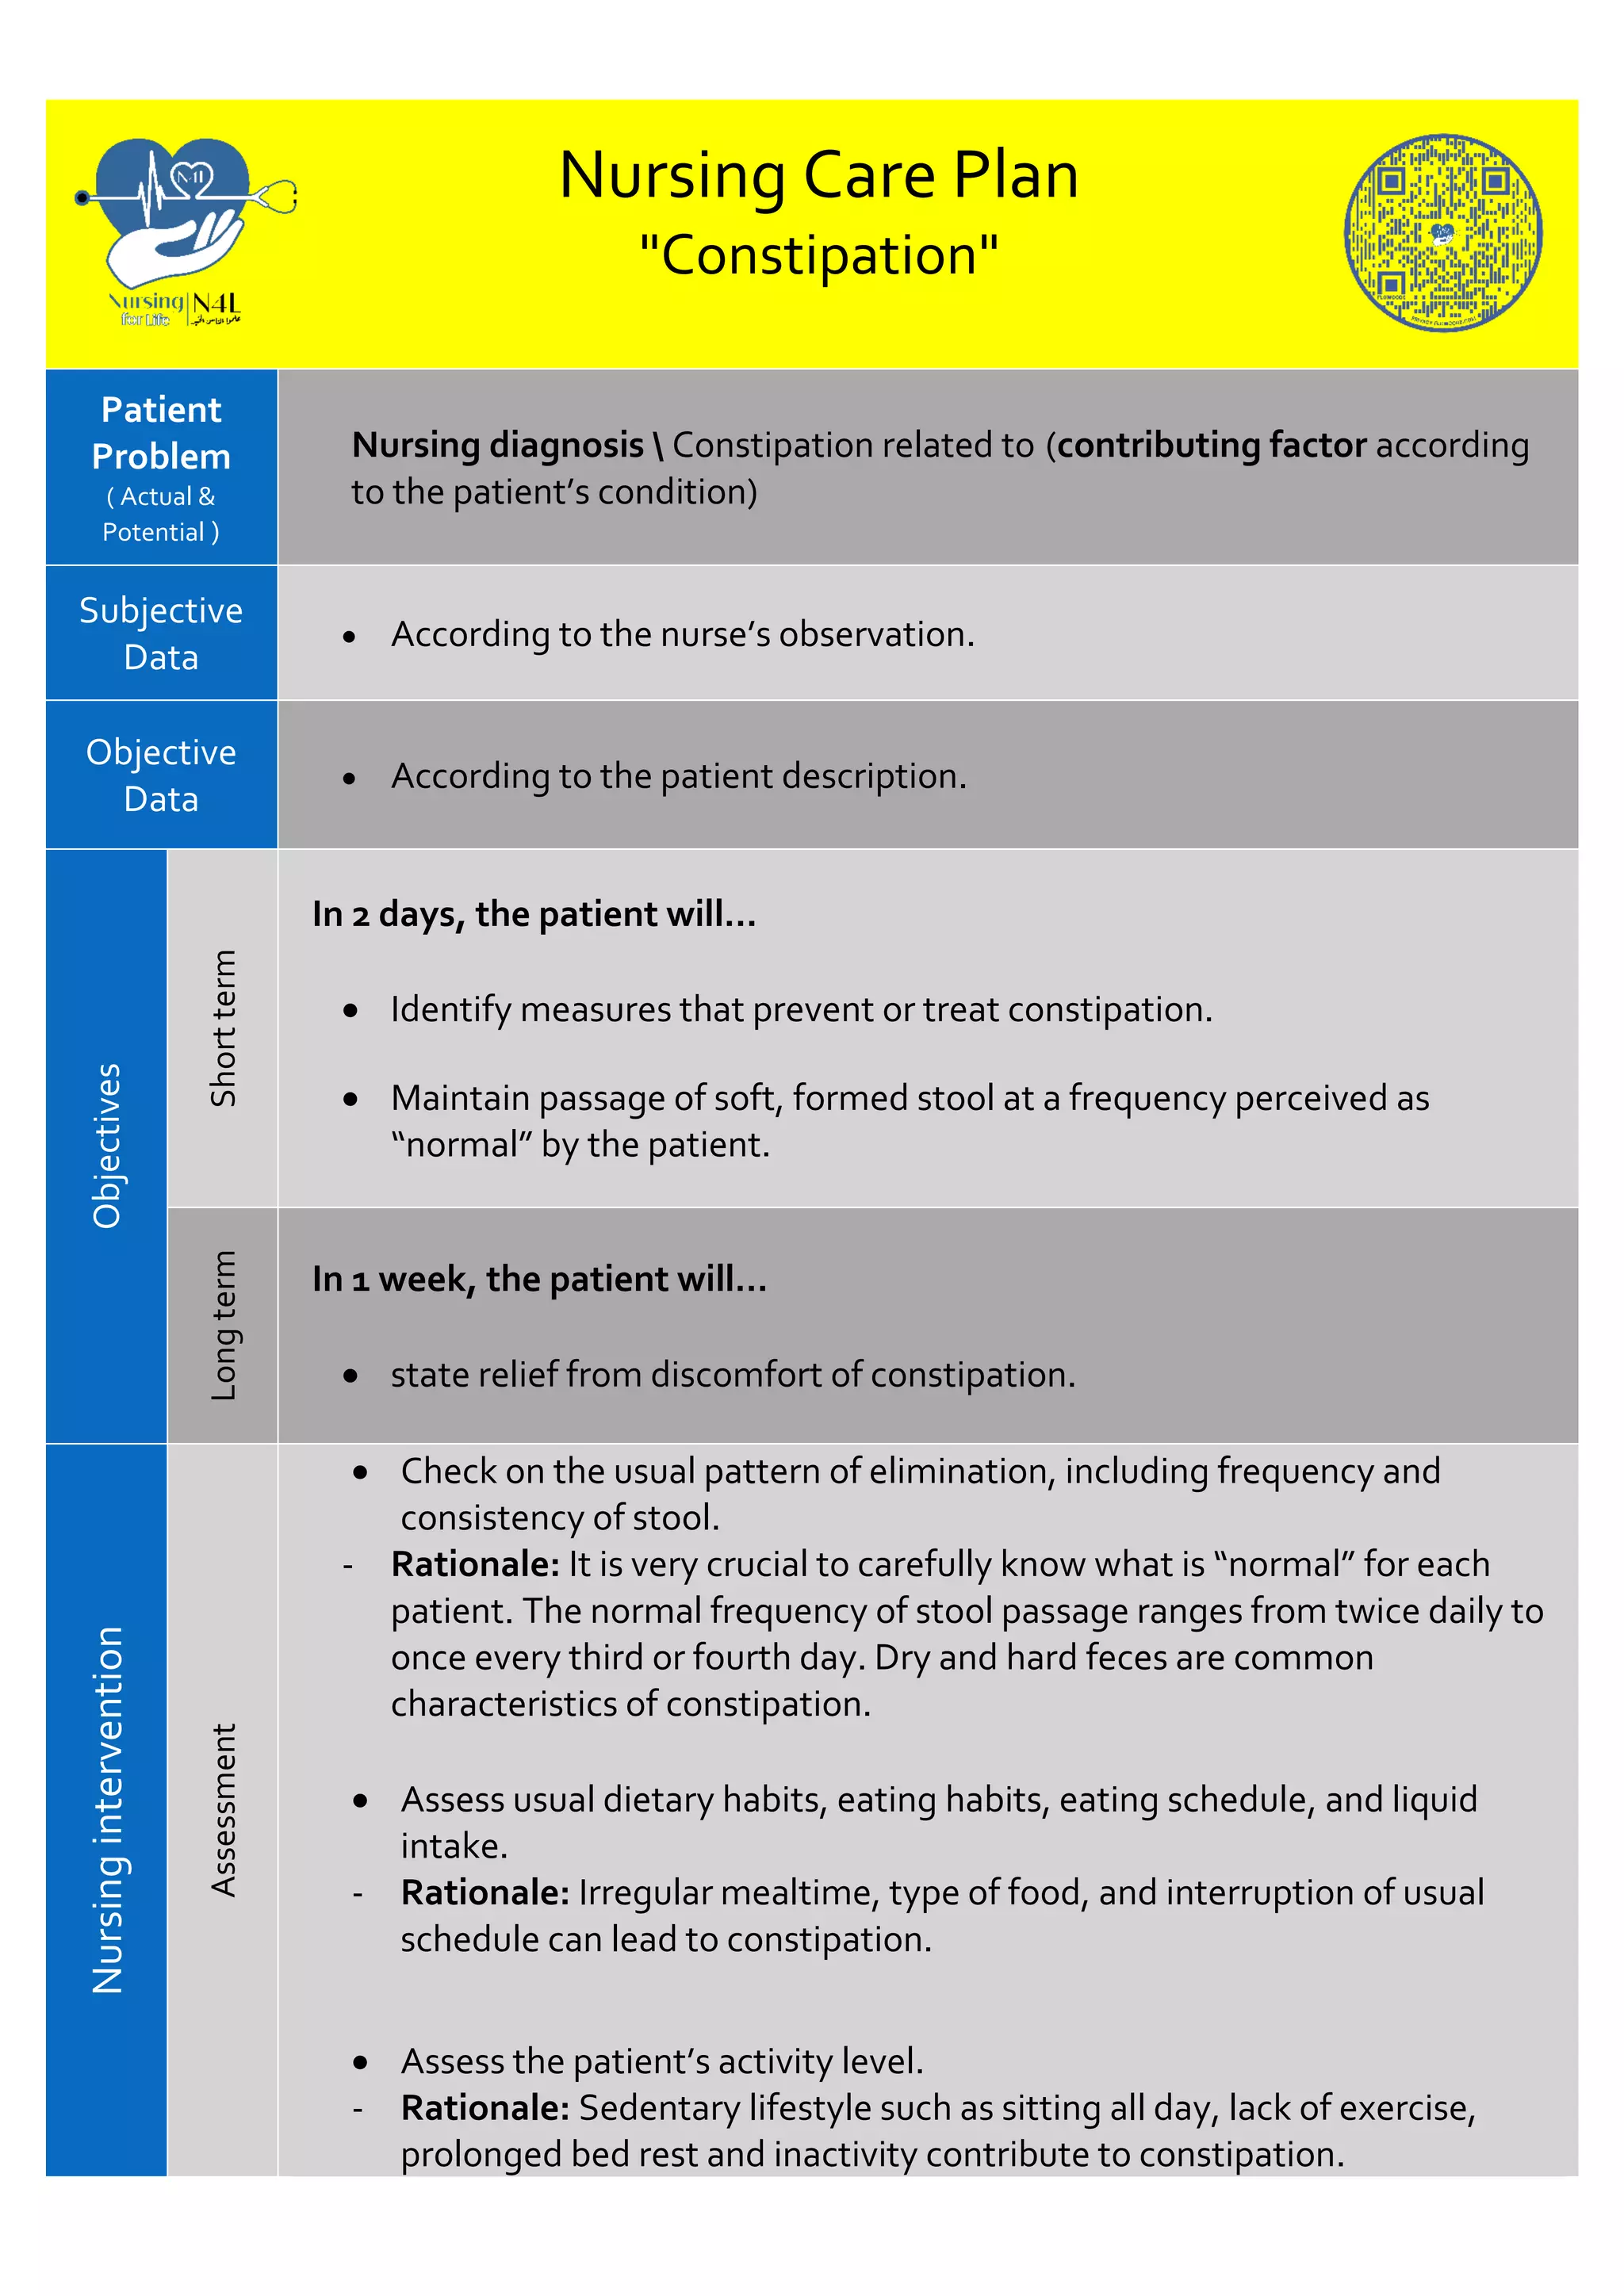
How we actually document and execute a Constipation Nursing Care Plan on the floor
Most nurses I see fumble through these care plans because they treat them like homework assignments instead of living documents. The real problem isn't writing one correctly. It's knowing what to adjust when the standard interventions don't move the needle within 48 hours. A proper plan starts with assessment, not interventions. You document bowel movement frequency, stool consistency using the Bristol Stool Scale, abdominal distension, patient-reported discomfort level, and dietary/hydration history. If you skip the assessment section, you're just guessing at interventions. I had a patient on post-op day four who hadn't passed stool since surgery. Standard protocol called for senna and plenty of fluids. I checked the chart more closely and noticed he was on a high-dose opioid analgesic schedule. The senna alone wasn't touching it. What actually moved things was adding a scheduled bisacodyl suppository and coordinating the timing with his pain medication doses rather than waiting for PRN requests. That took us from day four to day five of intervention before results, instead of day seven when we'd have just kept escalating orals.
Assessment priorities most people miss
Beyond the Bristol Scale, you need to track medication history. Opioids, anticholinergics, iron supplements, calcium channel blockers, and diuretics are the usual suspects. A surgical patient on PCA morphine will almost always need a proactive bowel regimen, not a reactive one. Documenting this connection in your nursing diagnosis saves time later when you need to justify interventions to the provider. Fluid intake documentation is another weak spot. Patients often report drinking enough water but actually sit at 800 to 1200 milliliters per day. I started charting estimated daily fluid intake directly in the notes instead of just marking "patient denies dehydration." That single change made my handoff notes significantly more useful.
Intervention sequencing that actually works
Non-pharmacological measures come first, but they need to be specific enough to evaluate. "Increased ambulation" means nothing without a target. I use documented steps or a set duration, like twenty minutes of hallway walking every shift. "Dietary fiber" is equally vague. I specify goals like thirty grams of fiber daily with examples of what that looks like — two prunes, half a cup of bran cereal, a medium apple with skin. Pharmacological interventions follow a ladder. Bulk-forming laxatives like psyllium are gentle but require adequate fluid intake or they can worsen impaction. Osmotic agents like polyethylene glycol work within twelve to twenty-four hours in most patients. Stimulant laxatives like senna or bisacodyl are faster but cause cramping. Saline laxatives like magnesium citrate are reserved for more stubborn cases and carry electrolyte risks in renal patients. I keep a chart at the nurses' station that maps intervention to onset time. It cuts down the back-and-forth with providers when ordering additional medications.
Get the Full Details

Documentation pitfalls to avoid
The biggest mistake I see is documenting outcomes that don't match the interventions. Writing "patient reports improved bowel regularity" when you only administered one dose of senna at 0800 and evaluated at 1000 is a red flag during chart audits. Bowel regimens typically need twenty-four to forty-eight hours to show consistent results. Match your evaluation timeframe to the pharmacology. Another issue is neglecting patient education documentation. If you recommended increased fluids but didn't document what teaching you provided, you have no record of whether the patient understood or agreed. I use a simple checklist in my notes: discussed dietary changes, reviewed medication schedule, demonstrated stool consistency scale, confirmed understanding. It takes about thirty seconds to document and protects you if a complication arises.
When the plan falls apart
There are scenarios where even a well-documented care plan hits a wall. Fecal impaction won't resolve with oral laxatives alone. You need disimpaction first, usually digital or with enemas, before any standard regimen makes sense. Patients with underlying conditions like hypothyroidism or diabetes with autonomic neuropathy often need physician involvement for persistent constipation. The nursing care plan should flag these situations clearly rather than continuing interventions that aren't working. Older adults are particularly tricky. Their bowel motility slows naturally, and polypharmacy compounds the problem. I've seen care plans fail because nobody addressed the interaction between a patient's antihypertensive, antidepressant, and iron supplementation. The constipation wasn't a standalone issue. It was a medication side effect cluster that required the provider to reconsider the regimen.
Putting it together
A functional Constipation Nursing Care Plan is iterative. You assess, intervene, re-assess, and adjust. The documentation should reflect that cycle, not just a static list of orders. When you write it as a dynamic plan with clear timelines and realistic expectations, it becomes useful for the whole care team instead of just another chart requirement.




