What a Cord Stimulator Psychological Evaluation Actually Involves
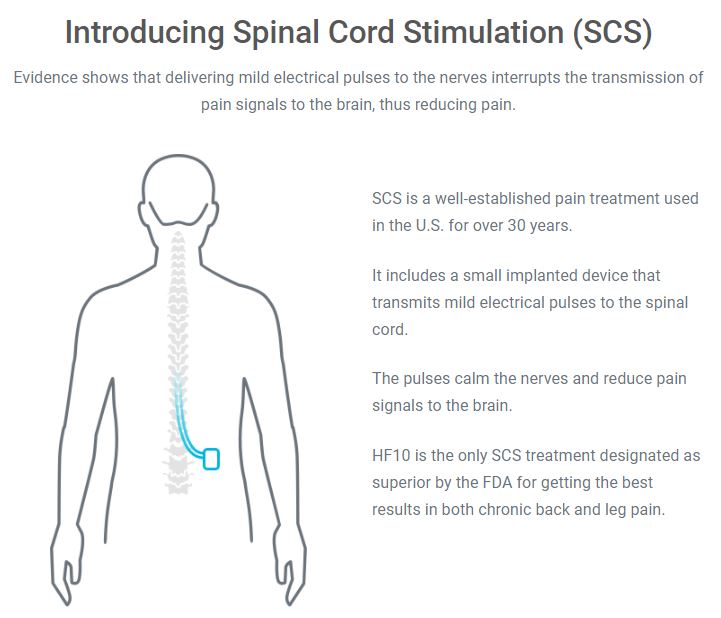
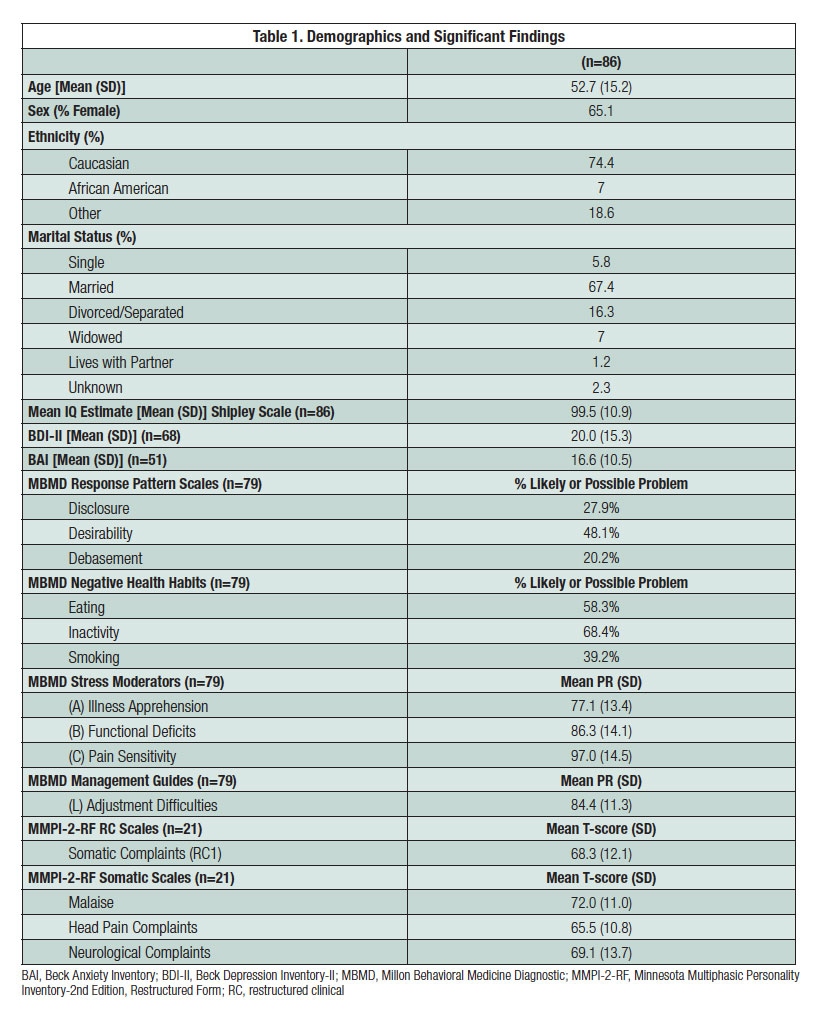
A cord stimulator psychological evaluation is a clinical assessment done before implanting a spinal cord stimulation device. It is not a pass/fail IQ test. It is a structured screening for factors that predict whether someone will actually benefit from the treatment or end up with worse outcomes. Most clinics use a combination of standardized questionnaires and a brief clinical interview. The usual batteries include the MMPI-2 or MMPI-2-RF, the BDI-II for depression screening, the GAD-7 for anxiety, and sometimes the Pain Catastrophizing Scale. These tools are chosen because they correlate with treatment adherence, placebo response magnitude, and risk of symptom amplification after implantation.
Cord Stimulator Psychological Evaluation: What You Actually Need to Know
I have gone through this process twice in different contexts, once as a patient advocate reviewing cases and once when I needed one myself for a clinical trial. The thing most people get wrong is assuming it is about proving you are stable enough to handle a surgery. It is not. It is about predicting whether chronic pain expectations align with what the device can actually deliver. Spinal cord stimulation works best for radicular pain, not axial back pain. The psychological evaluation helps separate patients whose pain generators are clearly neuropathic from those whose suffering is maintained by central sensitization without a clear peripheral driver. Both groups report high pain scores. Only one group typically responds well to SCS. Here is a practical breakdown of how it typically works.
Step one is the questionnaire battery. You will spend about 45 minutes to an hour completing the instruments. They are not short. The MMPI-2 runs 567 items. The R version is shorter at 335 but still substantial. Do not rush through them. Response style matters more to clinicians than any single score. If you answer too positively, the validity scales will flag it. If you answer inconsistently, you get an invalid profile and they send you back for a retest. Step two is the clinical interview. This is usually 30 to 45 minutes with a psychologist or psychiatrist. They ask about your pain history, previous treatments, employment status, ongoing litigation or compensation claims, and your specific goals for the implant. Be direct. Saying you expect the device to eliminate 90 percent of your pain and return you to your pre-injury job will raise red flags. Saying you want better functional capacity and a reduction in opioid dependence reads as realistic. The evaluation produces a written report. It typically includes a summary of findings, a diagnostic impression, risk factors, and a recommendation: proceed, proceed with caution, or do not proceed. The recommendation is advisory. The final implant decision rests with the pain specialist and the surgical team.
Get the Full Details

One edge case I ran into that most guides do not mention involves patients with comorbid PTSD. A significant subset of chronic pain patients have untreated or poorly treated trauma histories. The standard batteries will pick up elevated trauma-related scales, but they do not always differentiate between baseline PTSD symptoms and acute exacerbation triggered by pain flares. I encountered a case where a patient was flagged as high-risk based on elevated hypervigilance scores that turned out to be entirely pain-driven, not trauma-driven. The workaround was straightforward: I requested that the evaluating psychologist administer the PCL-5 separately and time-stamp the results against the patient's current pain diary. The correlation analysis showed the hypervigilance tracked directly with pain days, not with trauma reminders. The recommendation shifted from do not proceed to proceed with caution and concurrent trauma-informed therapy. Another thing people miss is the impact of medication state on testing. Benzodiazepines and certain gabapentinoids can flatten response patterns on self-report inventories. If you take these medications, mention it before the evaluation. The clinician can adjust interpretation or defer testing until levels are stable. Skipping this step leads to false negatives on depression screening, which then gets misread as emotional resilience when it is actually sedation masking symptoms. Cost and access vary by region. In the United States, a full psychological evaluation typically runs between 400 and 800 dollars if billed to insurance. Without insurance, private evaluators charge 600 to 1,200 dollars depending on complexity. Turnaround time for the report is usually 10 to 20 business days. Some centers have in-house psychologists who deliver results within a week.
If you are preparing for one, bring a current medication list, a timeline of prior interventions including dates and outcomes, and a brief written summary of your primary functional limitations. The more concrete your documentation, the less the evaluator has to guess, and the more accurate the recommendation will be. There are limitations to this process that deserve blunt acknowledgment. Psychological evaluation does not predict device success with high accuracy. The best published predictors for SCS outcome remain the presence of radicular-predominant pain, prior successful trial stimulation, and absence of widespread comorbid pain conditions. The psychological screen adds modest predictive value at best. It is more useful for risk mitigation than for outcome forecasting. Patients should not interpret a favorable evaluation as a guarantee of success, nor a cautious one as a definitive barrier. If you are denied or flagged as high-risk, the typical pathway is targeted treatment of the identified comorbidity followed by reassessment. Depression treated to remission, untreated sleep apnea managed, or substance use in recovery all change the risk profile over time. Re-evaluation after six to twelve months of stabilized treatment is common and usually straightforward.