Reading Coronal Brain MRIs Without Losing Your Mind
Most people learn axial first, then sagittal, then finally deal with coronal like it's some kind of punishment. That is backwards. Coronal is actually where a lot of things become obvious once you stop fighting it.
When I first started reading neuroimaging, I treated coronal as just another orientation to get through. Then I ran into a case that changed how I approach it entirely. A glioma in the insular cortex was basically invisible on axial and barely suspicious on sagittal. On coronal, it lit up like a Christmas tree because you can see the insula in cross-section with the Sylvian fissure radiating around it. That taught me that coronal is not optional. It is the plane that catches what the others miss.
Coronal Brain Mri Anatomy: What You Actually Need to See
Let us talk about what the coronal plane gives you that the other two do not, and what you will routinely mess up if you are not paying attention.
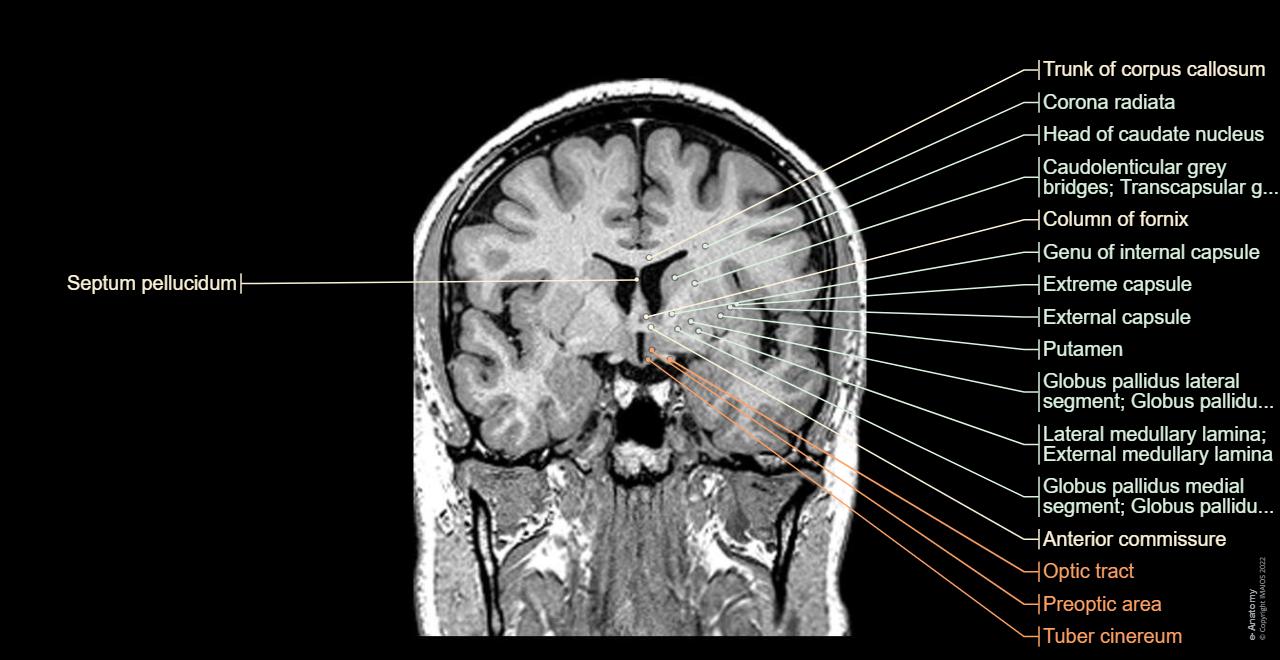
At the level of the lateral ventricles, you should be identifying the body of the lateral ventricle, the trigone posteriorly, and the temporal horn looping around. The caudate nucleus sits along the lateral margin of the frontal horn. If you cannot clearly distinguish the head of the caudate from the putamen at this level, you are going to have trouble elsewhere. The internal capsule separates them. Think of it as a thin V-shaped or curved white matter band. If you miss that landmark, everything else gets confusing.
The third ventricle is midline. The thalami sit on either side. The hypothalamus is anterior and inferior to the thalami. This is the level where you assess for mass effect causing shift. A subfalcine herniation is visible here as the cingulate gyrus getting pushed under the falx. I have seen residents miss this because they were so focused on the ventricles themselves that they did not check whether the cingulate was symmetric.
Moving inferiorly, the temporal horns are where things get tricky. They should be slit-like. If they are dilated, you have temporal horn enlargement, which is a sign of obstructive hydrocephalus or focal atrophy. The hippocampus curls around the inferior horn. You need to see the head, body, and tail. Asymmetry of the hippocampus between sides is one of those findings that looks subtle until you know exactly where to look. Normal hippocampal volume on coronal T2 is roughly 4 to 5 cm³ per side. If one side looks smaller and the signal is increased, mesial temporal sclerosis is a real possibility.
At the level of the basal cisterns, the midbrain should be visible with its characteristic shape. The cerebral peduncles are anterior. The interpeduncular fossa sits between them. The ambient cisterns wrap around the midbrain laterally. If you are looking at a lesion here, coronal gives you information about crural and ambient cistern involvement that axial simply cannot provide cleanly.
The posterior fossa on coronal is limited. You see the superior cerebellar hemispheres and the vermis at higher cuts, but the brainstem and lower posterior fossa structures are better assessed on axial and sagittal. Do not rely on coronal alone for posterior fossa pathology. It is not built for that.
What Goes Wrong When You Read Coronal Scans
The most common mistake I see is ignoring slice thickness and through-plane resolution. Coronal sequences are often acquired with thicker slices than axial. If you are using a 5mm coronal T1 without fat saturation, you are going to miss small lesions. I had a case once where a 4mm pituitary microadenoma was completely invisible on the initial coronal review because the technologist had set the slice thickness to 6mm and the gap to 2mm. The lesion sat in the gap between slices. We went back and re-imaged with 3mm slices and no gap. Found it immediately. That is not a rare problem. It happens constantly in busy practices where protocol selection is rushed.
Another issue is misidentifying normal variants as pathology. The arachnoid granulations along the superior sagittal sinus can look like focal defects in the bone or even masses. On coronal T1 they appear as well-circumscribed CSF-density lesions indenting the calvarium. They are benign. But I have seen reports calling them metastatic deposits because the reader did not recognize the appearance. The key is that they track with CSF on all sequences and do not enhance. If you are unsure, grab a FLAIR or post-contrast T1 and confirm.
Partial volume effect is another trap. When a structure is smaller than the slice thickness, the signal gets averaged with adjacent tissue. This is why thin-slice coronal imaging matters, especially for the hippocampus and the pituitary. The pituitary stalk should be midline and approximately 3mm in diameter. If it is thicker than that on coronal, you are looking at either infundibular enlargement or just partial volume from a thick slice. Re-measure on thinner slices before you commit to a diagnosis.
Practical Workflow for Coronal Interpretation
I read coronal in a specific order now. It is not the most elegant system but it catches things reliably.
First, I check symmetry. Left versus right. Anything obviously different gets flagged. This includes asymmetry of the ventricles, the hemispheres, the basal ganglia, and the sulcal pattern. Asymmetry is never normal until you prove it is.
Second, I trace the ventricular system from anterior to posterior. Frontal horns, bodies, trigones, temporal horns, occipital horns. Each should have a predictable shape and size. Any deviation triggers a closer look at the surrounding parenchyma.
Third, I evaluate the deep gray matter structures. Caudate, putamen, globus pallidus, thalamus. Signal abnormalities here are clinically significant. Hyperintensity in the thalamus on T2, for example, could be thalamic stroke, metabolic disturbance, or a low-grade tumor. The coronal plane helps you localize the exact nuclear group involved.
Fourth, I look at the white matter tracts. The internal capsule, external capsule, and claustrum should be identifiable. White matter disease shows up clearly on coronal T2 and FLAIR. Periventricular hyperintensities are easiest to appreciate on coronal because you can see their relationship to the entire ventricular perimeter at once. On axial, you only get a short segment at a time.
Fifth, I assess the extra-axial spaces. Subdural collections, subarachnoid space, and the basal cisterns. A chronic subdural hematoma that is isodense to brain on axial can be obvious on coronal because of the way it layers along the convexity. I found a case last year where the axial looked essentially normal. The coronal showed a thin crescentic collection along the entire hemisphere that was missed initially. The patient had been having headaches for months and nobody connected the dots until someone finally looked at the coronal reformats.
Limitations You Need to Accept
Coronal MRI has real limitations. Motion artifact is worse on coronal than axial in many cases because head movement in the anterior-posterior direction directly affects the coronal slices. Patients who cannot hold still will produce unusable coronal images more often than axial ones.
Spatial resolution is typically lower on coronal than on high-resolution axial sequences. If you need to see fine detail, like the inner ear structures or the optic nerves, axial high-resolution imaging is superior. Coronal is useful for the optic nerves but not as detailed as dedicated orbital axial slices.
The sella turcica and pituitary are best imaged coronally, yes, but the pituitary infundibulum can appear artificially thickened if the slice is not perfectly aligned with the coronal plane of the stalk. I have seen several cases where a presumed pituitary stalk thickening turned out to be oblique slicing. Always verify with sagittal images before calling stalk pathology.
For posterior fossa evaluation, coronal is inadequate. Cerebellar tonsillar ectopia, fourth ventricle obstruction, and brainstem lesions are all better assessed on axial and sagittal. Do not skip those planes because you spent extra time on coronal.
There is also the issue of flow artifacts. Coronal images often show flow voids or signal loss in theCircle of Willis and major venous sinuses that can be confused with pathology. The superior sagittal sinus should be bright on T1 and dark on T2 due to flow. If it is bright on T2, that is thrombosis. But normal variants of sinus flow can mimic abnormality on certain sequences. I learned this the hard way when I reported a suspected sagittal sinus thrombosis that turned out to be normal slow flow on a repeated scan. The follow-up MRI with faster flow-sensitive sequences cleared it up.
If you are working with older scanners or patients who cannot tolerate long scans, coronal acquisition time is often the first sequence to get cut or compromised. A 3-minute coronal T2 is not the same as a properly acquired 8-minute one. Do not trust rushed protocols. Ask for a repeat if the images look noisy or if the slice thickness is questionable. This is not pedantry. It is how you avoid missing real pathology.