Understanding Corporate Practice of Medicine in 2022: What Actually Matters
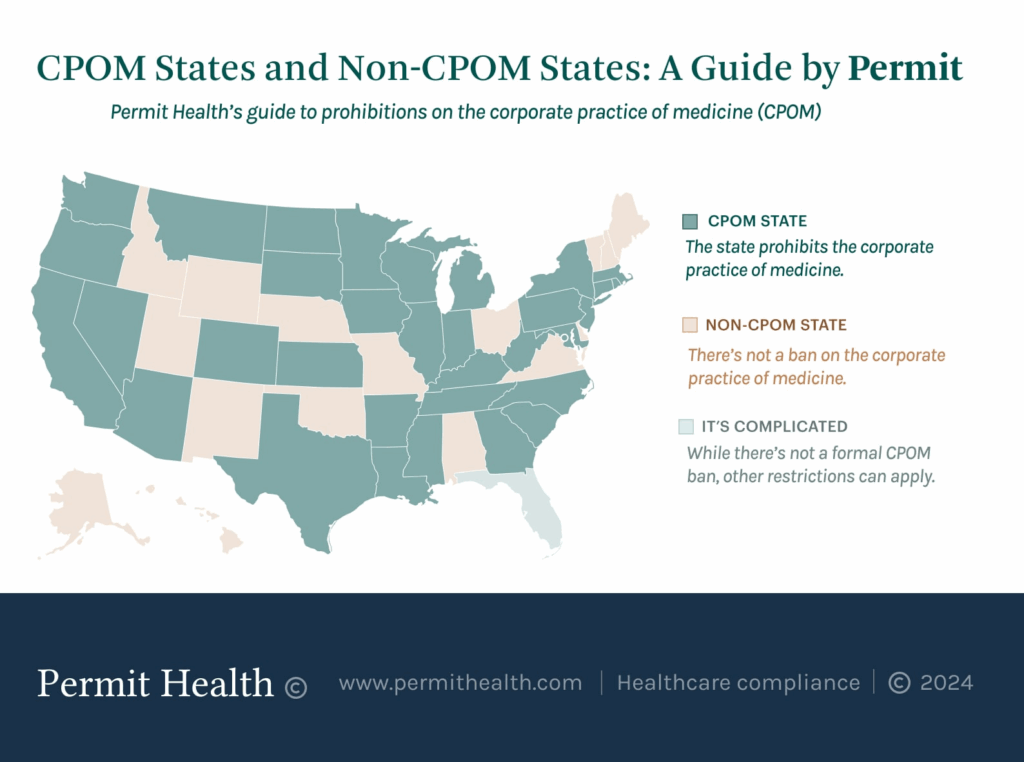
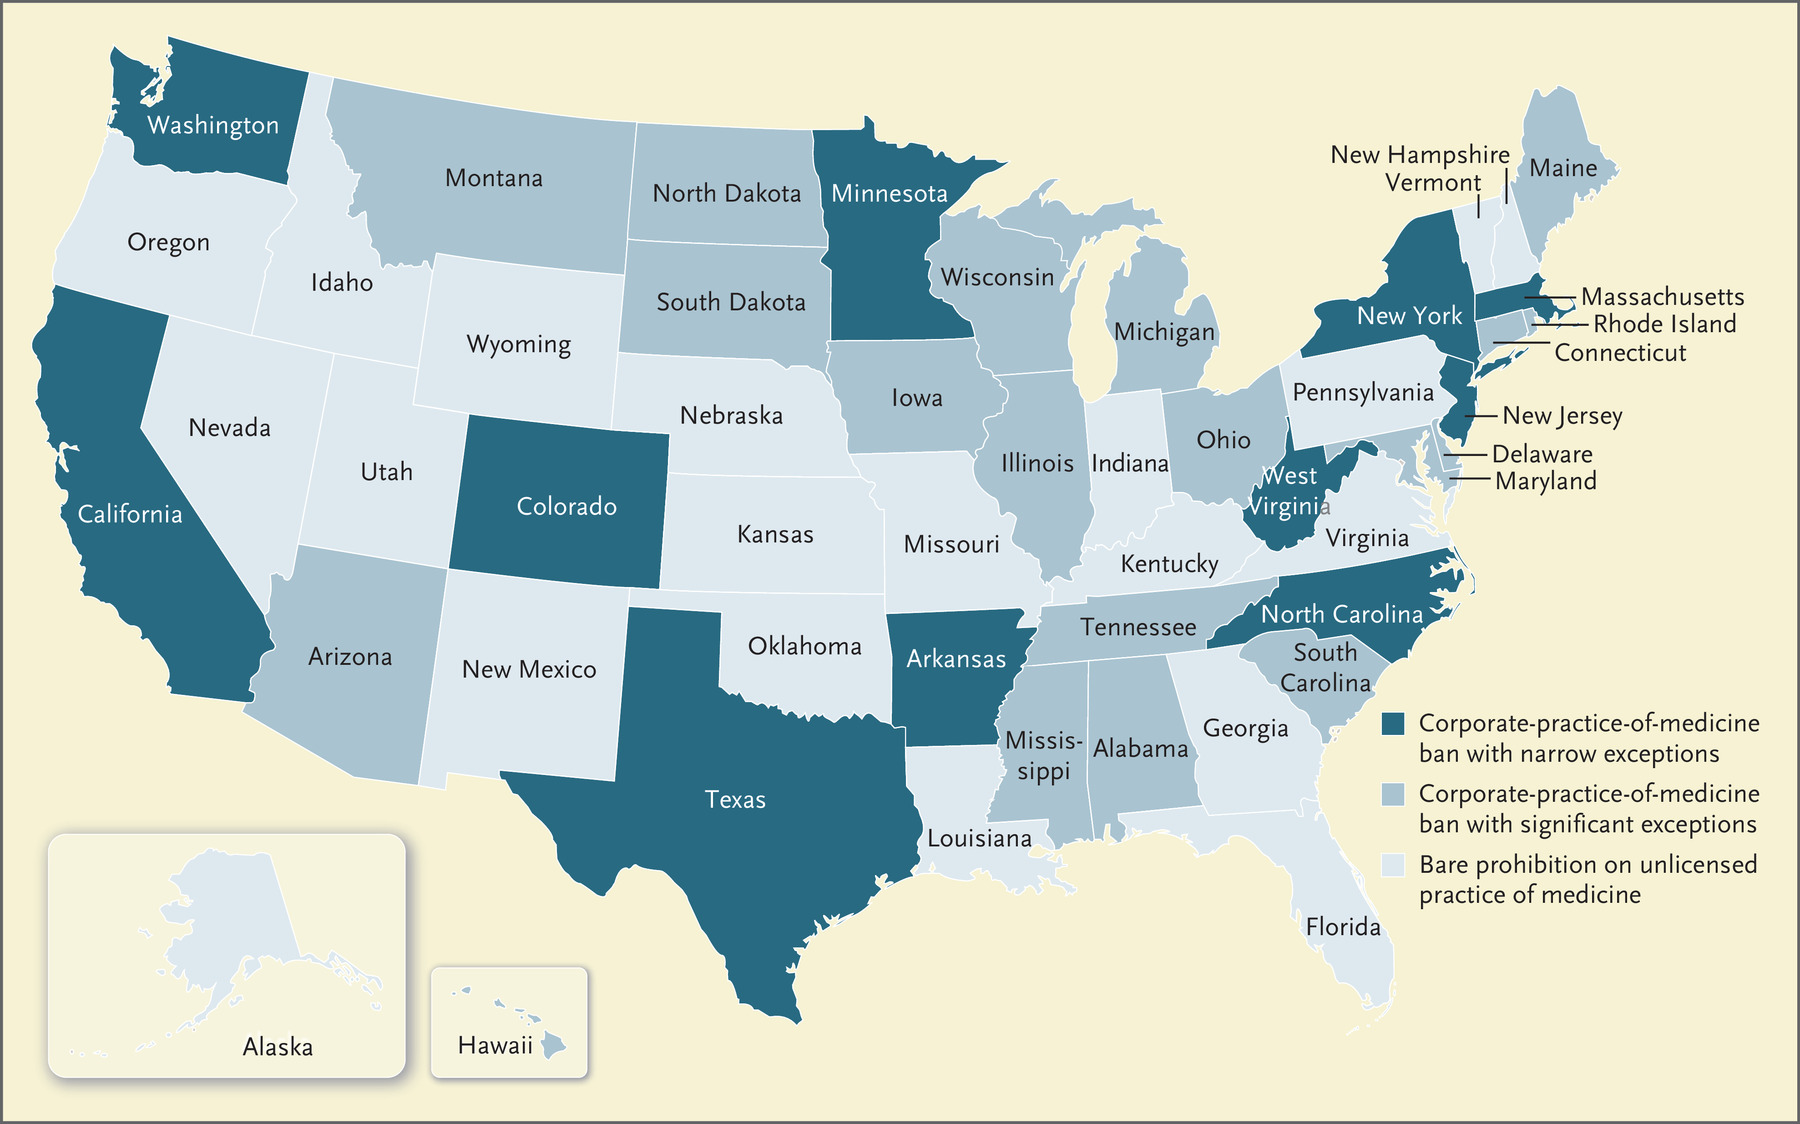
The Corporate Practice of Medicine doctrine is a patchwork of state-level restrictions that prevent corporations from employing or controlling licensed physicians. It exists in some form across roughly half the states, and the landscape shifted noticeably in 2022 with new attorney general opinions and court rulings that clarified what counts as "control." If you're running an AMS or a corporate medical group, ignoring this is how you get sanctioned, fined, or lose your license. I need to be upfront about what this doctrine actually blocks. It is not a blanket ban on physicians working for companies. The restriction is specifically about who makes clinical and operational decisions. A corporation cannot direct a doctor's medical judgment, set fees based on physician productivity in a way that constitutes control, or hire and fire at will without physician oversight. The line between permissible management and impermissible control is where most people get tripped up. Here is how the states broke down heading into 2022. California is the strictest. Any corporate entity practicing medicine there faces immediate scrutiny. Colorado followed closely with enforcement actions that targeted non-physician owners in dermatology and dermatopathology arrangements. Texas, Florida, and New York have their own versions with varying degrees of teeth. Some states like Illinois and Michigan enforce the doctrine through their medical boards rather than through explicit statutes. A few states barely enforce it at all, which does not mean it does not exist there.
The 2022 updates came from two directions. State attorneys general in several jurisdictions issued formal opinions addressing whether physician assistants and nurse practitioners could serve as the "corporate" owners in structures that used to require a physician-only entity. Some said yes under specific conditions. Others drew hard lines. Courts also weighed in, particularly around the definition of "practice of medicine" itself. If your state has not updated its guidance since 2020, you are already behind. I learned this the hard way a few years back when I structured a dermatology practice in a mid-Atlantic state with a standard management services organization agreement. The CPA running the MSA was non-physician. We thought we were fine because the physicians retained all clinical decision-making authority. Then the state medical board asked for a copy of our operating agreement to confirm that the MSA could not directive any clinical matters. Turns out our agreement had a clause about "quarterly performance reviews tied to clinical quality metrics" that the board interpreted as indirect control. I rewrote the language to separate outcome measurement from operational direction. That cost me about three weeks and a revised $8,000 legal bill. Now I run every agreement through a compliance checklist before anything gets signed.
How to Navigate Corporate Practice Restrictions in Practice
Start by identifying your state's exact rule. The doctrine goes by different names in different places. Some call it the corporate practice doctrine, others reference it through their unlicensed practice statutes. A handful of states codify it. Most do not. That means you need to read board opinions, attorney general letters, and relevant case law, not just the statute. Next, structure your entity correctly. In strict states, you generally need a professional corporation or professional association owned entirely by licensed physicians in the relevant specialty. The non-physician ownership piece is where the doctrine bites. If you need outside capital, a management services organization can handle billing, HR, facilities, and procurement. But the MSA cannot control clinical decisions, hiring of physicians, or fee-setting that effectively determines physician compensation in a controlling manner. Write your agreements with that line in mind. I use a simple test on every contract: if the non-physician party can fire a doctor for refusing a protocol, the agreement is non-compliant. Period. Compensation models should be based on work actually performed, not on productivity targets that function as de facto employment terms. RVU-based pay is acceptable in most states, but you need language that makes clear the physician controls their own patient volume and that compensation adjustments are not tied to clinical judgment decisions.
Get the Full Details

Physician oversight committees are your best structural defense. Establish a medical director or clinical oversight committee with real authority. Document their meetings. The board will ask for proof that physicians are running the practice, not just named on paper. I keep a simple log: meeting dates, attendees, topics discussed, and any clinical decisions made. This takes about twenty minutes a month and has saved me from two audit findings. Watch out for the assistant loophole. Some states allow PA or NP-owned entities to operate where physician-only ownership would be required. This varies significantly. In 2022, several states expanded this allowance, while others explicitly closed it. If you are relying on this pathway, verify it with a current opinion, not a statute from five years ago. The rules change faster than most people realize.
Common Pitfalls That People Keep Making
The first and most frequent mistake is assuming that having a medical director on paper is enough. Boards look at substance. If the medical director never actually meets, never votes on clinical policies, and signs off on everything the MSA sends over, you do not have a medical director. You have a signature factory. I have seen this result in cease-and-desist orders in at least three states within a two-year window. The second pitfall is the marketing and branding trap. When a corporate entity owns the practice name and controls the patient acquisition funnel, some boards view that as economic control. I recently advised a group that changed their naming structure to use a physician-group brand instead of the corporate parent's brand. This alone reduced their compliance risk significantly because it removed the appearance of corporate oversight of patient relations. A third issue is cross-state operations. If you operate in multiple states, each one has its own version of the doctrine. A structure that works in one may be illegal in the next. I learned this the hard way when a client expanded from a compliant Texas structure into Oklahoma without adjusting the ownership. The Oklahoma medical board flagged it within six months. You need state-specific entity structures, not a one-size-fits-all approach.
There is also the telemedicine angle that most people overlook. Providing telehealth services across state lines can trigger corporate practice concerns if the delivering entity is a corporation in one state and the patient is in another. Some states have explicit telemedicine exemptions. Many do not. Check before you start cross-state practice.
What the 2022 Landscape Means Going Forward
The trend is toward more enforcement, not less. States are realizing that dermal, pain management, and psychiatric AMS models are generating significant revenue outside traditional physician ownership. Several states have moved to close the NP and PA loophole. Others have issued new opinions restricting how productivity-based compensation can be structured. If your practice model was built on a 2019 or earlier framework, it may already be non-compliant in your state. The practical reality is that compliance is an ongoing process, not a one-time setup. I recommend running through a formal compliance review at least annually. A good review takes about four hours for a single-state practice and costs between $2,000 and $5,000 depending on complexity. The alternative is waiting for a board to notice something you missed. That is far more expensive. If you are starting a new practice, engage counsel who specializes in healthcare corporate compliance before you file any entities. General business attorneys will miss the nuances. I have watched too many practices get structured correctly on paper and then fail a board review because the actual operating procedures contradicted the organizational documents. The paperwork needs to match the workflow. Every time.
The doctrine is not going away. It has survived decades of challenges and shows no sign of disappearing. The states that enforce it most aggressively tend to be the ones with the largest cosmetic and dermatology markets. If you operate in those spaces, the compliance burden is real and it is getting heavier. Plan for it accordingly.



