Understanding Clinical Evaluation for Numbness and Tingling
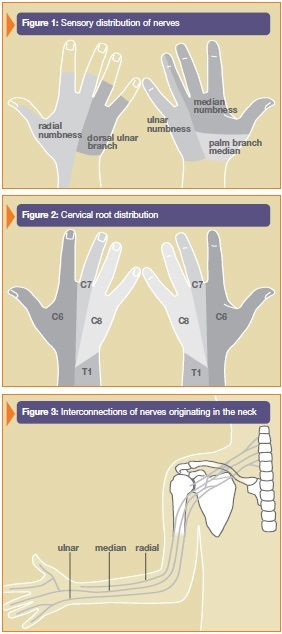
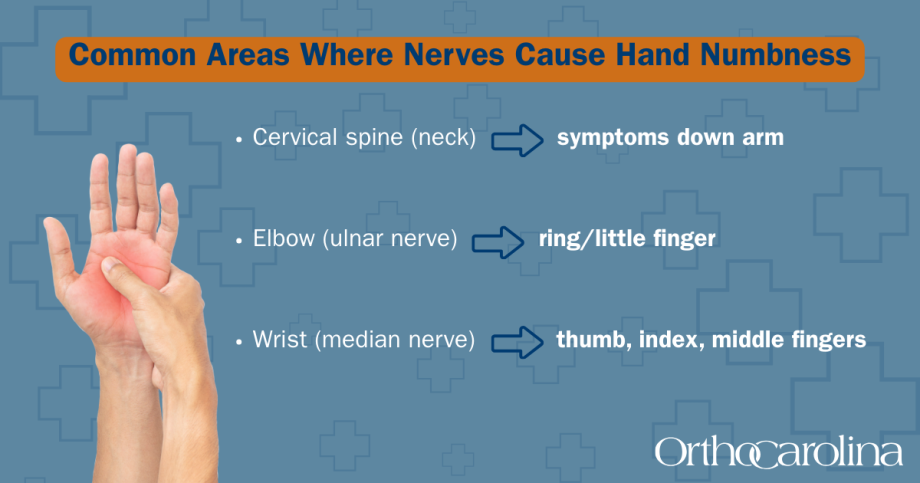
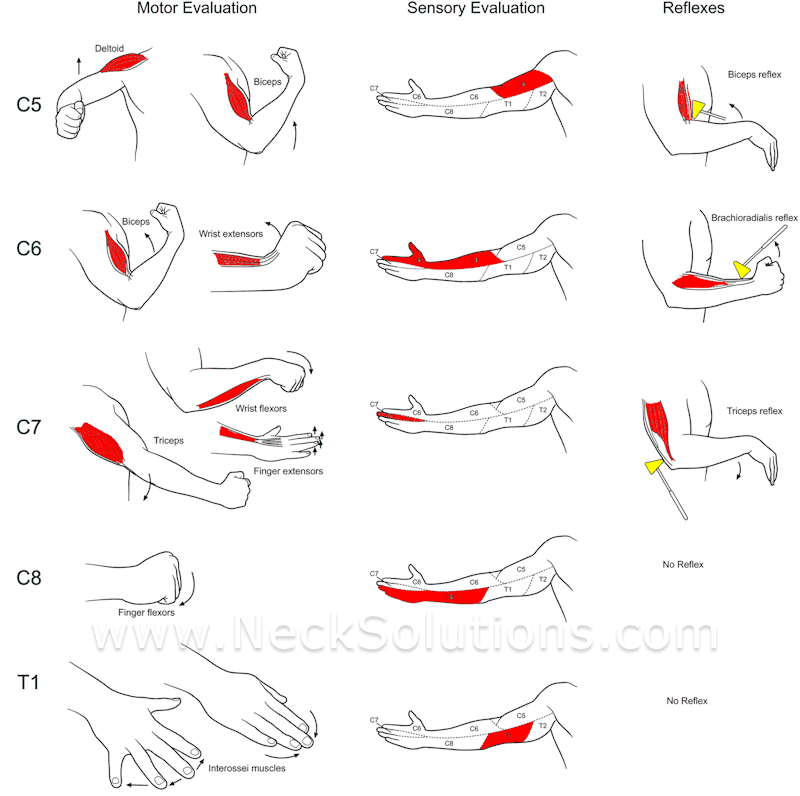
There is no single standardized test called a Cp Exam For Numbness And Tingling in mainstream neurology or primary care practice. What exists is a series of bedside assessments that clinicians use to map sensory deficits, identify dermatomal patterns, and determine whether paresthesia originates from peripheral nerve compression, radiculopathy, or central nervous system pathology. If you have been searching for a formal certification or single proprietary exam by that exact name, you will likely come up empty. The terminology sometimes circulates in online forums or alternative medicine spaces, but it does not correspond to anything recognized by the American Academy of Neurology or standard clinical guidelines. When a patient presents with complaints of numbness or tingling, the examination begins with a focused history. The location matters enormously. Are the symptoms symmetric or asymmetric? Do they follow a glove-and-stocking distribution, which typically points toward peripheral neuropathy, or do they map to a specific dermatome, suggesting nerve root involvement? I once evaluated a construction worker who reported tingling in his left hand that worsened at night. The pattern was not random. It followed the ulnar distribution precisely, and a simple Tinel sign at the elbow reproduced his symptoms within seconds. That single maneuver, combined with two-point discrimination testing, confirmed cubital tunnel syndrome without requiring an MRI. The whole assessment took approximately eight minutes. The sensory examination itself involves several tools. Light touch is tested with a cotton wisp or monofilament. Pinprick sensation assesses small fiber function using a safety pin or neurotip. Vibration perception is checked with a 128 Hz tuning fork placed over bony prominences like the medial malleolus or distal thumb. Temperature discrimination, though less frequently used in routine practice, can be evaluated with objects at different temperatures. Pattern recognition testing, where the clinician writes numbers or letters on the patient's palm and asks them to identify the character by touch, evaluates cortical sensory function.
Common Pitfalls Beginners Miss
One of the most frequent errors I see is testing sensation only on the palmar surface of the fingers when evaluating median nerve function. The dorsal aspect, particularly the distal phalanx, is also innervated by the median nerve and should be included. Another mistake is comparing only the affected side to the unaffected side without establishing a normal baseline on the unaffected side first. Sensation can vary significantly between individuals, so the contralateral limb serves as the internal control. A more subtle issue involves the distinction between paresthesia and dysesthesia. Paresthesia refers to abnormal spontaneous sensations like tingling or pins and needles. Dysesthesia is an unpleasant abnormal sensation, often described as burning or painful, even to stimuli that are not normally painful. Confusing these two can lead to misclassification of the underlying mechanism. Burning dysesthesia in a dermatomal pattern suggests neuropathic pain and may warrant different treatment than purely sensory paresthesia without pain components.
Limitations and When to Refer
Bedside sensory testing has well-defined limitations. It is subjective by nature, relying entirely on patient response. Children, elderly patients with cognitive impairment, or individuals with language barriers may provide unreliable answers. The examination also lacks quantitative precision. Two-point discrimination thresholds can vary between testers, and vibration perception diminishes with age independently of any pathological process. A 60-year-old may have reduced ankle reflexes and decreased vibration sense at the toes without having any treatable condition. When the clinical picture is unclear, or when symptoms progress despite conservative management, referral for electrodiagnostic studies is appropriate. Nerve conduction studies and electromyography can localize the level of nerve injury with far greater precision than bedside testing alone. MRI of the spine or brain may be indicated if central causes are suspected. I generally recommend imaging when there are red flag features such as bilateral symptoms with bowel or bladder dysfunction, progressive weakness, or a history of malignancy. These situations rarely resolve with observation. The bottom line is that evaluating numbness and tingling requires a systematic approach rather than a single definitive exam. The clinical assessment guides further testing, but it does not replace it when the diagnosis remains uncertain. Any claim that a particular Cp Exam For Numbness And Tingling provides complete diagnostic certainty is misleading. Real practice is messier than that, and the skill lies in knowing when the bedside examination is sufficient and when additional investigation is necessary.
Get the Full Details