Speech Therapy Billing Is a Pain, But You Figure It Out
I've been doing this long enough to know that every therapist eventually hits the wall when they need to pick the right CPT codes for speech therapy and find themselves staring at a spreadsheet instead of a patient. The codes aren't the problem. The problem is the modifiers, the documentation requirements, and the payer-specific rules that change every year without warning. Let me just lay out what actually works before getting into the weeds.
Cpt Codes For Speech Therapy — The Usual Ones
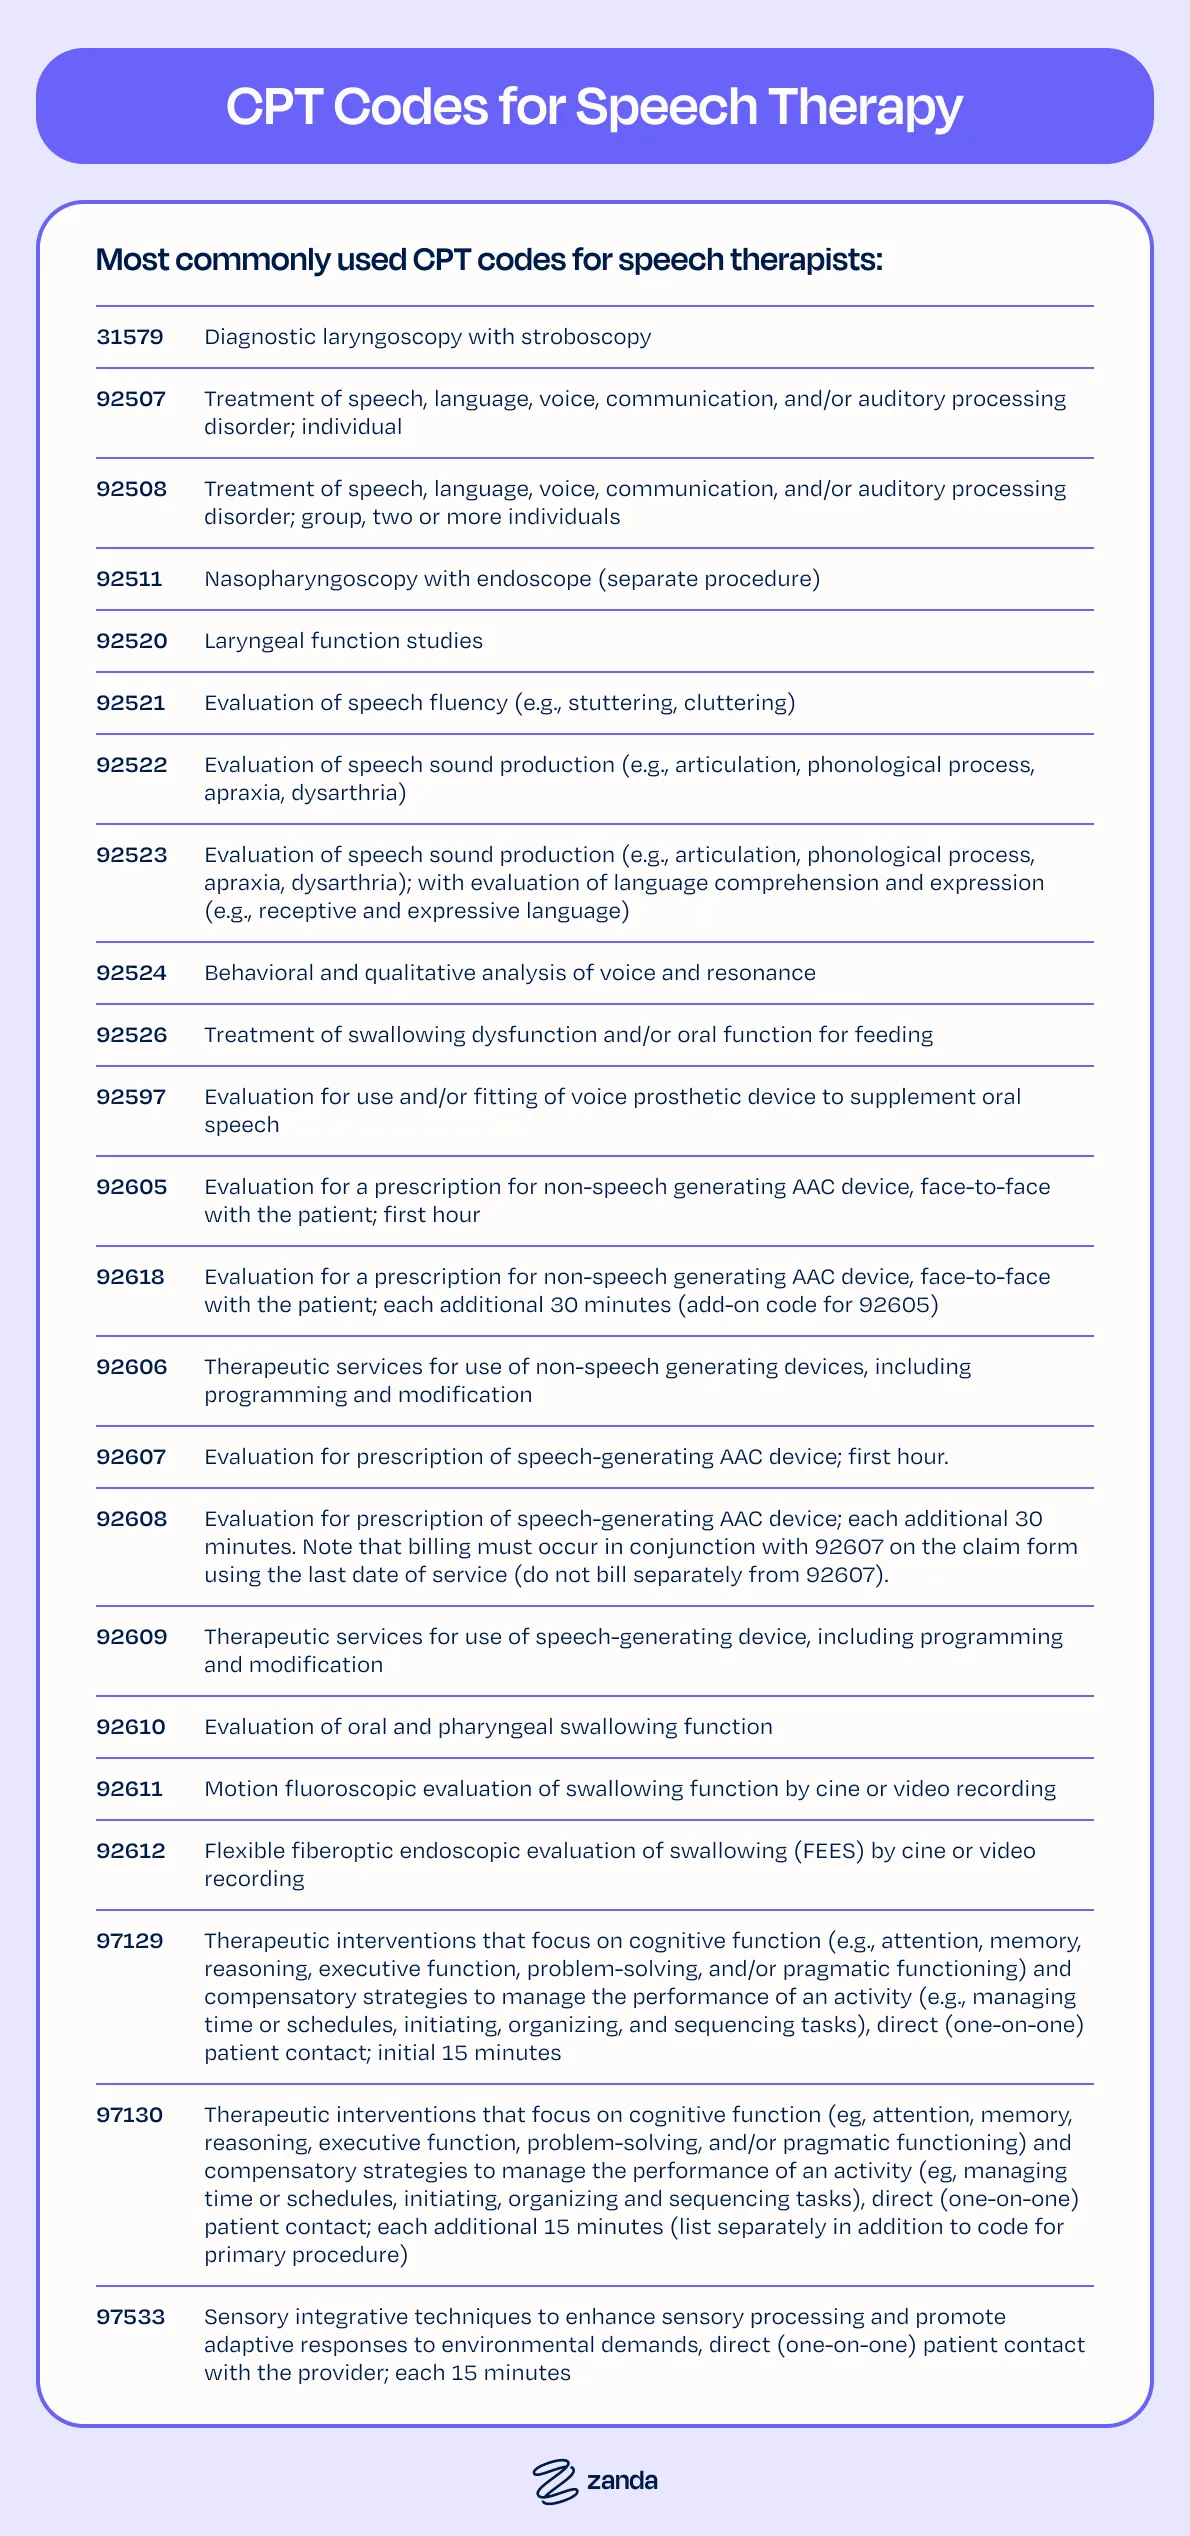
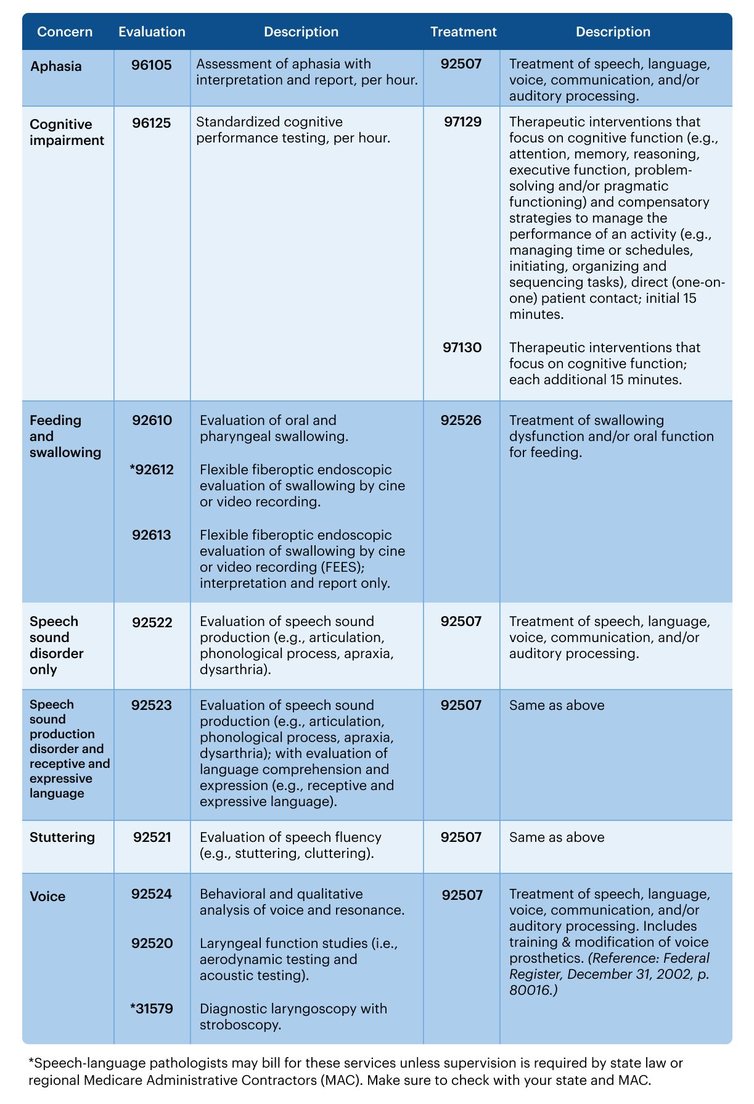
Here are the codes you're going to use most of the time. I'm not going to rank them by popularity because that's nonsense. I'm just listing what shows up in my notes: 92507 — This is the big one. Therapeutic procedures for speech, language, voice, or fluency. Evaluation and/or treatment. It requires one-on-one contact with the patient. You bill in 15-minute units. If you spend 23 minutes, you bill two units. If you spend 38 minutes, you bill three units. The quarter-hour rule applies here. Simple enough until a payer decides they only reimburse for whole minutes instead of the standard 4-minute threshold, which has happened more than once in my experience. 92508 — Oral rehabilitation for speech articulation. This one gets used less frequently but it covers specific articulation work beyond what 92507 captures. Some payers bundle it into 92507. Others want it separate. Check your contracts before you start using it on insurance claims.
92523 — Treatment of auditory processing deficits. This one's often overlooked because people don't realize it exists as a standalone code. If you're working on auditory processing skills, this is the code. Not 92507, even though the overlap is real. Auditory processing is its own thing. 92607 — Augmentative and alternative communication evaluation and/or treatment. If you're doing AAC work, whether it's a switch-based system or a speech-generating device, this is the code. The evaluation part and the treatment part are bundled into a single code number, so don't try to split them across two lines on a claim form. 92610 — Treatment of speech, language, voice, or fluency disorders. I actually use this less than I used to. It's basically the same as 92507 with different wording in the descriptor. Some older EMR systems default to this one. Make sure you're not double-billing 92507 and 92610 for the same session. That's an audit trigger.
Get the Full Details

What Nobody Tells You About These Codes
The first thing people miss is that modifier usage depends entirely on whether you're billing Medicare, Medicaid, or a private payer. Medicare uses GP for speech-language pathology services and GO for outpatient therapy. Private payers might want SZ or nothing at all. I had a claim denied three times because I kept using GO on a Medicaid plan that required SB. Took me four months to figure that out. The second thing is the time requirement. Some payers require a minimum of 8 minutes before you can bill a single unit of 92507. Others require 15. Medicare requires 8 minutes for the first unit and 15 minutes per additional unit under the quarterly rule. If you're seeing patients back-to-back, track your actual clock time. Rounding up to the nearest quarter doesn't fly with every payer. Here's a specific problem I ran into recently that illustrates why this matters. I had a patient who came in for a 32-minute session. I billed one unit of 92507 with 8 minutes and one unit with another 8 minutes, leaving 16 minutes unaccounted for. The claim was denied because I hadn't billed the third unit. The patient left early. The 16 minutes were documented in the note, but I hadn't mapped them to a billable unit on the claim. It happens all the time. Always map your total minutes to units before you submit. Don't trust your memory about what you billed.
Feeding and Swallowing Codes Are Their Own Beast
If you do any dysphagia work, you need to know these codes separately because they're billed differently and sometimes under a different benefit structure entirely: 92525 — Swallowing electrophysiology (VEESGT or FEES). This is a diagnostic code, not a treatment code. You use it when you're doing video fluoroscopic swallowing studies or fiberoptic endoscopic evaluation of swallowing. It's typically a physician-order procedure. Don't confuse it with therapeutic swallowing codes. 92622 — Feeding and/or swallowing therapy, oral. This is for oral-phase feeding therapy, usually with pediatric patients. It's distinct from 92507 even though it involves the same anatomical area. Some insurers require a separate diagnosis code to justify it.
92623 — Feeding and/or swallowing therapy, oral with intraoral work. The addition of "intraoral" is the key difference. If you're doing oral motor work inside the mouth, not just feeding strategies, this is the right code. Using 92622 when you should have used 92623 is a common upcoding risk that auditors flag.

Documentation That Actually Protects You
I've seen claims denied for insufficient documentation on 92507 more than any other single code. The pattern is always the same: the note says "worked on articulation" without specifying which sounds, which errors were corrected, and what the functional outcome was. That's not enough. Write down the baseline, the intervention, the patient response, and the next step. Four sentences. Takes thirty seconds. For 92607, document the specific AAC system being used, the goals addressed, and the patient's level of independence with the device. Generic notes like "patient used AAC" won't survive an audit. One more thing that matters: if you're using telehealth, make sure you have the right place-of-service code. POS 02 for telehealth is standard for Medicare, but some private plans still want POS 11 or POS 12 depending on where the patient is physically located during the session. I've had claims bounced back because the patient was at a relative's house and I put POS 02 instead of the correct home-based POS.
There isn't a free downloadable list that covers all of this because the code sets change. The CPT book gets updated every January and the ASCC adds new codes periodically. My advice is to subscribe to the ASHA resource center and check their billing pages twice a year. That's about all anyone can do to stay current without hiring a billing specialist.