What You Actually See on a Brain CTA
CT angiography of the brain is straightforward in theory and frustrating in practice. You inject contrast, you scan fast, and you get a volumetric dataset showing arterial flow. The tricky part is reading it properly. Most beginners look at the source images and call it done. That gets things missed. The standard phase for cerebral CTA is the arterial phase, roughly 20 to 25 seconds after injection. Timing matters more than most people admit. Shoot too early and your basilar artery looks patchy. Shoot too late and your venous structures start filling, which creates clutter exactly where you don't want it. I spent weeks dealing with suboptimal timing before I learned to use a test bolus protocol instead of a fixed delay. Fixed delays are a gamble. Test bolus saves you from rescheduling half your morning.
Ct Brain Angiography Anatomy
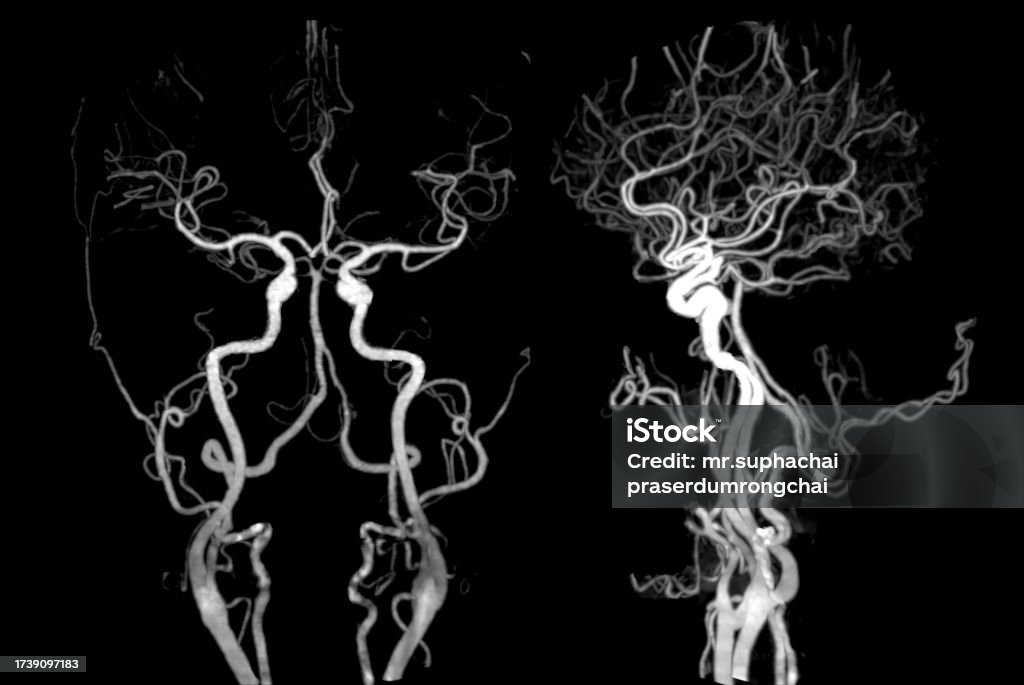
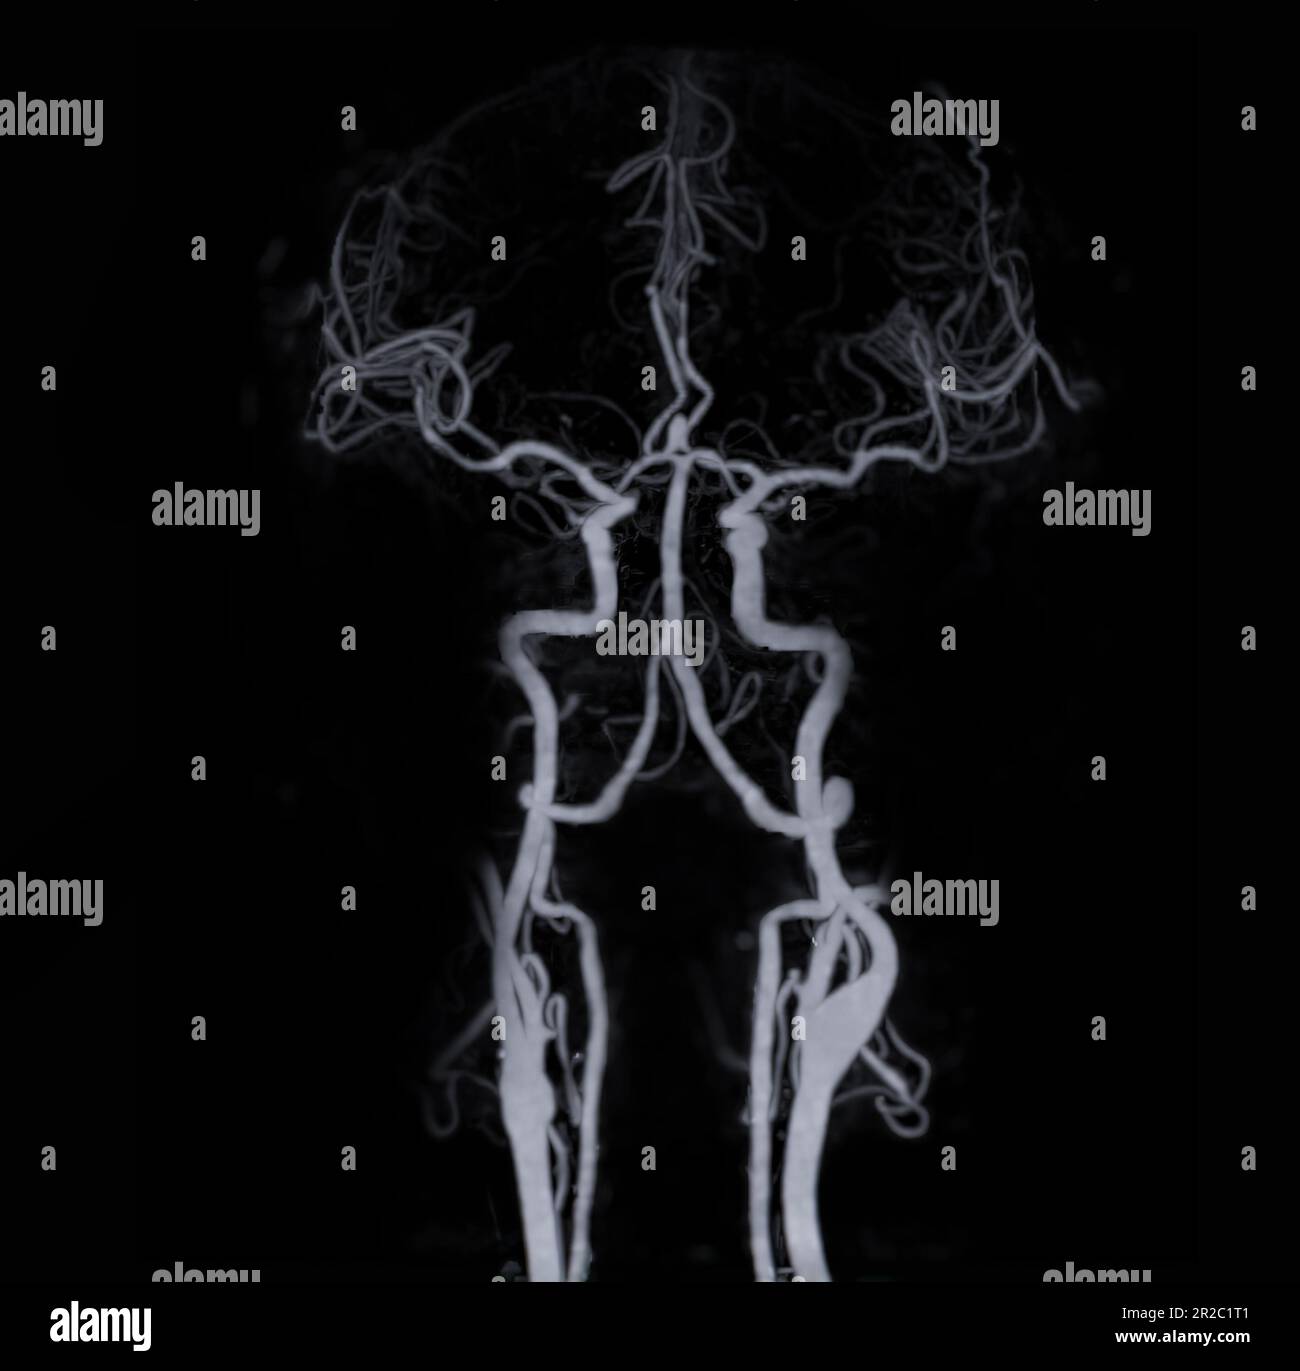
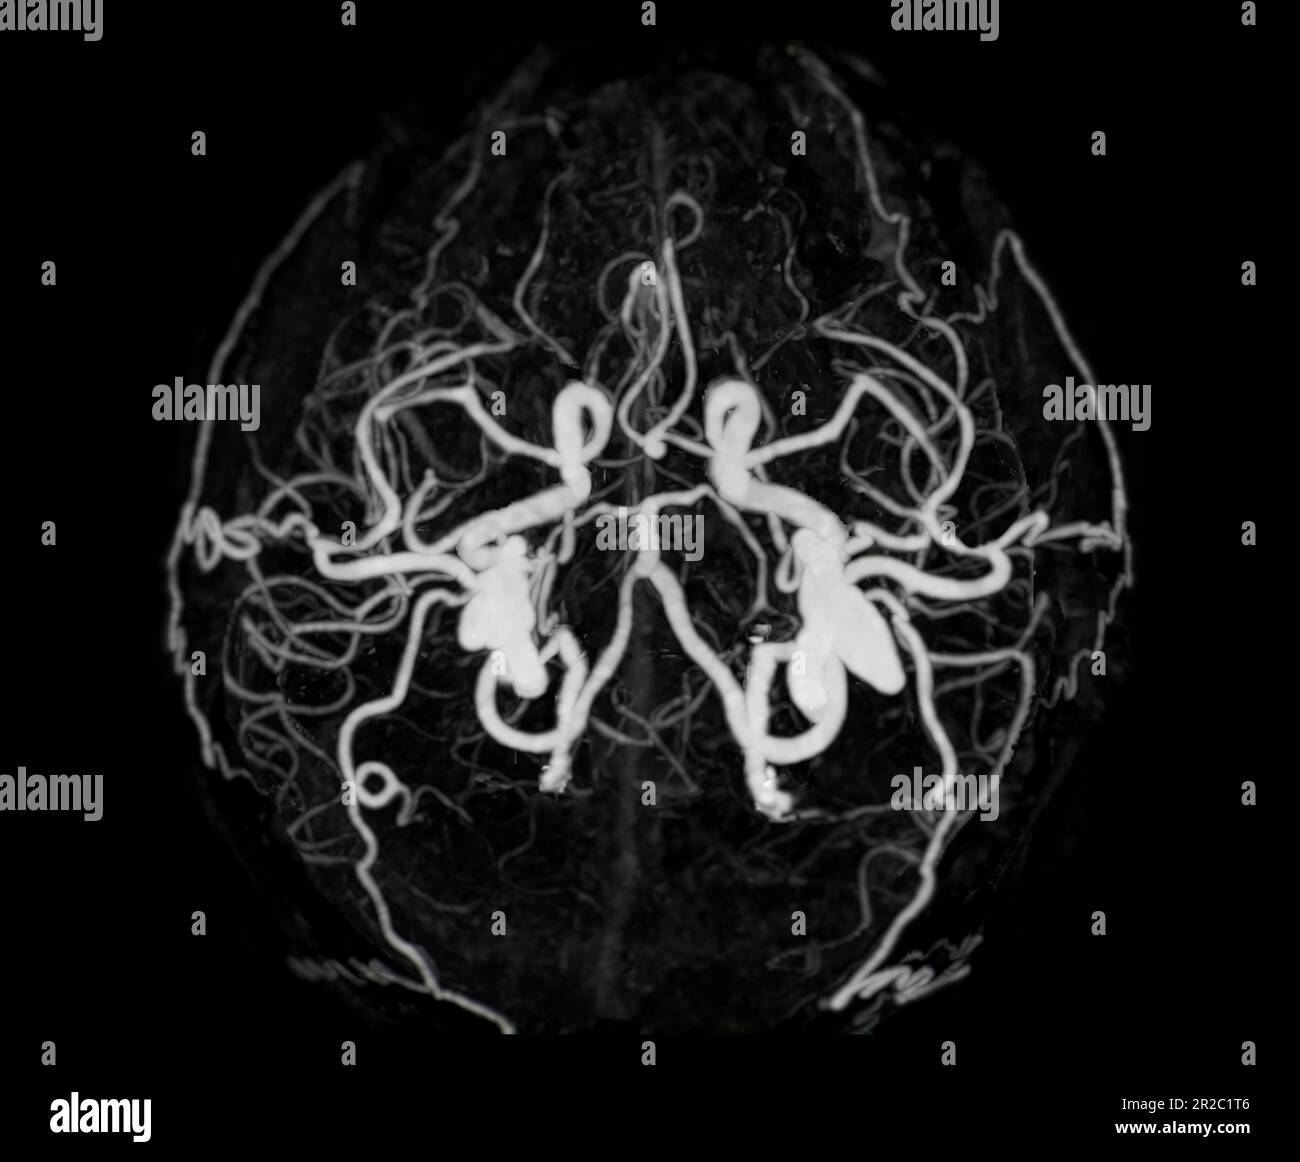
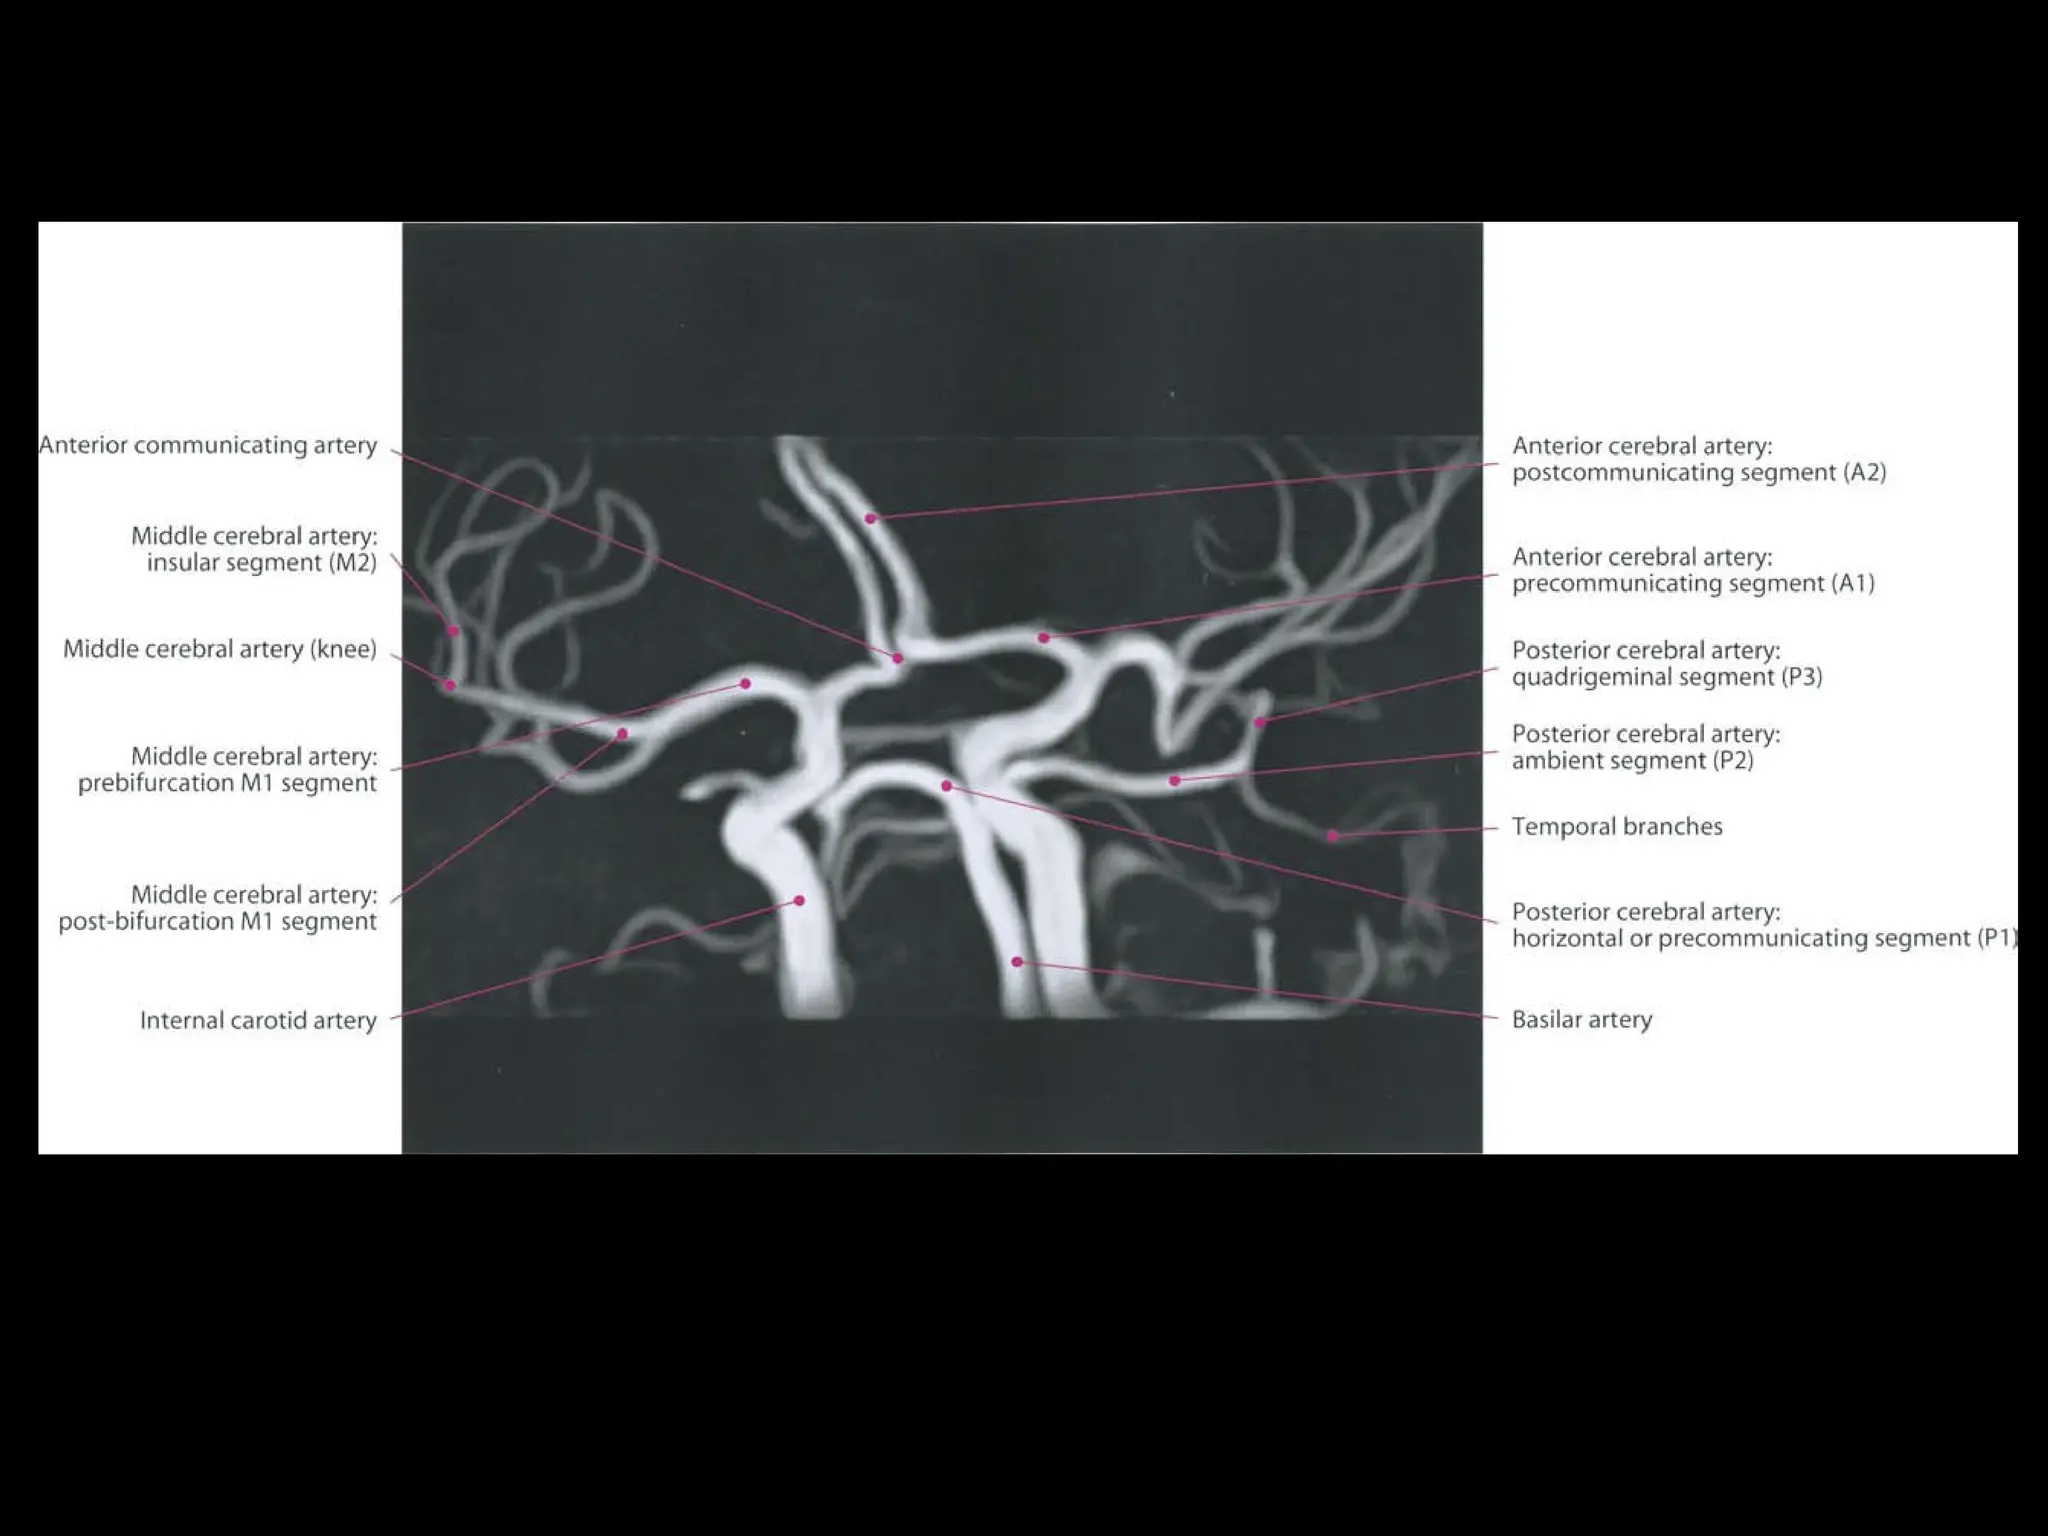
Start with the Circle of Willis. This is where everything converges. The internal carotid arteries branch into the anterior cerebral artery and the middle cerebral artery. The posterior circulation comes from the vertebral arteries joining to form the basilar artery, which then splits into the posterior cerebral arteries. The communicating arteries connect the two systems. Anterior communicating artery sits between the ACAs. Posterior communicating arteries link the ICAs to the PCAs. If any of these are hypoplastic or absent, don't flag it as a pathology immediately. About 20 to 30 percent of normal people have at least one variant. I have a habit of checking both sides before writing anything down. Beyond the circle, trace each vessel segment carefully. The M1 segment of the middle cerebral artery runs laterally. The M2 segments fan out over the insula. The A1 segment of the anterior cerebral artery is short and variable. The A2 segment curves around the corpus callosum. In the posterior circulation, the P1 segment of the posterior cerebral artery connects the basilar tip to the PCA proper. The pontine branches, the superior cerebellar arteries, and the anterior inferior cerebellar arteries all come off the basilar and vertebral system. Missing these small branches is an easy mistake, especially when you're reading on a worklist that moves fast. Here's something people don't tell you: the lenticulostriate arteries matter more than you think. These tiny perforators come off the M1 segment and supply the basal ganglia and internal capsule. They're almost never seen on routine CTA unless the resolution is good and the contrast opacification is bright. But when you're looking for vasculitis or a perforator aneurysm, they become relevant. I once read a CTA as essentially normal because I wasn't looking for them, and a follow-up angiogram showed multiple microaneurysms along those exact perforators. Don't skip the deep territory just because it's small.
The bone window setting on your workstation is not just for looking at fractures. Subtraction CTA removes bone and soft tissue, but sometimes you want to check if a calcified plaque is actually compressing a vessel or just sitting adjacent to it. Switching to a non-subtracted bone window and comparing it with the MIP reconstruction takes three clicks and prevents a misread. I learned that the hard way with a heavily calcified ICA bifurcation that looked like a tight stenosis on the subtraction images until I checked the unscaled source data. Reconstruction thickness is another detail that separates careful readers from rushed ones. Standard 1 millimeter MIPs work for most cases. But when you're hunting for a small aneurysm under 3 millimeters or assessing a tandem lesion in the carotid siphon, go down to 0.6 millimeters or even thinner. The noise goes up, yes, but the spatial resolution improves enough to catch things you'd otherwise blur past. Just make sure your detector rows support it. Old 64-slice scanners hit a wall here. Artifacts are the real enemy. Dental fillings create streaks that can completely obscure the anterior circulation, especially the ACA and the distal ICA near the cavernous segment. Beam hardening from the skull base does the same thing for the basilar artery and posterior fossa vessels. I've worked around dental artifact by switching to a higher kVp reconstruction on the fly, which reduces the photon starvation effect. It doesn't eliminate the streaks, but it makes the vessels behind them readable again. For skull base artifact, dual-energy CTA helps if your scanner supports it, but not every hospital has that capability. When it's unavailable, you just have to acknowledge the limitation in your report and recommend MRA or DSA if the clinical question is urgent.
Get the Full Details
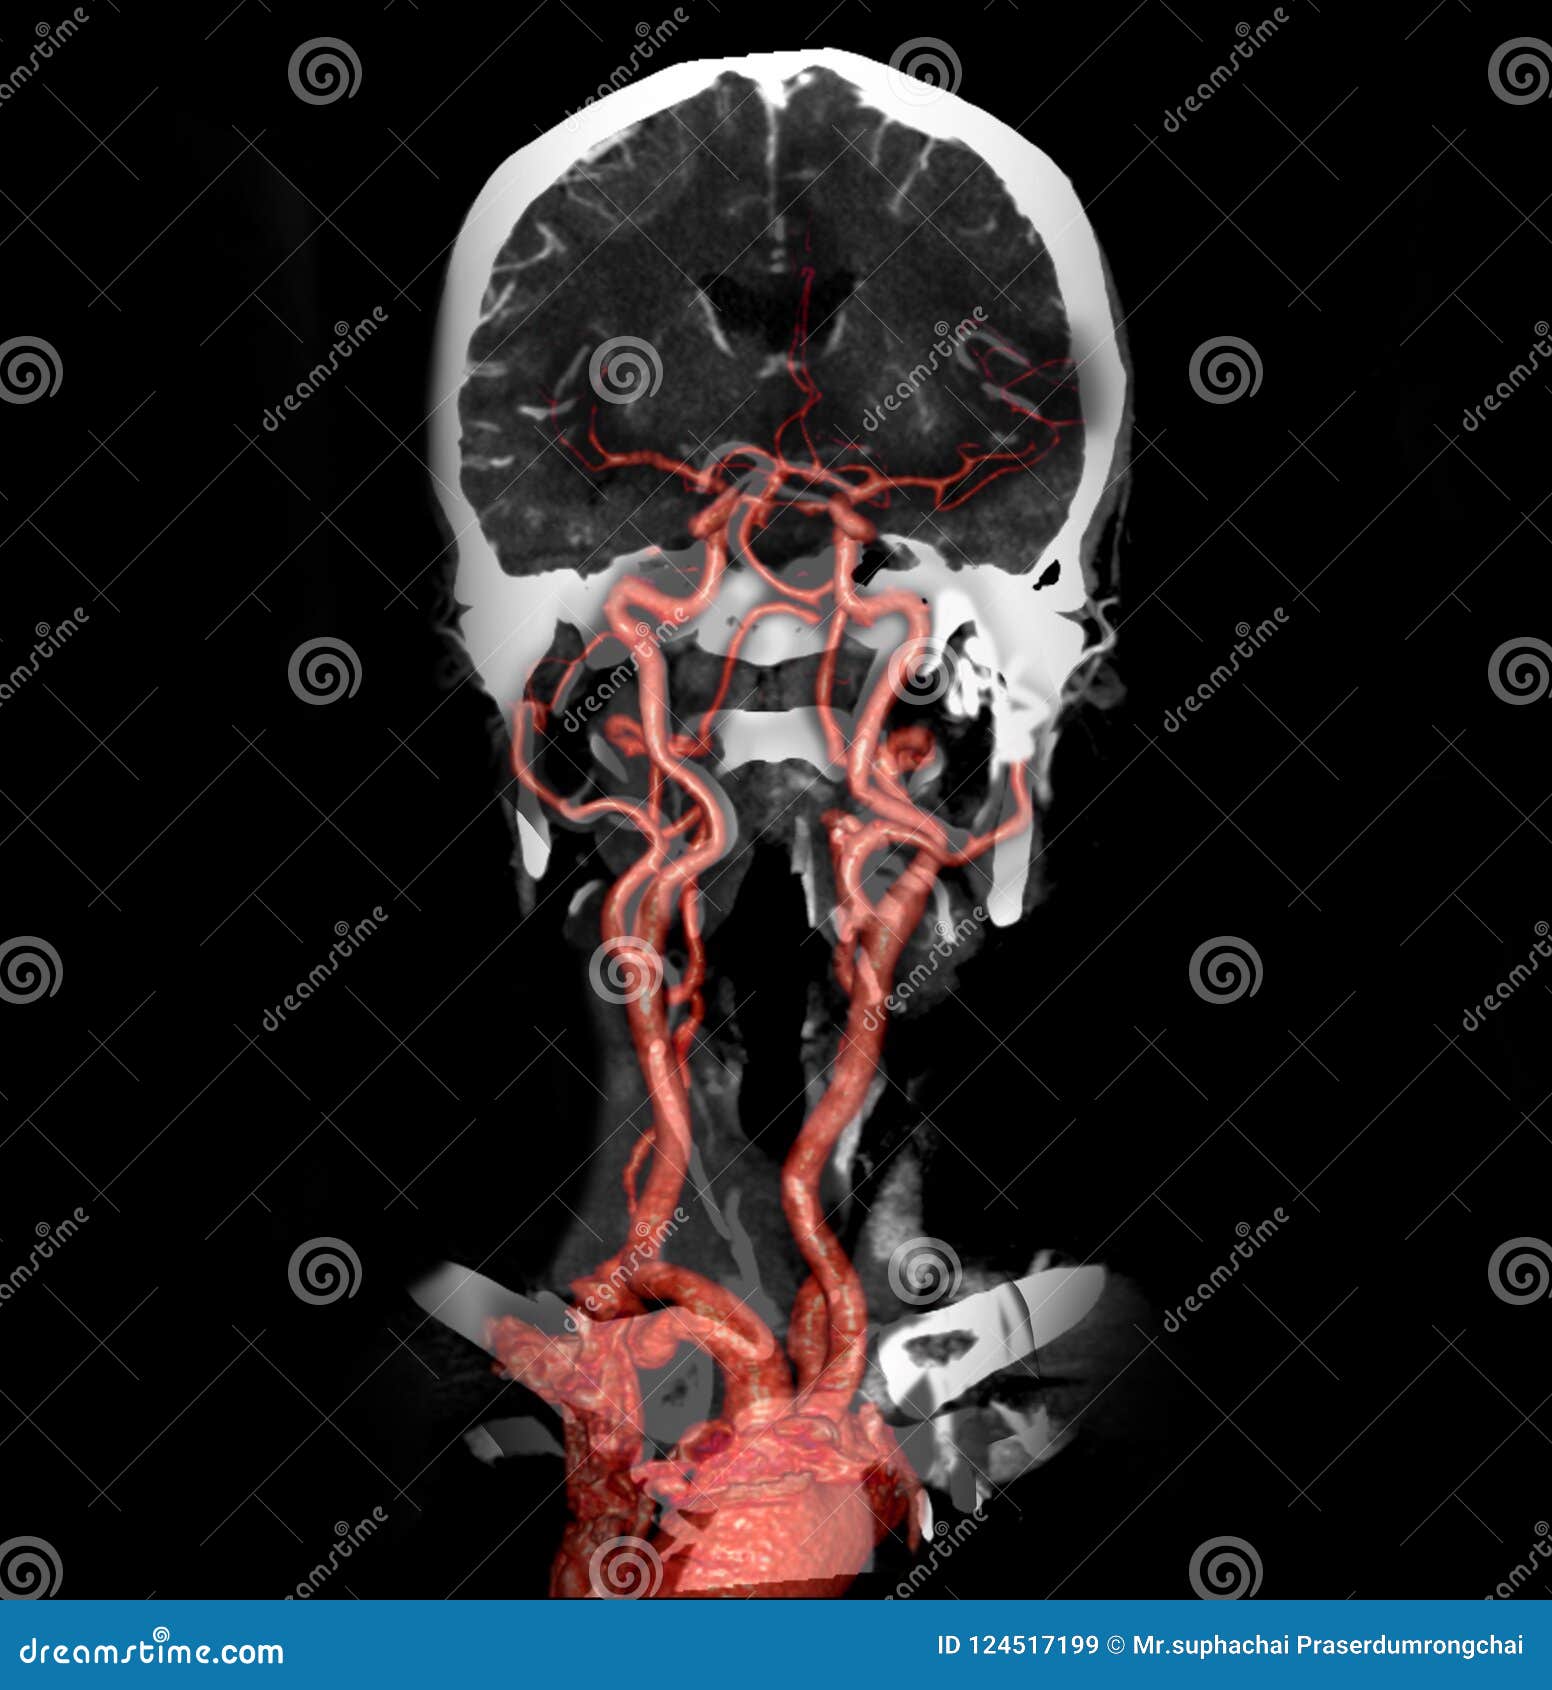
Trouble spots in the anatomy include the vertebrobasilar junction, the origin of the vertebral artery where it passes through the transverse foramen, and the ophthalmic artery segment of the ICA. The vertebral origin can be obscured by the clavicle and shoulder on the scan table. Tilting the arms up during acquisition helps, but not every technologist remembers to do it. I always check whether the arms were positioned correctly before I call a vertebral origin stenosis. Half the time it's just a positioning artifact. The ophthalmic artery is another one. It arises from the cavernous ICA and its course can be variable. A persistent trigeminal artery or other embryological remnant shows up here sometimes. These variants are usually incidental, but they confuse people who haven't seen them before. The biggest practical limitation of CTA for brain angiography is that it only shows the lumen. You cannot assess flow dynamics the way you can with digital subtraction angiography. Stenosis severity is estimated visually or with software calipers, and it consistently overestimates compared to DSA. A 70 percent stenosis on CTA might be 50 percent on conventional angiography. The North American Symptomatic Carotid Endarterectomy Trial criteria were built on DSA, not CTA. So when you're reporting for surgical decision-making, factor that in. I usually write something like "appearances consistent with moderate-to-severe stenosis" rather than giving an exact percentage when the vessel is heavily calcified or the image quality is borderline. Another limitation is contrast load. A typical brain CTA uses about 60 to 80 milliliters of iodinated contrast. For patients with renal impairment, that's a real concern. I always check a recent creatinine before requesting the scan if the patient is over 60 or has known kidney disease. The alternative is MR angiography, which avoids iodinated contrast entirely, though it takes longer and has its own artifacts from motion or metal implants. Neither modality is perfect. They're complementary.
One final thing that trips people up: the distinction between intracranial and extracranial anatomy on CTA. Most brain CTA protocols cover from the aortic arch or at least the clavicles up through the skull. If your indication is carotid stenosis, make sure the protocol includes the neck. A brain-only CTA will cut off right at the skull base and you'll miss the entire extracranial ICA. I've had referring physicians order "CTA head" when they meant "CTA head and neck," and the radiology tech just followed the order as written. Always clarify the clinical question before the scan happens.