Reading Pelvic Floor Muscles on CT
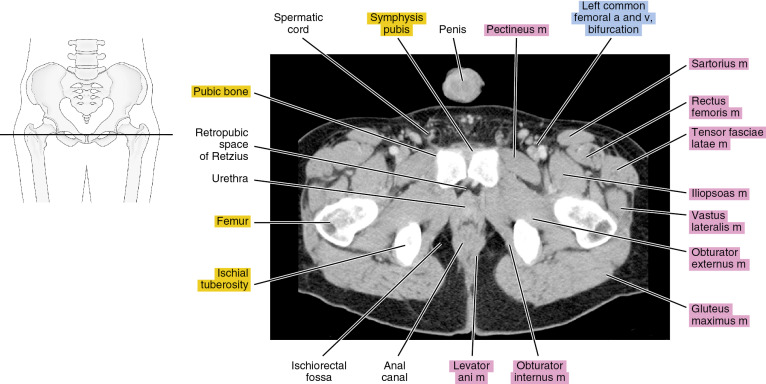
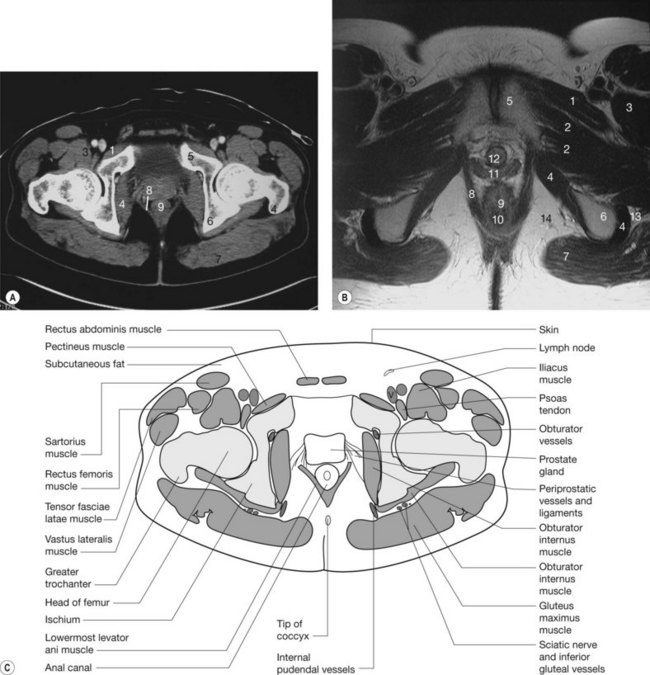
CT isn't the first modality most people think of for pelvic floor anatomy. MRI or ultrasound usually gets the call. But when you have a contrast-enhanced CT of the abdomen and pelvis, those muscles are there, and they're actually quite visible if you know where to look. The problem is most radiology reports don't mention them, so young residents learn to skip that region entirely. The pelvic diaphragm is made up of the levator ani complex and the coccygeus muscle. On axial CT images, the levator ani appears as a thin sheet of soft tissue draping from the inner table of the pubis, wrapping around the rectum and vagina (or prostate in males), and inserting onto the coccyx and anococcygeal raphe. The three components — puborectalis, pubococcygeus, and iliococcygeus — often blend together on CT, making sub-regional identification unreliable. Don't bother trying to separate them unless you're working with very high-resolution thin-slice data. Here's what most people miss. The obturator internus muscle also forms part of the pelvic sidewall and contributes to the lateral boundary of the pelvic floor. It's easy to overlook because it sits lateral to the levator ani and can be confused with fat or connective tissue, especially in thinner patients where there's less pelvic organ bulk pushing it into view.
I had a case last year where a patient was being evaluated for recurrent stress urinary incontinence, and the referring clinician wanted to know if the puborectalis was intact after a prior sphincteroplasty. The CT had been read as "unremarkable" by an outside facility. I went back and traced through the axial slices at the level of the proximal urethra, and sure enough, there was an asymmetric thinning of the puborectalis on the right side that had been completely missed. The trick was not looking at a single slice but running through the entire volume and watching the muscle's course in context. A static image doesn't tell you much about a structure that wraps around itself.
Practical Approach to Identification
Start with the contrast phase. A portal venous phase CT gives you the best soft tissue differentiation for these muscles. Arterial phase imaging washes out the contrast too quickly, and the muscles lack the enhancement needed to distinguish them from surrounding fascia. If you're looking at a non-contrast scan, good luck. The muscle bundles merge with adjacent structures, and you'll be guessing more than observing. The key anatomical landmarks are the ischial spines, the pubic rami, and the coccyx. The levator ani forms a muscular hammock between the ischial spines anteriorly and the coccyx posteriorly. On axial slices, look for the characteristic V-shaped or U-shaped configuration of the puborectalis sling around the anorectal junction. This is the most consistent and reliable structure to identify because it maintains its configuration regardless of patient position or bladder filling status. In females, the vaginal wall provides an excellent landmark. The pubovaginalis fibers insert into the lateral vaginal walls, and you can trace these fibers laterally to the obturator internus. In males, the prostatic urethra sits within the puboprostatic ligaments, and the puboprostaticus fibers are more variable in their development. Some men simply don't have well-defined puboprostaticus fibers, and that's normal. Don't call it an abnormality just because it looks different from what you saw in the textbook.
Get the Full Details
Common Pitfalls
The biggest error I see is misidentifying the periprostatic venous plexus or the deep dorsal vein as a muscle. On axial CT, these vascular structures can appear as rounded soft tissue densities adjacent to the prostate, and without a contrast-enhanced study, they're nearly impossible to distinguish from the levator ani fibers. Always verify vascular structures by checking adjacent slices — vessels will show continuity and enhancement patterns that muscles do not. Another frequent mistake is confusing the piriformis muscle with the levator ani. The piriformis exits the greater sciatic foramen and sits superior and posterior to the pelvic floor. On thicker axial slices, it can appear continuous with the iliococcygeus, leading some readers to overestimate the extent of the pelvic diaphragm. The piriformis is higher up, attached to the sacrum, and passes through the sciatic foramen — it doesn't insert onto the coccyx. Keep your slice selection tight and don't rely on reconstructions thicker than 3mm. I've also seen the external anal sphincter mistaken for the puborectalis. They sit close to each other, and the puborectalis is actually a thickening of the levator ani, not a separate muscle. On CT, you can sometimes see the transition from the tubular puborectalis sling wrapping around the anorectal junction to the more circular external sphincter below it, but only if you have thin slices and proper contrast. With standard clinical protocols at 5mm thickness, that distinction is nearly impossible. You'll need sub-millimeter isotropic reconstructions if you're going to make that call, and even then it's borderline.
When CT Falls Short
I need to be straightforward about this. CT has real limitations for evaluating pelvic floor muscle anatomy. The spatial resolution is adequate but not excellent. The muscles are small, thin, and variably positioned. CT doesn't show the functional dynamics — you can't see how these muscles change during straining or Valsalva maneuvers the way you can with dynamic MRI or ultrasound. If your question is whether the pelvic floor is functioning properly, CT is the wrong tool. It tells you about morphology, not function. The radiation dose is another consideration, though in practice most pelvic CTs are already being performed for other indications. You're not exposing the patient to additional risk if the scan is already ordered. But if you're specifically trying to evaluate pelvic floor anatomy, you'd be better off with pelvic MRI, which gives you superior soft tissue contrast and can be done in multiple planes without radiation. Or dynamic defecography if you need functional information. That said, CT has an advantage that people don't always consider. It's fast, widely available, and the images are already there in most cases where you're dealing with oncology, trauma, or vascular patients. I've found it useful in rectal cancer staging to assess whether the levator ani has been invaded by a low-lying tumor. If the fat plane between the tumor and the puborectalis is obliterated, that changes the surgical approach. That's a concrete clinical decision where CT pelvic muscle anatomy actually matters.
A Note on Variability
There's significant normal variation in pelvic floor muscle size and configuration between individuals. Body habitus plays a role — leaner patients tend to have more visible muscle bulk because there's less surrounding fat. Age matters too. The levator ani undergoes atrophy with age, and you'll see this more prominently on imaging. A 70-year-old woman will almost certainly have thinner pelvic floor muscles than a 30-year-old, and that doesn't necessarily mean pathology. It means aging. Sexual parity also affects the appearance. Women who have had vaginal deliveries often show some degree of asymmetry or thinning of the puborectalis, particularly if there was a third- or fourth-degree perineal tear. This isn't something you need to flag as abnormal unless it correlates with symptoms, but it's worth knowing so you don't chase every asymmetry as a finding. The bottom line is that reading pelvic muscles on CT requires patience and a systematic approach. Start with the anorectal junction, identify the puborectalis sling, trace the levator ani laterally to the obturator internus, and work your way posteriorly toward the coccyx. Don't rush through the slices. Spend time in that region, and you'll find the anatomy. Most people don't because they don't expect to find it there.