Why Most Nurses Get Cultural Assessment Wrong
You hand a patient a standard assessment form and fill it out with a few checkboxes about diet, language, and religion. You think you have done a cultural assessment. That is not how this works. The process is messier than a form allows, and the places where it breaks are the ones that cause actual patient harm. I spent years charting cultural assessments the way the EHR template dictated. I hit the boxes, saved the note, and moved on. It was not until I got a call from a surgical floor about a post-op patient who had refused pain medication for two days that I understood what I was missing. The form had a checkbox for "no pork" under dietary preferences. What the nurse on the floor actually needed to know was that the patient, a devout Hindu man in his sixties, interpreted his illness through a framework of karmic consequence. Taking pain meds was seen by him as numbing the body's ability to process that karma. The standard cultural assessment tool on our unit had not come close to uncovering that.
What Cultural Assessment In Nursing Actually Requires
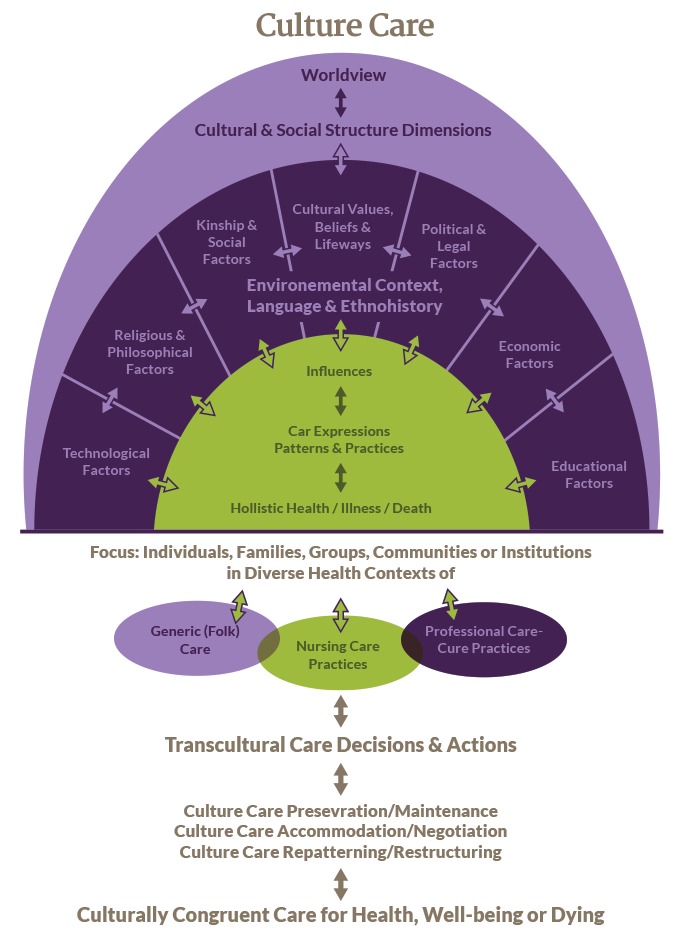
Cultural assessment in nursing is the systematic process of gathering information about a patient's cultural beliefs, values, and practices that influence how they experience illness, interact with the healthcare system, and make treatment decisions. It is not a single form you complete at admission. It is an ongoing conversation that should be woven into your assessment over time. The most commonly used tool is Campinha-Bacote's Ask-Care-Discover model, though many programs still rely on the LEARN framework or the Purnell Model. These are starting points, not destinations. A practical approach is to use the five structural domains from the clinical cultural assessment: communication, family roles and dynamics, nutrition and dietary practices, spiritual and religious beliefs, and approaches to pain and illness. When you structure your intake around these five areas, you cover the ground that actually matters in a clinical setting. Here is what that looks like in a real shift. I am admitting a patient from a Somali background. Instead of filling out the generic "cultural considerations" box in the EHR, I ask three things upfront: What foods can you eat that we might offer that would be uncomfortable for you? Who in your family makes healthcare decisions? Are there religious or spiritual practices you need us to accommodate during your stay? Those three questions take about four minutes and surface more useful information than ten checkboxes ever would.
Edge Cases Where Standard Tools Fall Apart
The hardest case I ran into involved a Southeast Asian refugee who had received no formal healthcare before arriving in this country. He spoke virtually no English. The interpreter service was booked for two hours out. His wife was with him but she was clearly uncomfortable discussing certain topics in front of him. He kept touching his chest and pointing to his stomach in a way that made no clinical sense. He was constipated, severely, and probably in significant discomfort. The cultural assessment tool we used had nothing to say about someone whose cultural context was shaped more by trauma and displacement than by any identifiable cultural tradition. My workaround was to stop trying to fit him into the framework and just observe. I asked the wife, privately since she was clearly the decision-maker here, what symptoms he would normally treat at home. She said they used a herbal tea. I asked if we could get some for him. We couldn't source the exact herb, but we got him castor oil packs and a warm compress protocol, and the team agreed to let her prepare the tea herself rather than relying on the cafeteria. It was not in any policy manual. It also worked. His obstruction resolved within eighteen hours and he was discharged a day earlier than expected. Another scenario that trips people up is patients who identify as atheist or agnostic but still practice culturally rooted rituals. A colleague of mine once charted a patient as "no religious accommodations needed" because they marked "none" on the spiritual preference line. That same patient then asked for a priest to come and lay hands on them before surgery. They did not identify as religious but the cultural expectation of ritual care in their community was strong. The assessment should never be reduced to a single religion question.
Get the Full Details

Counter-Intuitive Things You Will Learn the Hard Way
First, the more structured your assessment becomes, the less useful the data tends to be. Patients will tell you what they think you want to hear if you ask closed questions. "Do you have any cultural restrictions?" gets you "no" ninety percent of the time. "Walk me through a typical day of eating" or "Tell me about a time you were sick before and how your family handled it" gets you something real. Open-ended questions cost you more time upfront but save you from surprises later. Second, documenting a cultural assessment in your EHR does not mean you have completed the assessment. The chart note is administrative output. The actual assessment happens in the conversation. I have seen nurses spend twenty minutes writing a beautifully detailed cultural note and then proceed to ignore everything in it during rounds. The culture lives in the practice, not the paperwork. Third, you will encounter patients whose cultural practices conflict with evidence-based care. This happens more often than you might expect in postpartum care, pediatric vaccination discussions, and end-of-life decisions. The correct response is not to dismiss the practice or to compromise on safety. It is to acknowledge the practice, explain the medical reasoning without judgment, and negotiate where possible. A patient who believes in hot and cold food therapy after childbirth is not wrong for having that belief. You can acknowledge it while still ensuring the patient understands which foods are medically recommended and why. Documentation should reflect that the discussion happened and the patient's choice was informed, not that you agreed or disagreed with their framework.
Practical Limitations You Need to Accept
Cultural assessment is not a silver bullet. It will not prevent miscommunication with every patient from every background. It will not replace the need for professional interpreters when language barriers exist. In fact, relying on cultural assessment as a substitute for interpreter services is one of the most common mistakes I see. A patient can speak fluent English and still process health information differently based on cultural context. Another patient may have limited English proficiency and also hold deeply held cultural beliefs. These are two separate axes. The biggest bottleneck is time. A thorough cultural assessment, done properly, takes fifteen to twenty minutes of focused conversation. Most nursing shifts do not have that kind of uninterrupted time available during admission. The workaround is to spread it out. Ask one or two questions at initial contact. Follow up with another set during medication administration or wound care. Culture is not a box you check at 0800 and forget about. It is relevant at every interaction point. There is also the risk of stereotyping. If you assess one patient from a particular background and then assume every subsequent patient from that same background has identical beliefs, you will be wrong. Cultural assessment is about the individual, not the demographic. The framework helps you ask better questions, but the answers are always person-specific.
Resources That Actually Help
The Health Resources and Services Administration (HRSA) maintains a free Cultural Competency Curriculum Module that is widely used in nursing programs. It is not a form you download and fill out. It is a training resource that covers the framework, the tools, and the common pitfalls in more depth than most hospital orientation provides. The National CLAS Standards from the Office of Civil Rights provide the regulatory framework that most hospitals must comply with. Knowing which standard applies to your situation helps you understand why the assessment matters beyond good practice. For quick reference during a shift, I keep a laminated card with the five assessment domains on my badge reel. Communication, family dynamics, nutrition, spirituality, and pain/illness beliefs. Four minutes. Covers the territory that matters. The form your facility provides is probably adequate for compliance. Do not let it be adequate for your practice. The patients who need the most careful cultural assessment are the ones who do not fit neatly into any checkbox on your EHR template.