How I Actually Use This Worksheet in Practice
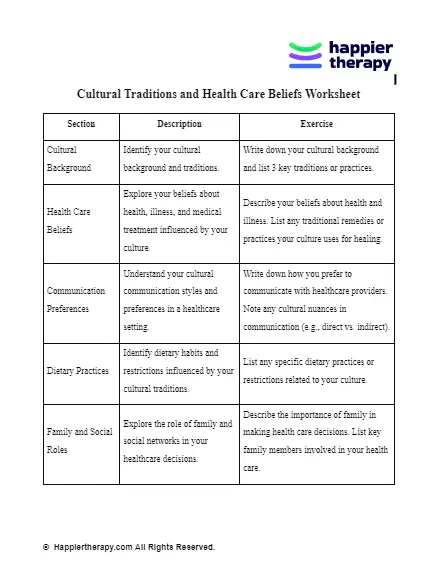
I've been working with cultural competency materials in clinical education for years, and the Cultural Traditions And Healthcare Beliefs Worksheet Answers document comes up more often than I'd like to admit. It shows up when nursing students need to complete assignments on patient belief systems, when public health educators design community outreach programs, and occasionally when I'm reviewing cases where treatment non-compliance traced back to unexamined cultural assumptions. The thing about this worksheet that nobody really explains upfront is that the answers section isn't a grading key you memorize. It's a reference framework. I learned that the hard way during my second semester trying to help a student who thought the worksheet was asking for a single "correct" interpretation of every cultural practice. She spent three hours trying to match each tradition to a specific ethnic group like it was a multiple choice quiz. The worksheet was actually designed to help students recognize that healthcare beliefs vary along multiple axes simultaneously—religion, regional custom, socioeconomic access, generational differences, and individual family history. No template covers all of that.
Cultural Traditions And Healthcare Beliefs Worksheet Answers
Here's what the answer section actually contains and how each part functions in a real classroom or fieldwork setting. The first section typically deals with defining core terminology. Terms like health locus of control, explanatory models of illness, and cultural humility come with specific academic definitions that the answers reference. Health locus of control, for instance, is measured on a scale from internal (I control my own health outcomes through my actions) to external (health outcomes are determined by fate, doctors, or divine will). Students who confuse this with simple health literacy tend to miss the distinction entirely, which matters because a patient who believes illness is a punishment operates differently in a treatment plan than a patient who simply lacks information about their condition. The second section usually presents case scenarios with guided analysis. One common example involves a patient refusing blood transfusion. The surface answer points to religious belief, but a deeper reading of the worksheet answers shows that the real learning objective is recognizing that refusal might stem from religious doctrine, previous negative medical experiences within that community, distrust of research institutions, or a combination. The answers don't pick one. They model the diagnostic process of ruling out possibilities.
I encountered a specific edge case last year that tested exactly this. A physician assistant student was working with an elderly Hmong patient who consistently missed follow-up appointments. The worksheet's framework pointed toward cultural barriers, but the actual answer the student arrived at involved transportation access and the fact that the patient's family interpreted the clinic's appointment reminders as optional suggestions rather than obligations. The worksheet answers would have flagged communication style as the primary factor, but the real driver was socioeconomic. This is the kind of gap between the textbook answer and ground reality that the worksheet acknowledges but can't fully resolve on its own. The third section covers specific cultural health practices and their clinical implications. This is where students often struggle most because the answers deliberately avoid generalizations. A response about traditional Chinese medicine practices, for example, includes notes about herb-drug interactions that aren't in standard pharmacology references. Goldenseal can affect CYP450 enzymes. Ginseng may interfere with warfarin metabolism. These details matter clinically and the worksheet answers include them because cultural competency without clinical specificity is just good intentions. One counter-intuitive insight from the answers that beginners miss is that documenting cultural beliefs in the medical record isn't always beneficial. There's a section in the worksheet that addresses this directly. When a patient shares traditional healing practices, recording them as "patient beliefs" rather than "complementary treatments under consideration" creates a categorical distinction that can subtly shift how subsequent providers approach the case. The worksheet answers recommend framing documentation neutrally and integrating relevant practices into the treatment plan when they don't conflict with safety, rather than creating a separate cultural column in the record.
Get the Full Details

How to Work Through the Worksheet Efficiently
The process takes roughly forty-five minutes for a first pass if you're reading carefully. I usually allocate an hour because students who rush the case studies miss the nuance the answers are designed to highlight. Start with the terminology section. Don't skip it. The definitions in the answers section build the vocabulary you need to discuss the case studies without falling back on vague language like "the patient's culture." That phrase means nothing clinically. The worksheet answers push you toward precise descriptors instead. When you reach the case scenarios, write your initial analysis before looking at the answers. This is important because the worksheet is structured so that your first interpretation will often be incomplete in predictable ways. I've watched students consistently miss the socioeconomic layer in case studies. They see a cultural barrier and stop there. The answers then reintroduce factors like insurance status, language access, and transportation that the student had overlooked. The gap between the first draft and the final version is where the actual learning happens.
The reflection questions at the end are the part students underestimate. These aren't filler. They ask you to identify your own assumptions about health and illness. The answers acknowledge that everyone brings bias to these exercises and that recognizing bias is different from eliminating it. You don't finish this worksheet culturally competent. You finish it aware of what you still don't know, which is the actual goal.
What the Worksheet Doesn't Cover
Being honest about limitations matters more than overselling the tool. The Cultural Traditions And Healthcare Beliefs Worksheet Answers document has real constraints that educators sometimes overlook. First, it covers broad categories of cultural practices without sufficient attention to intra-group variation. Two patients from the same community can hold completely different health beliefs based on generation, education level, migration experience, and individual family history. The worksheet occasionally acknowledges this but doesn't provide enough scaffolding for students to apply it consistently. Second, the case scenarios lean heavily toward Asian and Hispanic populations. African, Middle Eastern, Indigenous, and European American cultural health practices receive proportionally less coverage. If you're using this worksheet in a diverse clinical setting, you'll need to supplement it with additional materials.

Third, the answers assume a healthcare system context that may not match your reality. Discussion of insurance barriers, hospital policies, and referral networks reflects the US system. Students in other countries or in community health settings outside hospital systems will find some sections less applicable. A practical workaround I use is pairing this worksheet with the LEARN model from Berlin and Fowkes, which provides a structured communication framework that's more universally applicable. The worksheet gives you knowledge about specific traditions. The LEARN model gives you a process for applying that knowledge in any clinical encounter regardless of the specific cultural background involved. If you're looking for the full Cultural Traditions And Healthcare Beliefs Worksheet Answers document, it's typically available through academic course repositories or publisher companion websites. Check with your instructor or the course learning management system first. Some versions require an instructor key, and unofficial copies circulating online may contain outdated or incorrect information that won't match your current curriculum.
The worksheet works best when treated as a starting point rather than a comprehensive guide. Cultural competency in healthcare is a practice, not a destination, and no single assignment can teach you everything you need to know. But it does give you a structured way to begin examining the assumptions you bring into clinical situations, and that self-awareness is the foundation everything else builds on.