How We Actually Run Cumulative Analysis In Practice
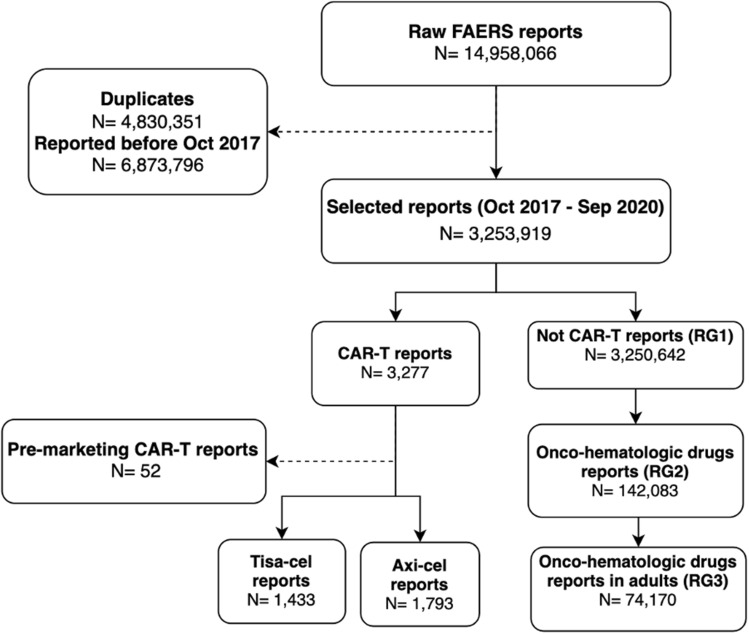
I spend most of my week pulling together cumulative safety summaries for products that have been on the market for three to eight years. It is not glamorous work. You sit down with millions of rows of adverse event data, export it from whatever database the pharmacovigilance team is using, and figure out whether the safety profile has shifted since the last report. The regulatory expectation is clear: every marketing authorization holder needs to provide a running total of all known adverse reactions, organized in a way that a reviewer can actually use. That means the Cumulative Analysis Of Post Authorization Adverse Event Reports has to tell a coherent story with numbers that reconcile across tables, figures, and narratives. The first thing most people get wrong is assuming the work starts with analysis. It starts with data hygiene. I have seen teams skip this step and spend three days chasing inconsistencies between the raw case database and the aggregate totals. The fix is usually straightforward: pull a complete dataset export, run a field-level validation script, and compare expected versus actual row counts against the previous reporting period. If you are working with EudraVigilance data or FAERS data, the field definitions differ slightly between regions. MedDRA version drift is another quiet killer. I switched from MedDRA 24.1 to 25.0 mid-analysis once and did not catch it until the system-generated summary table disagreed with my manual cross-check by about forty cases. The workaround was to lock the MedDRA version at the top of the project and regenerate the entire cohort before proceeding further. Takes about an hour, saves you from explaining discrepancies to a health authority later.
Cumulative Analysis Of Post Authorization Adverse Event Reports: What It Actually Is
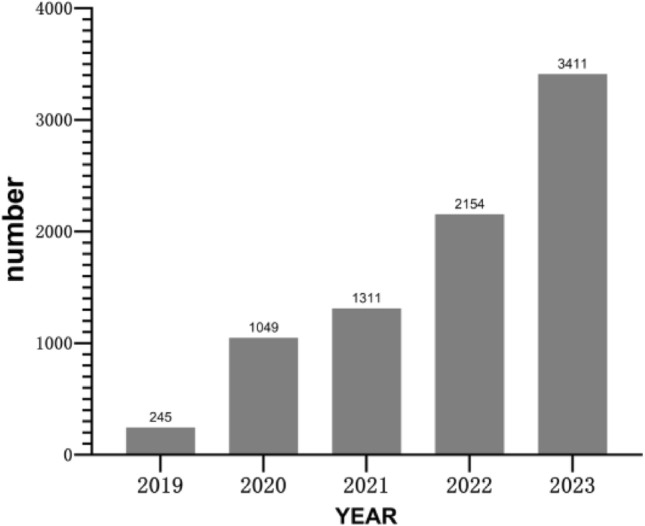
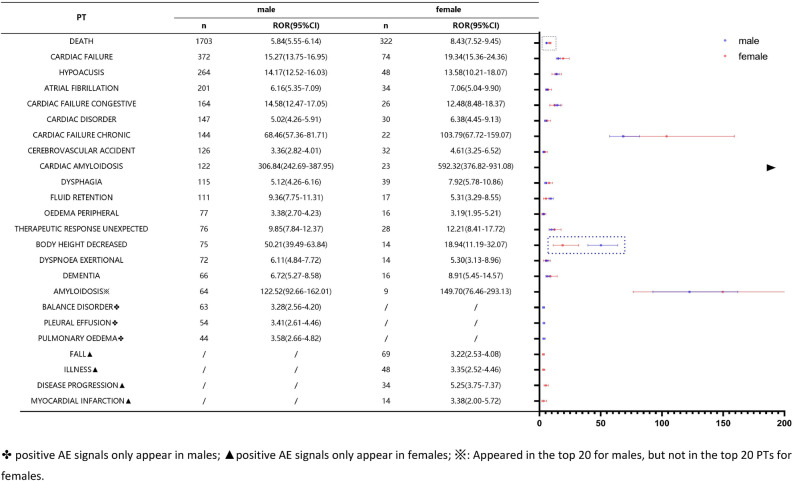
At its core, this is a living safety document. You take every adverse event report received after a product gets marketing authorization, add the new cases to the existing pool, and produce updated summary statistics. The output typically includes incidence rates where denominator data exists, frequency counts by system organ class, severity distributions, outcome classifications, and demographic breakdowns. Regulators want to see trends over time, not just snapshot numbers. A cumulative analysis shows whether a signal is growing, stabilizing, or fading as more data rolls in. The methodology section of any proper cumulative analysis needs to answer three questions: what data sources were included, what exclusion criteria were applied, and what time window does the current reporting period cover. I usually define the window as the period since the last PBRER or DSUR submission, whichever applies. Exclusion criteria typically remove duplicate reports, cases from clinical trials that fall outside the post-authorization scope, and reports where the product is listed only as a concomitant medication rather than the suspected cause. The exact rules depend on your indication and therapeutic area. Oncology products accumulate adverse events differently than narrow-therapeutic-index cardiovascular drugs. One thing that catches people off guard is the handling of fatal outcomes. A single death can shift the entire narrative of a cumulative analysis, even if the causal relationship remains unproven. I had a case where three death reports came in within the same quarter, all involving the same rare arrhythmia. The overall incidence remained extremely low, but the clustering triggered a mandatory safety amendment. The workaround I use now is to tag any death report at the point of entry and run a parallel narrative review before the final summary is locked. That extra day of work prevents the entire team from being blindsided during a regulatory query.
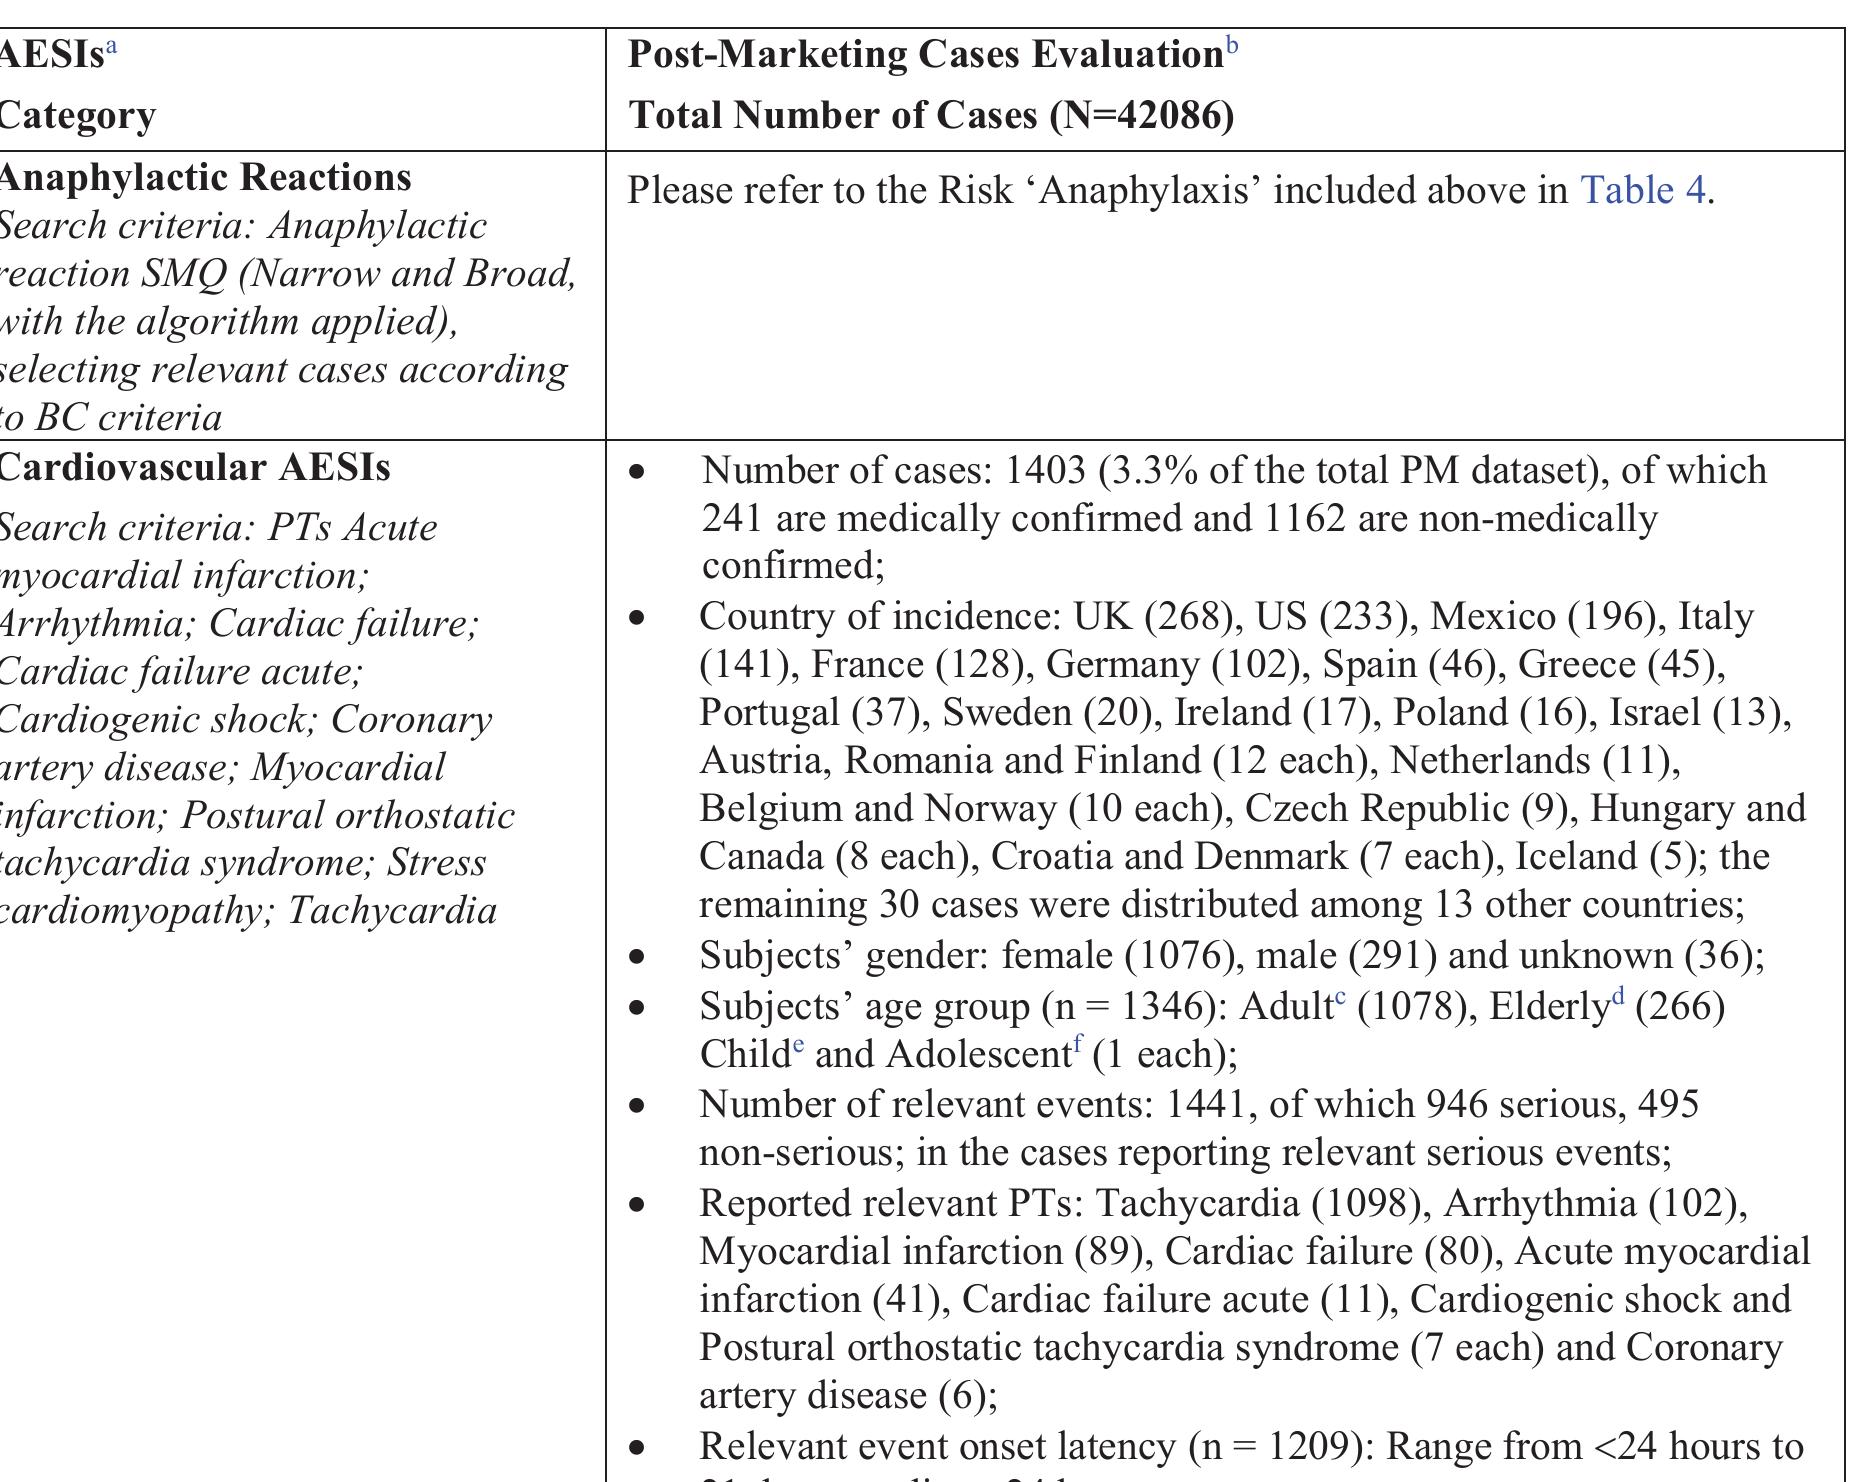
The numbers themselves are usually generated using standardized tables and listings. Table 11.1.1 from the PIC/S guidance is the starting point for most teams: a breakdown of all reported adverse reactions by system organ class and preferred term. Table 11.2.1 covers seriousness criteria. Table 12.1 provides information on post-authorisation studies. These tables are not optional. Health authorities expect them in the exact format, and deviating from the standard structure creates unnecessary friction during review. I have found that building the tables directly from validated database queries rather than rebuilding them in Excel reduces transcription errors significantly. The trade-off is that you need someone on the team who can write functional SQL or R code. If your pharmacovigilance unit does not have that capability, budget for external support or train an analyst. The cost of a re-review triggered by a formatting error is higher than the training investment. Denominator data deserves more attention than it gets. Post-authorization cumulative analysis often lacks reliable exposure denominators, especially for over-the-counter products or drugs with broad prescribing patterns. Without exposure data, you cannot calculate true incidence rates, and you are forced to rely on reporting frequencies. This limitation should be stated explicitly in the document. I usually add a dedicated subsection noting the absence of denominator data and explaining the impact on interpretability. Regulatory reviewers are accustomed to this gap. They are less accustomed to finding it hidden inside a paragraph of text where it can be easily missed. Signal detection is the part of cumulative analysis that most teams treat as an afterthought. The reality is that signal identification should happen continuously throughout the reporting period, not just at the end when the summary report is due. I keep a running register of potential safety signals flagged during routine case processing. When the cumulative analysis is compiled, each signal gets a status update: confirmed, refuted, or requiring further evaluation. This approach cuts the signal assessment phase from roughly two weeks down to about three days because the groundwork is already done.
Get the Full Details

Here is a practical workflow that works for most products. Export the full adverse event dataset for the current reporting period. Merge it with the cumulative dataset from all prior periods using a unique case identifier to avoid double-counting. Run the standard tables and listings through a validated script. Perform a narrative review of any serious unexpected adverse reactions. Update the signal register. Draft the discussion section, which should address changes compared to the previous report, new safety information, and any action taken or planned. The discussion is where the actual analysis happens. Numbers alone do not satisfy regulators. The narrative needs to explain what the numbers mean in clinical context. Software tools vary widely across the industry. Argus Safety, ArisG, and VigiBase are common in larger organizations. Smaller companies sometimes rely on spreadsheets and manual aggregation, which is manageable for products with low reporting volumes but becomes fragile quickly. If your product generates more than five hundred new adverse event reports per year, manual methods introduce unacceptable risk. I recommend at least a semi-automated pipeline where the database export feeds into a validated aggregation script with manual oversight at each step. There are legitimate limitations to cumulative analysis that nobody likes to advertise. Spontaneous reporting data is inherently biased. Severe and unusual events are overrepresented. Events from populations that are harder to monitor, such as pediatric or geriatric patients in certain therapeutic areas, are underreported. Cumulative analysis does not correct for these biases. It documents them. The best reports acknowledge the limitations upfront and frame the findings accordingly. Pretending the data is representative of the general prescribing population is a common mistake that leads to overconfident conclusions and subsequent regulatory pushback.
Another limitation is the lag time. Adverse event reports from healthcare professionals often arrive months after the event occurred. A cumulative analysis submitted in July may not include cases that happened in May or June. This delay is structural and unavoidable. The standard approach is to define the data cutoff date clearly and note that subsequent reports may modify the analysis. I usually add a footnote stating that approximately ten to fifteen percent of reports in any given period are late submissions, based on historical data from the relevant databases. The documentation itself should be organized so that a reviewer can verify any number with minimal effort. Every table should include a reference to the underlying data source and the query used to generate it. I store the SQL or R scripts alongside the final report in a version-controlled repository. This practice took about twenty minutes to set up initially and has prevented at least two potential credibility issues when regulators asked for audit trail documentation. The scripts should be annotated with comments explaining each major step. Future you will thank present you during the next reporting cycle when you need to reproduce or modify an analysis. Peer review of the cumulative analysis is not a luxury. It is a control measure. Before any report is finalized, a second qualified person should independently verify the table outputs against the raw data. This step typically catches about one or two errors per reporting cycle, usually rounding discrepancies or misclassified system organ classes. The review process adds roughly four to six hours to the timeline but prevents far more costly corrections later. I have seen corrected submissions require additional data clarifications that delayed approval timelines by several weeks. The peer review is cheaper than the alternative.
When writing the final document, keep the language precise and factual. Avoid interpretive statements that go beyond what the data supports. Phrases like "suggests a possible association" are acceptable when the evidence is indirect, but "establishes causality" should never appear in a cumulative analysis unless supported by specific pharmacological or epidemiological evidence outside the spontaneous reporting dataset. Regulators are trained to spot overstated conclusions, and encountering them creates an impression of carelessness that affects how the rest of the submission is received. The cumulative analysis is ultimately a snapshot of accumulated experience. It will never be complete, and it should never claim to be. The value lies in consistent methodology, transparent documentation, and honest interpretation. The products I work with generate thousands of reports annually, and the cumulative picture evolves slowly. Some safety signals emerge over years. Others fade as the population grows and rare events become statistically expected. The analyst job is to track that evolution accurately and communicate it clearly, not to force the data into a predetermined conclusion. If you are new to this type of work, start by mapping out your data sources and validation steps before writing a single table. Build the validation framework first. Then generate the tables. Then write the narrative. The order matters because each step depends on the integrity of the one before it. Rushing ahead without that foundation produces reports that look professional on the surface but fall apart under scrutiny.
Practical Considerations For Ongoing Maintenance
Cumulative analysis is not a one-time exercise. It is a recurring deliverable tied to periodic safety report submissions. The cadence depends on your authorization type and region. PBRERs are typically annual. DSURs follow the clinical trial reporting schedule. Individual member state requests can trigger ad hoc analyses at unpredictable intervals. Building a standardized pipeline that can handle both scheduled and unscheduled requests is essential. I maintain a master dataset that is updated monthly, so when an unexpected request arrives, the baseline analysis is already current and only requires extension to the requested cutoff date. This reduces response time from several days to roughly half a day for straightforward queries. The biggest operational risk is staff turnover. Cumulative analysis methodology is often embedded in individual knowledge rather than institutional documentation. When the person who knows how the aggregation scripts work leaves the company, the entire process stalls. I recommend maintaining a living methodology document that covers data sources, validation procedures, table specifications, and common troubleshooting steps. This document should be updated each reporting cycle and accessible to anyone who might need to carry the work forward. It is the single most effective practice I have seen for maintaining continuity in pharmacovigilance operations. There is no universal template that fits every product, but the structural expectations are remarkably consistent across health authorities. Define your scope. Present your data. Explain your methods. Discuss your findings. Acknowledge your limitations. Follow this sequence and the resulting document will meet the basic requirements regardless of therapeutic area or jurisdiction. Deviating from it requires a documented justification.