
Understanding Lymph Nodes In Arms
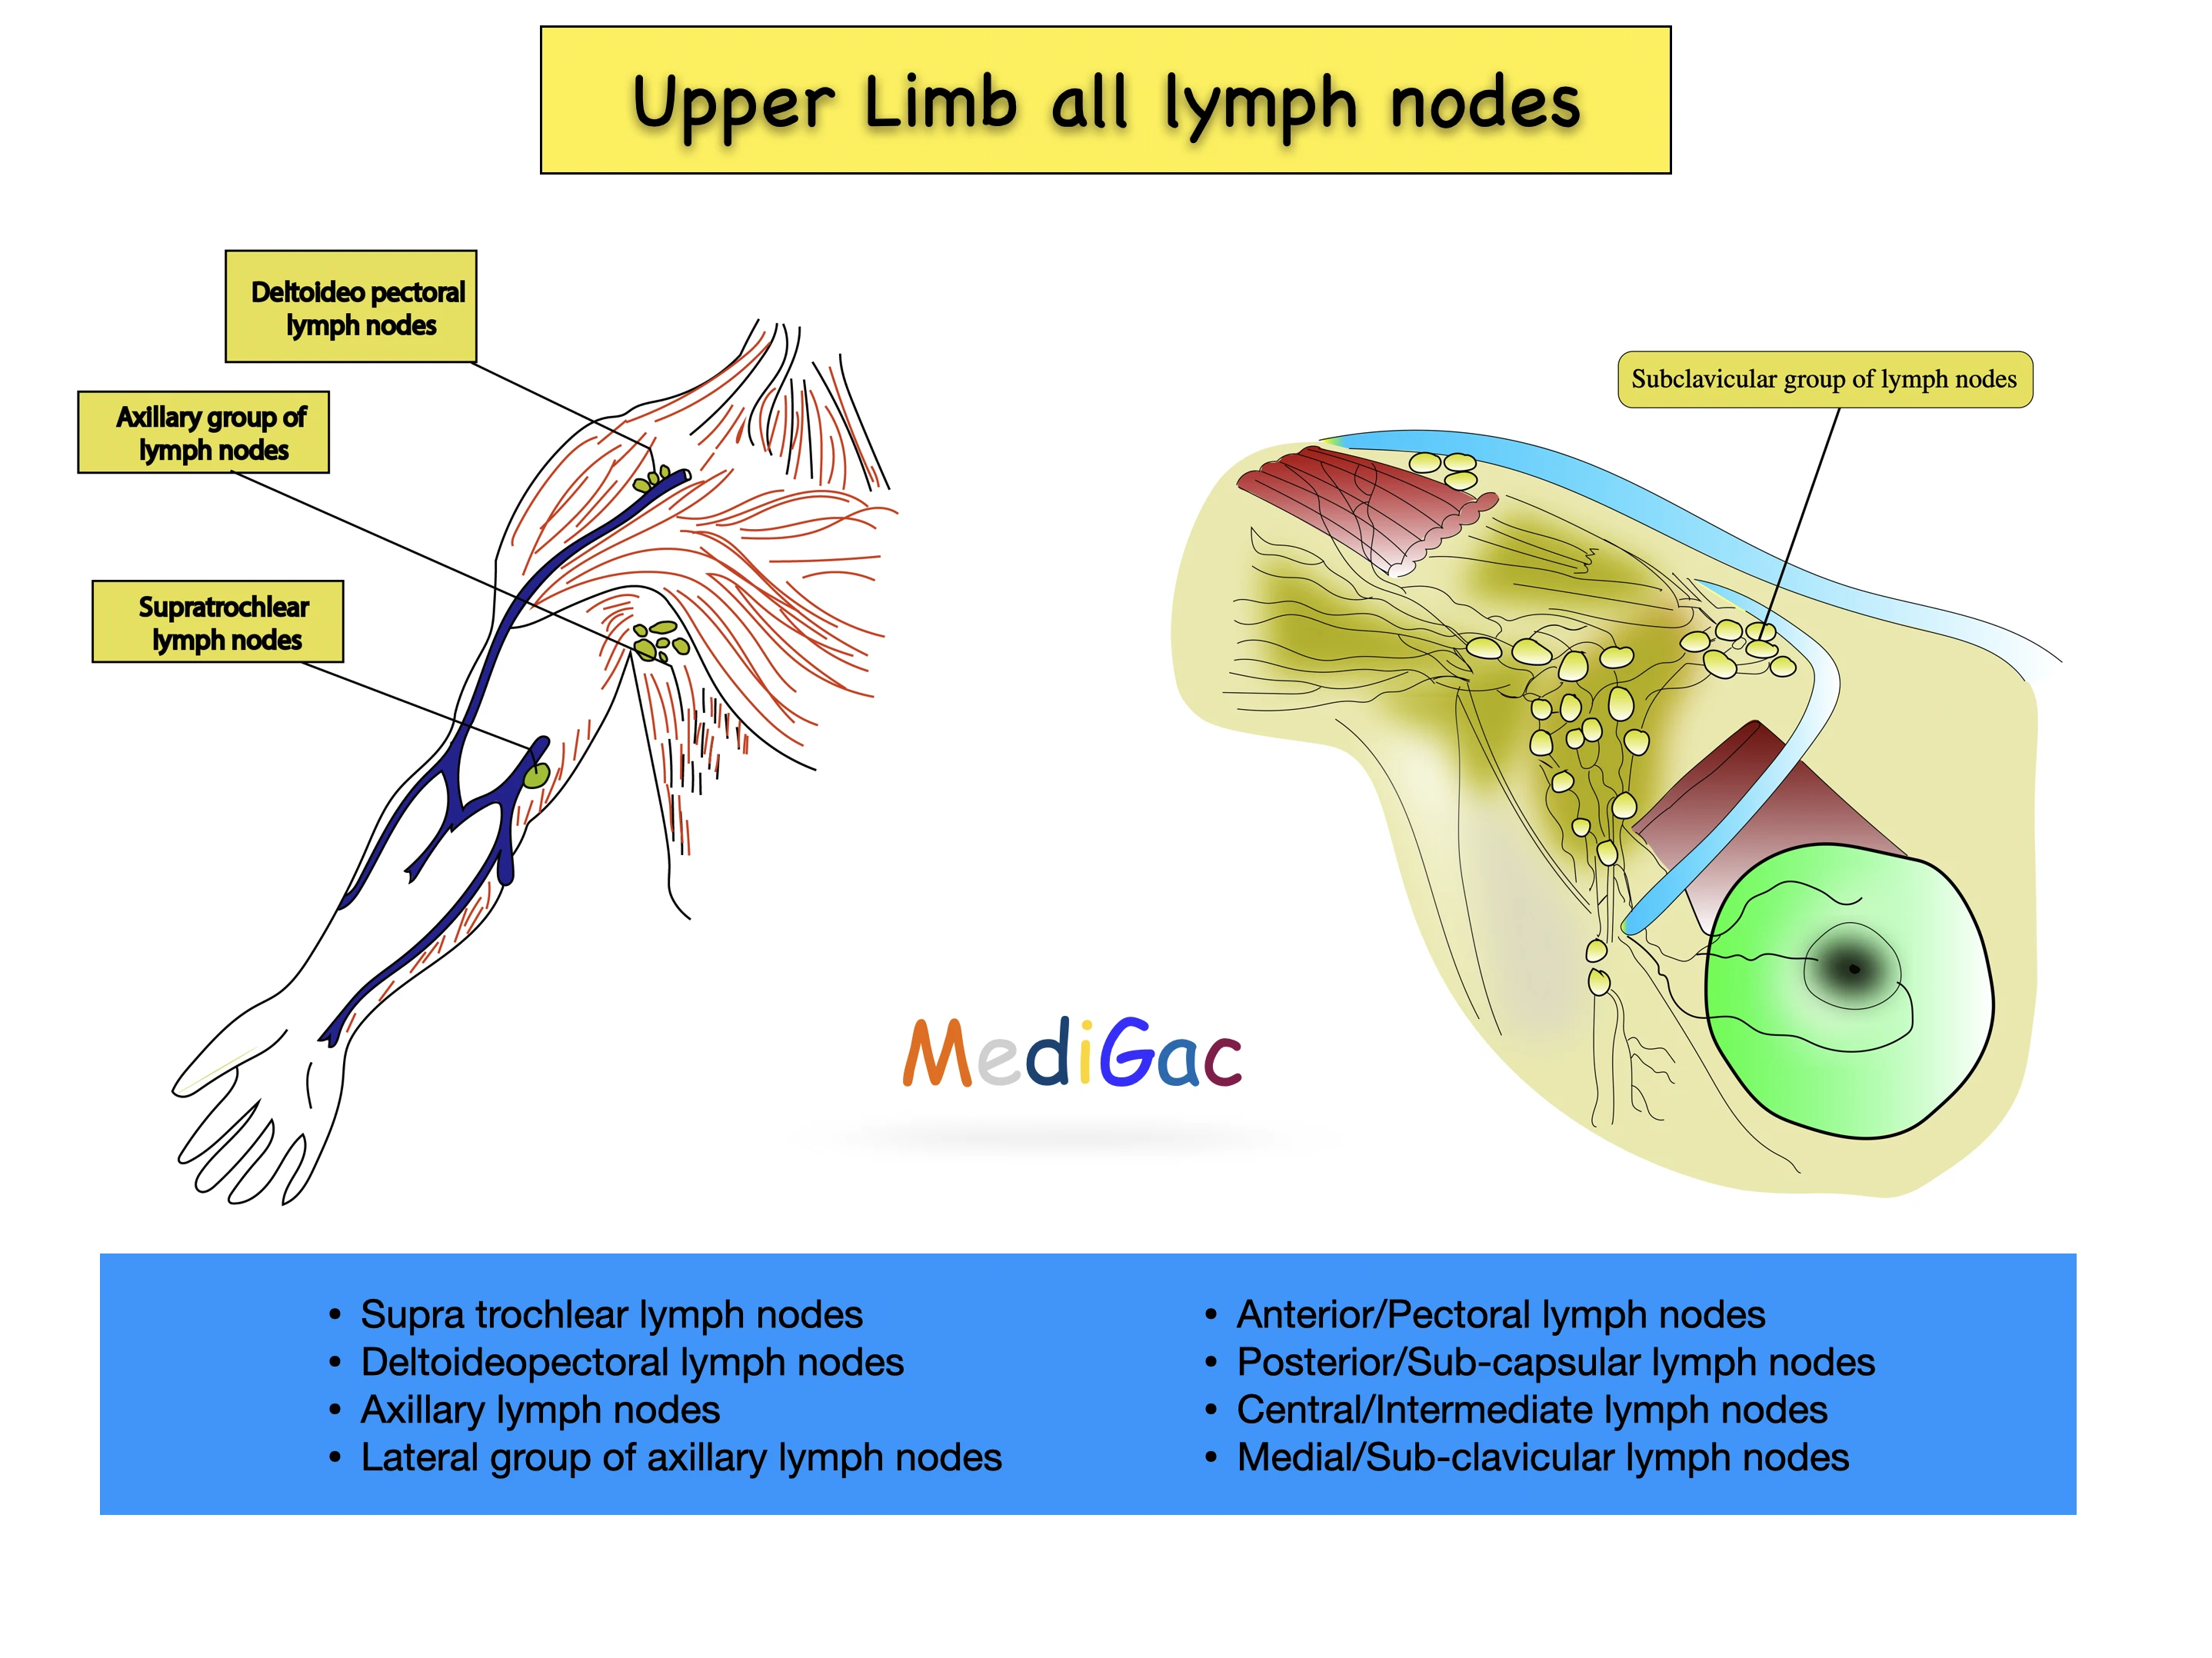
Lymph nodes in your arms are part of the drainage system that returns interstitial fluid to your bloodstream. They sit mainly in two clusters: the epitrochlear nodes near the inner elbow and the axillary nodes under the shoulder. Most people never notice them unless something triggers swelling. They filter lymph fluid, trap pathogens, and activate immune responses. The axillary nodes handle drainage from the arm, chest wall, and breast tissue on that side. The epitrochlear nodes cover the forearm and hand. When you get an infection in your left hand, for example, the left axillary chain is the first place the immune response concentrates. I work in immunology research and have handled dozens of cases where arm lymphadenopathy presented atypically. One patient came in with persistent epitrochlear swelling that everyone initially dismissed as a reactive node from a minor cut on her finger. It turned out to be a low-grade lymphoma presenting years before any systemic symptoms. The lesson was simple: persistent unilateral epitrochlear enlargement over four weeks always warrants imaging, regardless of how benign the story sounds.
How to Check Your Own Arm Lymph Nodes
You can palpate these nodes yourself. Use the pads of your fingers, not your thumbs, and apply moderate pressure. For the axillary nodes, lift your arm slightly and reach into the armpit. Feel for the natural crease and press gently in a circular motion. Normal nodes are smaller than a centimeter, mobile, and non-tender. Anything larger than that, fixed to surrounding tissue, or persistently tender should be evaluated. For the epitrochlear nodes, bend your elbow to about ninety degrees and press just above and medial to the medial epicondyle. These are harder to feel in most people. If you can distinctly palpate an epitrochlear node, that is clinically significant by definition, even if it feels small.
Common Causes of Arm Lymph Node Swelling
Reactive lymphadenopathy is by far the most common cause. Skin infections, cat scratch disease, recent vaccinations in the same arm, and even aggressive exercise can all trigger temporary enlargement. Vaccination-related lymphadenopathy typically appears within two weeks and resolves on its own, though it can persist for months in rare cases. More serious causes include lymphoma, metastatic cancer from the breast or melanoma on the same side, and autoimmune conditions like rheumatoid arthritis. The pattern matters. Bilateral symmetric enlargement points toward systemic causes. Unilateral painful swelling leans toward infection. Unilateral painless firm enlargement is the pattern that worries clinicians most.
Get the Full Details
When to Worry About Lymph Nodes In Arms
There is no single threshold that guarantees danger, but certain combinations increase risk. Nodes larger than two centimeters, hard or fixed to underlying tissue, present for more than four weeks without improvement, and accompanied by fever, night sweats, or unexplained weight loss should always be investigated. I have seen cases where the only clue was a single node that felt like a small marble but grew steadily over three months. Conversely, nodes that are soft, mobile, and tender are usually reacting to something benign. Pain itself is often a reassuring sign, not a warning. The immune response releases prostaglandins and bradykinin into the nodal capsule, and that stretches the sensitive fibrous covering. That stretching creates the tenderness.
Diagnostics You Might Encounter
A basic workup usually starts with blood work and an ultrasound. Ultrasound can distinguish between benign reactive morphology and suspicious features like loss of the fatty hilum, rounded shape, or abnormal vascularity. If ultrasound is indeterminate or clinical suspicion remains high, a core needle biopsy or excisional biopsy is the next step. Excisional biopsy remains the gold standard for diagnosing lymphoma because it preserves the nodal architecture. I once spent a week trying to interpret an ultrasound report that described a node as borderline. The measurements were only slightly off from normal. We watched it for six weeks, and it resolved completely. Sometimes the most appropriate action is simply not to intervene prematurely.
Treatment Depends Entirely on the Cause
Reactive nodes need no treatment beyond addressing the underlying trigger. Antibiotics for bacterial infection, time for viral causes, and observation for post-vaccination swelling. If an autoimmune condition is driving the enlargement, treating that condition usually shrinks the nodes back down. Malignant causes require oncology involvement. Lymphoma protocols vary widely depending on the subtype. Metastatic nodes from solid tumors are managed by treating the primary cancer and sometimes by node-directed radiation. I have never seen a swollen lymph node from metastatic breast cancer shrink without addressing the breast primary, and chasing the node alone is a well-known pitfall.

What Not to Do
Do not repeatedly massage or squeeze swollen nodes. That mechanical irritation can worsen inflammation and make assessment harder. Do not apply heat for extended periods unless a clinician has ruled out malignancy, because increased blood flow could theoretically aid tumor spread in rare scenarios. Do not assume that a shrinking node means everything is fine if the underlying cause was never identified. And do not rely on internet symptom checkers to triage lymphadenopathy. The differential is too broad and the consequences of missing a malignancy are too severe. A clinician with a history and a physical exam will catch patterns that algorithms consistently miss.
Bottom Line
Arm lymph nodes are meaningful but not inherently alarming. Most swelling resolves without intervention. The key is knowing when to escalate. Persistent, painless, firm enlargement, especially in the axilla or epitrochlear region, deserves proper evaluation. Anything else is worth monitoring and reassessing at a reasonable interval.


