Writing a Nursing Care Plan for Decreased Cardiac Output
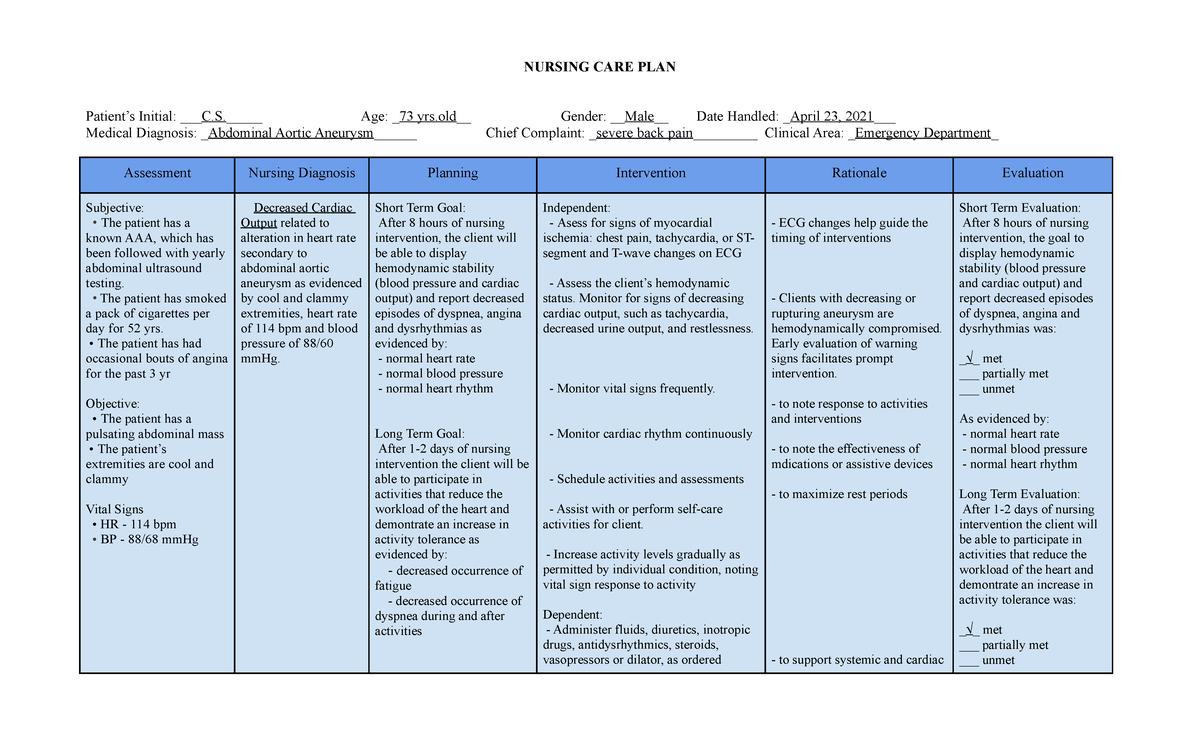
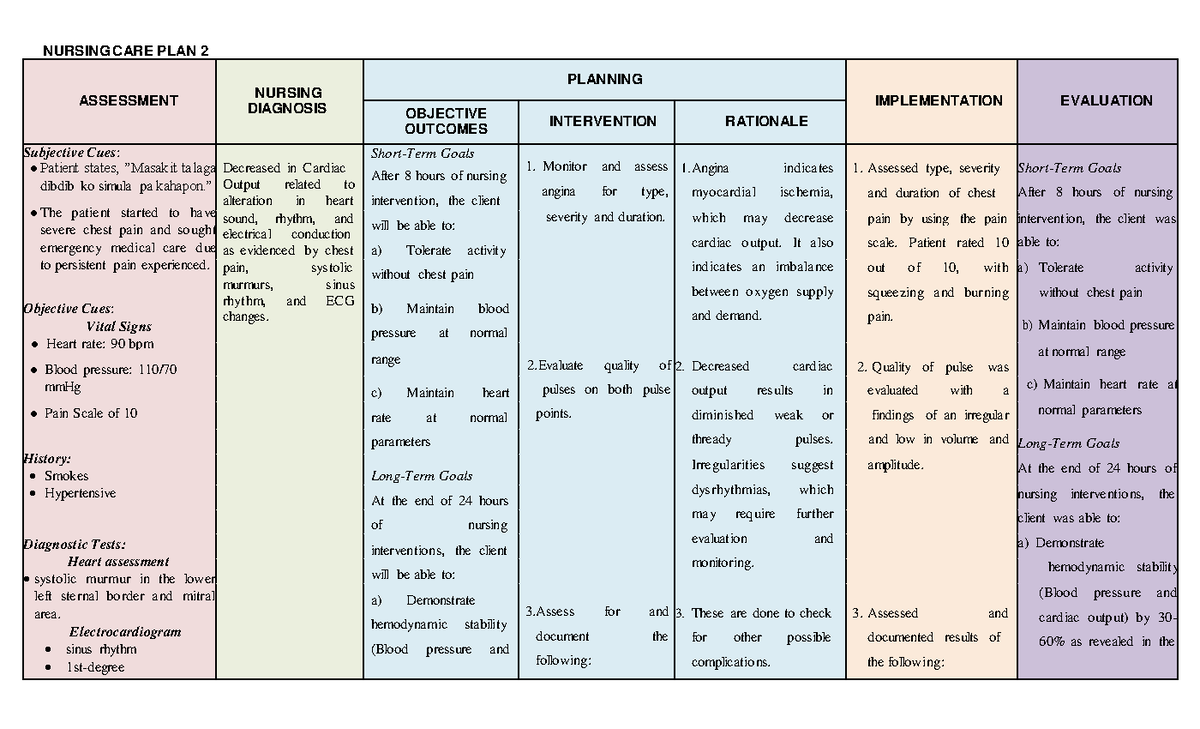
A nursing care plan for decreased cardiac output isn't rocket science, but it's also not something you can just fill in from a template and call it a day. I've graded too many of these where students slapped together generic nursing interventions that had nothing to do with the actual patient in front of them. Let me walk through how this actually works in practice. Start with the diagnosis. Decreased cardiac output is defined as the inability of the heart to pump enough blood to meet the body's metabolic needs. It's a NANDA-I approved nursing diagnosis. You'll see it coded as 00028 if you're using the NANDA system properly. The "as evidenced by" or defining characteristics section is where most people mess up. You need actual clinical data. Tachycardia, hypotension, dyspnea, fatigue, decreased urine output, cool clammy skin, altered level of consciousness, peripheral edema, crackles in the lungs, elevated jugular venous distention. Pick what matches your patient. Don't copy-paste the entire list just because it looks thorough. If the patient doesn't have crackles, don't list them as a defining characteristic. That's not how evidence-based documentation works.
Here's a specific problem I ran into recently. A student turned in a care plan for a post-MI patient that listed "decreased cardiac output" with pulse of 52 bpm and BP 90/60 as the evidences. Normal cardiac output presentation includes tachycardia, not bradycardia. Bradycardia with those vitals in a post-MI patient points to a different problem entirely — possible heart block or medication effect. I marked it down hard because the care plan was internally contradictory. The workaround is simple: know your pathophysiology before you write the plan. Look at the patient's actual vitals and medications and build from there, not from a textbook list.
Expected Outcomes That Actually Mean Something
Goals need to be measurable and time-bound. Generic goals like "patient will have improved cardiac output" are useless. Instead, specify what improvement looks like numerically. Blood pressure maintained within normal range, heart rate between 60 and 100 beats per minute, urine output greater than 30 mL per hour, patient reports decreased shortness of breath after walking to the bathroom, clear lung sounds on auscultation, normal peripheral pulses, improved skin temperature and color. The timeframe matters too. Short-term goals should be achievable within hours or a day. Long-term goals might span days to weeks depending on the condition. A post-op cardiac surgery patient and a CHF exacerbation patient will have very different timelines. Don't set outcomes that are impossible to measure. "Patient will feel better" is not a valid outcome statement.
Get the Full Details
Interventions and Rationales
This is the core of the care plan. Each intervention needs a rationale that shows you understand why you're doing it, not just that you copied it from somewhere. Monitor vital signs and hemodynamic parameters frequently. That's standard, but the rationale isn't just "to assess cardiac function." It's because changes in blood pressure, heart rate, and rhythm are often the earliest indicators of declining cardiac output, sometimes appearing before oxygen saturation drops or the patient reports symptoms. Early detection buys you time to intervene before things deteriorate further. Administer prescribed medications. Diuretics reduce preload and decrease the workload on the heart. Vasodilators reduce afterload, making it easier for the heart to eject blood. Inotropes like digoxin or milrinone increase contractility. Antiarrhythmics maintain sinus rhythm, which is important because loss of atrial kick can reduce cardiac output by up to 20 to 30 percent. The rationale for each medication should be specific to the drug class and the patient's condition. Don't just write "administer lasix" without explaining why diuresis is indicated.
Position the patient appropriately. Semi-Fowler's or high-Fowler's position decreases venous return and reduces preload, which can help in acute pulmonary edema. But this is not universal. A hypotensive patient with low cardiac output may actually benefit from Trendelenburg or passive leg raise to increase venous return. I've seen care plans blindly copy-paste Fowler's position without considering the patient's blood pressure status. That's dangerous thinking. Always consider the hemodynamic profile before deciding on positioning. Monitor intake and output strictly. Fluid balance is directly related to cardiac preload. The margin between adequate perfusion and volume overload is razor-thin in these patients. Daily weights are more reliable than fluid balance charts alone because they detect subtle changes. A two-pound gain over 24 hours usually means roughly one liter of fluid retention. Early recognition of fluid overload prevents emergency situations down the line. Limit activity as needed. The compromised heart can't increase cardiac output to meet increased demand. Activity intolerance is a direct consequence. Oxygen administration during activity, gradual progression of mobilization, and clustering care to allow rest periods are all practical interventions. Energy conservation techniques matter. A patient who walks across the room to eat breakfast may not have the cardiac reserve to digest that meal properly.
Common Pitfalls
One thing beginners consistently get wrong is prioritization. Decreased cardiac output often coexists with other diagnoses like impaired gas exchange, excess fluid volume, and activity intolerance. These aren't separate problems to list in isolation. They're interconnected. Fluid overload causes pulmonary congestion, which impairs gas exchange, which increases cardiac workload, which worsens the decreased cardiac output. It's a cycle. Your care plan should reflect this relationship, not treat each diagnosis as a standalone item on a checklist. Another pitfall is interventions that aren't nursing-appropriate. Ordering medications, adjusting IV rates, or changing physician orders are medical interventions, not nursing interventions. You can administer and monitor, but you don't independently prescribe. I've seen care plans that include "administer furosemide 40 mg IV push" without a physician's order in the rationale section. That doesn't fly in clinical practice. Documentation quality is also a frequent issue. Care plans are clinical tools, not homework assignments. Every intervention should be something you could realistically implement with the resources available in a general medical-surgical unit. Don't include interventions requiring specialized equipment or protocols unless the patient is actually in an ICU setting. I had a student list invasive hemodynamic monitoring with a Pulmonary Artery Catheter as a nursing intervention on a floor patient care plan. Unless the patient is in the CCU with a valid order, that's not happening. Stick to non-invasive monitoring: ECG telemetry, pulse oximetry, capillary refill, peripheral pulses, skin assessment, respiratory assessment.

What This Approach Won't Do
A well-written nursing care plan won't fix a patient's heart failure. It's a communication tool and a framework for nursing actions. The actual improvement comes from timely interventions, appropriate medical treatment, and ongoing reassessment. The care plan documents your thinking and ensures continuity of care between shifts. It should be living document, updated as the patient's condition changes, not something you write once and file away. A care plan that hasn't been revised in three days when the patient's condition is actively changing is outdated and potentially harmful. There's also a limit to how standardized these plans can be. Two patients with the same diagnosis can have very different underlying causes, comorbidities, and responses to treatment. A care plan for decreased cardiac output due to dilated cardiomyopathy looks different from one due to acute myocardial infarction or valvular heart disease. Context matters. The framework is the same, but the specific interventions, priorities, and outcomes will vary based on etiology and clinical presentation.