Working with Dense Regular Elastic Tissue in Histology
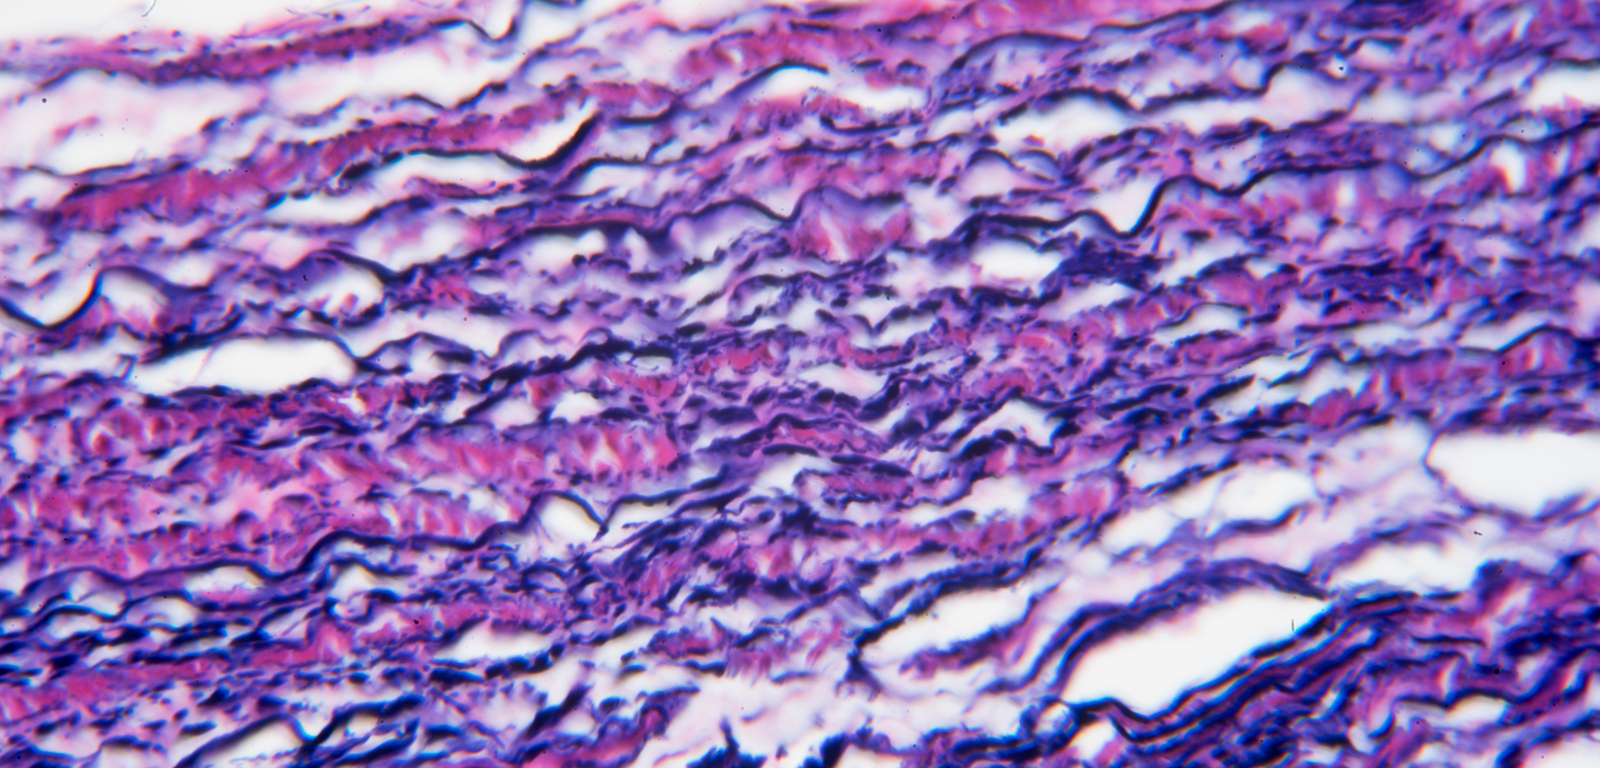
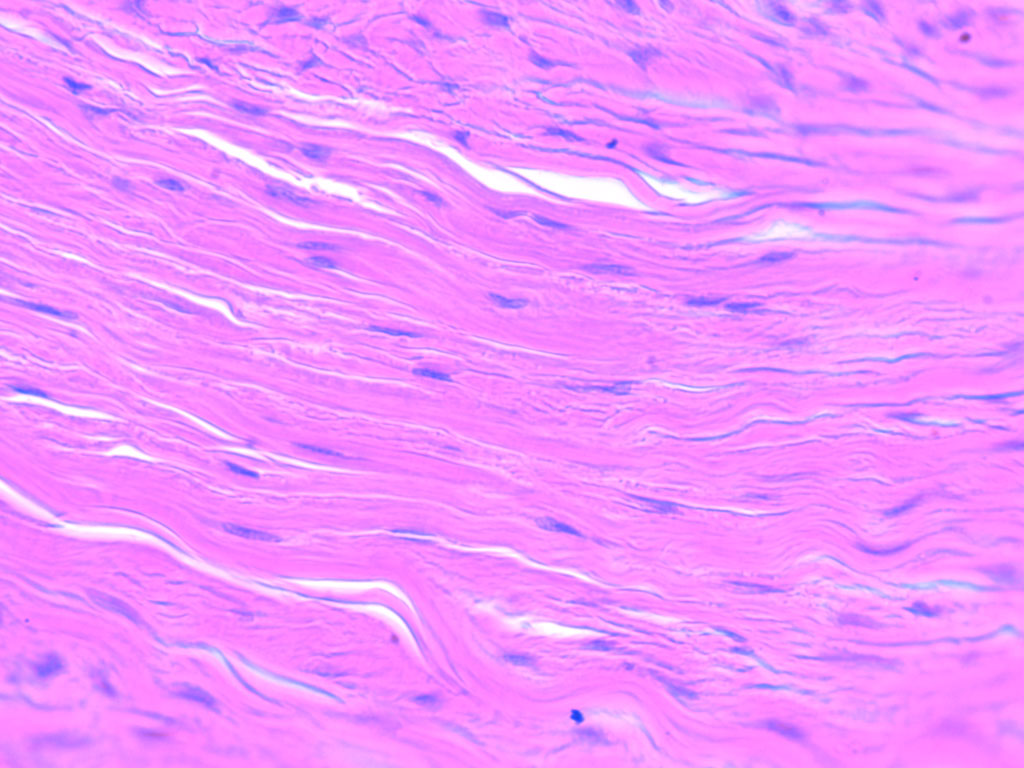
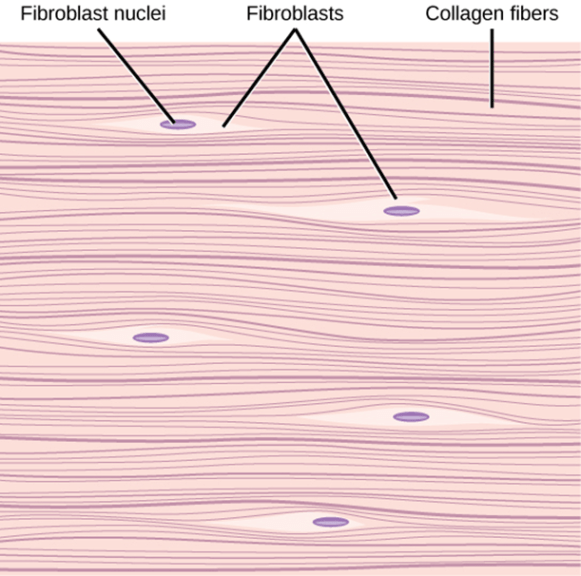
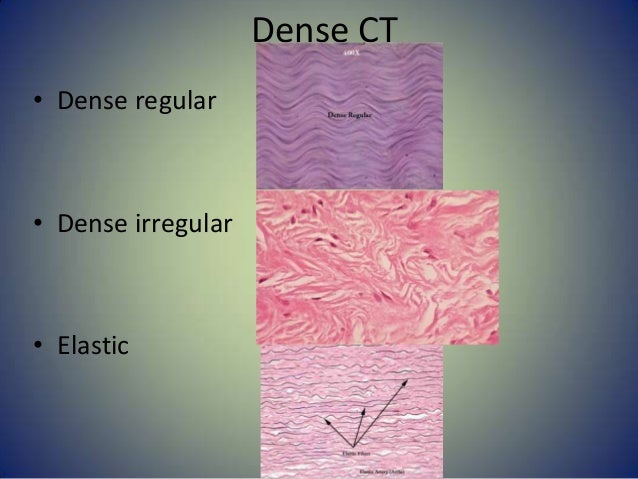
I have spent years preparing and reviewing sections of dense regular elastic tissue. It shows up mostly in ligamentum flavum, the walls of large elastic arteries, and the vocal ligaments. The problem is that it looks straightforward under a low-power scan and then becomes a nightmare once you start grading or measuring anything meaningful. The fibers are densely packed, highly aligned, and full of elastin, which means standard H&E staining alone will not give you a clean picture. This tissue type combines two features that usually conflict with each other. It is dense, meaning collagen fiber bundles are packed tightly together in parallel arrays. It is also elastic, meaning elastic fibers run alongside those collagen bundles to provide recoil. Under light microscopy, that combination creates a wavy, fibrous appearance that is hard to distinguish from pure dense regular collagenous tissue unless you use the right stains. Standard H&E will make the collagen look pink and the nuclei look purple, but the elastic component blends into the background. That is why I always recommend Verhoeff-Van Gieson or Movat pentachrome when you need to evaluate the elastic architecture properly. The cells are sparse. You will see elongated fibroblast nuclei between the fiber bundles, sometimes called fibrocytes when they are less metabolically active. In ligamentum flavum, these cells are interspersed among both collagen and elastic fibers, and their distribution changes noticeably with age. That is a detail most textbooks skip over, but it matters if you are working with older specimens.
Staining Protocols That Actually Work
The most common mistake I see is using hematoxylin and eosin alone and then trying to assess elastic fiber integrity. You cannot do that reliably. The Verhoeff-Van Gieson stain is the workhorse here. It colors elastic fibers black, collagen red, and the background yellow. It takes about forty-five minutes to an hour depending on your lab conditions, and the results are consistent enough for grading. I usually run a control section of normal artery wall alongside my unknowns so I can compare staining intensity across batches. Movat pentachrome is more expensive and takes longer, roughly ninety minutes to two hours, but it gives you five different tissue components in one slide. If you need to distinguish elastic fibers from smooth muscle in a vascular specimen, this is the method I reach for. The elastic fibers stain black, smooth muscle bright red, collagen yellow, and mucin blue. It is harder to interpret at first because there is more information competing for attention, but once you get used to the color map, it saves you from running multiple separate stains on serial sections. Aldehyde fuchsin is another option, though less common in routine labs. It stains elastic fibers a deep purple and works well when you need higher contrast against a pale background. I used it once on a set of ligamentum flavum samples where the Verhoeff stain was coming out weak and inconsistent, likely due to oxidizer age. The aldehyde fuchsin gave me clear results in a single overnight incubation. Not ideal for throughput, but reliable when you need it.
A Problem I Faced and How I Solved It
I was reviewing a series of aging ligamentum flavum sections stained with Verhchool-Van Gieson, and the elastic fibers in some samples were fragmenting into fine, broken pieces rather than showing the continuous lamellar pattern I expected. At first, I assumed it was postmortem degradation, but the control sections from younger donors looked normal, and the tissue fixation times were consistent across all samples. The issue turned out to be over-decalcification. These specimens had been in a weak nitric acid decalcifying solution for about seventy-two hours, which is within the recommended range for bone, but ligamentum flavum contains calcium deposits in older patients and the decalcifier was leaching elastin along with the mineral. The workaround was simple enough: I switched to a chelating agent-based decalcifier like EDTA for future samples, even though it takes about five to seven days instead of two days. The elastic fiber architecture came back intact, and the H&E counterstain remained clean. It added a day to my workflow, but it prevented me from misdiagnosing artifactual fragmentation as pathological elastosis. One thing beginners miss is that elastic fiber density does not correlate linearly with tissue elasticity in aging specimens. In ligamentum flavum from patients over sixty, you often see increased elastin content on stain, but the fibers are fragmented and cross-linked abnormally due to advanced glycation end products. So the tissue looks denser for elastin but behaves less elastically in mechanical testing. If you are correlating histology with biomechanics, you need to account for fiber continuity, not just fiber quantity. A quick picrosirius red stain under polarized light can help you assess collagen organization separately from the elastic component. Another issue is section thickness. Dense regular elastic tissue compresses easily during microtomy. If you cut at four microns, the fibers can buckle and create artificial waviness that looks like pathology. I usually cut at six to eight microns for these specimens and use a newer blade to minimize compression artifacts. The trade-off is slightly reduced cellular detail, but you get a more accurate representation of the fiber architecture, which is what matters in most diagnostic contexts.
Get the Full Details

When This Approach Falls Short
Light microscopy staining has hard limits. You cannot resolve individual elastic microfibrils or assess the spatial relationship between elastin and fibrillin without electron microscopy. If your question involves elastin gene mutations or congenital elastic fiber disorders, histological stains alone will not give you an answer. Immunohistochemistry for elastin and fibrillin-1 is more informative in those cases, but antibody availability and cost are real constraints, and the protocols are finicky. For routine diagnostic work on adult ligaments and arteries, standard elastic stains remain sufficient, but do not pretend they are comprehensive. They are a screening tool, not a definitive characterization method.
Dense Regular Elastic Tissue in Practice
The bottom line is that this tissue is deceptively simple to identify and difficult to interpret accurately. Pick the right stain for your question, watch out for decalcification artifacts, cut thick enough to avoid compression distortion, and remember that more elastin on a slide does not always mean better function. I have seen too many slides called "normal" when the elastic architecture was quietly falling apart at the micro-level. Slow down on the staining and the sectioning, and the tissue will tell you what it is actually doing.