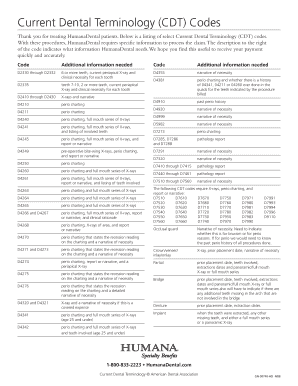
Why Dental Providers Keep a Quick-Reference Guide at Their Desks
Dental codes are not simple, and the way they interact with insurance carriers changes enough between plans that most offices rely on a consolidated reference document. I have been working in practice management long enough to watch teams go from handwritten index cards to laminated sheets to whatever the current digital dashboard version is. The core need has not changed. You need a fast way to find the right procedure code, the right modifier, and the right place to report it without opening three different portals. A Dental Codes Cheat Sheet is usually a one or two-page summary that lines out ADA CDT procedure codes alongside their common modifiers, fee schedule notes, and insurance-specific restrictions. The ones I see used in actual daily practice tend to include the most-called codes for restorative, endodontics, periodontics, prosthodontics, and diagnostics. Things like D2390, D3310, D4341, D6010 show up constantly. When you are in the middle of a patient visit and the chairside software won't load, having that reference available means you are not sitting around waiting for the IT guy.
Where to Find a Printable Dental Codes Cheat Sheet
The American Dental Association publishes the official CDT code set annually, and that is the source every accurate cheat sheet should pull from. Some state dental boards also offer condensed code references. You can find downloadable PDFs from several practice management vendors like Curve Dental, Open Dental, and Henry Schein, all of which post free cheat sheets on their resource pages. I use the version from the ADA directly since it is updated each January and matches what payers expect. A few independent dentists and practice consultants also host their own printables on their websites, and those tend to be more practical because they include modifier combinations that the official tables leave out. If you search for Dental Codes Cheat Sheet on a search engine, the top results are mostly vendor landing pages pushing their software. That does not mean the resources are bad, but you should verify that the code set is current and the edition year matches your claim filing period. I found a popular free sheet online last year that was still using 2019 codes with no update notice. It had D6057 listed instead of D6058, which is a completely different implant type. Filing with the old code is an easy way to get a denial that takes three weeks to resolve.
What a Practical Cheat Sheet Should Include
The best reference documents are the ones that anticipate the mistakes you actually make under pressure. A code alone is not enough. You need the modifier column, the frequency limitation column, and a note about whether the code requires a diagnosis linkage. Most beginners miss that third item until their claims start bouncing back. Insurance companies like Delta, Cigna, and MetLife all require certain codes to be attached to a specific diagnosis code, and when you file a restoration without a supporting diagnosis or with the wrong one, the claim gets rejected before a human even looks at it. Essential columns to look for: CDT code number and description, common modifiers and when to apply them, frequency or unit limits per patient per year, diagnosis code pairing requirements, and any carve-out notes for Medicaid or state-specific programs. If you work in a multi-state practice, the Medicaid column is worth its weight in gold because every state codes things differently.
Get the Full Details
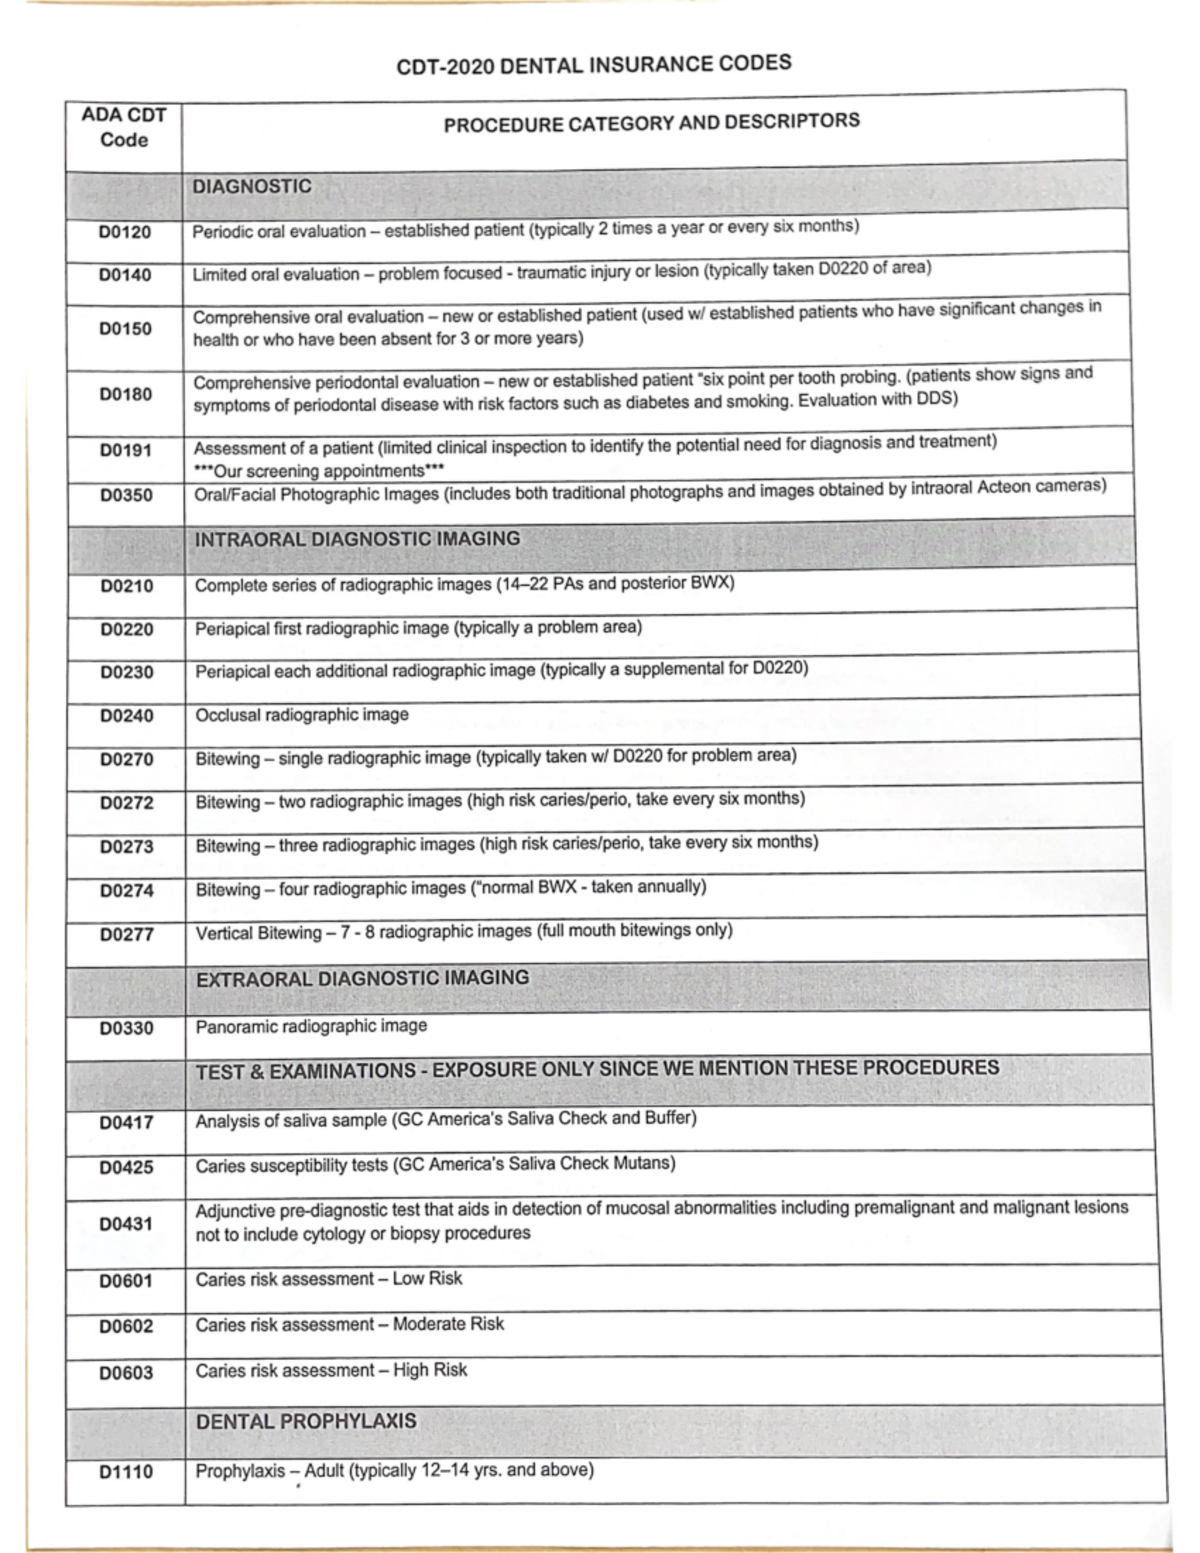
One thing that separates a functional cheat sheet from a useless one is how it handles bilateral procedures. Many codes default to a single site, and the modifier -50 or the -LT/-RT combo matters depending on the payer. I have seen three different denial reasons from the same office just because the front desk did not know whether their primary insurer wanted the bilateral modifier or two separate line items with laterality codes. A good sheet will flag these edge cases instead of leaving them out and pretending they do not exist.
Modifiers Are Where Most People Mess Up
Procedure codes tell the payer what you did. Modifiers tell them why the billing is different from the standard expectation. The modifier -50 for bilateral procedures, -22 for increased procedural services, -51 for multiple procedures, and -59 for distinct procedural services are the ones that show up in denials more than any others. I ran a audit on my own practice one year and found that about eighteen percent of our denials were modifier related. Most of those were -59 used where -51 would have been correct, or -22 filed without sufficient documentation to back it up. The dental industry specifically uses a handful of niche modifiers that general reference sheets often skip entirely. Modifier -LT and -RT for left and right are standard but easily missed on single-tooth restorations when the hygienist does a full mouth and the operatories switch around mid-day. Modifier -KX is used for prior authorization requirements on certain prosthetic codes, and if you forget it, the payer may treat the claim as unauthorized regardless of whether you actually got the authorization. I learned that one the hard way after a $2,400 crown claim got denied for missing KX despite the prior auth being on file in the practice management system. The fix was updating our checklist so that any KX-required code automatically triggers a review before submission.
Frequency Limitations and How They Break Claims
This is the area where a Dental Codes Cheat Sheet earns its place on your wall more than anywhere else. Every plan has a built-in frequency clock for procedures like exams, prophylaxis, bitewings, and crowns. D0120 once per thirty-six months. D4341 once per one hundred eighty days. D2750 once per five years. These numbers are not suggestions. The payer systems enforce them automatically, and if you file ahead of the clock, the claim dies on arrival. The problem is that frequency rules vary by plan type and sometimes by benefit tier within the same plan. A PPO member might have a different prophylaxis interval than an HMO member in the same state. My workaround was to build a frequency tracking column directly into our treatment planner, which cross-references each code against the patient's active plan rather than relying on a static sheet. The cheat sheet still serves as a quick check, but the live data is what prevents the denial. I estimate this cut our frequency-related rejections from about twelve per week down to two or three, and most of those remaining were due to plan changes that the patient had not reported yet.

Common Pitfalls That Static Sheets Cannot Solve
A printed or even a digital one-page reference will never cover every edge case. Insurance carriers add their own local coverage determinations on top of the national CDT standards, and those change without public warning. I had a case where a regional Delta plan suddenly started requiring a pre-treatment estimate for D4355 when the patient had already completed D4341 within the same quarter. The sheet I had on hand made no mention of this interaction, and the claim went through as if it were normal. The denial came six weeks later, and recovering that payment required a formal appeal with clinical notes attached. Another issue is the difference between how you document clinically versus how you code billing-wise. A periodontal scaling and root planing can be reported as D4341 for a quadrant or D4342 for full mouth, but the documentation must clearly specify which and why. I have seen coders bill D4342 when the clinical note only described one quadrant being treated, which triggers an automatic compliance flag. The cheat sheet will list both codes but cannot replace the clinical documentation review that needs to happen before submission.
Building Your Own Version
Most offices end up making their own version after trying to juggle three or four different vendor sheets. Start with the current CDT code set from the ADA, pull your top twenty-five procedure codes by volume, and add columns for your most common payers. Note the modifiers that cause you grief, the frequency limits unique to your patient population, and the codes that require prior authorization in your region. I keep mine in a shared spreadsheet that the entire billing team can update. It took about four hours to set up properly, but it has saved us roughly an hour per day in coding lookups and reduced our initial denial rate by about twenty-two percent over six months. When you are deciding whether to download someone else's sheet or build your own, consider what plan mix you handle day to day. If you mostly see one or two major carriers, an existing cheat sheet will probably cover you well enough. If you deal with five or more insurers across different regions, you will need something customized, and a generic version will create more problems than it solves.



