How To Actually Run A Determinants Of Health Assessment
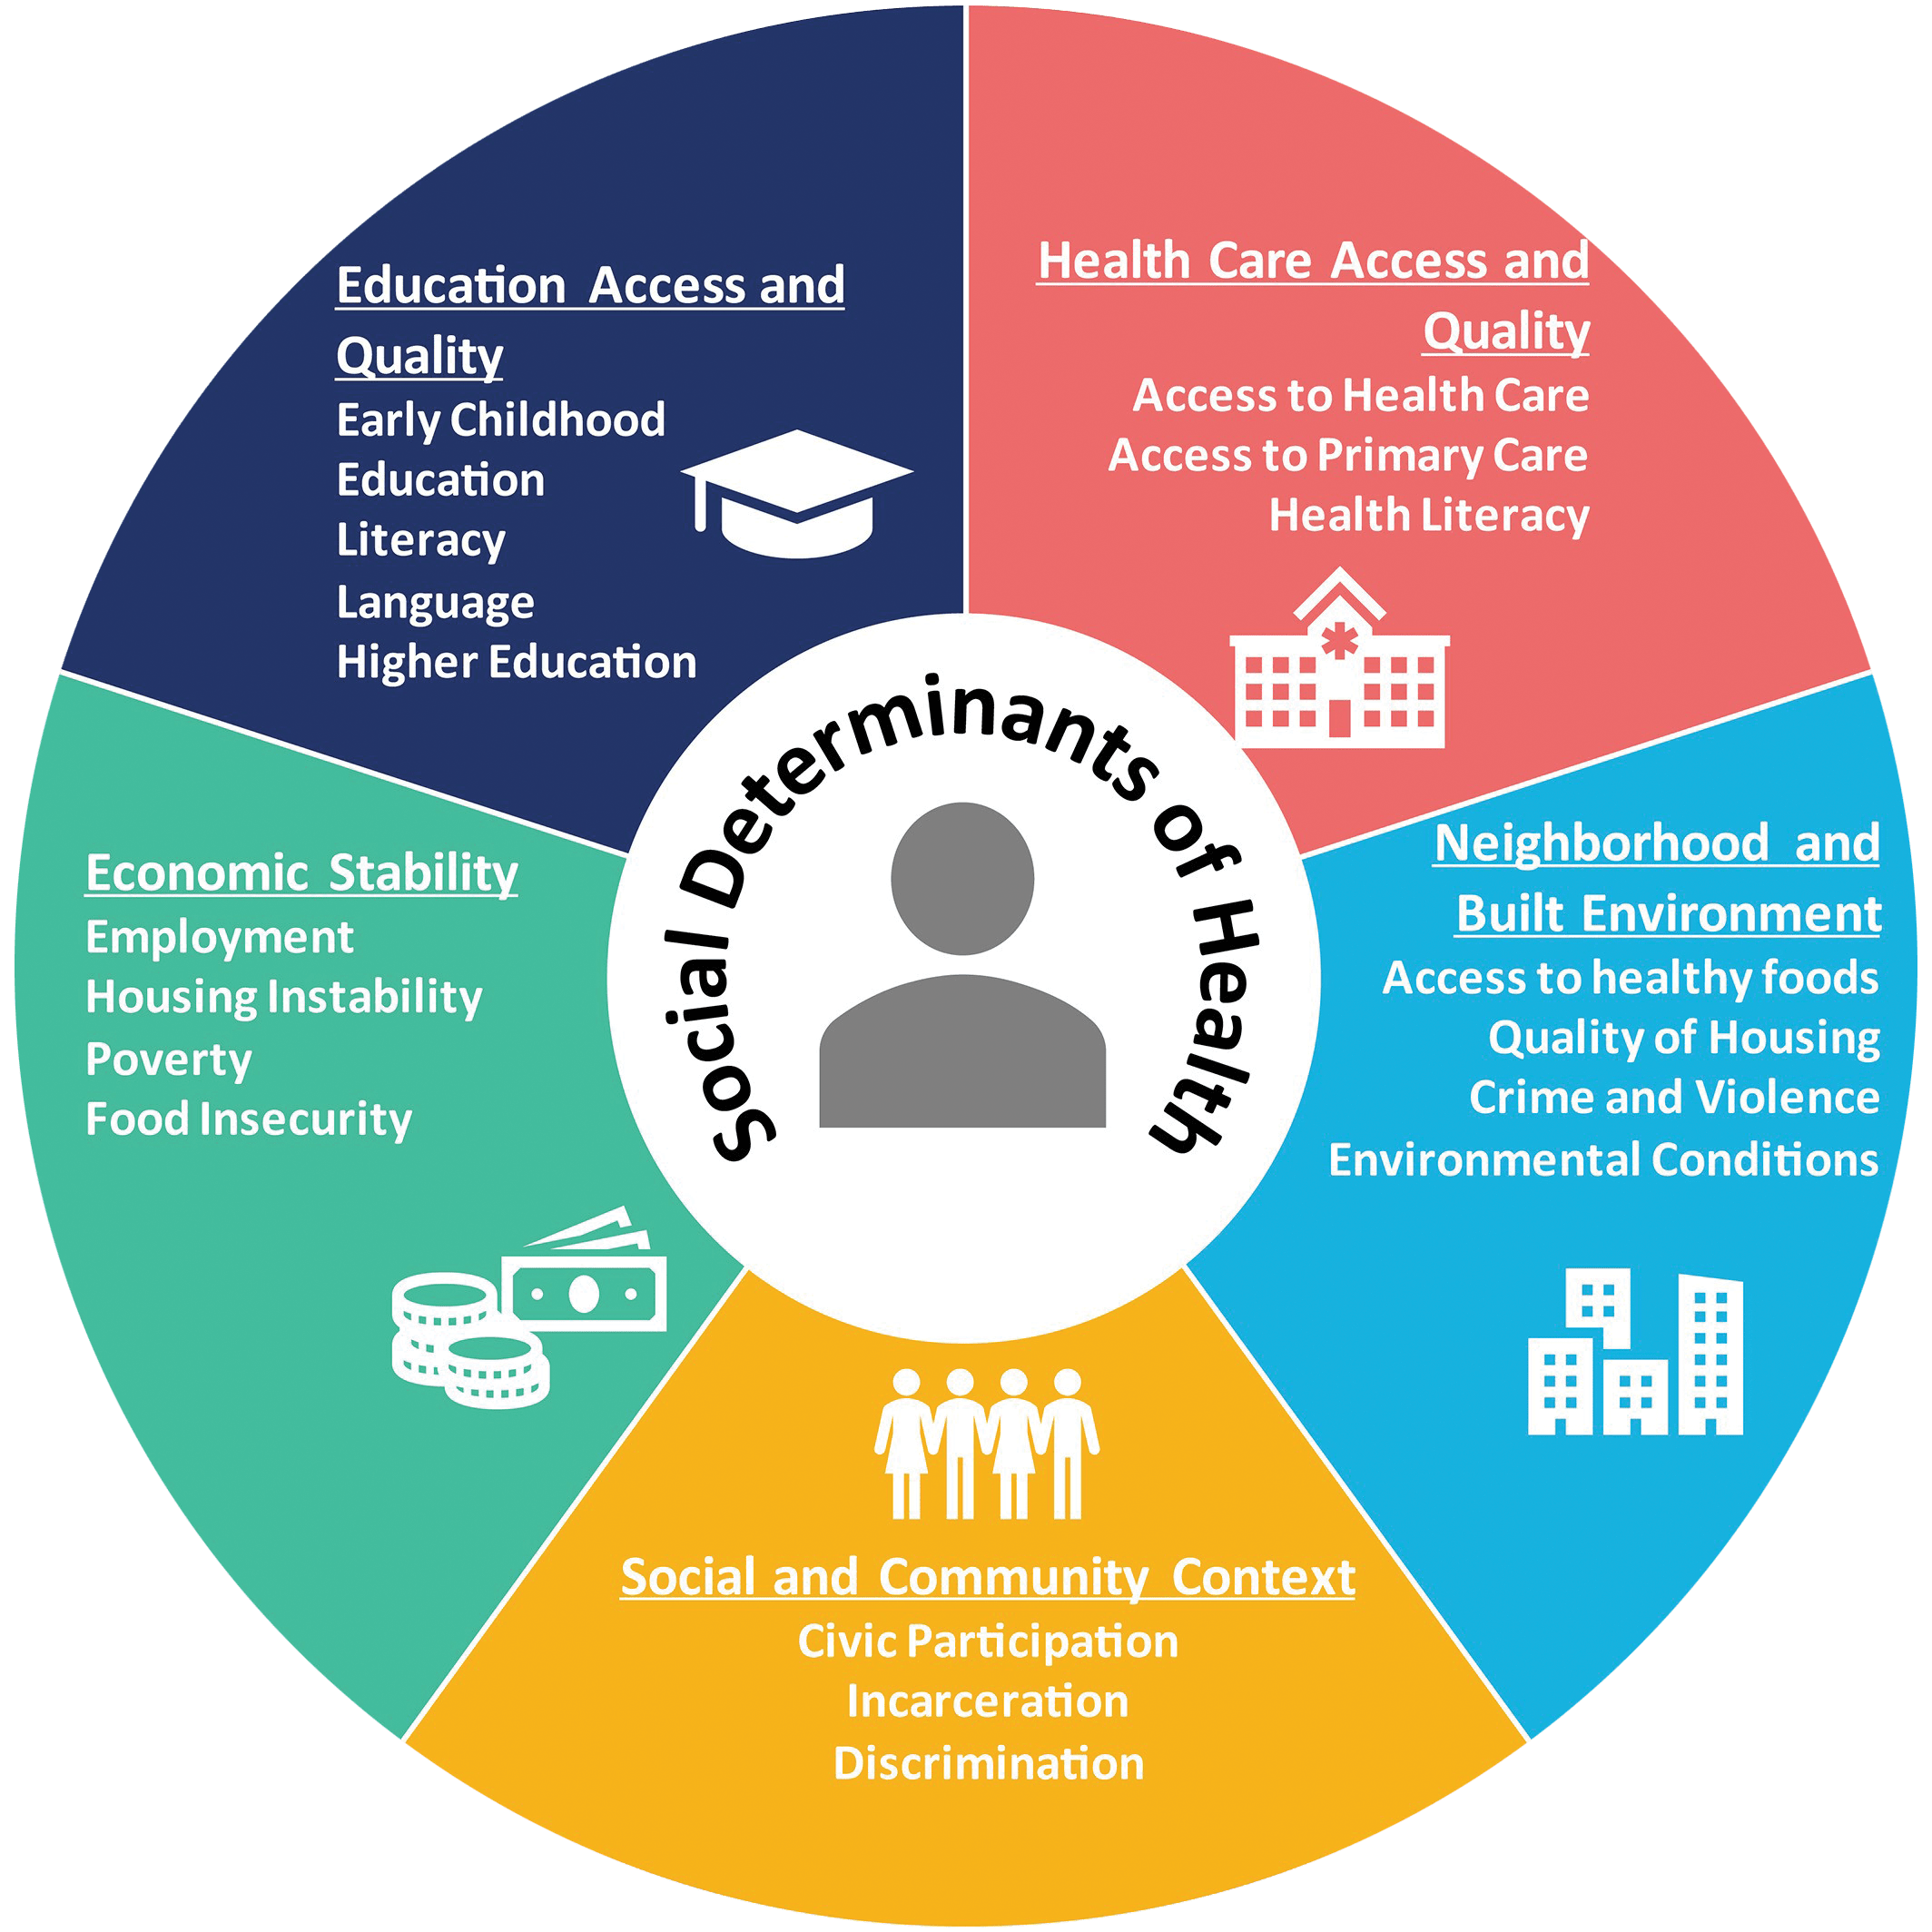
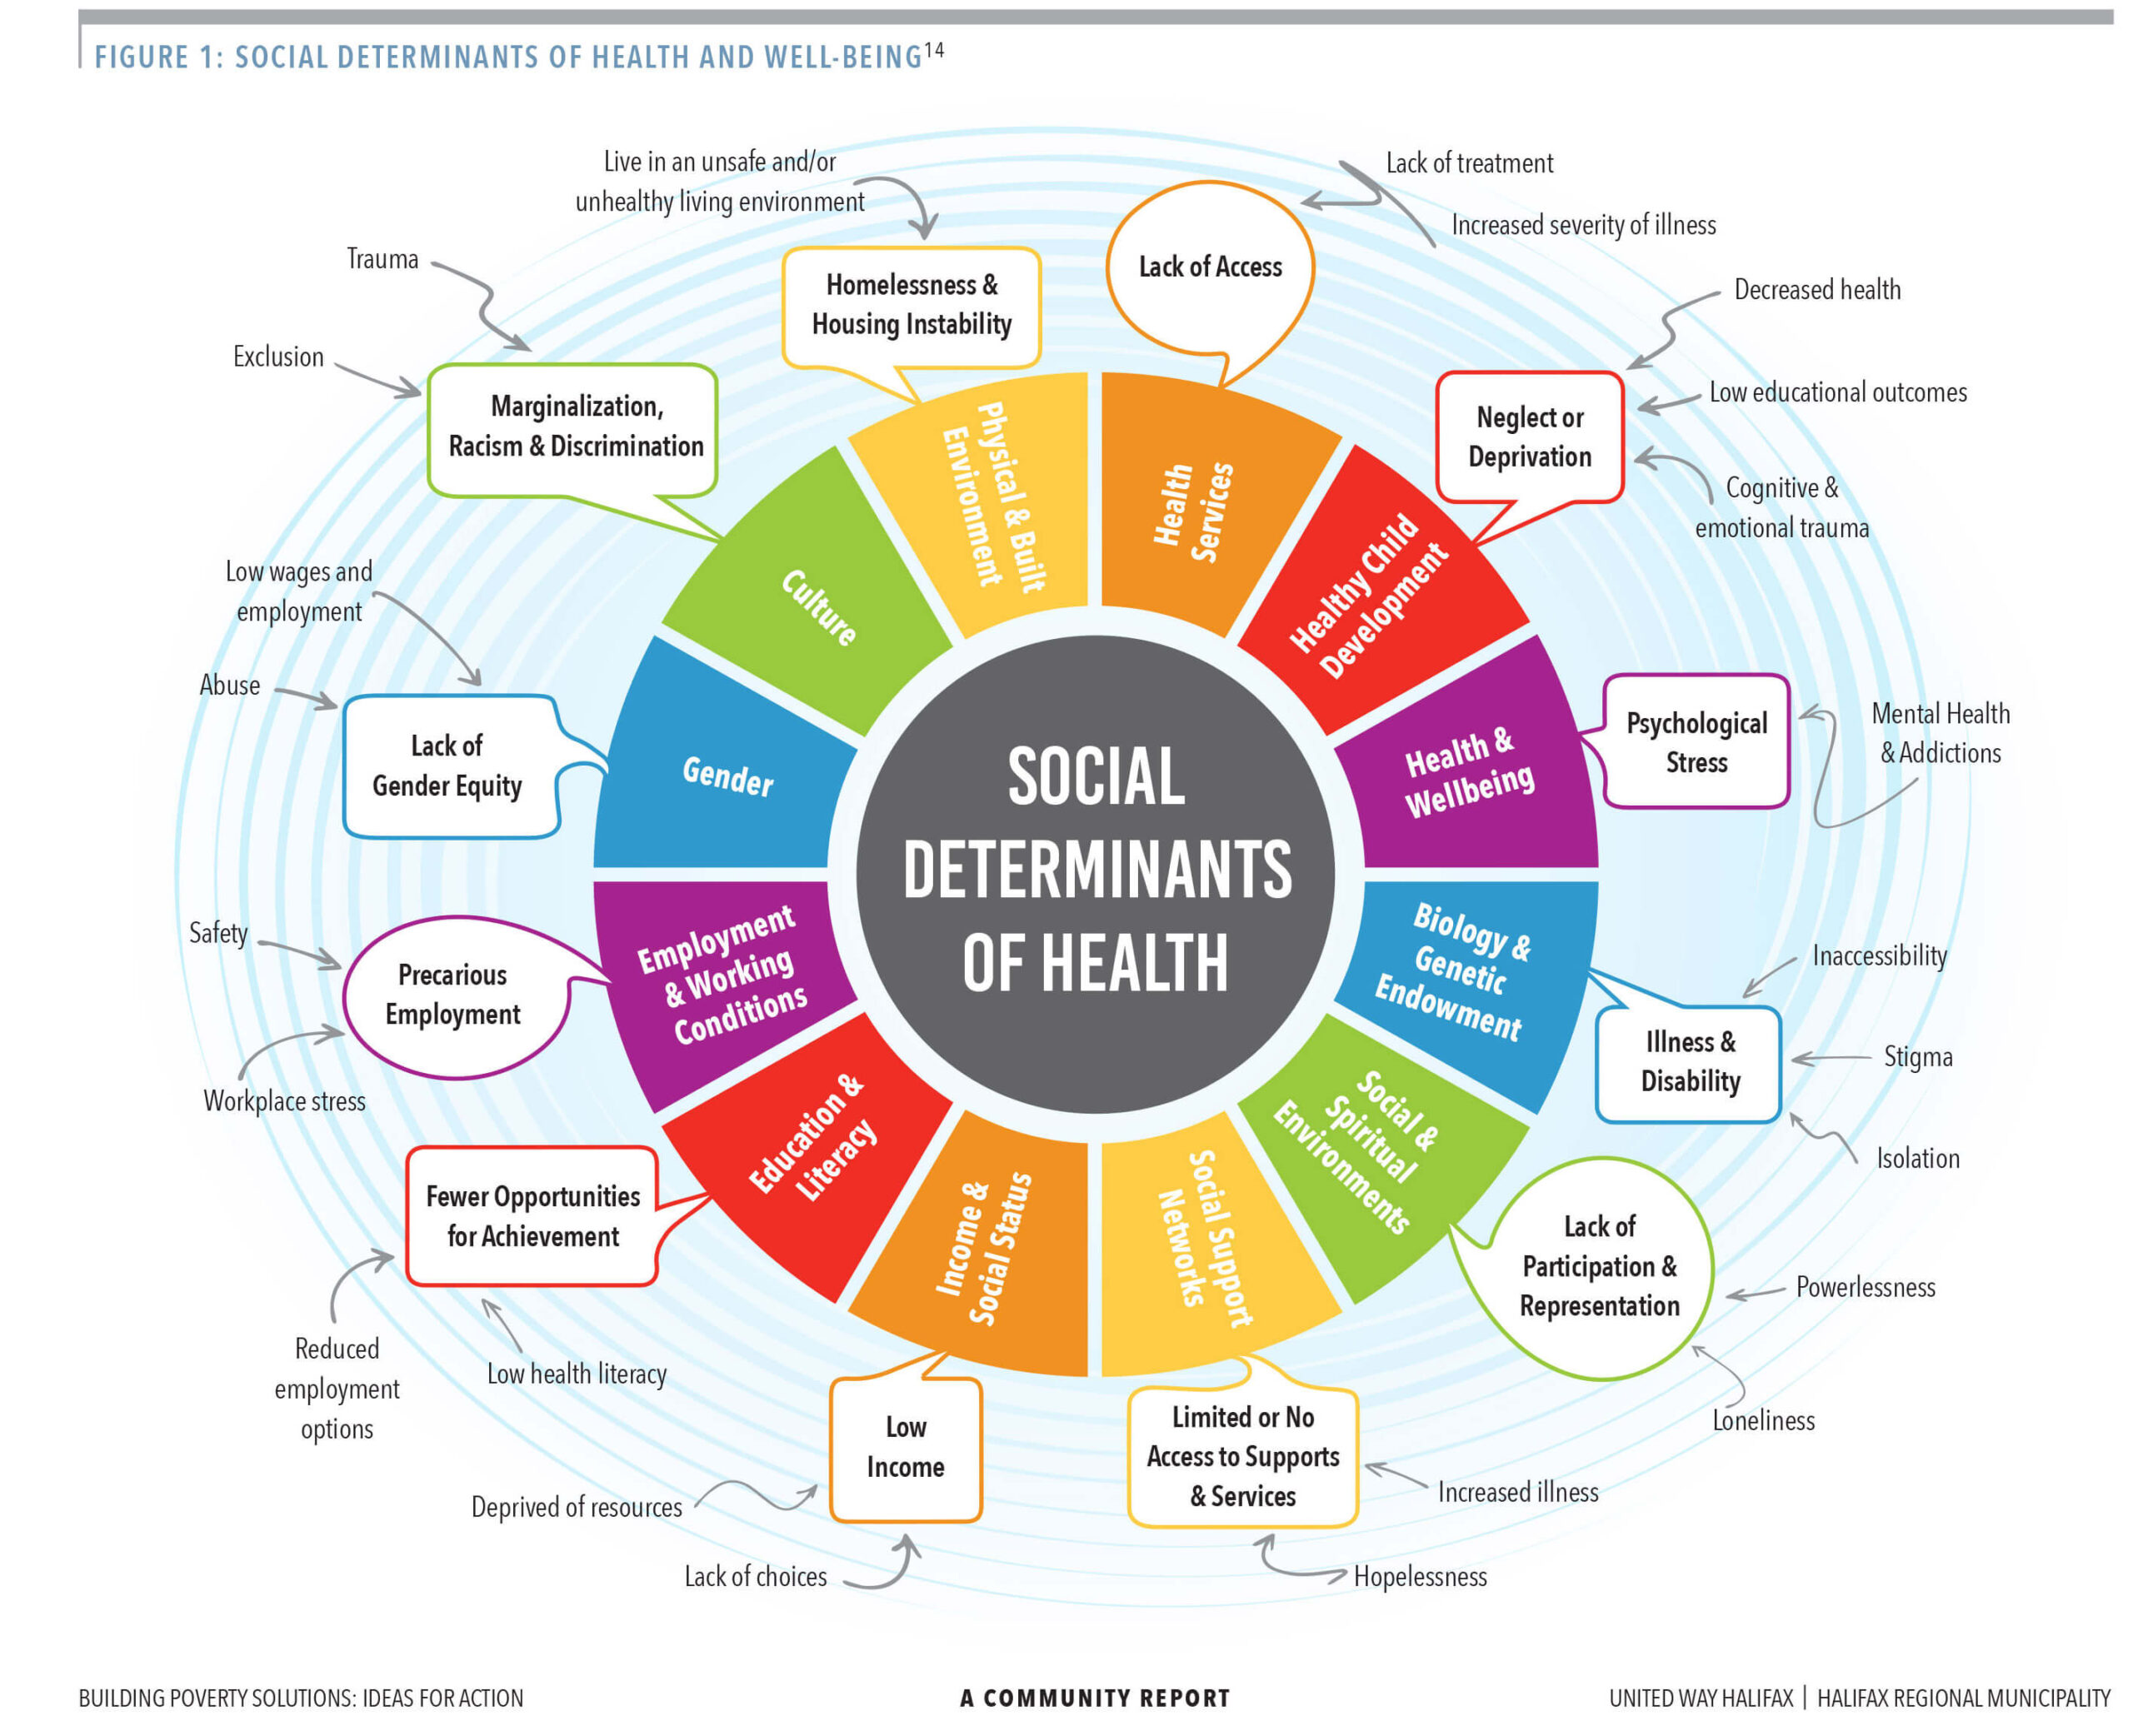
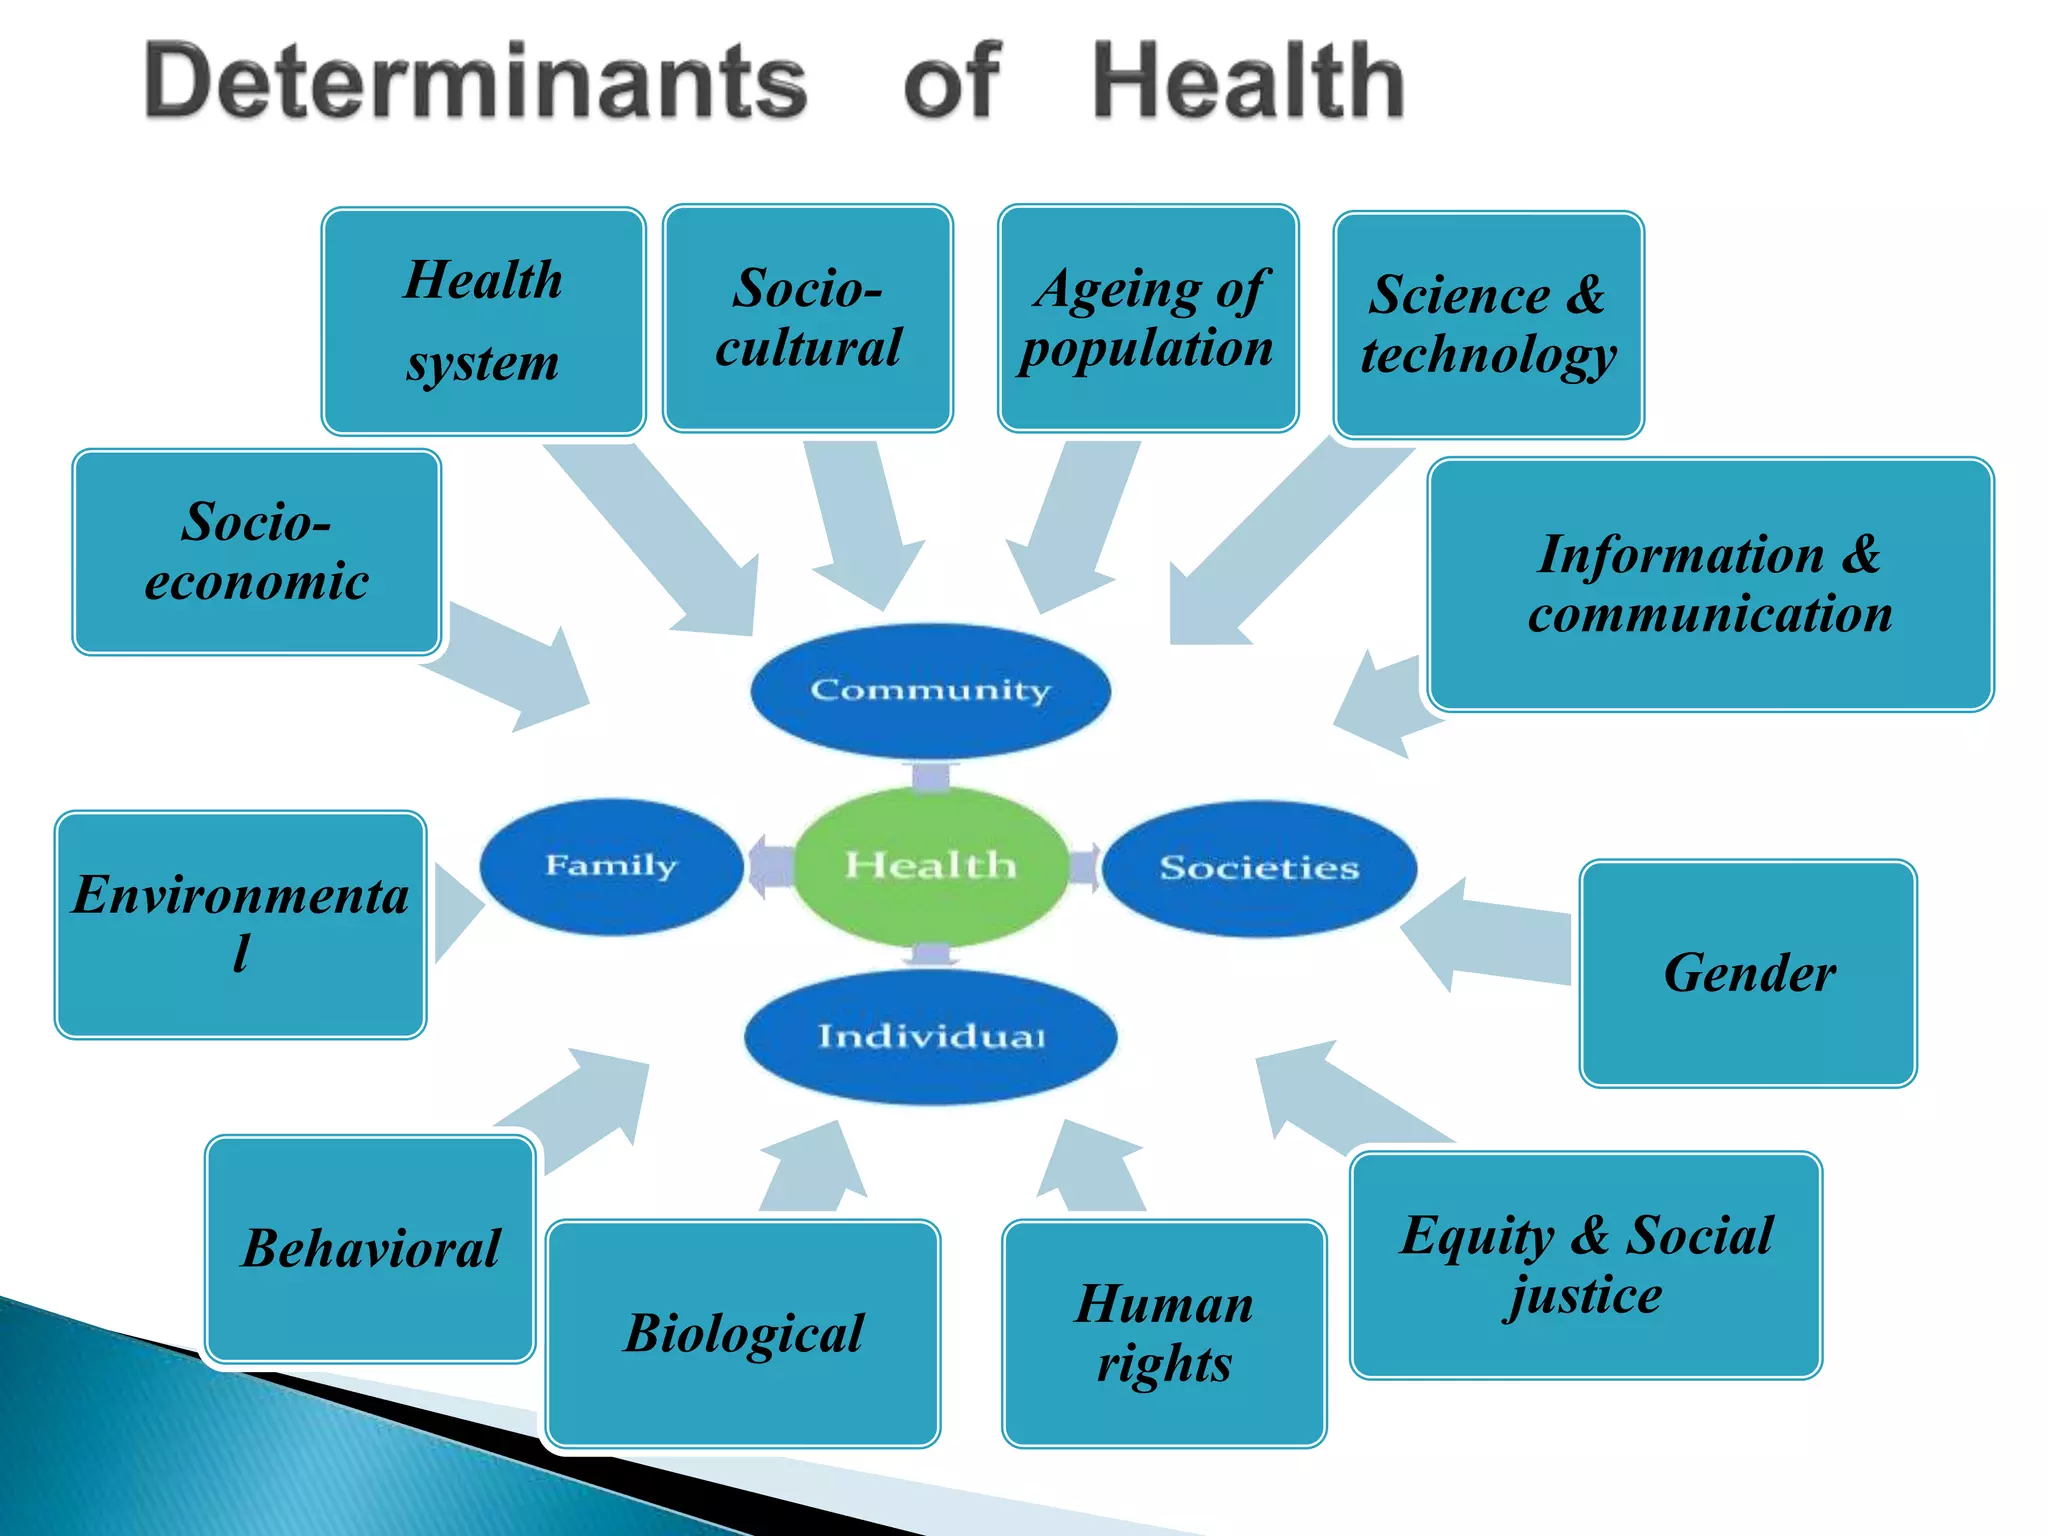
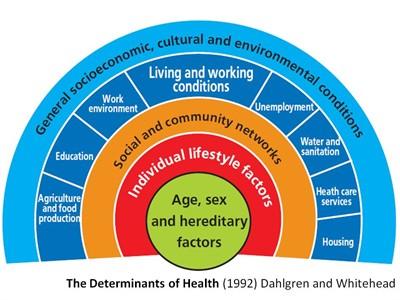
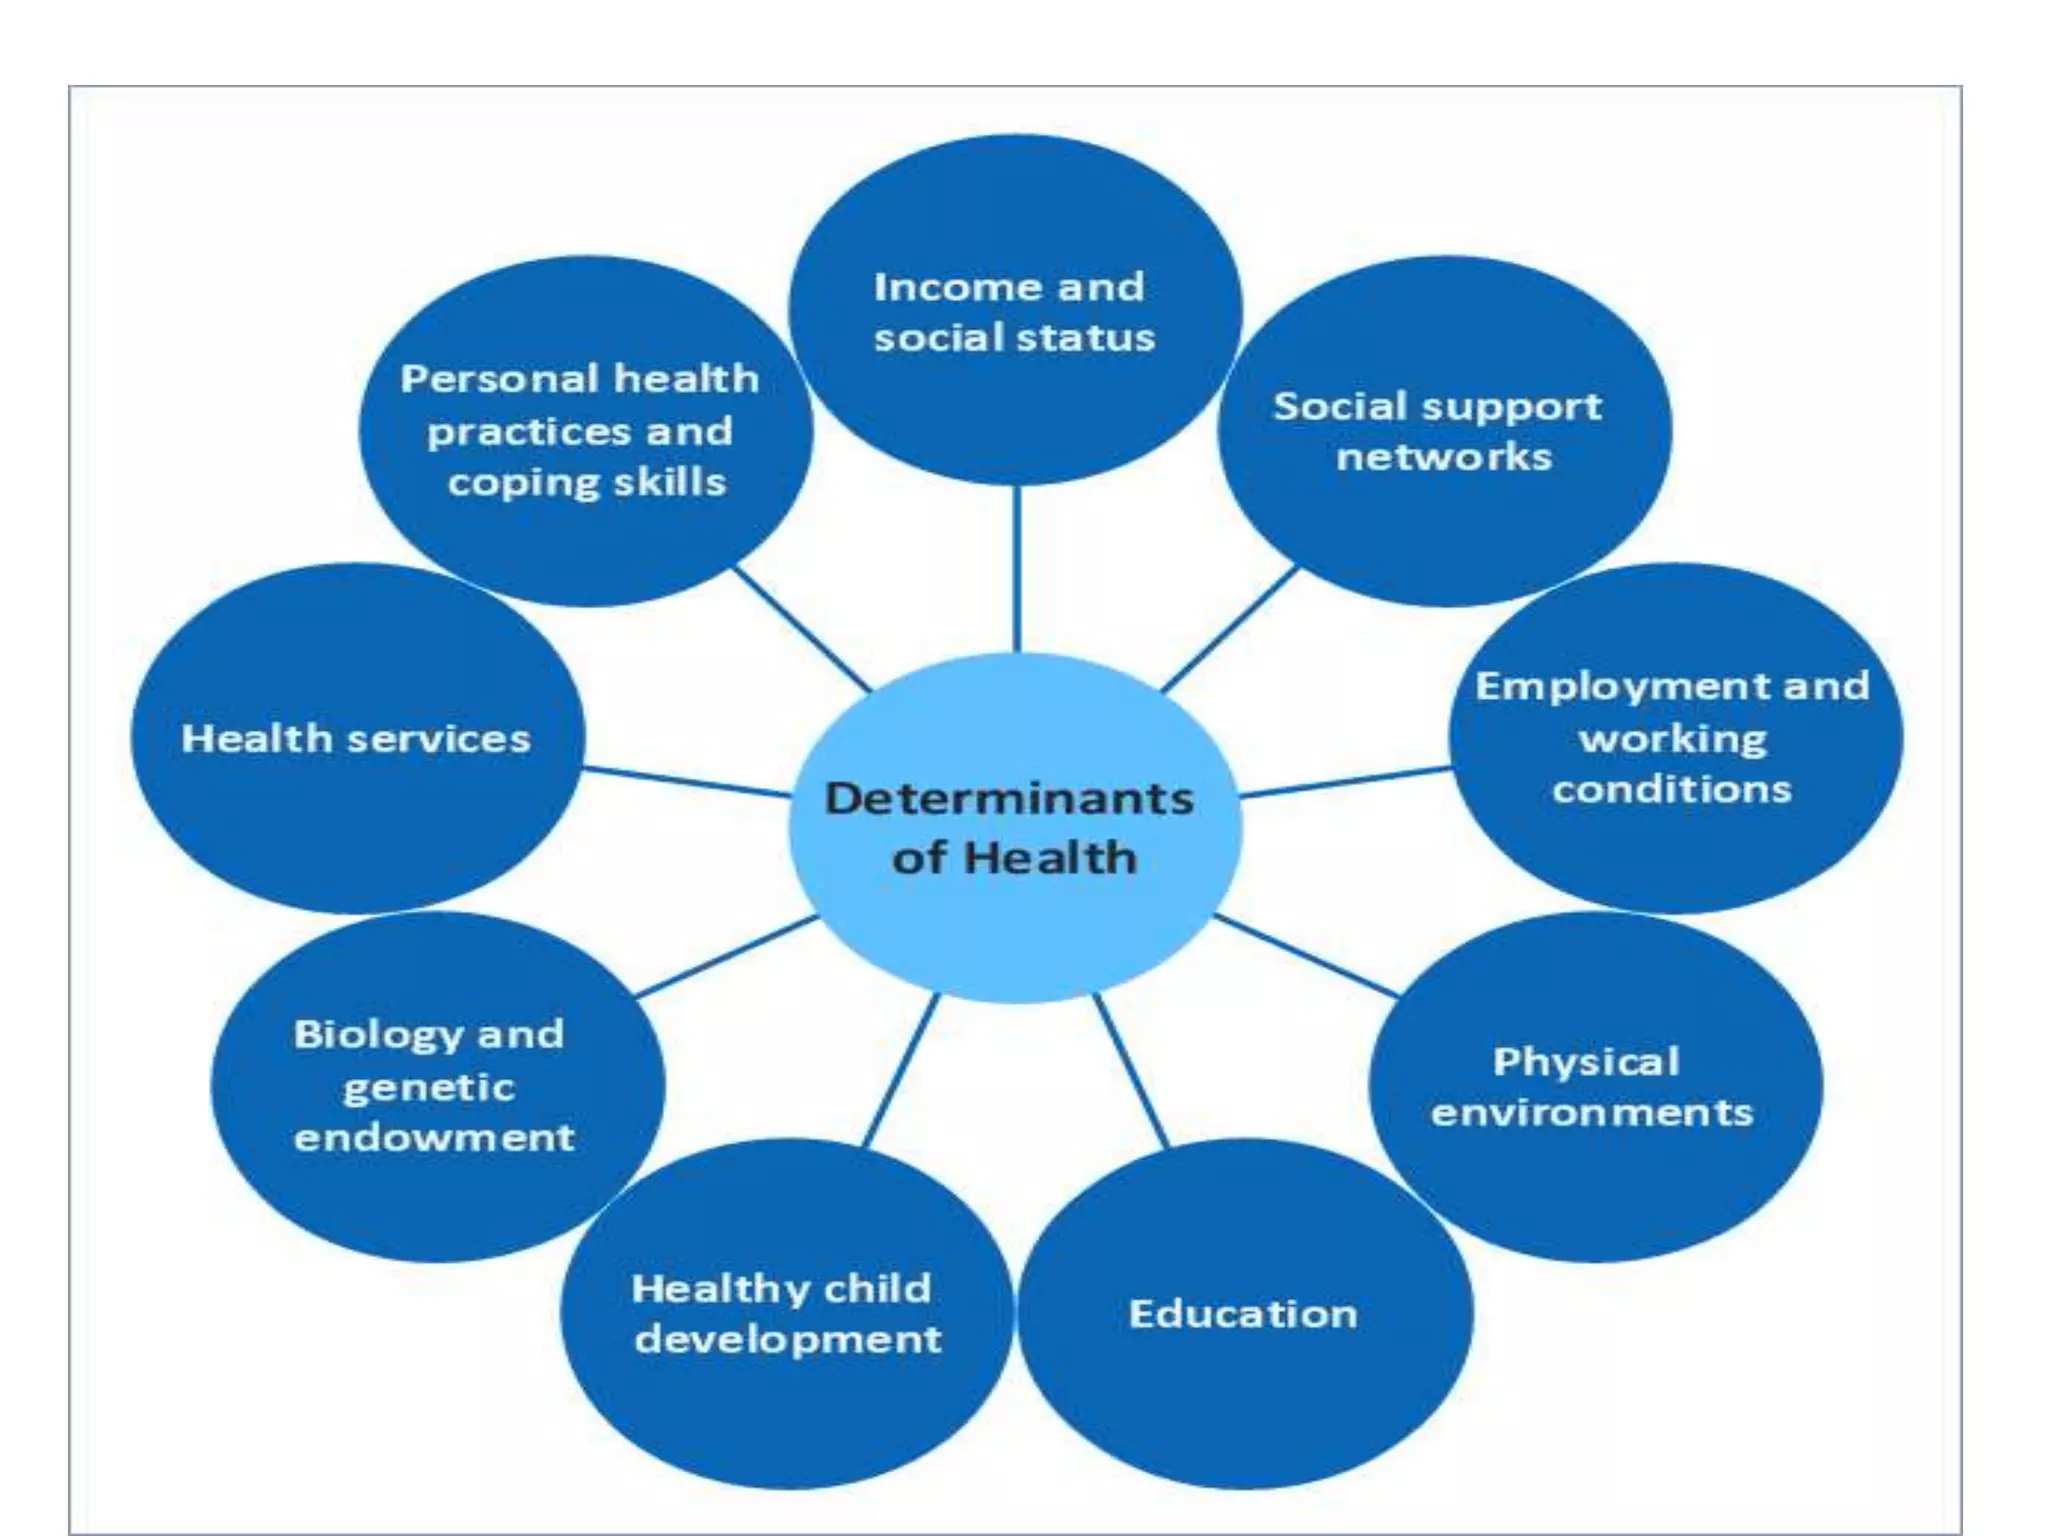
Most people treat this like a checkbox exercise. It isn't. A proper Determinants Of Health Assessment requires you to look at biological, behavioral, social, and environmental factors simultaneously, and then figure out which ones are actually driving outcomes for the population or individual you're studying. The theoretical framework is straightforward. The execution is where everything breaks down. Start by mapping the domains. The WHO framework gives you five buckets: biology, behavior, social context, healthcare access, and environment. Write them down. Then pull whatever data you have — clinical records, community surveys, census data, local health department stats. Cross-reference the data against each bucket. If you're missing data in one area, note it explicitly. Do not fake it or smooth over gaps. That will come back to haunt you later.
Running A Determinants Of Health Assessment: The Step-By-Step Process
Here is the order I use. It takes about 40 minutes for a single community profile if you have clean data, and about 3 to 4 hours if you're pulling from multiple fragmented sources. Step one: Define the scope. Are you assessing an individual patient, a clinic population, or an entire community? The scale changes everything. Patient-level assessments rely on chart data and patient interviews. Community-level assessments require aggregate data and sometimes field surveys. Be specific about your scope before you touch any tools. Step two: Gather baseline data. Pull mortality rates, hospitalization frequency, chronic disease prevalence, vaccination coverage, food insecurity metrics, housing instability statistics, and environmental quality indices. Every health department or hospital system has different databases. Sometimes they don't talk to each other. Expect to spend more time on data retrieval than on analysis.
Step three: Score each determinant. Rate each of the five domains on a scale from low to high risk. Use actual numbers when possible. Percentages of adults with obesity, rates of uninsured residents, average PM2.5 exposure, crime statistics — pick quantifiable metrics. If you can only get qualitative data, label it as such and move on. Step four: Identify intersections. This is where most assessments go wrong. Social determinants don't operate in isolation. A patient with uncontrolled diabetes who also lacks transportation to appointments and lives in a food desert needs a different intervention plan than a patient with uncontrolled diabetes who has insurance and a reliable car. Map the overlaps. Step five: Prioritize interventions. Pick the two or three determinants with the highest impact potential and the best data support. Do not try to fix everything at once. You will accomplish nothing. Document your reasoning so someone else can review your logic.
Get the Full Details
I ran into a specific problem last year that illustrates why this process is messier than the textbook version. I was assessing a rural community with unusually high rates of opioid-related emergency visits. The data clearly pointed to prescription overuse as the primary driver, but when I pushed deeper into the social determinants bucket, I found that the community had zero accessible mental health providers within a forty-mile radius and no substance abuse treatment facility. The biological and behavioral data told one story. The social and environmental data told a completely different one. I was tempted to recommend increased prescribing regulations because the emergency visit data made that seem like the obvious answer. Instead, I recommended a mobile telehealth psychiatry program and funding for a regional addiction treatment center. Both interventions addressed the same problem from different angles. The telehealth option alone would have moved the needle by maybe 15 percent. Combined with the treatment facility, the projected impact jumped to around 40 percent. It is not a dramatic difference in theory, but in practice the difference between a failing assessment and a functional one.
Tools And Resources
The CDC's Population Health Data tools and the WHO's Global Health Observatory both offer downloadable datasets you can use for community-level assessments. The Social Vulnerability Index from the Agency for Toxic Substances and Disease Registry is free and provides county-level scoring that maps directly onto the social determinant domain. For individual patient assessments, the PRAPARE tool from the National Association of Community Health Centers is the standard. It covers twenty-seven questions across housing, food, transportation, income, and education. Takes about eight minutes to administer. There is no single downloadable template that covers all five domains in a way that works universally. I built my own using a modified PRAPARE framework combined with community-level data fields from the county health rankings database. The setup took roughly two weeks of iteration. After that, running a full assessment takes about forty minutes for community profiles and twelve minutes for individual screenings.
What This Method Does Not Handle Well
Let me be blunt about the limitations. A Determinants Of Health Assessment is not a predictive tool. It identifies correlations and risk factors. It does not tell you what will happen to a population over time. Causal inference requires longitudinal studies and statistical modeling, which is a completely different discipline. Do not conflate the two. The biggest bottleneck is data quality. If you are working with a community that has incomplete census data, outdated health department records, or no systematic tracking of environmental exposures, your assessment will be built on assumptions. I have seen assessments that looked professionally presented but were built on five-year-old data that no longer reflected current conditions. The worst part is that the output still looked legitimate. Garbage in, garbage out applies more here than almost anywhere else in public health. Another failure mode is domain overload. When you include every possible determinant, you end up with a report that says nothing useful. Every community has some level of poverty, some environmental concern, some access gap. The trick is filtering for what matters in your specific context. I usually cut any domain where the data quality is below a reasonable threshold or where the variance between subpopulations is negligible. That trims the analysis significantly and forces you to focus on the actual differentiators.
 Final.jpg)
If you need something faster and less comprehensive, a simplified screening tool focused on the behavioral and social domains alone can give you actionable results in under ten minutes per patient. It is not as thorough, but it is more practical for busy clinical settings where full assessments are unrealistic. The core challenge remains the same regardless of which approach you use: the gap between what the data says and what actually exists on the ground. No assessment framework closes that gap completely. The best you can do is document your uncertainty, state your assumptions explicitly, and update your findings whenever new data becomes available. Everything else is just formatting.