Why Most Answer Keys Fail Before Students Even See Them
I spent three years building nursing exam banks before I realized the problem wasn't the questions themselves. It was how little thought went into the rationale behind each answer choice. A poorly constructed answer key doesn't just give wrong information — it actively teaches the wrong mental model for clinical decision-making. The difference between a decent key and a solid one usually comes down to one thing: whether the distractors reflect real clinical confusion or just obvious wrong answers. Here is how I approach it now, after watching students repeatedly second-guess correct answers because the explanation lacked the actual reasoning path they needed to follow.
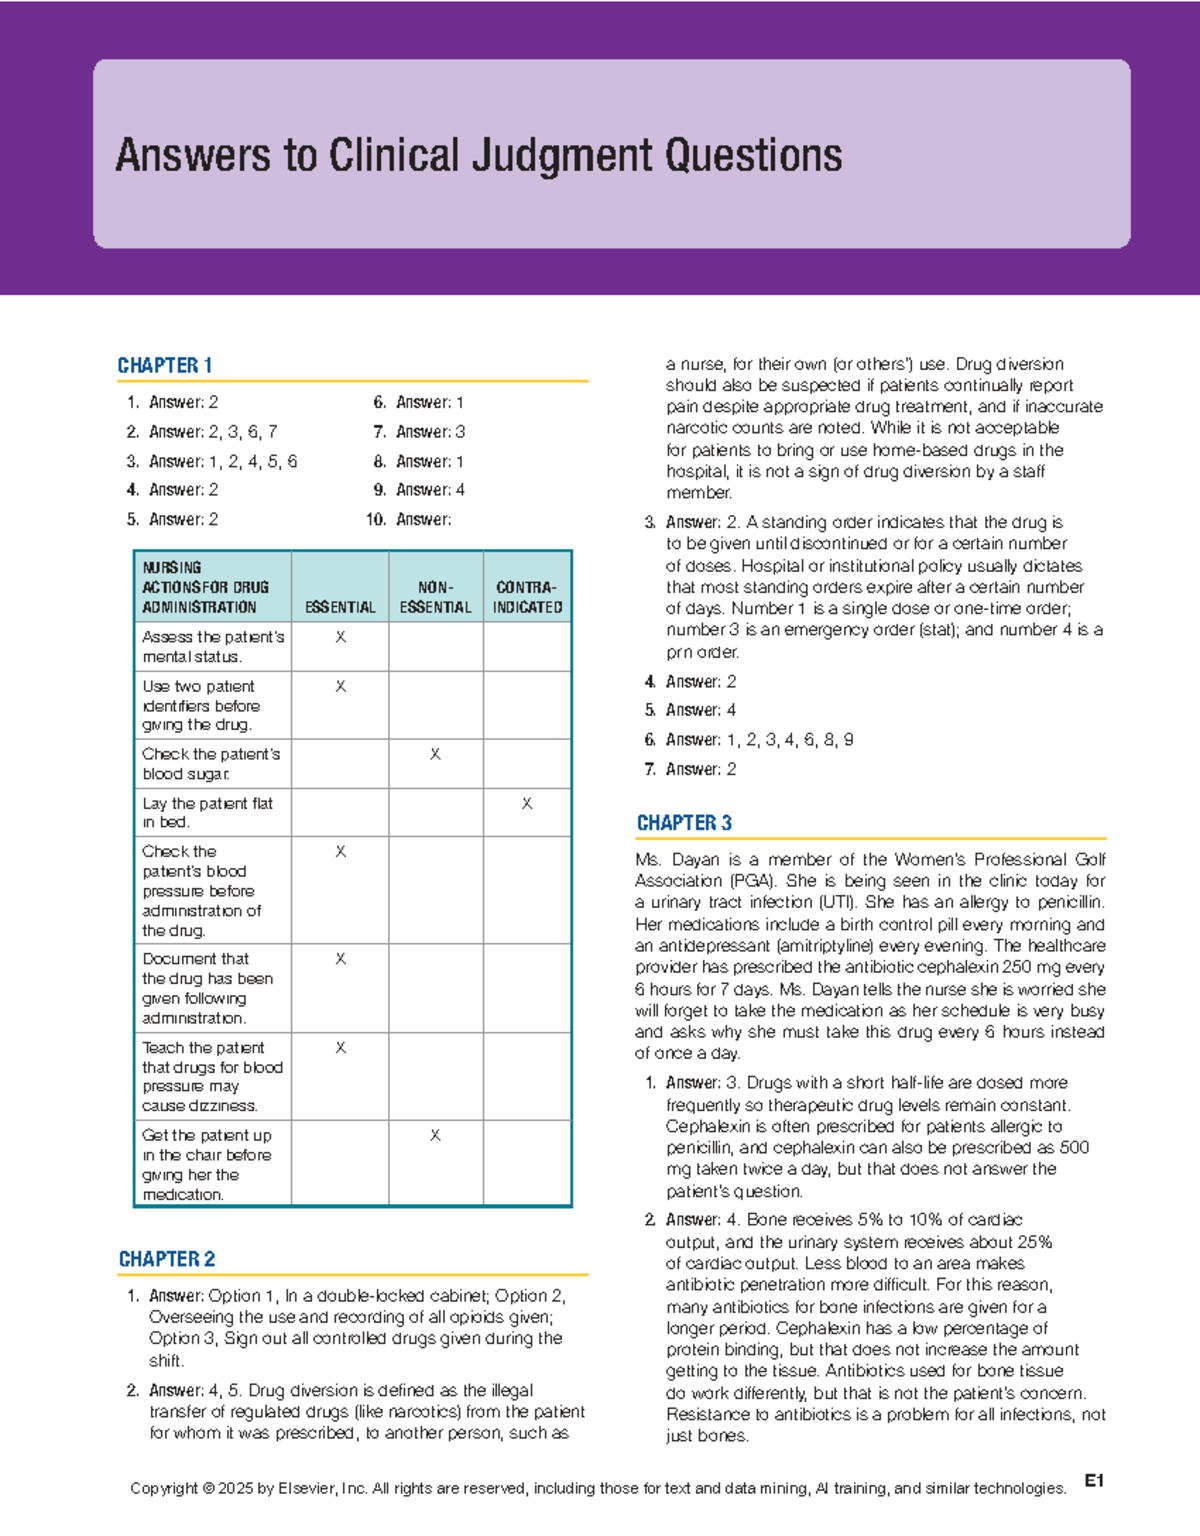
Developing Clinical Judgement Answer Key
The core process starts with the clinical scenario, not the question. Write the patient presentation first — age, chief complaint, vital signs, relevant history, lab values, whatever fits. Then ask yourself what a competent clinician would actually do at that moment. The correct answer is whatever that person does. Everything else is a plausible deviation from that standard. Distractors need to target specific reasoning errors, not random facts. When I build keys for the NGN-style items that are now standard, I map each wrong option to a particular cognitive failure: anchoring bias, premature closure, availability heuristic, or simple knowledge gap. A student who picks the wrong answer should be able to look at the rationale and understand exactly what thought process led them there. That is where the learning happens. I remember building a sepsis triage question where I initially made all three wrong answers clearly dangerous choices — like withholding fluids in hypotension or delaying antibiotics past the six-hour window. Every student eliminated them immediately. The question had zero discrimination. I replaced them with options that reflected actual errors I see on the floor: giving antibiotics but ignoring source control, starting vasopressors before adequate fluid resuscitation, or focusing on lactate clearance while missing the clinical picture entirely. Those are the decisions real nurses and residents wrestle with. The key had to explain why each was insufficient without being condescending about it.
The Rationale Structure That Actually Works
Every correct answer in my keys follows the same three-part structure. First, state the clinical principle being tested. Second, walk through why this patient meets or does not meet the criteria. Third, address the closest competing answer and explain why it falls short. That third part is the one most people skip. It is also the part students read most carefully. For incorrect options, I write a one-sentence explanation of the reasoning error, not just a statement that it is wrong. "This option reflects premature closure on the initial diagnosis without accounting for the new laboratory findings" is useful. "This is incorrect because it does not address the priority" is not. The second version tells the student nothing about what they did wrong conceptually. The length of the rationale matters more than people admit. Too short and it reads like a textbook answer key from 1998. Too long and students stop reading before they finish. My sweet spot is eighty to one hundred twenty words per option for complex clinical judgement items, shorter for knowledge-recall questions. The NGN format especially demands longer rationales because the task is explicitly about reasoning, not recall.
Get the Full Details

Tagging and Blueprint Alignment
A well-built key is not just explanations. It is metadata. I tag every item with the cognitive level (remember, understand, apply, analyse), the clinical judgement phase (recognize cues, analyze cues, prioritize hypotheses, take action, evaluate outcomes), and the content domain. This lets you run analytics later to see if your exam actually tests what you intended to test. I once shipped a full pharmacology section where the blueprint called for forty percent application-level questions and twenty percent analysis-level questions. After the exam, the stats showed seventy percent were at the application level. The distractors had been too distinctive — students who could identify the drug mechanism got every question right without ever having to weigh competing priorities. I had to rebuild roughly a third of the set with higher-order scenarios before I could trust the scores.
Common Mistakes I See Over and Over
The most frequent flaw is making the correct answer unusually detailed while the distractors stay vague. It signals to students which option is right without requiring any clinical reasoning. If the correct answer has four clauses and three distractors have one clause each, the item is measuring test-taking savvy, not clinical judgement. Another pattern is answering based on the ideal textbook scenario rather than the messy reality the question presents. A patient with chest pain and a history of anxiety, hypertension, and GERD — the correct answer might still be ECG and troponin first, but if your rationale only addresses the cardiac workup without acknowledging why the anxiety history is a deliberate red herring, you are not teaching clinical judgement. You are teaching pattern recognition, which is a different skill. A third issue is inconsistent difficulty within a single topic area. I have seen keys where five neurology questions test cranial nerve localization at an advanced level and the sixth asks what the normal range for pupil size is. That swings the entire section's variance and makes the score meaningless for anyone trying to measure clinical reasoning ability specifically.
How I Validate a Key Before It Goes Live
I run a three-stage check. First, peer review with someone who has experience in the relevant area. A psychiatrist reviewing a psychopharmacology key will catch different errors than I would. Second, I do a trial run with at least ten current students or practitioners and collect their reasoning aloud, not just whether they got it right or wrong. The think-aloud data reveals which distractors are ambiguous and which rationales miss the actual confusion point. Third, I calculate point-biserial discrimination indices. Any item below 0.25 typically means the question is either too easy, too hard, or the distractors are not working. I revise or drop it. This validation step usually adds three to four days to the development timeline for a fifty-item bank, but it catches problems that no amount of internal review misses. The think-aloud protocol alone has saved me from shipping at least six items across different test forms that looked fine on paper but broke under actual use.
When This Approach Fails
Clinical judgement answer keys require time and subject-matter depth that most individual instructors simply do not have. Building a twenty-question psychiatric assessment set with proper NGN-format rationales and validated distractors takes a single expert roughly twelve to fourteen hours of focused work. If you are asking five people to each build five questions, you will get inconsistency in tagging, rationale style, and difficulty level that undermines the entire exam. The other hard limitation is that these keys become stale fast in rapidly changing clinical areas. Sepsis guidelines shifted significantly between 2021 and 2023. Anticoagulation protocols change with new drug approvals. A well-built key on current topics will need a formal review cycle, ideally every two years, with changes tracked version by version. Skipping that review cycle is how you end up teaching outdated standards under the guise of clinical reasoning. If you do not have access to practicing clinicians who can review each item in its final form, a simpler recall-based key with shorter rationales is honestly more defensible than an overreaching clinical judgement set that cannot be properly validated. A mediocre but honest key is better than a sophisticated one that contains undetected errors.



