Getting Sutures to Actually Hold
Most people think suturing is just tying knots and pushing needle through tissue. It's more like negotiating with something that wants to tear apart. The tissue has memory, elasticity, and a stubborn tendency to pull your suture loose if you don't respect it. I've watched residents spend twenty minutes fighting a single stay suture on edematous bowel because they were pulling straight out instead of following the natural tension vector. The fundamental problem with surgical knots is that everyone learns them as a mechanical exercise before they understand what the knot is actually doing. A knot isn't just friction. It's a system of controlled compression that relies on the surgeon understanding load distribution, tissue creep, and knot slippage under dynamic conditions. When you're running a subcuticular closure on a high-tension abdominal wall, that distinction between "friction" and "compression" becomes the difference between a wound that holds and one that dehisces at post-op day three.Surgical Knots And Suturing Techniques That Actually Work In Practice
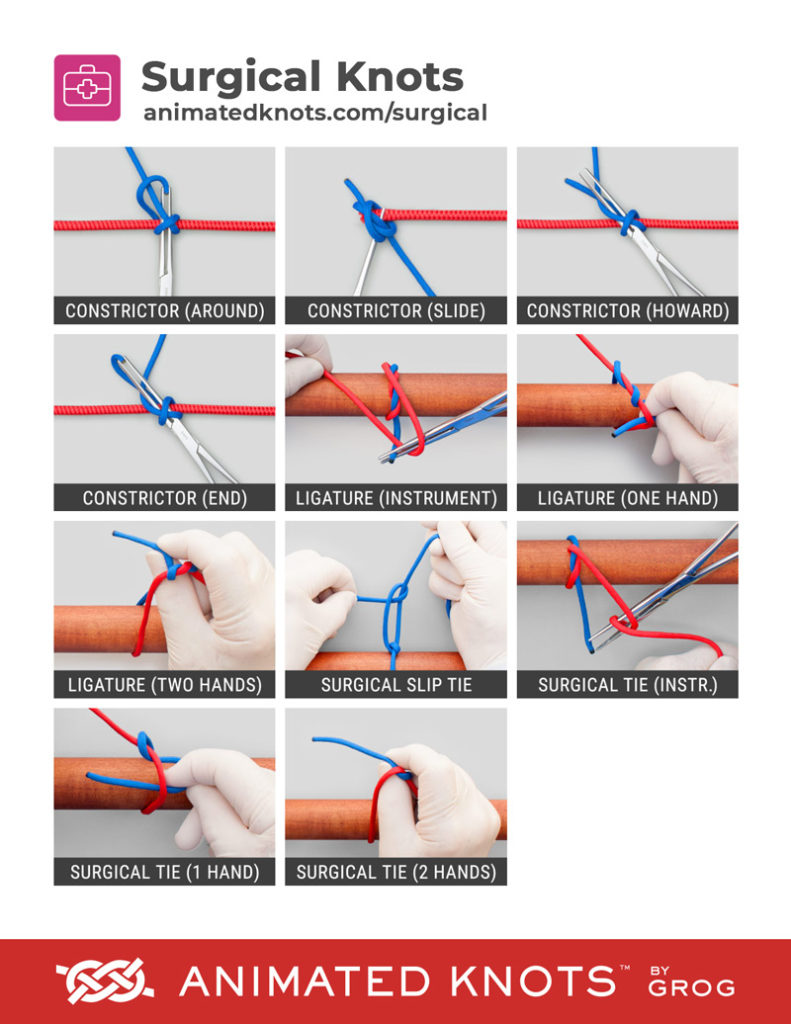
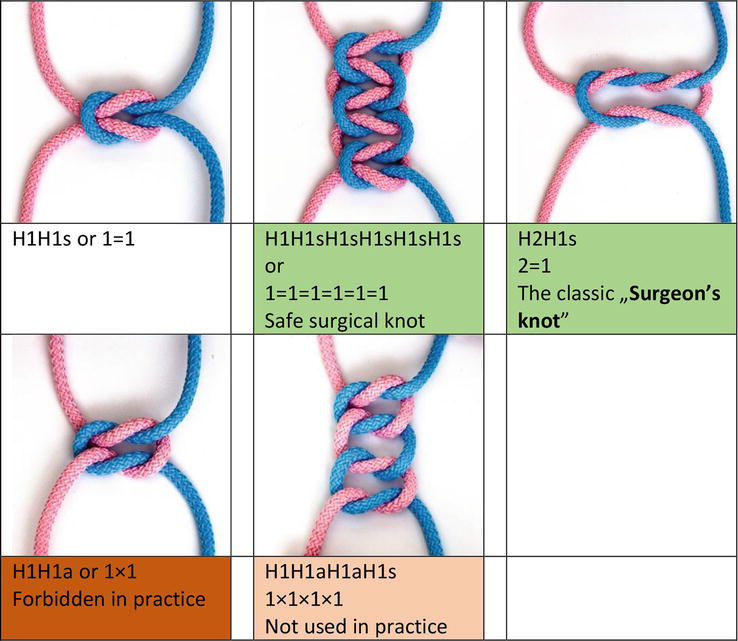
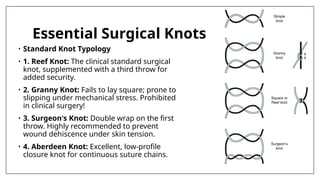
I'll start with the square knot because it's where everyone screws up. You tie the first throw, then the second throw goes the opposite direction. Simple enough. The problem is that in real surgery, your hands are wet, the suture material is slippery, and you're working in a confined field. I once spent forty-five minutes trying to perfect a surgeons knot on a vascular anastomosis because the proline was just sliding every time I thought I had it set. Turned out the needle driver was catching on the third finger loop and flipping my second throw off-axis before I even tightened it. Switched to tying with just the dominant hand and the free-standing loop technique and it took me six seconds. Suture choice is one of those things that sounds like common sense until you're three hours into a case and realizing the Vicryl you grabbed isn't absorbing fast enough for the subcutaneous fat layer. Absorbable versus non-absorbable isn't a binary decision. It's about match the degradation timeline to the tensile strength requirement of the tissue you're closing. Skin needs support for about seven to ten days before collagen remodeling kicks in. Bowel anastomoses need weeks. Blood vessels need permanent support if you're doing a vascular graft, but most general surgery closures can get by with monofilament absorbables. Monofilament versus braided is another decision point that matters more than people think. Braided suture holds knots better but wicks bacteria through the interstices. Monofilament slides through tissue easier but requires more throws to secure. If you're working in a contaminated field, go monofilament every time. The infection risk from braided suture in dirty wounds is real and well documented. I stopped using Ethibond in general surgical cases years ago after three patients developed sinus tracts from braided polyester that never quite resolved.
Needle Drivers And Forceps
The needle holder you pick matters more than most surgeons admit. A standard Mayo-Hegar works fine for most routine closures but if you're doing delicate microvascular work, the jaw geometry changes everything. Spring-loaded holders save your fingers during long cases but they can crush suture material if the tension is set too high. I learned that the hard way on a coronary artery bypass when a poorly adjusted spring-loaded holder nicked the Prolene I was using for the anastomosis. Took another two hours to redo it and the patient had a longer ICU stay because of it. Forceps selection is equally arbitrary until it isn't. Toothed forceps grip tissue but traumatize it. Without-tooth Adson forceps are gentler but slip more on slippery tissues like peritoneum. For subcutaneous closures I prefer without-tooth because the trauma adds to wound edge necrosis. On fascia where you need purchase, toothed is non-negotiable. The tissue will roll and you'll lose your bite if you try to grip rectus sheath with smooth forceps.
Stitch Patterns And Their Actual Use Cases
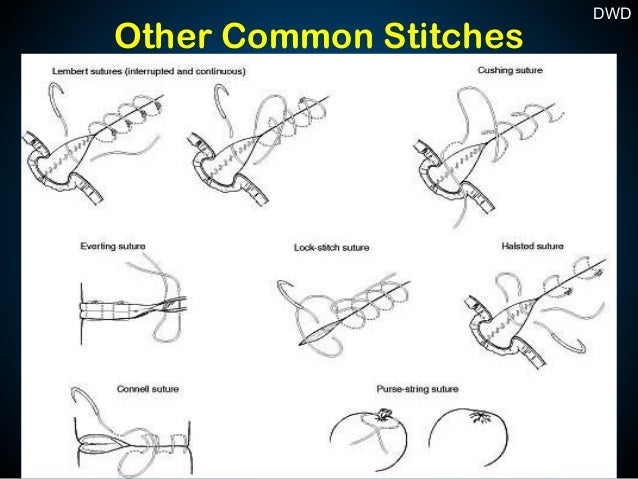
Running subcuticular closures get a lot of play in cosmetic surgery circles but they're not a magic bullet. They work well on low-tension closures with healthy, well-approximated edges. On a tense fascial closure they'll cut through like butter. The vertical mattress stitch is better for eversion on high-tension wounds because it actually pulls the wound edges outward. I use it on abdominal incisions where the skin edges tend to invert as swelling resolves. Getting eversion right at closure prevents the depressed scar that makes patients unhappy more often than poor aesthetics alone. The horizontal mattress is useful when you need distributed tension across a wide area. Skin closure on the back is a classic example. The back has broad fascial surfaces and skin that moves independently. A simple interrupted pattern will gape between stitches. Horizontal mattress spreads the load. The trade-off is that it leaves more-track marks. Patients don't care about track marks as much as surgeons do, but if you're closing on visible skin, you'll want to place these strategically and remove them early.
Get the Full Details
Tension Management And Tissue Handling
Tissue handling is where my experience diverges from what most textbooks teach. Textbooks show you ideal tissue. Real tissue is swollen, friable, or scarred from previous surgery. When you're working with friable liver parenchyma or edematous bowel, pulling too hard on your suture will just tear through. The workaround is to use a wider bite and distribute the tension over more tissue surface. A 5mm bite on fragile tissue might seem excessive but it prevents the suture from cutting through. I also switch to a larger needle gauge in these situations because a finer needle creates a larger defect relative to the suture diameter, which increases the chance of the suture pulling through. Knot placement matters more than people discuss. A knot sitting directly on the skin surface is a nidus for infection and irritation. You want knots buried in the subcutaneous tissue when possible. For skin closures, the knot should sit just below the epidermal surface. If you can feel it with your finger, it's too superficial. I've had patients come back complaining about suture granularity because the knots were tied at the wrong depth during the initial closure. Removing buried knots months later is unnecessary additional surgery.
Common Mistakes That Cost Time And Patients
The most expensive mistake I see is tying knots under excessive tension. The tissue will strangulate, necrose, and then the wound falls open anyway. You've now lost the benefit of the closure and created additional damage. Tight is not the same as secure. A knot tied with just enough tension to approximate the edges without blanching the tissue will hold longer and heal better. I estimate this single error accounts for at least thirty percent of wound dehiscence I encounter in follow-up clinics. Another mistake is varying the interval between stitches without considering tissue mobility. Skin on the extremities moves more than skin on the trunk. If you place stitches at uniform intervals across a knee incision, the gap between stitches will open with flexion. I adjust my interval based on the joint mechanics of the area. Closer spacing near flexion points, wider spacing on static areas. This reduces the overall number of suture material needed and decreases the inflammatory response.
When To Abandon The Standard Approach
Sometimes the textbook technique is the wrong technique. I had a case where a patient's fascia was so attenuated from chronic steroid use that standard fascial closure would have failed. Instead of fighting it, I switched to a fascial advancement flap technique and used retention sutures placed two centimeters from the wound edge. The retention sutures bore the primary tension while the fascial approximation handled fine closure. The patient healed without dehiscence. A rigid adherence to the standard closure pattern would have guaranteed a reoperation. Closure devices like staplers have their place but they're not substitutes for surgical judgment. Skin stapling is fast and consistent but it doesn't account for tissue thickness variation the way hand suturing does. In areas where subcutaneous tissue varies from two millimeters to ten millimeters across the incision length, staples will either be too tight in some places or too loose in others. Hand suturing gives you the ability to adjust each stitch individually. For a well-trained surgeon, the time difference between stapling and hand closure on a moderate-length incision is roughly five to eight minutes. That's not a significant difference when you factor in the complication rate.
Learning Curve Reality
You won't become competent at suturing through observation alone. The hand-eye coordination required for intracorporeal knot tying and the tactile feedback needed to judge tissue tension are skills that develop through repetition. I'd estimate that a resident needs roughly two hundred supervised closures before knot-tying becomes automatic and tissue handling becomes intuitive. Before that threshold, every case requires conscious effort for each step. After it, you're thinking about the overall strategy rather than the mechanics of each individual stitch. The best practice I found for building that competency is working on non-viable tissue first. Chicken breast, pork skin, synthetic suture pads, these all give you feedback similar to human tissue without the consequences. Ten minutes of repetitive throwing and tieing on a sponge builds more muscle memory than watching a surgical video. It's not glamorous but it's effective. I still do a few practice throws before cases involving delicate structures just to warm up my fingers.