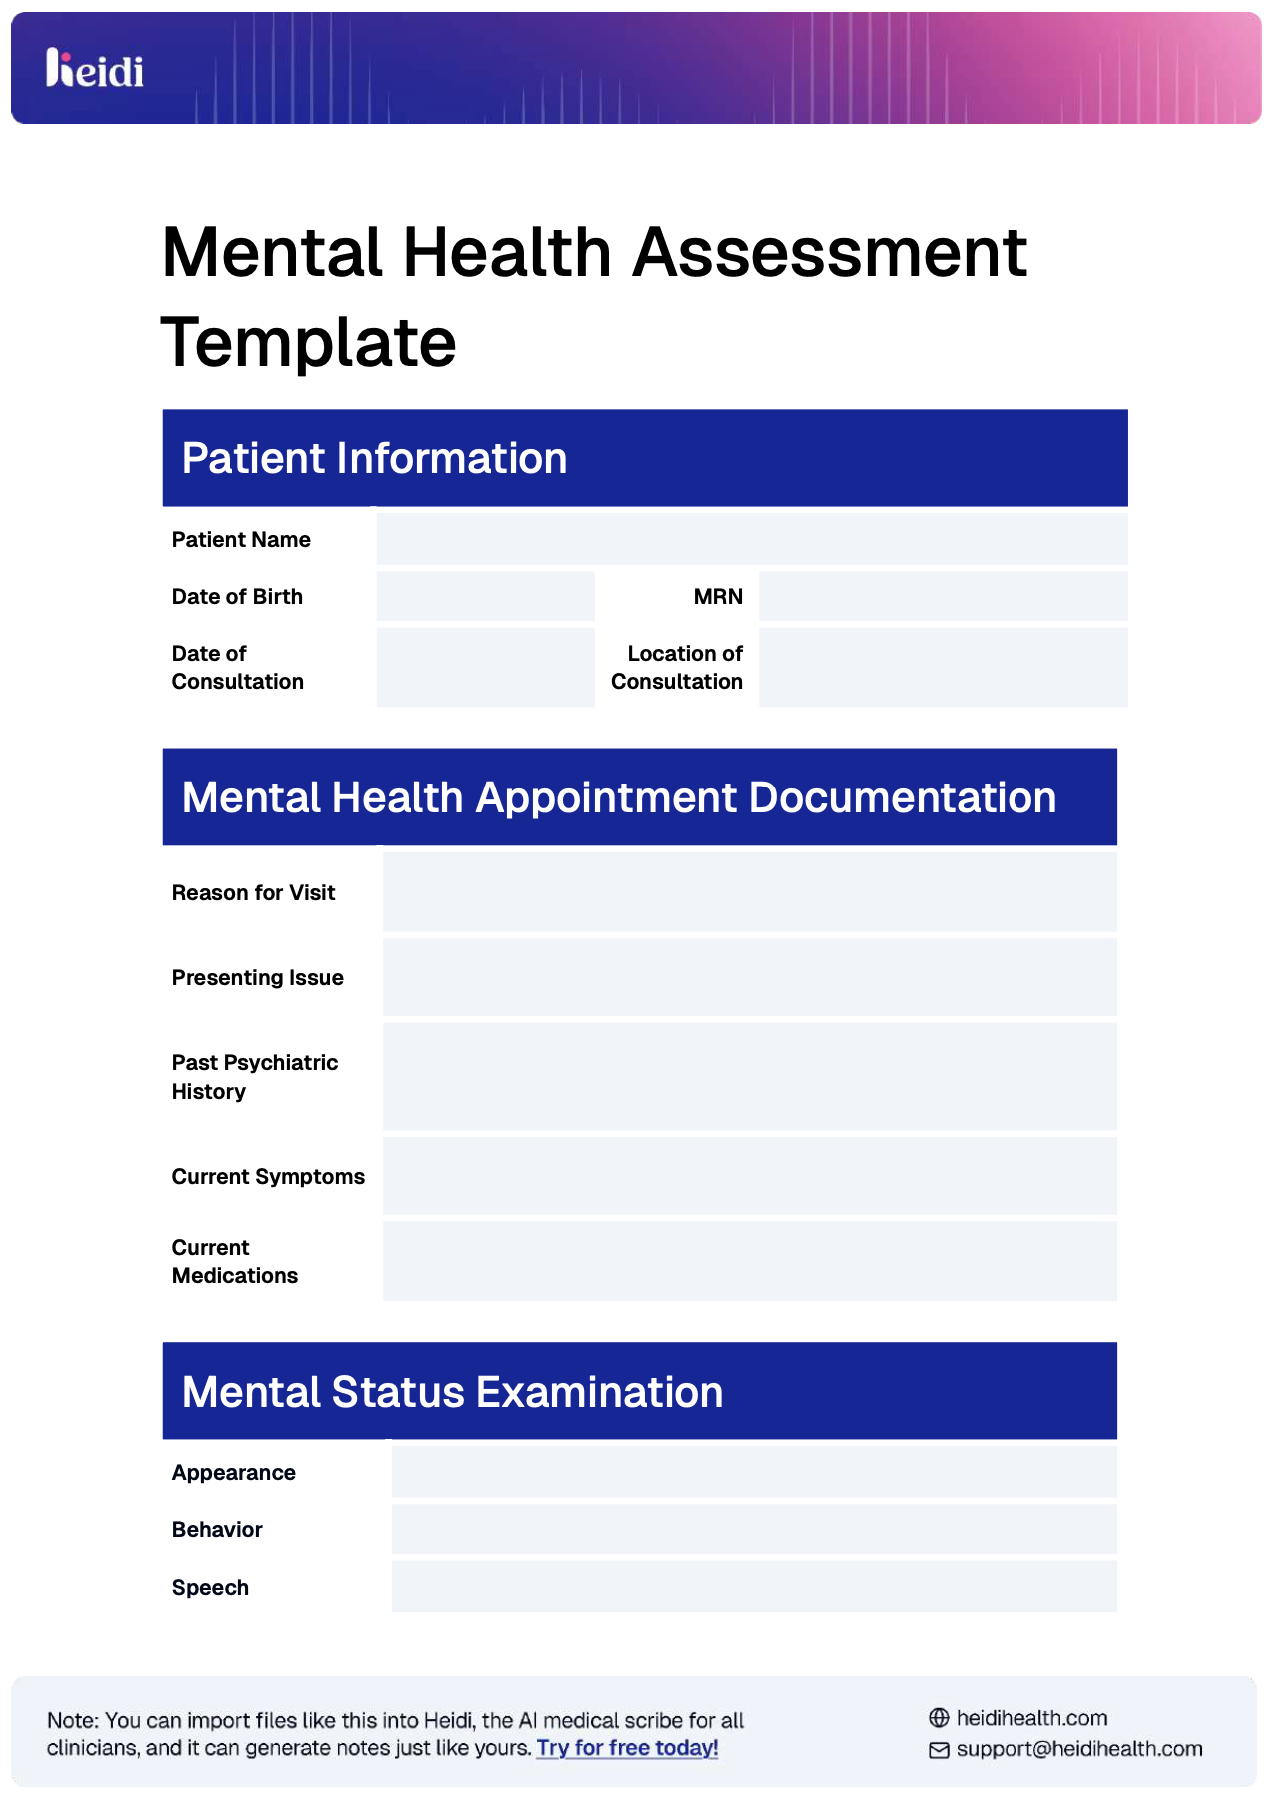
What Actually Happens During a Diagnostic Assessment
A diagnostic assessment in mental health is essentially a structured information-gathering process. It is not a single test you pass or fail. It is a collection of clinical interviews, standardized questionnaires, behavioral observations, and sometimes collateral information from other providers or family members. The goal is to determine whether a person meets criteria for a specific diagnosis, or whether symptoms are better explained by something else entirely. I have sat on both sides of this process over the years. The way it actually unfolds in practice is nowhere near as clean as textbook descriptions suggest. Most assessments I have reviewed or conducted take between 60 and 90 minutes for a standard intake. Comprehensive evaluations with psychometric testing can stretch into multiple sessions over several weeks.
Diagnostic Assessment Mental Health: How to Navigate One
If you are looking to get assessed, the first practical step is figuring out who actually performs these assessments and what credentials they hold. Psychiatrists can diagnose and prescribe medication. Psychologists with doctoral-level training can conduct thorough diagnostic evaluations and psychological testing. Licensed clinical social workers, licensed professional counselors, and nurse practitioners can also diagnose within their scope depending on your jurisdiction. The depth and rigor you get depends heavily on which professional you see. Before the appointment, gather any relevant history. Previous diagnoses, medications you have tried, hospitalizations, family mental health history, substance use patterns, and major life events all matter. Written notes help because the assessor will likely ask the same core questions in different ways throughout the session. Writing things down beforehand ensures you do not forget details under the pressure of being evaluated. During the assessment itself, expect direct questions. Some will seem mundane. Others will feel intrusive. Questions about sleep, appetite, suicidal ideation, substance use, trauma history, and social functioning are standard. The assessor is building a clinical picture. Being honest, even when the answer feels embarrassing, is the single most important thing you can do for the accuracy of the result.
I once worked with a client who presented with what looked like classic treatment-resistant depression on paper. She had failed two antidepressant trials and scored firmly in the moderate-to-severe range on every PHQ-9 ever administered. The diagnostic interview revealed she had been working three night-shift jobs for the past eight months while caring for a disabled parent. She was chronically sleep-deprived. Her depressive symptoms were real and severe, but the root driver was circadian disruption and chronic stress, not a primary mood disorder. We adjusted the diagnosis, addressed sleep hygiene and accommodation needs, and her scores improved dramatically within six weeks without any medication changes. A rushed assessment that only looked at the questionnaire scores would have missed that entirely.
Get the Full Details
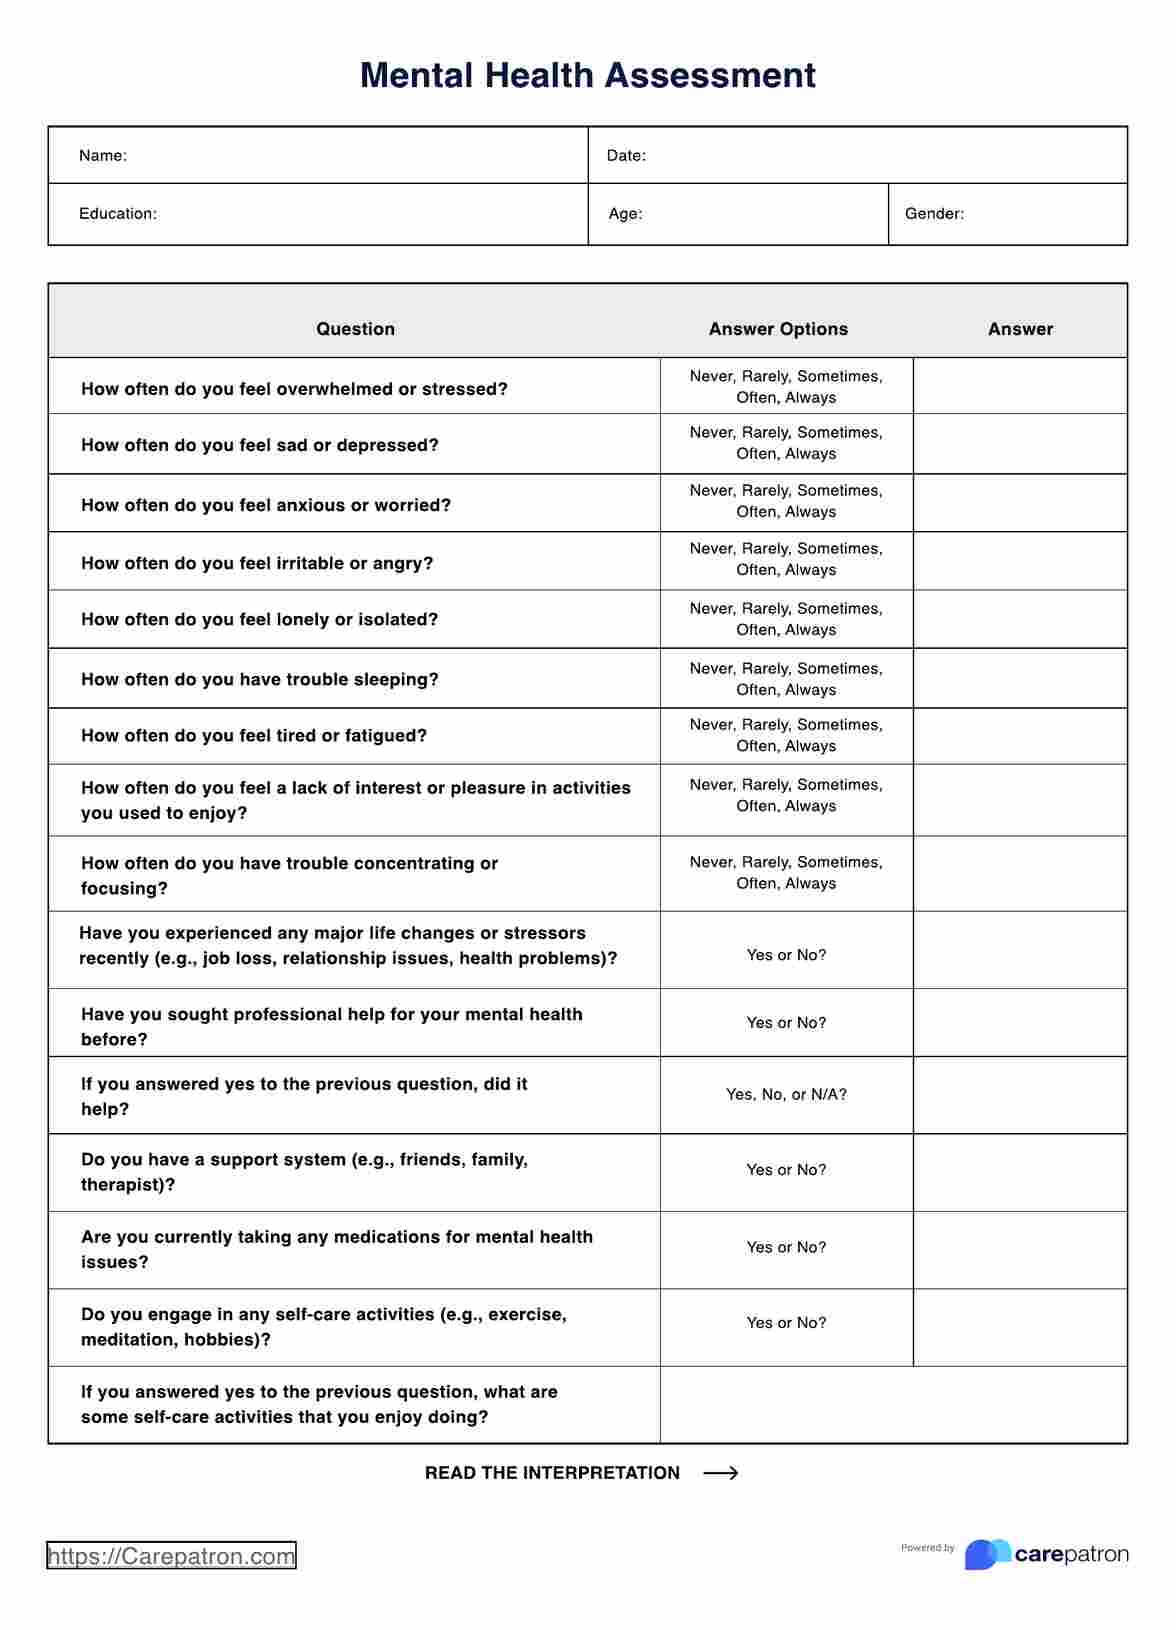
What the Tools Actually Are
Standardized instruments commonly used include the MINI International Neuropsychiatric Interview, the SCID-5, the PHQ-9 for depression screening, the GAD-7 for anxiety, the CRAFFT for adolescent substance use, and various PTSD checklists like the PCL-5. These are screening and diagnostic aids, not standalone diagnostic tools. A high score on the PHQ-9 does not equal a depression diagnosis. It equals a recommendation for further clinical evaluation, which is exactly how they are supposed to be used. Psychological testing adds another layer. Instruments like the MMPI-3, the PAI, or the BDI-II provide personality and psychopathology profiles that can differentiate between conditions with overlapping symptoms. For example, borderline personality disorder and bipolar disorder share affective instability as a feature. The MMPI-3 can help distinguish between the two by looking at response patterns across hundreds of items, not just the obvious ones. This is where the assessment moves from a quick interview to a more comprehensive evaluation.
Common Pitfalls That Derail Accurate Diagnosis
Diagnostic overshadowing is a persistent problem. When a person has a known physical health condition, their psychiatric symptoms are too often attributed to the medical issue rather than investigated on their own merits. A patient with hypothyroidism presenting with fatigue and low mood might get a thyroid dose adjustment and nothing else, when in fact they also meet full criteria for major depressive disorder. The reverse happens too. Someone with an established psychiatric diagnosis like schizophrenia might present with new neurological symptoms that get dismissed as "just part of their illness" when they should be getting a neurology workup. Comorbidity is the rule rather than the exception. Roughly 60 percent of people who meet criteria for one mental disorder meet criteria for at least one additional disorder. Assessor bias toward diagnosing the most salient or dramatic condition while ignoring subtler co-occurring issues is a real risk. ADHD and autism spectrum disorder in adults, particularly in women and gender-diverse people, are consistently underdiagnosed because clinicians are looking for the more obvious anxiety or depression presentation first. Another issue I see repeatedly is cultural translation failure in assessment tools. Most widely used instruments were normed on Western, educated, industrialized populations. A symptom like "feeling guilty about things" might mean something very different in a collectivist cultural context where personal responsibility is distributed across the family unit. The score looks pathological on paper. The clinical reality is more nuanced. Any competent assessor should be considering cultural formulation at minimum, and ideally using culturally adapted instruments when available.
Limitations You Should Know About
Diagnostic assessments have real constraints. They are snapshot evaluations. A person's presentation on any given day is influenced by sleep, recent substance use, current stressors, and how well they can rapport with the assessor. Two different clinicians evaluating the same person can arrive at different diagnoses, especially in borderline cases. This is not theoretical. Inter-rater reliability for personality disorder diagnoses is notably lower than for Axis I conditions like major depression or panic disorder. The DSM-5 and ICD-11 frameworks are descriptive, not etiological. They tell you what symptoms cluster together and what to call them. They do not tell you why the person has those symptoms or what the underlying mechanism is. That matters because treatment planning benefits from understanding function, not just label. A diagnosis of PTSD is useful for insurance and treatment guidelines, but two people with PTSD might need very different approaches depending on whether their trauma was a single event, repeated interpersonal violence, or complex developmental trauma. There is also the problem of diagnostic drift over time. A person assessed as having bipolar II disorder at age 25 might present differently at age 40. Substance use history changes the picture. Medical conditions develop. The original diagnosis was not necessarily wrong, but it is not a permanent stamp either. Good clinical practice involves periodic re-evaluation, though insurance and healthcare systems rarely incentivize that.
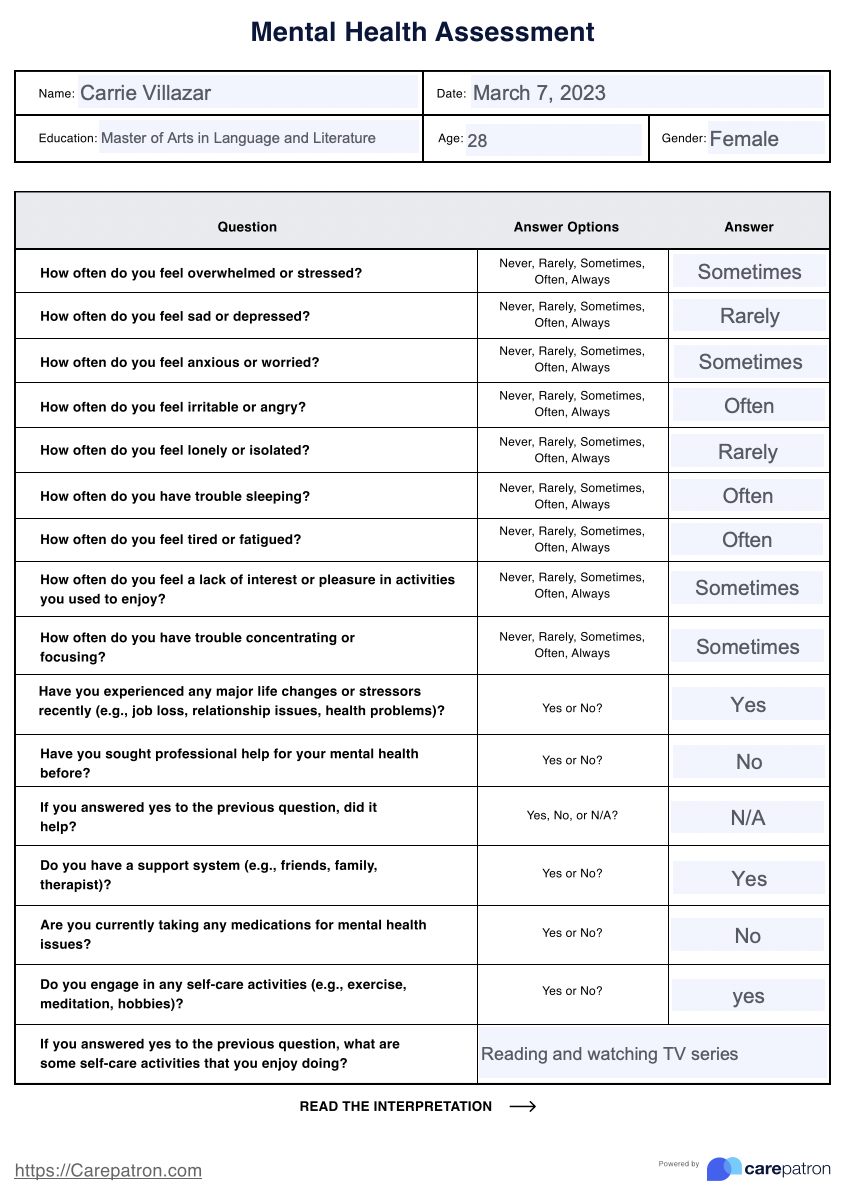
What a Thorough Assessment Should Include
A properly conducted Diagnostic Assessment Mental Health evaluation should cover: current presenting symptoms and their timeline, developmental and psychiatric history, medical history and current medications, substance use history, family psychiatric history, psychosocial functioning across work, relationships, and daily living, risk assessment for suicide and violence, mental status examination findings, and standardized measurement where appropriate. Documentation should include the specific criteria met for each diagnosis, differential diagnoses considered and why they were ruled in or out, formulation explaining how the diagnosis makes clinical sense given the person's history and context, and a treatment plan that follows logically from the assessment findings. If an assessor hands you a diagnosis after a 20-minute conversation with no questionnaire and no review of history, you are not entitled to the result professionally, and you should seek a second opinion. That is not meant to be dramatic. It is just how the process works when done correctly.