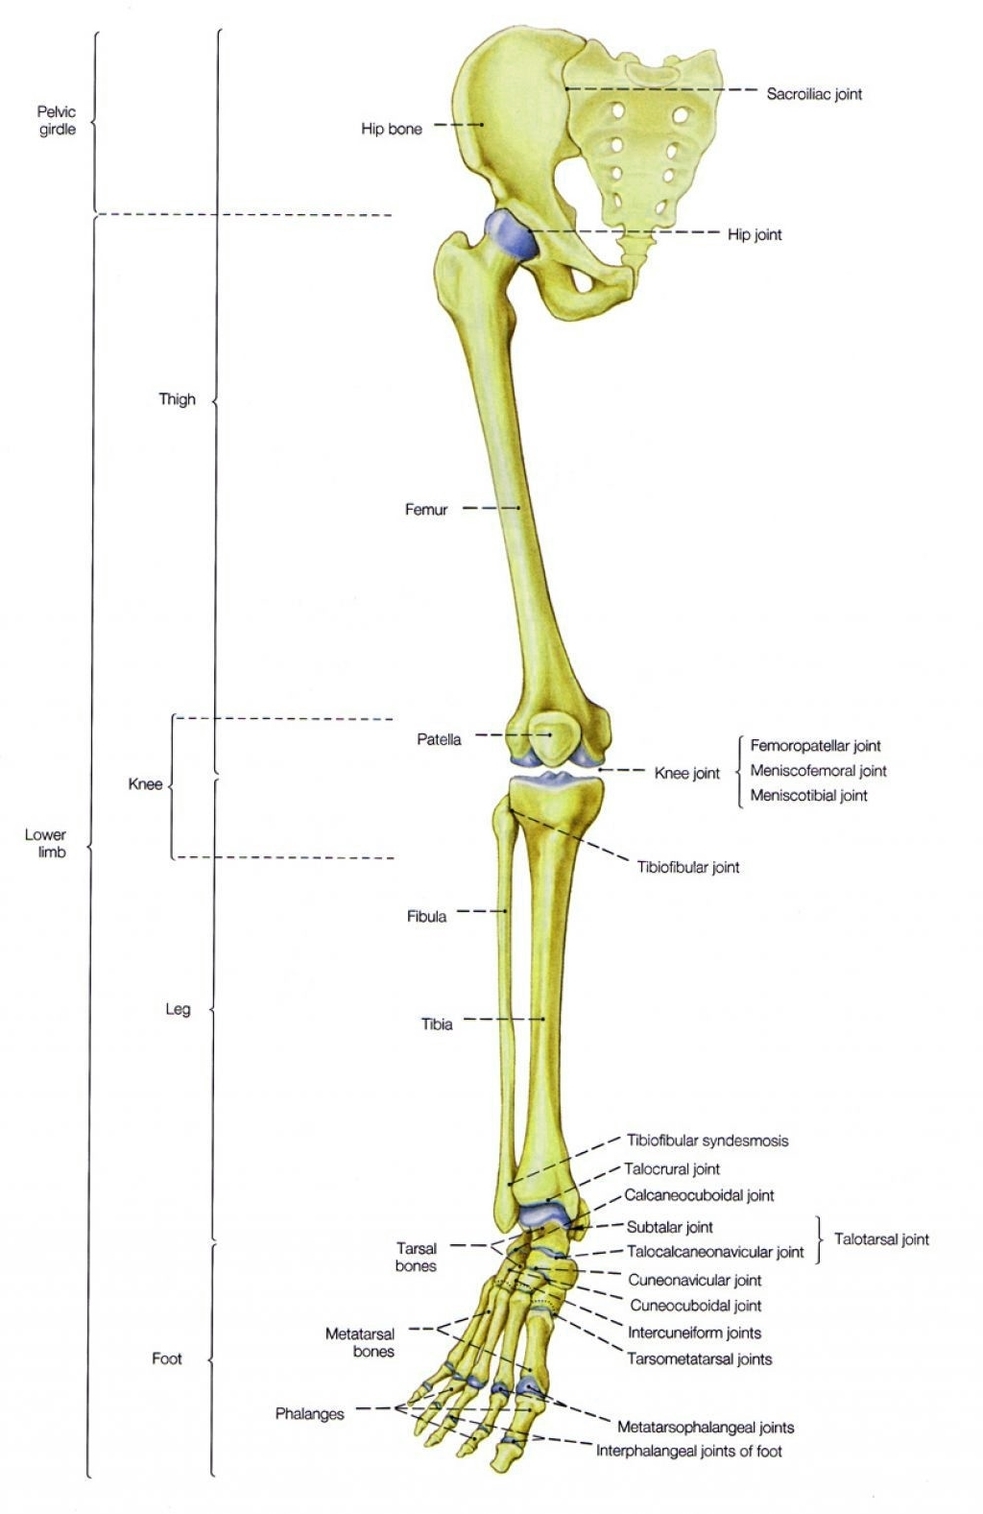
The leg has six main bones, and a Diagram Of Bones In Leg is mostly useful when you actually need to reference them without opening a textbook.
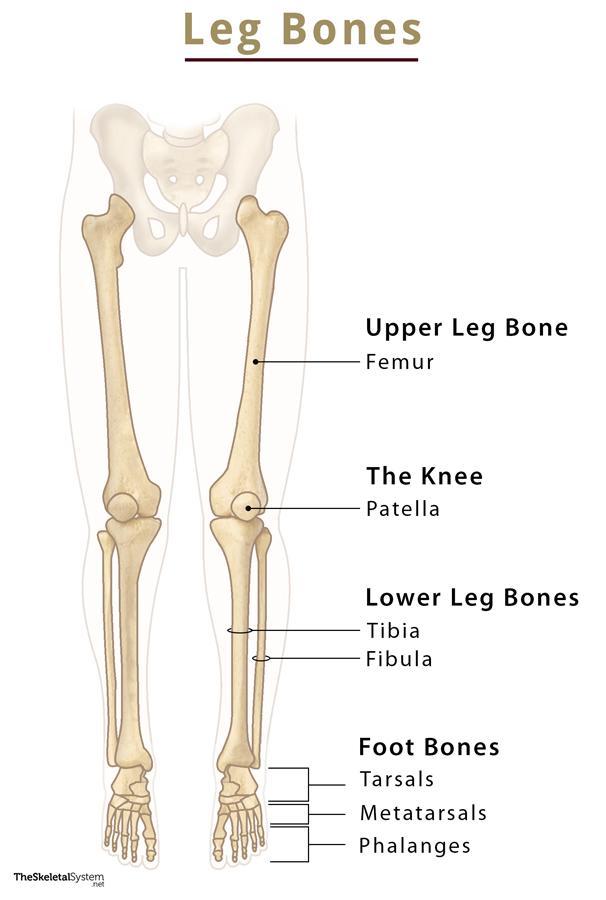
The femur is the thigh bone, the longest in the body, ending at the knee where it meets the tibia and fibula. The patella sits in front of the joint as a sesamoid bone embedded in the quadriceps tendon. Below the knee, the tibia carries most of the weight while the fibula runs alongside it as a thinner structure that anchors ligaments and muscles but doesn't really participate in load-bearing. The tarsals form the rear foot, the metatarsals run through the midfoot, and the phalanges make up the toes. That's the basic layout. Most diagrams I've seen since med school basically show this same arrangement with different coloring schemes. I spent years looking at these in radiology rotations and then actually working trauma cases, and the first thing I learned is that printed diagrams don't tell you much about real fractures. A diagram shows clean borders and perfect joints. Real X-rays show overlapping structures, patient rotation, and artifacts from surgical hardware. When I was doing orthopedic rotations, we had a resident who could identify every bone on a pristine diagram but got completely lost when looking at an actual AP/lateral knee film from a dirty ER. The trick is learning to read the shadows and intersections, not just memorize labels. If you're studying for exams, start with the proximal femur because that's where people mess up. The femoral neck, the greater and lesser trochanters, the intertrochanteric line versus crest — these landmarks matter when you're trying to classify a hip fracture. A Diagram Of Bones In Leg will label them, sure, but it won't tell you that an intertrochanteric fracture has a better prognosis than a femoral neck fracture because of the blood supply disruption risk. That's the kind of thing you pick up from actual cases.
The tibial plateau is another area where diagrams fail you. They show two flat surfaces. In reality, the lateral plateau is more commonly depressed in high-energy trauma, and the posterior slope angle matters for knee stability. I once had a patient with a bicondylar plateau fracture that looked straightforward on the initial film but actually had a posterior fragment we missed until the CT scan. The diagram didn't prepare us for that. The diagram never prepares you for that.
Where to find reliable diagrams and what to do with them
Most medical illustration sites offer decent quality images, but the anatomy diagrams from sources like the NIH or university anatomy departments tend to be the most accurate. I usually grab mine from the Netter collection or the Gray's Anatomy plates if I need something really detailed. For quick reference, the Radiopaedia images are useful because they pair the diagram with actual pathology cases. The problem with most free diagrams online is that they're oversimplified. You'll see the fibula shown as a straight rod, but in reality it has a characteristic spiral shape with a pronounced head and a distal lateral malleolus that extends further distally than the tibia. When I was teaching students, I'd have them compare a textbook diagram to an actual lateral X-ray and point out where the diagram was wrong. It was always eye-opening for them. I downloaded a fairly detailed diagram set from a medical supplier last year for about twenty dollars. It included annotated versions showing muscle attachments, ligament insertions, and neurovascular relationships. That level of detail is what separates a decent study tool from something you'd use as a poster in a waiting room. If you're just curious, the open-source OpenMaP project has some solid leg bone diagrams you can download for free.
Get the Full Details
Pitfalls that everyone misses
The fibula is easy to forget about until you're dealing with an ankle fracture. It's not just a stabilizer, and it articulates with both the tibia and the talus. A high fibular fracture like a Maisonneuve fracture can accompany an ankle injury and is easily missed if you're only looking at the ankle without imaging the full fibula. I saw that happen twice in my first year of practice. The attending pointed it out on follow-up films, and I felt terrible I hadn't thought to look higher up. Another thing: the sesamoid bones under the first metatarsal head. They're not always present, they vary in number, and they're easy to mistake for extra fragments on a foot X-ray. If you're reading a Diagram Of Bones In Leg and see the metatarsals, remember that those tiny sesamoids are sometimes there and sometimes aren't. They're clinically relevant in turf toe injuries and bunion surgery planning. The distal tibiofibular syndesmosis is another area where diagrams lie by omission. They show the bones sitting next to each other, but they don't convey how much motion is actually happening between them during ankle dorsiflexion. That's relevant for syndesmotic injuries, which are increasingly common in athletic populations and often get misdiagnosed as simple lateral ankle sprains.
What works in practice
I keep a laminated diagram from Medscape on my desk because it's at the right level of detail for quick reference during rounds. Not the fancy colored ones with muscle overlays, just clean bone outlines with labels. When I'm presenting a case to the team, I can point to the specific area I'm talking about without pulling up a three-dimensional reconstruction that takes twenty seconds to load. For patients, the simplest diagrams work best. I print off a basic labeled image from a patient education resource and let them mark where it hurts. Usually they'll point to the anterior tibia and say their shin hurts, which tells me more than I'd get from asking them to describe the location. The diagram becomes a communication tool, not just a study aid. When I was putting together a study guide for junior residents, I compiled diagrams from multiple sources and added my own annotations about common fracture patterns and anatomical variants. That ended up being more useful than any single commercial product because it reflected what I'd actually seen in practice over twelve years. The diagrams showed the anatomy, and the notes showed the problems.