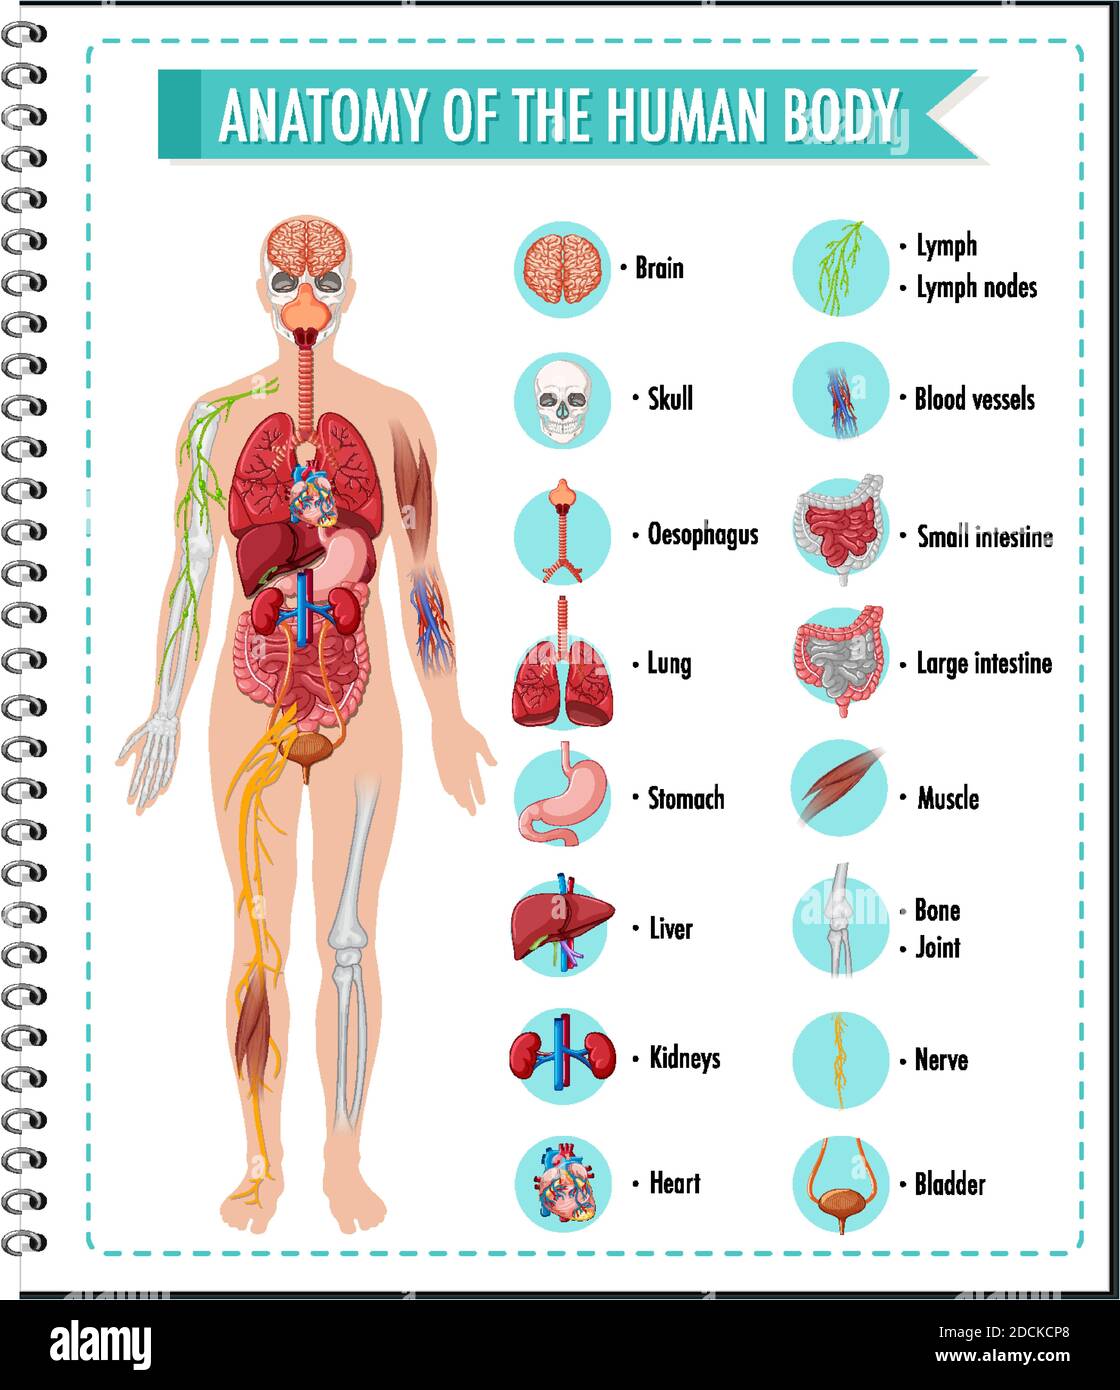
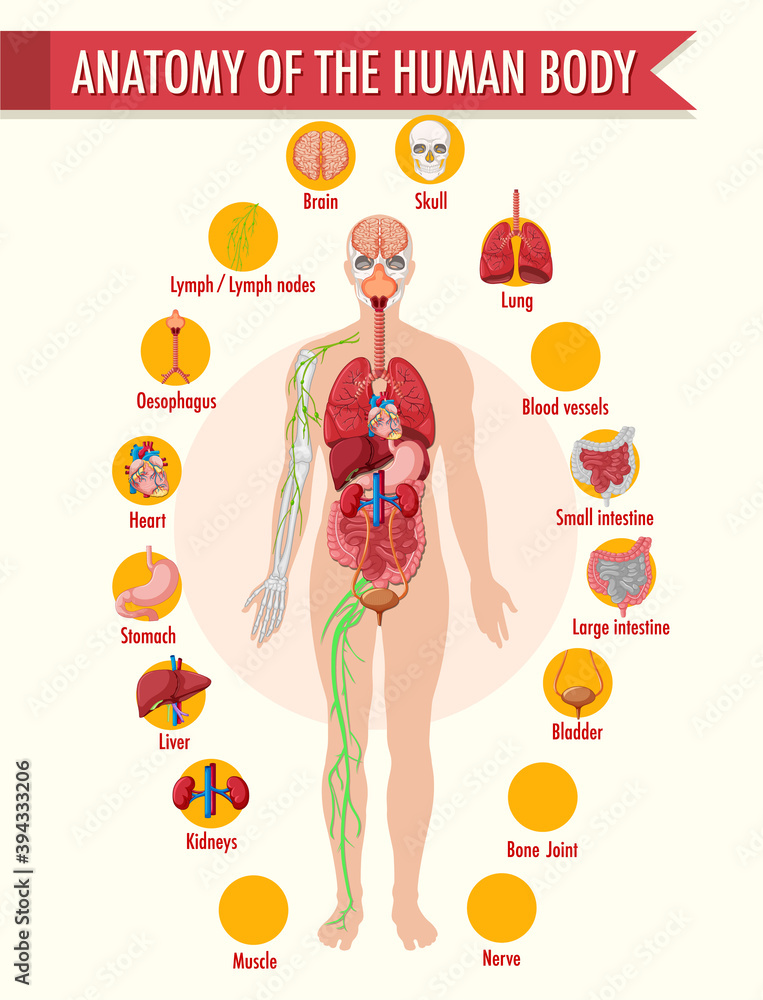
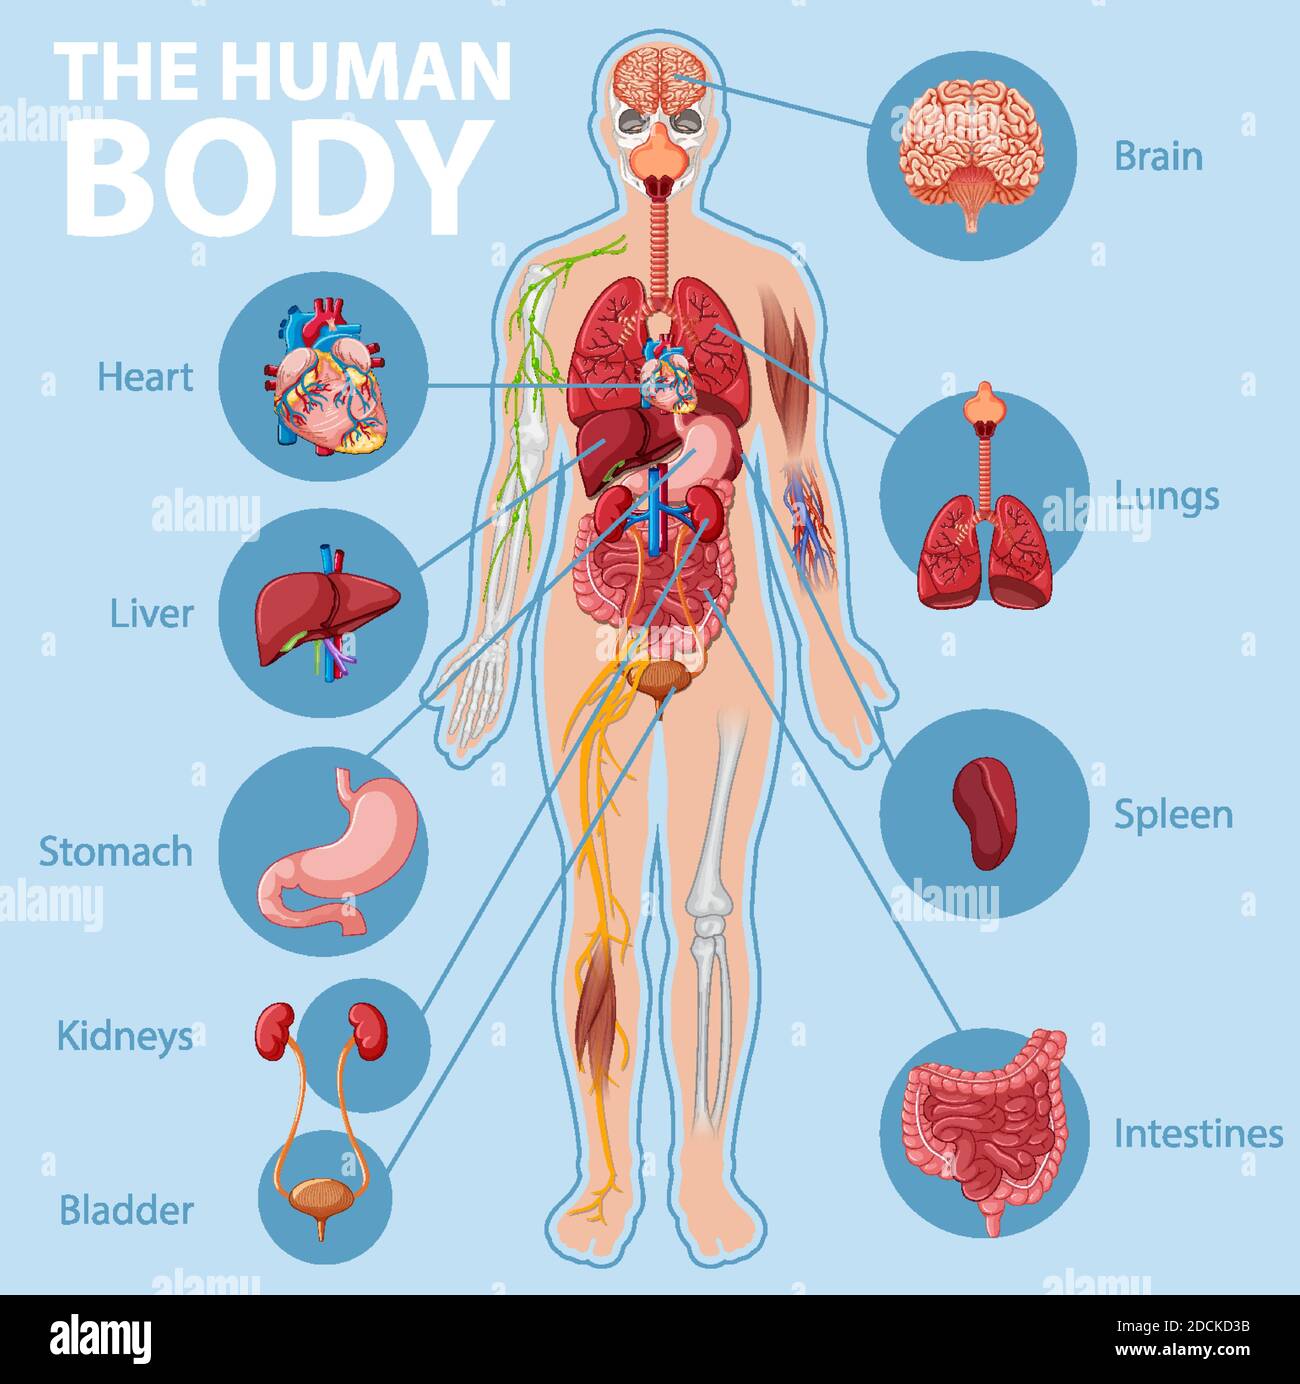
Most people searching for a Diagram Of The Anatomy Of The Human Body end up with either a cartoonish coloring-book version or a dense medical textbook plate that looks like it was drawn by someone who has never actually taught anyone. Neither helps much. One is too simple to be useful beyond high school biology, the other assumes you already know the terminology and just needs something to point at while explaining.
I spent three years helping nursing students and pre-med undergrads actually understand spatial relationships in the body, and what I learned is that a good diagram does one thing poorly and another thing extremely well. The best ones I have ever used were hand-drawn by someone who had been doing cadaver dissections for a decade. They were ugly by design. Every line had a purpose.
What to Look for in a Real Diagram Of The Anatomy Of The Human Body
Start with organ systems rather than trying to memorize every named structure at once. The muscular system diagram you find in standard references usually labels around 640 individual muscles, which sounds impressive until you realize you will never use more than maybe eighty of them in a typical clinical scenario. Focus on the ones that actually matter.
The brachial plexus region trips people up constantly. Most diagrams show it as a neat bundle of nerves emerging from behind the clavicle, but in reality the relationships are messy. I remember one student who was preparing for her anatomy practical and kept mixing up the posterior and lateral cords because the diagram she was studying made everything look symmetrically organized. It took me about twenty minutes to redraw it on a whiteboard with actualrelationships, showing how the cords wrap around the axillary artery rather than sitting in neat rows. She passed her practical that afternoon and never confused them again.
The Skeletal Framework Matters More Than You Think
Bone diagrams are usually the easiest to study because they do not have the same depth complexity as soft tissue, but they are also the most frequently misunderstood. People tend to memorize bone names without understanding the landmarks that actually matter for surface anatomy and clinical procedures. The greater trochanter of the femur is not just a bump you can ignore. It is where the gluteus medius and minimus attach, and identifying it correctly determines whether you can give a safe intramuscular injection in the deltoid versus avoiding nerve damage in the hip region.
The skull is another area where diagrams oversimplify dramatically. The foramen magnum, the sphenoid sinus, the cribriform plate, these are not abstract concepts you can skip. I once watched a physical therapy student fail a spine mobility assessment because she could not locate the C2 vertebra by palpation, even though she could label every bone in a textbook diagram. We spent a single session feeling for the spinous process and the odontoid process on each other, and she finally understood why the atlas and axis move differently from the rest of the cervical column.
Muscles and the Problem of Over-Labeling
A well-made muscle diagram should show origin, insertion, and action clearly labeled for each major group. Too many resources just slap names everywhere without indicating which end moves during contraction, which creates confusion when students later try to understand movement mechanics. The biceps brachii originates on the scapula and inserts on the radial tuberosity, and understanding that relationship explains why supination and flexion happen together rather than being separate unrelated actions.
I encountered a specific edge case while creating teaching materials for a kinesiology course. A student was studying the rotator cuff and could not understand why supraspinatus injuries were so common when the subscapularis also provides significant stabilization. The diagram she was using showed all four muscles as equal contributors, but in practice the supraspinatus passes through the narrowest space beneath the acoracoacromial ligament, making it the first to get impinged during overhead movements. I drew a simplified cross-section showing the actual spacing, and within five minutes she understood the mechanical reason behind the clinical pattern. It was not about memorizing more names, it was about seeing the actual constraints.
Nervous System Diagrams That Actually Help
The peripheral nervous system is where most diagrams fall apart completely. They show the major nerves emerging from the spinal cord and then stop, leaving students to figure out the branching patterns on their own. The brachial plexus, the lumbar plexus, the sacral plexus, these are not isolated structures but overlapping networks that require understanding spatial relationships rather than linear memorization.
The sciatic nerve is frequently misunderstood in textbook diagrams because they show it as a single straight line from the sacrum to the knee. In reality it often splits above the gluteal region, and the division point varies between individuals. I had a student who was studying for her anatomy exam and kept losing points on questions about leg innervation because she assumed the common peroneal and tibial divisions were always separate. She was wrong, and the correction took about ten minutes of looking at actual cadaver specimens rather than relying on the oversimplified diagram.
Visceral Organs and the Challenge of Depth
Internal organ diagrams suffer from a different problem. They usually show everything in a single plane, which makes the abdominal cavity look flatter than it actually is. The liver sits above the stomach, which sits above the intestines, but a flat diagram cannot convey the actual three-dimensional relationships without multiple views. Most resources provide anterior, posterior, and lateral views, but few show the superior-inferior stacking clearly enough for beginners to build mental models.
The relationship between the gallbladder and the common bile duct is one area where diagrams are particularly misleading. They show the duct as a simple tube connecting the liver to the duodenum, but in practice the cystic duct joins the common hepatic duct at an angle that varies between individuals, and stones can lodge at that junction causing obstruction. I remember helping a medical student who was struggling to understand biliary anatomy because every diagram he looked at showed the same idealized configuration. We spent a session looking at actual surgical photographs from open cholecystectomy cases, and within fifteen minutes he understood why the critical view of safety requires identifying three structures before cutting anything. It was not about knowing more terminology, it was about seeing the actual variation.
How to Actually Use These Diagrams Effectively
The most practical approach I have found is to draw your own versions rather than passively studying published materials. The act of creating the diagram forces you to make decisions about what to include and what to omit, and those decisions reveal gaps in your understanding that passive viewing never will. A blank page with a few key bones sketched in pencil takes about five minutes and reveals more about your mental model than an hour of staring at a color illustration.
When you are studying for an exam or preparing clinical skills, print out a diagram and cover half of it with paper. Try to label the visible structures from memory, then check your work. This testing effect is well-documented in educational research and typically improves retention by about forty percent compared to repeated passive review. The process takes about ten minutes per session and works better than any amount of highlighting or re-reading.
Digital resources like Complete Anatomy, Visible Body, and the Gray's Anatomy app offer interactive 3D models that let you rotate structures and peel away layers. They are useful for understanding spatial relationships, but they tend to reinforce passive consumption rather than active recall. I recommend using them for about fifteen minutes to build initial understanding, then switching to hand-drawn diagrams for actual memorization. The combination works better than relying on either method alone.
Common Mistakes That Waste Time
The biggest mistake students make is trying to memorize every label on a diagram rather than understanding the relationships between structures. A diagram showing forty named arteries on the upper limb is not a study goal. It is a reference tool that you should use selectively based on what you are actually trying to learn. Focus on the ten most clinically relevant structures first, then expand your knowledge gradually rather than attempting comprehensive memorization in a single session.
Another frequent error is studying diagrams in isolation without connecting them to actual function. The anatomy of the heart makes sense when you understand that the right ventricle pumps blood to the lungs at lower pressure than the left ventricle pumps to the body, and the wall thickness differences are a direct consequence of that functional requirement. Without understanding the why, the structural details become arbitrary facts that are difficult to retain and easy to forget under exam pressure.
When Diagrams Are Not Enough
No diagram can fully replace hands-on experience with actual specimens, whether that is cadaver dissection, prosected specimens, or high-quality photographic atlases from surgical procedures. The tactile feedback from palpating real structures, feeling the texture of different tissues, and observing the actual color and consistency of organs provides information that flat images simply cannot convey. Even the most detailed diagram of the knee joint cannot replicate the experience of actually manipulating the ligaments and feeling their tension during flexion and extension.
For clinical skills training, I recommend supplementing diagram study with palpation practice on living subjects. Learning to feel the pulsation of the radial artery, identifying the crest of the ilium by touch, locating the apex beat of the heart on a chest wall, these are practical skills that diagrams can support but never replace. A diagram shows where the structures are supposed to be. Your fingers tell you where they actually are in the person lying in front of you.
Gallery Diagram Of The Anatomy Of The Human Body
Premium Photo | Diagram of the human body with internal organs and bones
Vetor de Anatomy of the human body information infographic do Stock | Adobe Stock
Anatomy Chart Of The Human Body Anatomical Position - Printables Templates Free
Human Anatomy Male Body And Organs Diagram High-Res Vector Graphic - Getty Images
Human Body Diagram Anatomy