Understanding Surface Foot Anatomy Diagrams
I've spent years working with anatomical references for the lower extremity, and most people approach this the wrong way. They pull up a generic Diagram Surface Foot Anatomy illustration and think they understand what they're looking at. They don't. The gap between a decent reference diagram and actual clinical application is where most mistakes happen. A surface foot anatomy diagram shows you the visible and palpable landmarks of the foot, but it doesn't teach you how those landmarks shift during movement. That's the first thing you need to accept before you go further.
Why a Diagram Surface Foot Anatomy Resource Matters
The foot has twenty-six bones, thirty-three joints, and over one hundred muscles, tendons, and ligaments. When you're looking at a diagram, you're seeing a static representation of something that is constantly changing shape under load. A supinated foot looks completely different from a pronated one, yet most diagrams only show a neutral or weight-bearing frontal view without noting that distinction. I learned this the hard way during my second year of practice. I was studying a standard surface anatomy diagram for the plantar aspect of the foot and memorized the course of the tibialis posterior tendon insertion point. Two weeks later, I was assessing a patient with posterior tibial tendon dysfunction and couldn't palpate the insertion reliably because the diagram never showed what happens when the arch collapses. The landmark literally disappears under soft tissue deformation during pronation. I spent another six months relearning the dynamic variations through palpation practice on real patients rather than relying on static illustrations.
What You'll Find on a Standard Reference Diagram
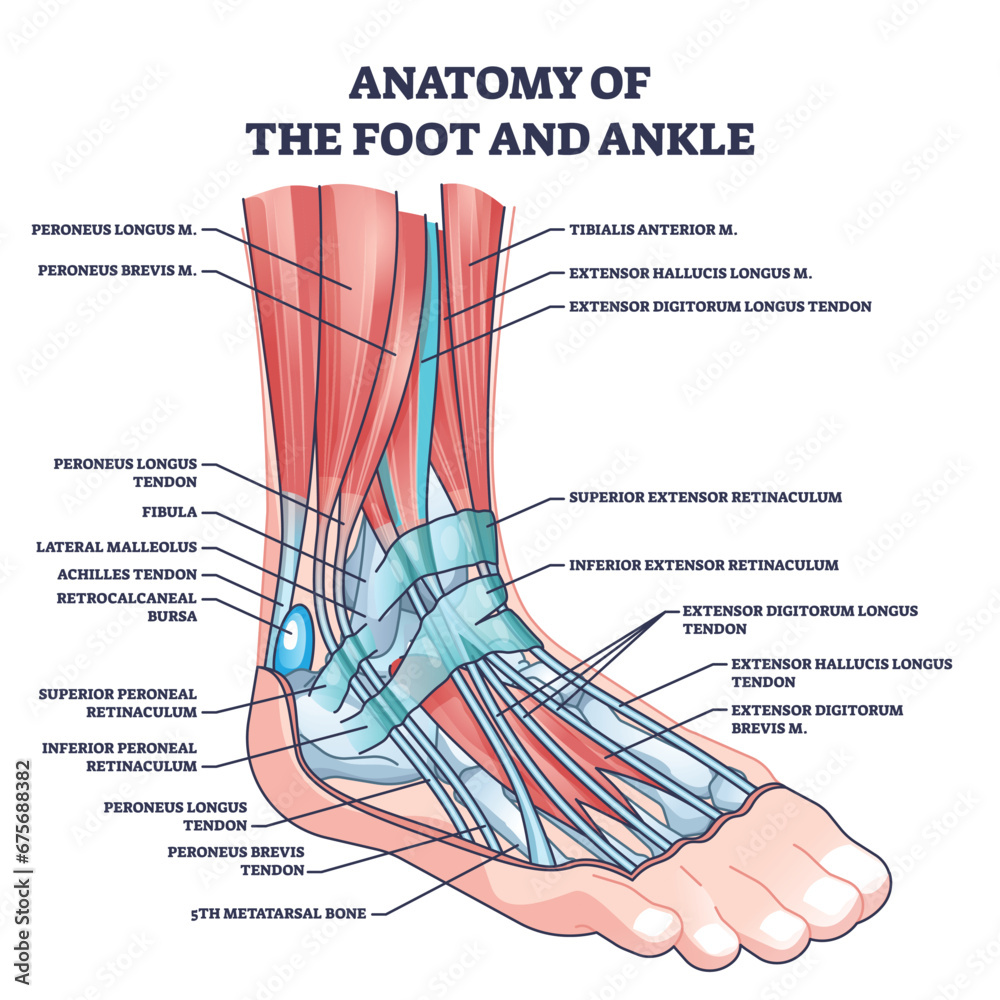
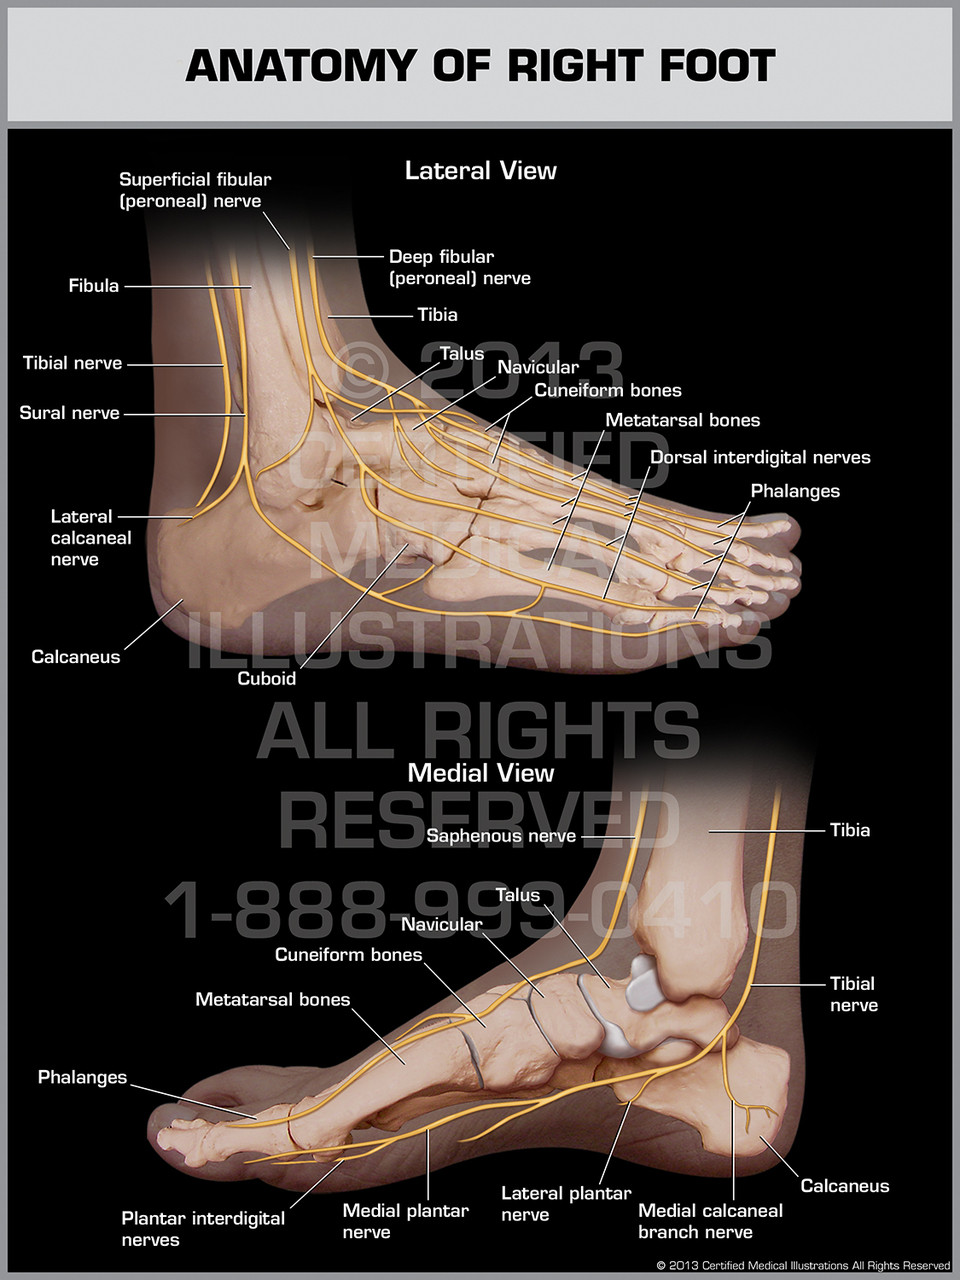
The dorsum of the foot is the easier side to start with. You'll see the extensor digitorum longus tendons running toward the lateral four toes, the extensor hallucis longus separating medially toward the great toe, and the peroneus tertius fading into the lateral border. The dorsal veins form a visible network that diagrams often gloss over but that you'll need for venipuncture or assessment of venous insufficiency. The plantar surface carries more clinical information but is also where diagrams do the worst job. The sole is divided into three compartments, and the superficial layer contains the abductor hallucis, flexor digitorum brevis, and abductor digiti minimi. Diagrams show these as clean layered illustrations. In practice, the medial plantar nerve and artery sit just deep to the abductor hallucis, and the lateral plantar nerve and artery run beneath the abductor digiti minimi. Neither structure is visible on the surface, but knowing their approximate depth matters when you're performing injections or assessing nerve entrapment. The calcaneal region on a diagram usually shows the plantar fascia originating from the medial tubercle of the calcaneus and spreading distally. What the diagram won't tell you is that the medial band of the plantar fascia is the thickest and most clinically significant portion. It's also the most common site of fasciitis. The lateral and central bands get far less attention in most resources, which is a mistake if you're dealing with lateral foot pain that isn't peroneal in origin.
Get the Full Details

Palpation Over Passive Viewing
The diagram is a starting point, not a destination. Here's what actually works: take a standard Diagram Surface Foot Anatomy reference and use it alongside live palpation. Start with your own foot because it's accessible and you can actively change its position. Stand barefoot and roll your foot slowly from supination to pronation while tracking the bony landmarks. The navicular tuberosity becomes prominent on the medial side during pronation. The fifth metatarsal base rises laterally during supination. The cuboid shifts appreciably under the skin along the lateral midfoot. You can feel these movements in real time, and no static diagram conveys that information as effectively as the actual kinesthetic feedback. For the dorsal aspect, place your thumb just distal to the ankle joint and ask someone to dorsiflex and plantarflex their foot. The tibialis anterior tendon becomes clearly visible and palpable as it passes anterior to the ankle and inserts on the medial cuneiform and first metatarsal base. The diagram shows the tendon. Your fingers tell you when it's tight, when it's adhered, and when there's a gap suggesting partial rupture.
Common Landmarks Beginners Misidentify
The medial malleolus is straightforward. The lateral malleolus is straightforward. The first metatarsal head is palpable when the great toe is extended. Where people consistently go wrong is identifying the navicular bone on the medial side. It sits roughly 1.5 to 2 centimeters distal to the medial malleolus and is easiest to find by tracing along the tibialis posterior tendon proximally until it reaches its insertion. The scaphoid (navicular) is the landmark. Diagrams label it clearly, but the distance from the malleolus varies considerably between individuals based on arch height and soft tissue volume. Another frequent error involves the peroneal tendons behind the lateral malleolus. These sit in a fibro-osseous retinaculum that diagrams rarely depict in cross-section. During ankle inversion injuries, the superior peroneal retinaculum can rupture, allowing the peroneus brevis tendon to subluxate anteriorly over the lateral malleolus. A static diagram won't help you recognize that clinically. You need to understand the three-dimensional relationship, and that comes from imaging studies and hands-on palpation, not from looking at a flat illustration.
What These Diagrams Leave Out
Most Diagram Surface Foot Anatomy resources omit the neurovascular pathways at clinically relevant depths. The plantar nerves branch significantly within the substance of the plantar fascia. If you're performing a nerve block or injecting into the plantar surface, knowing that the medial and lateral plantar nerves diverge just distal to the flexor retinaculum can prevent complications. That detail rarely appears on surface diagrams. The arterial anastomoses around the foot are another gap. The dorsalis pedis artery anastomoses with the lateral plantar artery through the deep plantar arch. Diagrams show both vessels but don't convey the collateral circulation that makes this anastomosis clinically important in peripheral arterial disease. A blocked femoral artery might still permit viable perfusion to the foot through this network. Surface diagrams don't communicate that kind of functional redundancy. There's also the matter of age-related changes. Pediatric feet have apophyses and growth plates that shift the surface landmarks. The calcaneal apophysis is a common site of Sever's disease, and the tuberosity prominence varies with skeletal maturity. Adult diagrams applied to pediatric assessment lead to misdiagnosis of normal developmental variants as fractures. I've seen this happen repeatedly in clinic settings where references weren't age-stratified.
Practical Workflow
Start with a reliable Diagram Surface Foot Anatomy reference that includes both dorsal and plantar views in neutral and weight-bearing positions. Multiple reference sources are better than a single detailed one because each has different strengths. Netter's Atlas handles the muscular anatomy well, while Gray's Anatomy provides more complete neurovascular detail. Clinical references like Magee's Orthopedic Physical Assessment tie the anatomy to examination maneuvers. Once you have your references, spend fifteen minutes each day palpating landmarks on a willing partner or family member. Document what you find in a notebook with timestamps and conditions, noting whether the person was weight-bearing or non-weight-bearing. This builds a personal reference library that no published diagram can replicate. After about three weeks, you'll start recognizing patterns that allow you to predict anatomical variations before you even palpate them. The diagrams remain useful, but they're reference maps, not territory. The foot is a complex biomechanical structure that changes configuration under load, and any Diagram Surface Foot Anatomy resource you consult should be treated as a guide to where things generally are rather than a precise atlas of where they always are. That distinction separates competent practitioners from the ones who rely too heavily on static illustrations and miss what's actually happening in front of them.