What Davita Actually Expects From New Techs
Davita's Dialysis Technician Training Davita program is their internal onboarding pipeline for people who need to get certified and placed on the floor within a few weeks. The program runs across every clinic location, but the curriculum itself is standardized. You will go through classroom modules, hands-on station rotations, and then supervised shifts where you run patients under the watch of a senior tech or the charge nurse. Most people finish the core training block in roughly 4 to 6 weeks, but that timeline stretches out if you have work restrictions, if staffing is thin, or if your preceptor is pulled away for patient care. The training splits into three phases. First is the classroom portion, which covers dialysis basics: how hemodialysis works, vascular access care, machine operation, infection control, and the regulatory requirements like CMS conditions and state licensing rules. Second is the skills lab, where you practice cannulation on training arms, run the machines in demo mode, and drill through water treatment systems. Third is clinical rotation, where you shadow an assigned preceptor and gradually take on real tasks under direct supervision. You cannot independently run a patient until your preceptor signs off and your clinic manager confirms competency. The thing nobody tells you upfront is that the sign-off process is not just a formality. Your preceptor is legally accountable for what you do on the floor. They are going to watch you closely, and they are not going to sign off on something they are uncomfortable with. I learned this the hard way during my second rotation when I was cleared for routine vital signs and weight tracking but not yet approved for cannulation. A patient had a particularly stubborn fistula with scarring, and my preceptor had stepped into a treatment room for an emergency. Another tech asked me to help, and I said yes even though I was still in the restricted category. I got the patient onto the machine without issue, but when the charge nurse found out later that day, my preceptor had to document the incident and I lost signing authority for two weeks while they reassessed my readiness. The workaround was straightforward after that: if you are not signed off, you say no. Politely, but firmly. The patient will not suffer, and neither will your record.
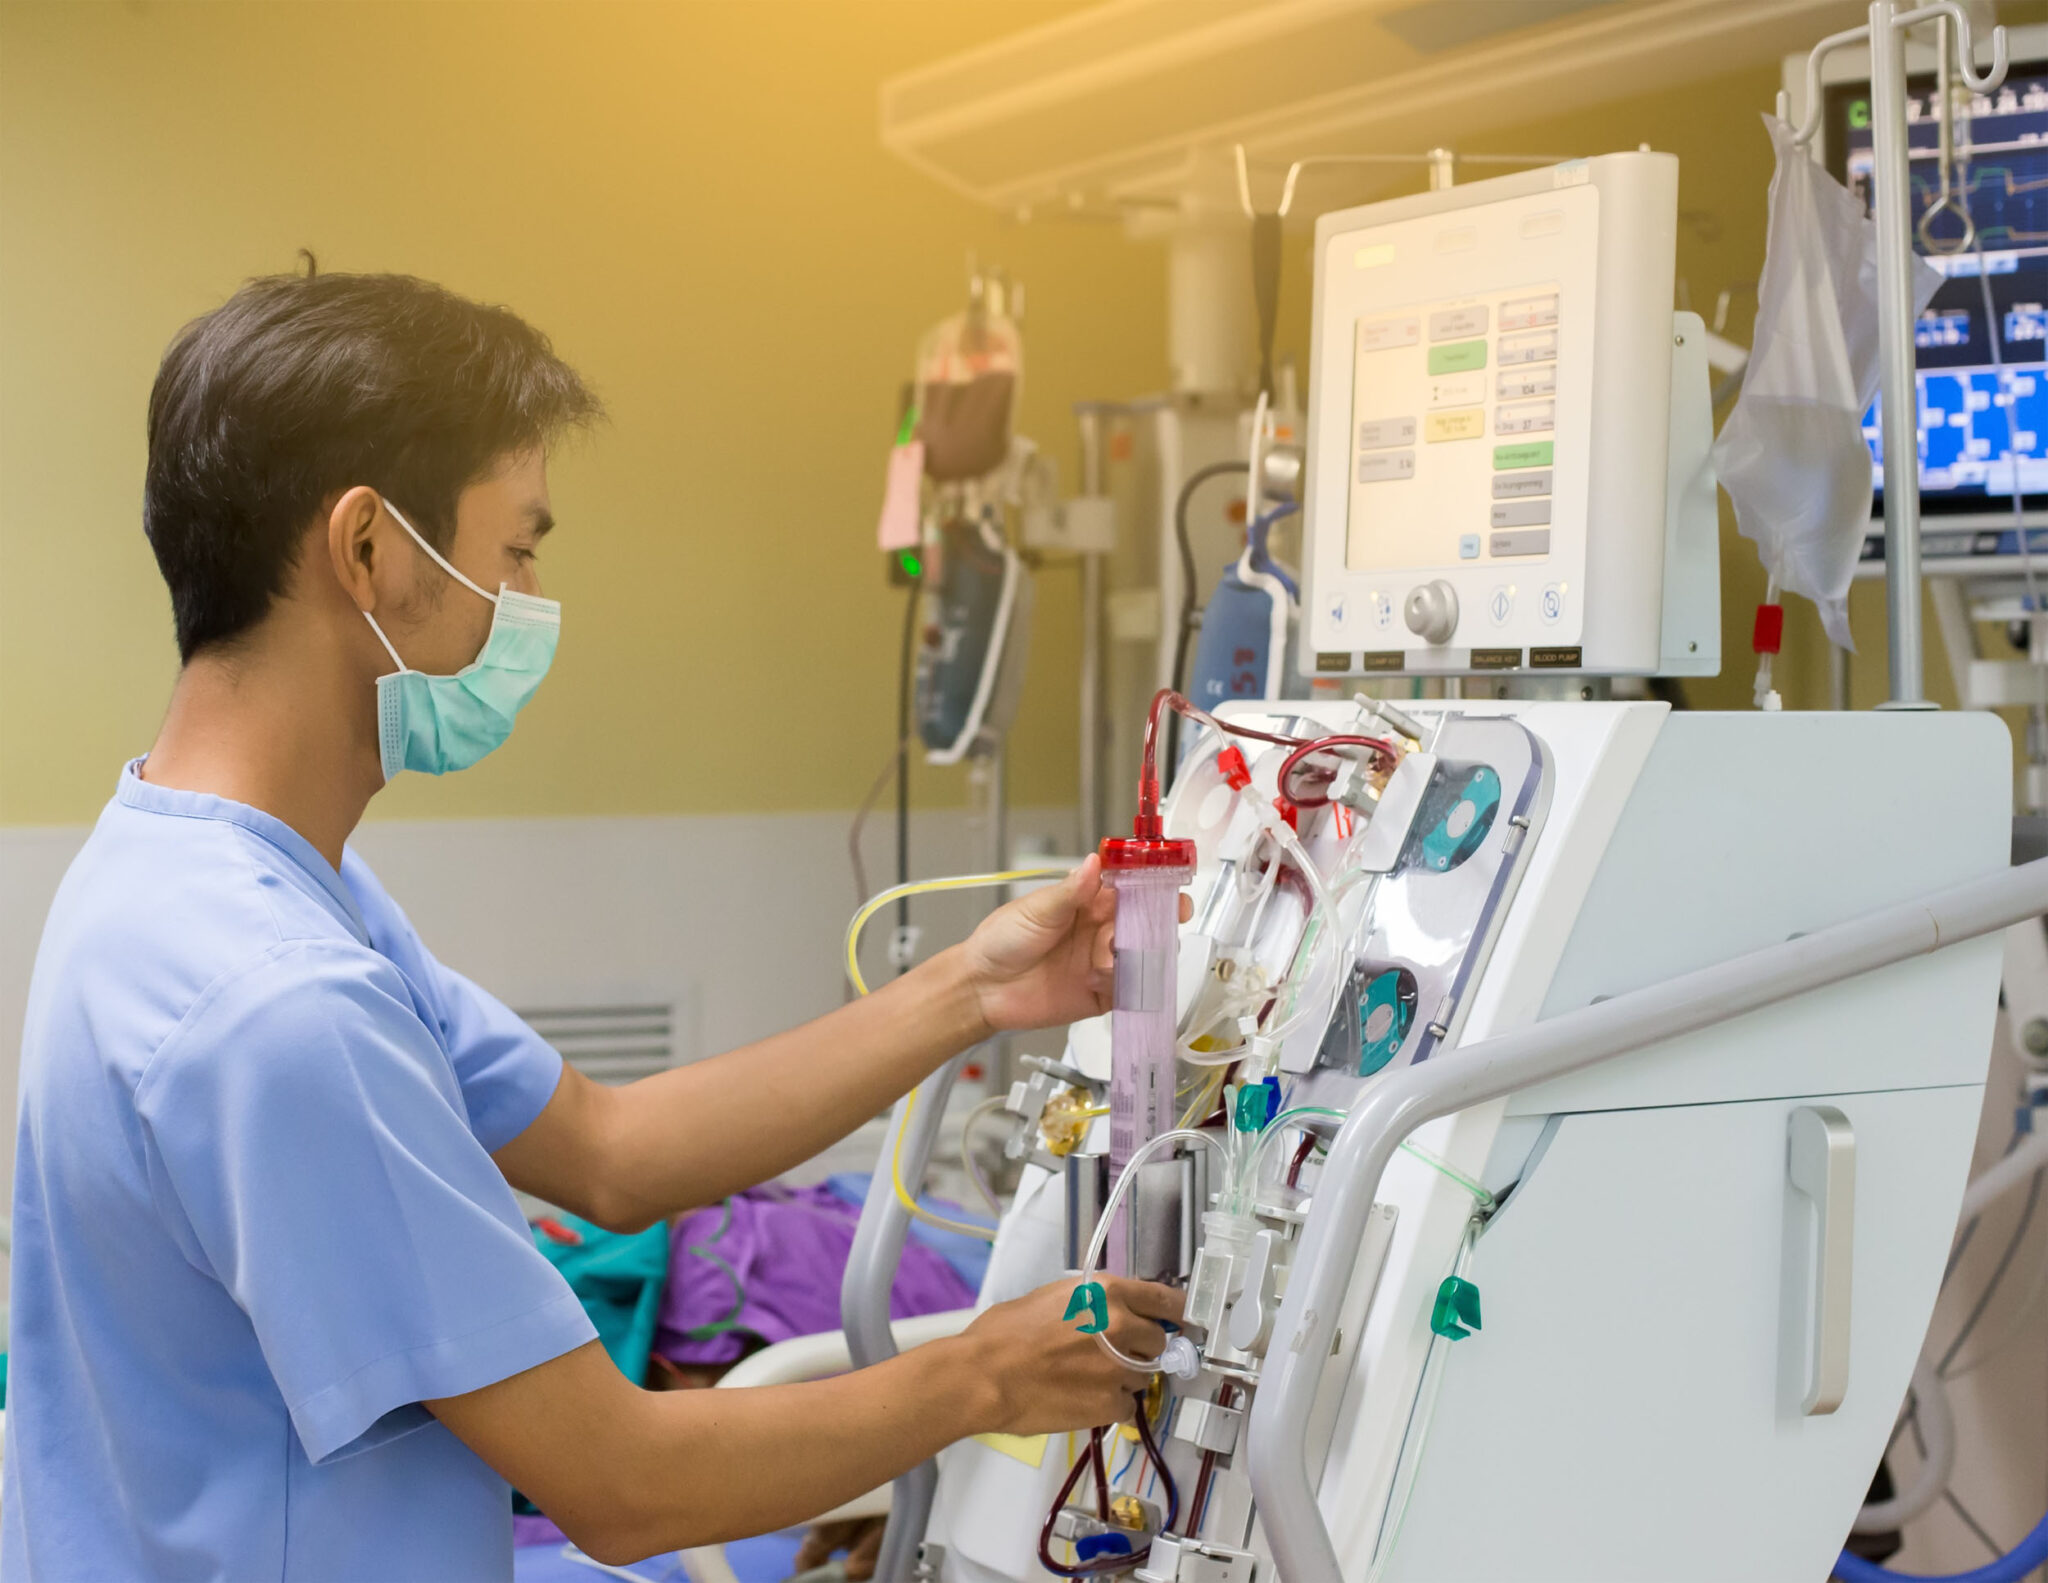
There is also a counterintuitive detail about machine setup that most beginners overlook. The dialysis machines at Davita are mostly Fresenius 5008 series, and the computer-driven setup sequences can make you feel like you do not need to understand the underlying mechanics. The screen walks you through priming, saline fill, and air detection checks. But here is the thing: when alarms start going off mid-treatment, the screen diagnostics will often point you toward a generic cause while the real issue is something physical, like a kinked arterial line or a partially occluded needle. I once spent twelve minutes troubleshooting a blood leak alarm on a 5008, cycling through the menu prompts, while the actual problem was that the patient had rolled over and pinched the return line against the bed frame. If you understand how the blood path works instead of relying solely on the computer prompts, you save time and reduce alarm fatigue for the whole station. Another area where people trip up is water treatment. You will get tested on it during training, but the practical knowledge matters more than the test score. The reverse osmosis system, the water distribution loop, and the point-of-use deionizers are what keep the dialysate safe. Chloramine testing is non-negotiable, and the carbon filters need to be monitored on schedule. I recall one shift where the water quality alarm flagged a chloramine reading slightly above threshold. The COA had been signed off the day before, but the carbon tank was older than its recommended service interval, and the flow rate had been bumped up during a busy morning to keep up with demand. That combination dropped the carbon contact time below what the manufacturer specifies. We took one machine offline, flushed the loop, and swapped the carbon tank within forty minutes. After that, I made it a habit to check the carbon filter service dates during my own machine setup rather than assuming the facilities team had covered it.
What You Should Do Before You Start
Before you walk into orientation, get a copy of your state's dialysis technician licensing requirements. Davita will train you, but your state license or certification is what actually qualifies you to work independently. Some states require a CDET credential from the NDTAA or the BONENT exam. Others have their own nursing board requirements. Do not assume that completing Davita's internal program alone satisfies state law. It does not. The training gets you competent. The exam or credential gets you legal. Learn the Fresenius 5008 interface before day one. Watch some videos on YouTube, read through the operator manual, and familiarize yourself with the alarm hierarchy. When you show up already knowing where the saline pump controls are and what the bicarbonate concentration buttons do, you look prepared instead of reactive. Preceptors notice that. Download link and resource note: Davita does not publish their full internal training curriculum online, and there is no official downloadable PDF of the complete program. What you will find on third-party sites claiming to offer "Dialysis Technician Training Davita downloads" are usually outdated study guides or generic nephrology materials that do not reflect current Davita protocols. The legitimate path is through Davita's own careers portal or by contacting a clinic hiring manager directly. Once you are hired, the training materials, LMS access, and skills checklists are provided through their internal systems.
Get the Full Details

Common Pitfalls During the Program
The biggest mistake I see is people treating the classroom modules as something to rush through so they can get to the clinical rotation. The classroom modules are where the regulatory framework is built. CMS conditions, documentation requirements, adverse event reporting, and the legal standards for dialysis practice all live there. If you skip the detail, you will make costly errors later, like charting vitals in the wrong field or missing a required pre-treatment assessment step. Another pitfall is assuming that every clinic operates the same way. Davita is standardized, but individual clinics have their own workflows. Some prioritize vascular access care more heavily. Others focus on patient education compliance. The preceptor you are paired with shapes your daily experience. A good preceptor will slow down and explain the why behind each step. A rushed preceptor will expect you to absorb things passively, which rarely works. If you are not getting clear instruction, ask directly. Say you want to make sure you are following their preferred method and ask them to walk through the steps again. That is not annoying. It is expected. There is also the issue of burnout before you even finish training. Dialysis tech work is physically demanding. You are on your feet for hours, lifting patients, managing lines, and dealing with difficult symptoms. It is emotionally heavy too. Patients in crisis, families who are scared, and the constant pressure of machine alarms create a cumulative stress that is easy to underestimate. I knew someone who quit two weeks into clinical rotation because they had not realized how much emotional labor was involved, not just the technical side. If you are feeling overwhelmed, talk to your trainer. The program is designed to support you, but they cannot help unless you tell them something is wrong.
After You Complete the Training
Once you finish the program and get signed off, you are still not done learning. The real education happens in the first six months on the floor. You will encounter edge cases that were never covered in training: a patient with an aneurysm rupture risk, a difficult dialysis access that requires ultrasound-guided cannulation, or a machine that throws a code that the quick-reference guide does not address. Keep a notebook. Write down what happened, what you did, and what the outcome was. Review it before your next shift. That habit alone will separate competent techs from ones who are just going through the motions. Also, maintain your certification. If your state requires annual continuing education or a recertification exam, do it on schedule. Lapses in certification create problems for the clinic and for you. There is no workaround for that. You are not allowed to work independently without current credentials, and the compliance team tracks this automatically through the scheduling system.