What Actually Works When You're Trying to Manage Blood Sugar Through Food
Most people getting started on dietary advice for type 2 diabetes walk into this completely unprepared. They've read headlines about superfoods and keto, maybe picked up a pamphlet from their endocrinologist's office, and now they're staring at a spreadsheet of carb counts trying to figure out where to begin. I watched this happen repeatedly when I was consulting for a diabetes education clinic back in 2018. The gap between what patients think they need to do and what actually moves the needle on their A1C is wider than most guides admit. The core mechanism here isn't complicated, but it's easy to get wrong in practice. Type 2 diabetes is fundamentally about insulin resistance — your cells don't respond efficiently to insulin, so glucose stays in your bloodstream longer than it should. The dietary approach aims to reduce the glucose load your body has to deal with at any given time while improving insulin sensitivity through other means. Carbohydrate management gets the most attention because it's the most direct lever, but that's only part of the picture.
Dietary Advice For Type 2 Diabetes That Isn't Just "Eat Less Carbs"
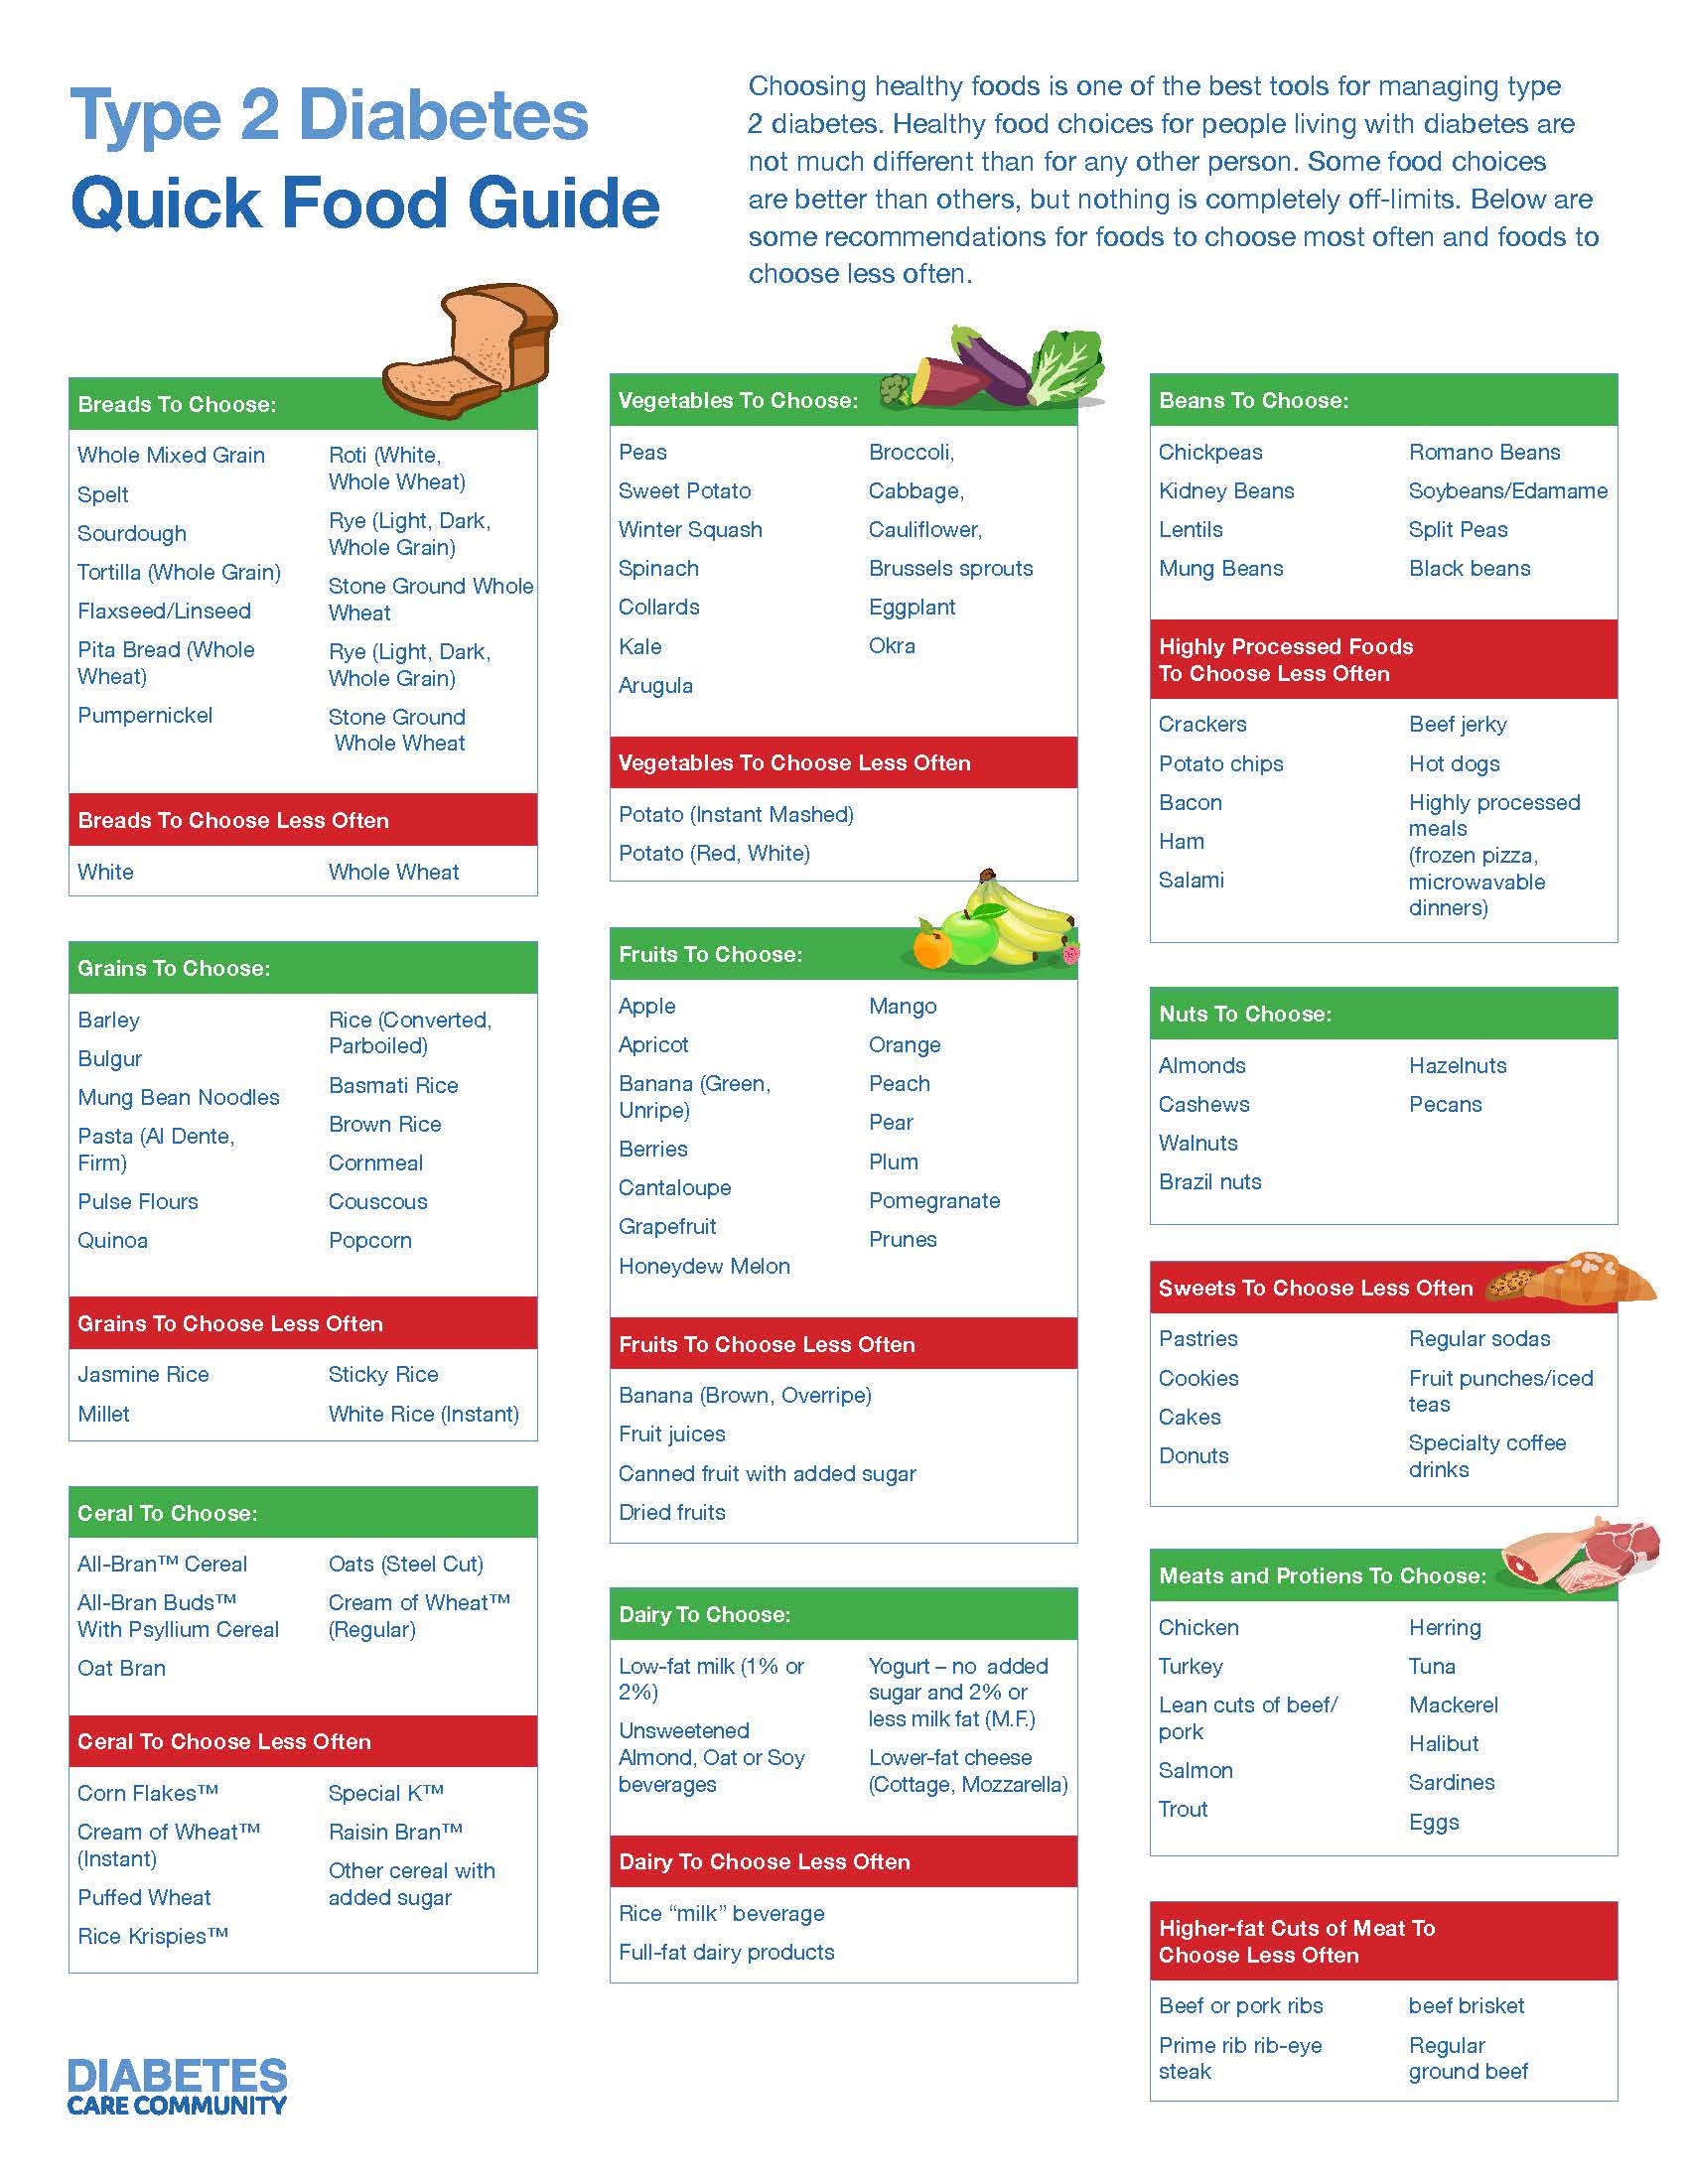
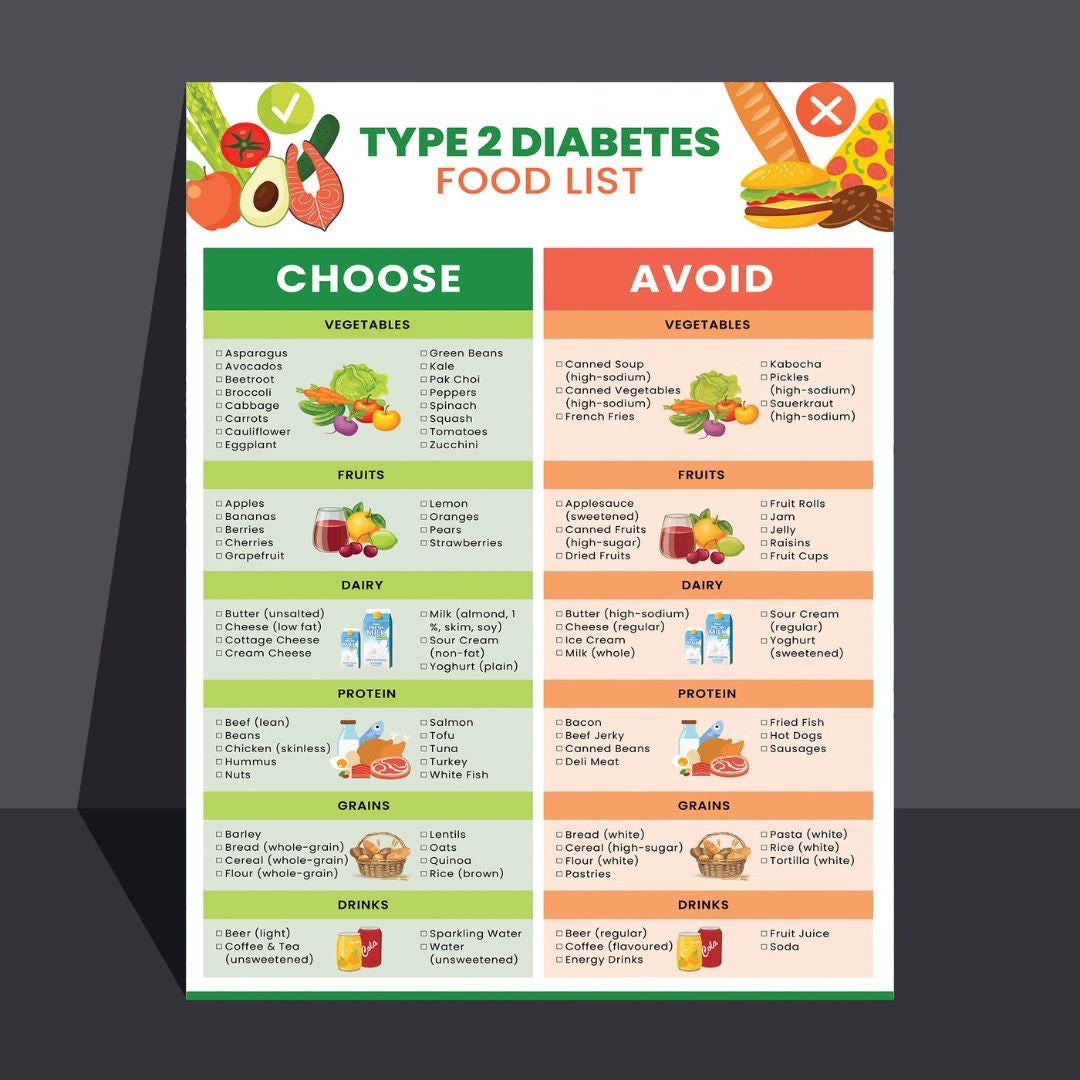
Let me give you the sequence that actually works, even though it's not the order most resources present it in. Start with meal timing and protein distribution, then worry about carb quality, and only after that concern yourself with the specific numbers. Here's why: two patients can eat the exact same number of carbohydrates but get wildly different blood glucose responses depending on whether they ate protein and fat before the carbs, and whether they're spreading intake across three meals or two. The order you eat things matters more than most people realize. A practical starting point most people can implement without much friction: eat a small protein-rich food — anything from Greek yogurt to a handful of almonds to some cheese — about fifteen to twenty minutes before your main carbohydrate-containing meal. This primes insulin secretion and slows gastric emptying. In my experience, this simple sequencing tweak alone can reduce postprandial glucose spikes by thirty to fifty milligrams per deciliter for many people. It's not dramatic enough to replace medication if you need it, but it's noticeable and it costs nothing. Now, onto the carbohydrate side of things. The standard advice is to count carbs and stay under a certain threshold per meal, usually somewhere between forty and sixty grams. That framework isn't wrong, but it's incomplete. Total carb count misses the distinction between rapidly digestible starches and slowly digestible ones. Half a cup of white rice and half a cup of steel-cut oats can have nearly identical carb counts, but your blood glucose will react to them very differently. The glycemic index exists for this reason, though it's more useful as a relative guide than an absolute rule. Resistant starch — found in cooled cooked potatoes, legumes, and slightly green bananas — behaves more like fiber than like sugar in your gut. Accounting for resistant starch and fiber separately from total carbohydrates gives you a much more accurate picture of actual glucose impact.
There's a specific edge case that trips people up regularly, and I ran into this myself when I was managing my own pre-diabetic markers before they fully resolved. You eat what looks like a perfectly reasonable meal — say, a smoothie with berries, banana, Greek yogurt, and protein powder — and the carb count looks fine on paper, maybe thirty-five grams of net carbs. But within forty-five minutes your glucose is spiking like you just drank a glass of soda. The issue is that blending breaks down cell walls in the fruit and releases sugars that would otherwise be digested slowly. A whole apple and a blended banana in a smoothie can produce dramatically different glucose curves even though the carb count is similar. The workaround is straightforward: keep your fruits whole when possible, and if you do blend things, add extra fiber or fat to slow absorption. A tablespoon of chia seeds or a quarter cup of full-fat yogurt in that smoothie makes a measurable difference. Here's something most beginner guides don't emphasize enough: the relationship between body fat and insulin resistance isn't just about weight loss, though losing visceral fat does help significantly. Your meal composition affects inflammation and liver fat content independently of total calories. Replacing refined carbohydrates with monounsaturated fats — olive oil, avocados, nuts — improves insulin sensitivity through pathways that have nothing to do with calorie restriction. The PREDIMED study looked at this directly, and participants on a Mediterranean-style diet with extra virgin olive oil showed meaningful improvements in insulin sensitivity even without deliberate calorie cutting. You don't have to follow that diet exactly, but the principle holds: fat quality matters as much as carb quantity. Fiber intake is another area where the advice-is-right-but-the-execution-is-wrong pattern shows up constantly. The general recommendation is twenty-five to thirty-five grams per day, and most people in developed countries eat about half of that. Soluble fiber — from oats, beans, psyllium husk, apples — forms a gel in your digestive tract that physically slows glucose absorption. Insoluble fiber — from whole grains, vegetables, nuts — adds bulk and affects gut transit time. Both matter, but soluble fiber is the one that directly blunts post-meal glucose spikes. Adding five to ten grams of soluble fiber per day can reduce postprandial glucose excursion by roughly ten to fifteen percent in clinical settings. Psyllium husk taken with water before a meal is one of the most underutilized tools I've seen in practice, and it costs about two dollars a month.
Get the Full Details

Let me be clear about where this approach hits limits, because it's important not to oversell it. If your pancreatic beta-cell function is significantly impaired — which happens in advanced type 2 diabetes — dietary changes alone won't bring your A1C into target range no matter how carefully you manage meals. In those cases, medication or insulin is necessary regardless of diet. The dietary approach works best as a first-line intervention for recently diagnosed patients, for people with mild to moderate insulin resistance, and as a complementary strategy alongside pharmacological treatment. It's also less effective if you're eating outside your normal routine frequently — shift work, irregular meal times, or social situations that force you to eat on unpredictable schedules can undermine even the best meal planning. No amount of carb counting fixes a lifestyle that doesn't allow consistent eating patterns. Another limitation worth stating plainly: self-monitoring blood glucose gives you useful feedback, but it has real constraints. A home glucometer typically has a margin of error of about fifteen percent, and finger-prick measurements only capture a single moment in time. You might check your glucose two hours after a meal and see a reasonable number, not realizing that your spike at forty-five minutes was dangerous. Continuous glucose monitors solve this problem but they're expensive and not always covered by insurance. The practical compromise is to check fasting glucose every morning and check post-meal readings at least three to four times per week, rotating through different meals so you actually see the variety in your daily glucose response. When it comes to specific food swaps that tend to move the needle, the highest-yield changes are usually the ones people resist the most because they involve giving up familiar staples. Swapping white rice for cauliflower rice mixed with regular rice at a one-to-one ratio cuts the carb load of a typical serving by roughly half without changing the texture dramatically. Replacing bread with large lettuce wraps or low-carb tortillas for the things you actually need wrapping — sandwiches, tacos — eliminates about twenty to thirty grams of rapidly digestible carbs per meal. These aren't permanent lifestyle overhauls; they're targeted substitutions that reduce glucose load while keeping the foods you enjoy recognizable.
Alcohol deserves a mention because it's a common source of unexpected glucose disturbance. Hard liquor doesn't spike blood sugar directly, but mixed drinks often do. Beer contains substantial carbohydrates, and wine sits somewhere in between. More importantly, alcohol impairs gluconeogenesis in the liver, which means your body's ability to release stored glucose during fasting periods is temporarily reduced. If you're on medications that stimulate insulin production — sulfonylureas like glipizide or glyburide — combining them with alcohol increases hypoglycemia risk significantly. Even for people not on those medications, a heavy drinking session can cause delayed low blood sugar the next morning because your liver is busy metabolizing the alcohol instead of managing glucose. The sustainable version of this isn't about perfection. It's about understanding which levers affect your glucose the most and pulling them consistently rather than trying to control every variable at once. Track your fasting glucose weekly. Monitor one or two post-meal readings per day. Notice how different foods make you feel — energy crashes, hunger patterns, sleep quality — these are real data points even if they don't show up on a glucose monitor. And if your numbers aren't improving after six to eight weeks of consistent dietary changes, that's not a failure of the approach, it's information. It means you need to talk to your doctor about adjusting your medication or investigating other factors like sleep apnea, cortisol dysregulation, or medication side effects that might be interfering with your progress.