What Actually Changes in Each Month of Pregnancy Nutrition
Most pregnancy diet guides just list foods and calories. They miss the part where your body literally stops processing things the same way from month to month. Your insulin sensitivity drops significantly by the third trimester, which means the same meal that kept you stable at month three will spike your blood sugar at month seven. Understanding this shift matters more than any food list.Diets During Pregnancy Month By Month
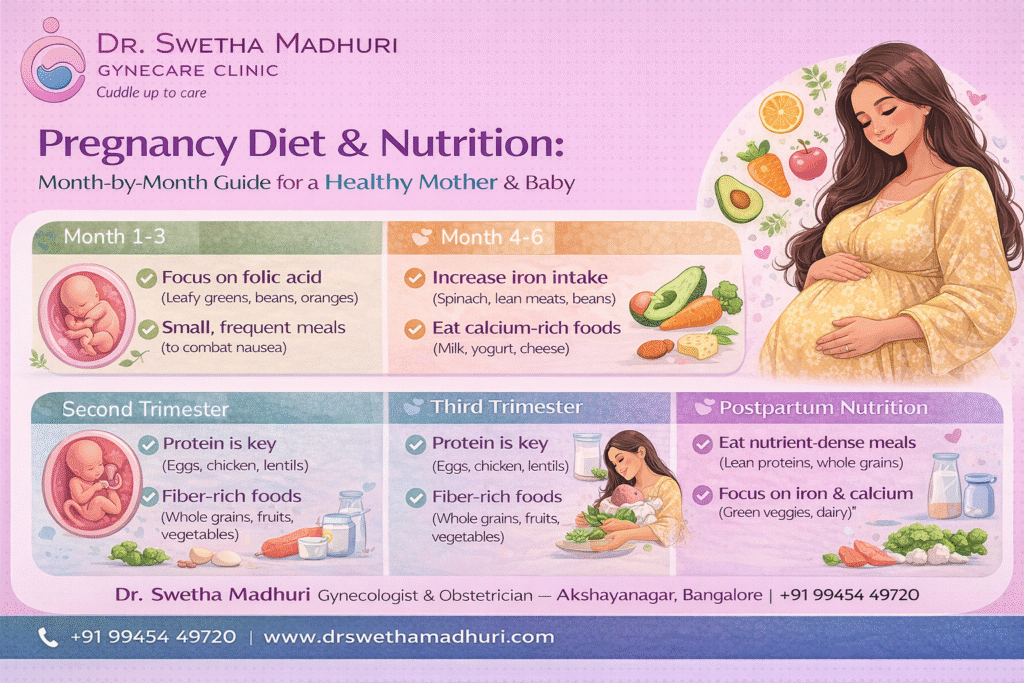
In the first month, you haven't changed your diet yet. Nobody tells you this because it sounds anticlimactic. Your embryo is the size of a poppy seed. Your caloric needs haven't moved. What matters now is getting folic acid — at least 400 micrograms daily — and making sure you're not eating anything that could carry listeria or toxoplasma. Raw sushi, unpasteurized cheese, and undercooked eggs are actual problems at this stage. The risk is low but the consequences aren't worth the snack. Month two is where the real test starts. Nausea hits about 60 percent of pregnant people somewhere between weeks four and nine. The standard advice is to eat small frequent meals and keep crackers by the bed. That works for some people. For others, it's completely useless. I had a patient once who couldn't tolerate the smell of almost anything, including the crackers she'd been told to keep ready. The workaround was cold foods instead of warm ones — cold chicken breast, cold rice balls, plain yogurt. Warm smells trigger more nausea because volatile compounds become more active. Cold food stays relatively odorless. She ended up maintaining her weight on a diet that mostly looked like a hospital cafeteria at room temperature, but she stayed nourished and nobody panicked. By month three, the first trimester nausea usually eases enough that appetite returns. This is also the month most people start thinking about prenatal vitamins as a shield, which they sort of are, but not in the way marketing suggests. A prenatal vitamin does not make a bad diet acceptable. It fills specific gaps — iron, folate, DHA — but it won't give you adequate protein or the broader nutrient profile your developing fetus actually needs. Focus on hitting roughly 75 to 100 grams of protein daily. That's the number most people dramatically undershoot in month three when they feel "fine" again and go back to their old eating patterns without realizing the baby's growth rate is about to accelerate.
Month four kicks into the second trimester proper. Your blood volume is expanding faster now, and your iron requirements jump noticeably. You might not feel different, but your body is building a whole new circulatory system for the placenta. Red meat, lentils, fortified cereals — whatever gets you iron — should be on your plate more often this month. Pair it with vitamin C to improve absorption. Don't pair it with calcium supplements or large amounts of dairy at the same meal, because calcium competes with iron for uptake. This is one of those details nobody emphasizes until someone's ferritin comes back low at a routine blood work check. Month five is when you'll likely feel the strongest hunger signals. Your metabolic rate has increased by roughly 300 calories above baseline, and your baby is building bone and fat stores rapidly. This is the month where people either gain too much or not enough because they misjudge how much extra they actually need. Three hundred calories is not a large meal. It's roughly a turkey sandwich and a piece of fruit. People who treat this as permission to eat for two often overshoot by 500 to 800 calories, which leads to excessive gestational weight gain and complicate delivery later. In month six, your uterus is pushing upward against your stomach and intestines. Small meals aren't just a nausea strategy anymore — they're a mechanical necessity. A normal-sized meal will feel enormous and cause significant reflux or discomfort. This is also the month many providers schedule the glucose tolerance test for gestational diabetes screening. If your results come back borderline, don't panic, but take it seriously. Gestational diabetes affects about 6 to 10 percent of pregnancies and is largely managed through diet alone in the majority of cases. Cutting back on refined carbohydrates and spreading carbohydrate intake evenly across meals makes a measurable difference for most people.
Month seven is when calcium and vitamin D demands peak because the baby is depositing roughly 250 milligrams of calcium per day into its skeleton. That's a lot. Dairy, fortified plant milks, leafy greens, sardines with bones — you need sources throughout the day, not just at dinner. One large serving won't cover it. Your body can only absorb so much at once, and whatever isn't absorbed just passes through. Splitting your calcium intake across three meals is more effective than loading it at one sitting. Month eight brings a new set of challenges. Your stomach capacity is now severely compressed. Some people can't finish a full sandwich anymore. You're also at higher risk for varicose veins and swelling, and sodium awareness becomes relevant — not extreme restriction, but avoiding the heavily processed convenience foods that push sodium way past what your kidneys are comfortable handling this late. Omega-3s, particularly DHA, remain critical for the final stretch of brain development. Fatty fish like salmon are a good option, but stick to two servings per week maximum due to mercury concerns. One serving of low-mercury fish gives you roughly 200 to 300 milligrams of DHA, which is in the target range most OBs recommend. Month nine is where logistics matter more than nutrition theory. You're going to be uncomfortable, exhausted, and possibly unable to cook much of anything. Meal prep during month seven or early eight is genuinely useful here. Freeze portions of soups, stews, grain bowls, and protein-rich snacks. When you're nine months along and someone asks if you want to chop vegetables, the answer should be no. Pre-made food that meets your nutritional targets is infinitely better than skipping meals because cooking felt impossible.
Get the Full Details

The Parts Nobody Talks About
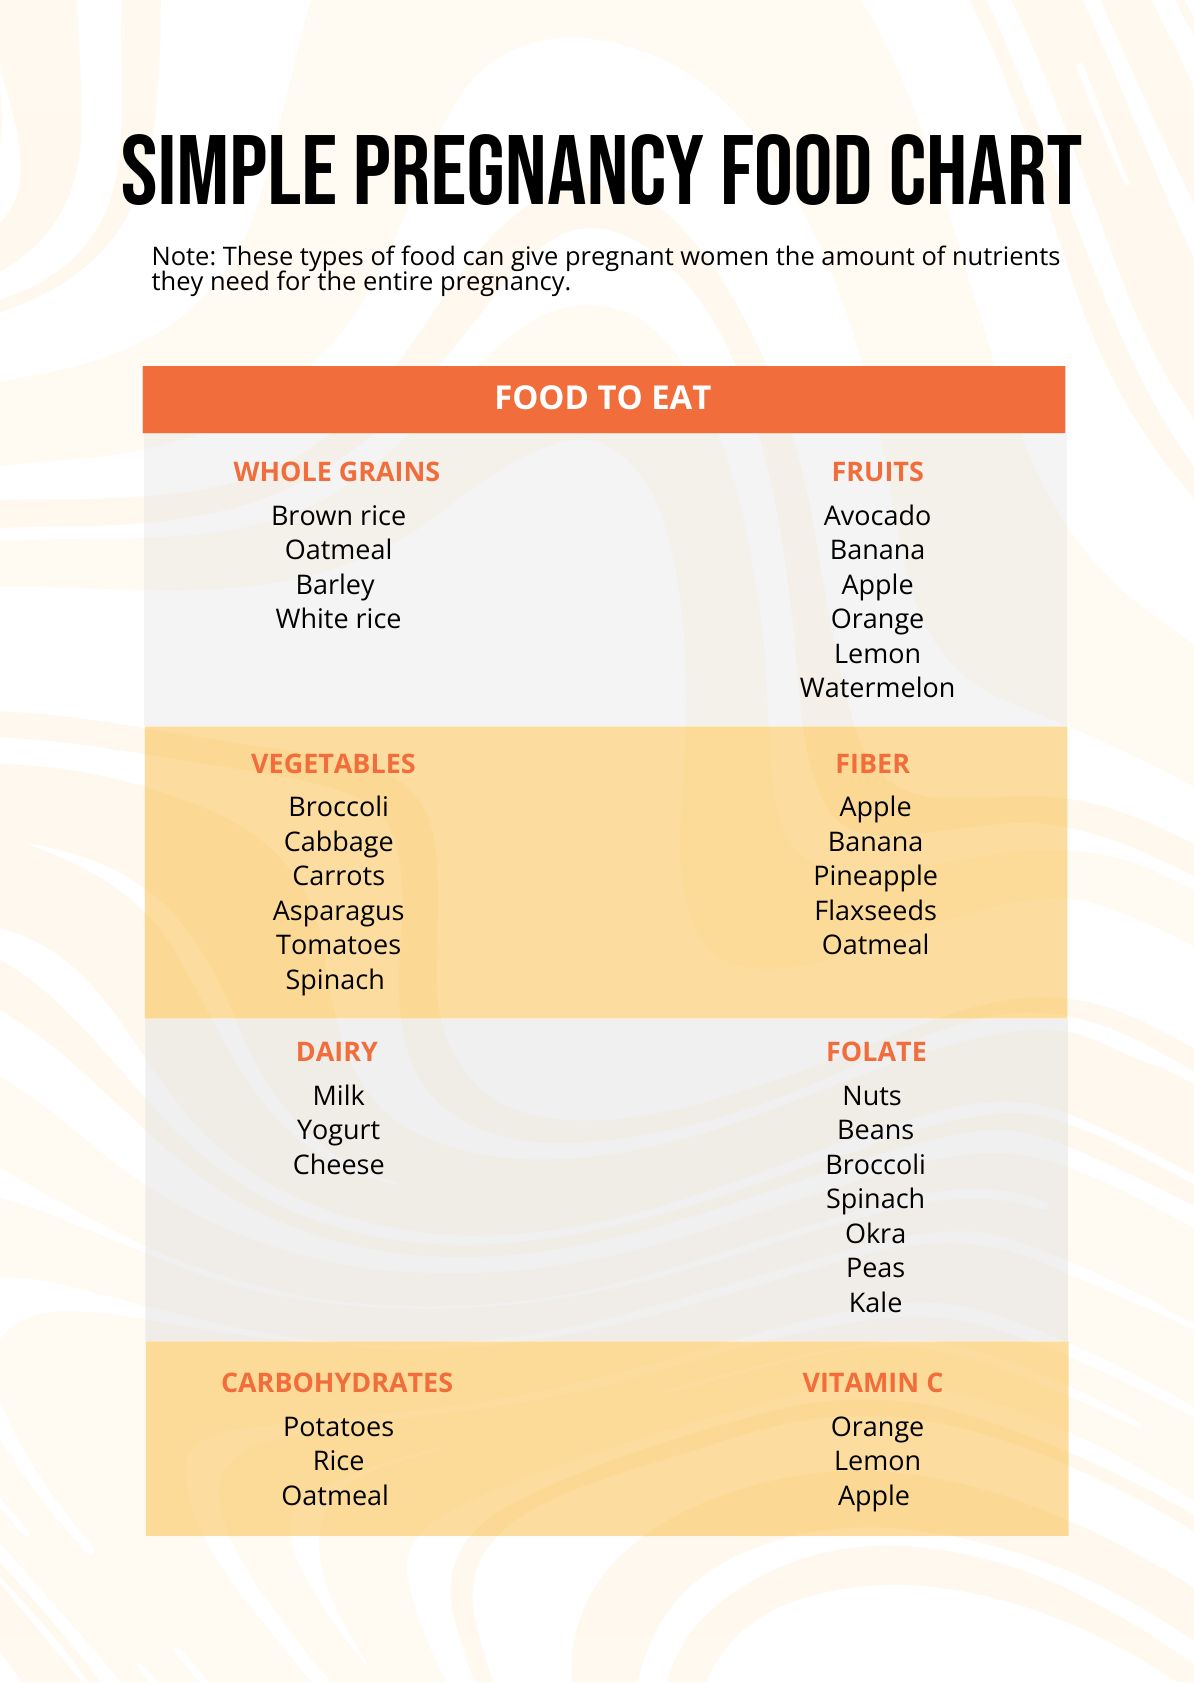
Craving and aversion are real physiological responses, not personality quirks. They're driven by hormonal shifts that affect your olfactory and taste processing centers. If you suddenly can't stand the taste of chicken, it's not willpower failure to switch to fish or beans. Your body may genuinely be signaling a nutrient need, or it may just be overwhelmed by a hormone-driven sensitivity. Either way, substitution is fine. The goal is adequate nutrition, not sticking rigidly to a food you've decided you hate. Another thing that trips people up is the assumption that prenatal vitamin brands are interchangeable. They're not. The form of iron matters — ferrous sulfate causes constipation for a large percentage of people, while ferrous bisglycinate is gentler on the gut but sometimes harder to find. The DHA source matters too. Fish oil versus algae-based DHA can affect both tolerability and mercury exposure risk. If your current prenatal is making you sick or isn't covering your labs, talk to your provider about switching. There are decent alternatives, but don't assume every green bottle is the same. Hydration gets less attention than it deserves, especially in the third trimester. Dehydration can trigger Braxton Hicks contractions that mimic real labor, and it worsens constipation, headaches, and fatigue. Aim for roughly 8 to 12 cups of fluid daily, more if you're active or living in a hot climate. Water is fine. Electrolyte solutions help if you're struggling to keep fluids down. Herbal teas count toward your total unless your provider has flagged a specific herb as unsafe.
Where This Approach Breaks Down
The month-by-month framework doesn't work well for people with pre-existing conditions like type 1 diabetes, celiac disease, or severe hyperemesis gravidarum. Hyperemesis affects roughly 1 to 3 percent of pregnancies, and those patients often can't follow any standard dietary pattern because they're vomiting persistently enough to cause dehydration and weight loss. They need medical intervention — IV fluids, antiemetics, sometimes feeding tubes — not dietary adjustments. If you're in that category, this guide is irrelevant to your situation and you should be under specialist care. The framework also assumes a singleton pregnancy. Twins and triplets change caloric and nutrient requirements substantially. A twin pregnancy typically needs an additional 600 calories per day starting in the second trimester, plus significantly more iron and protein. The monthly structure still applies, but the numbers shift considerably. Finally, cultural and socioeconomic factors matter enormously. This advice assumes you have access to fresh produce, variety in your grocery options, and the time and equipment to prepare meals. If your food environment limits what's available or affordable, focus on the nutrients rather than the specific foods. Frozen vegetables have the same nutrition as fresh. Canned beans are cheap and iron-rich. Beans and rice together provide complete protein. The principle is what carries across situations, not the particular ingredients listed in any given example.