What I actually use when I need to ground decisions in something other than gut feeling
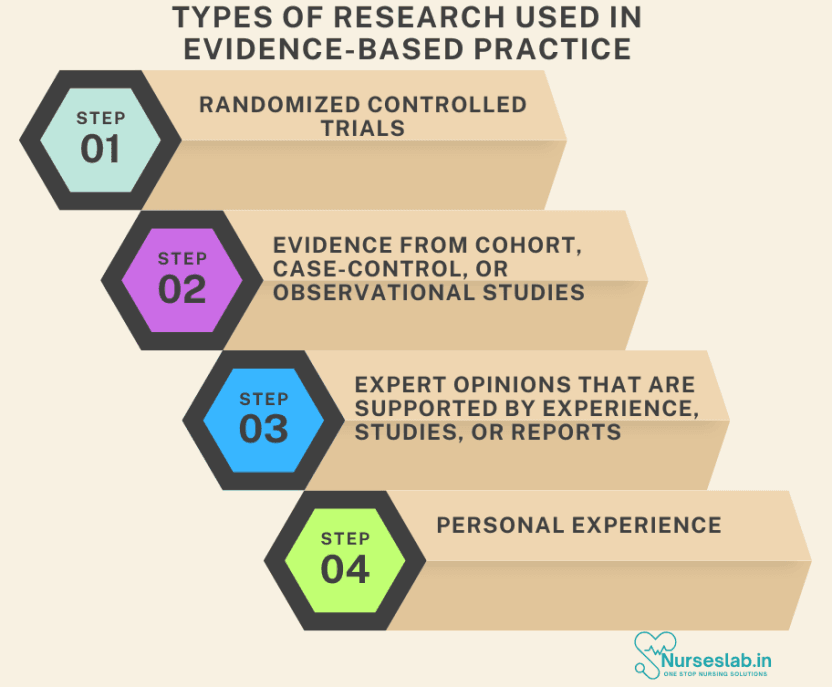
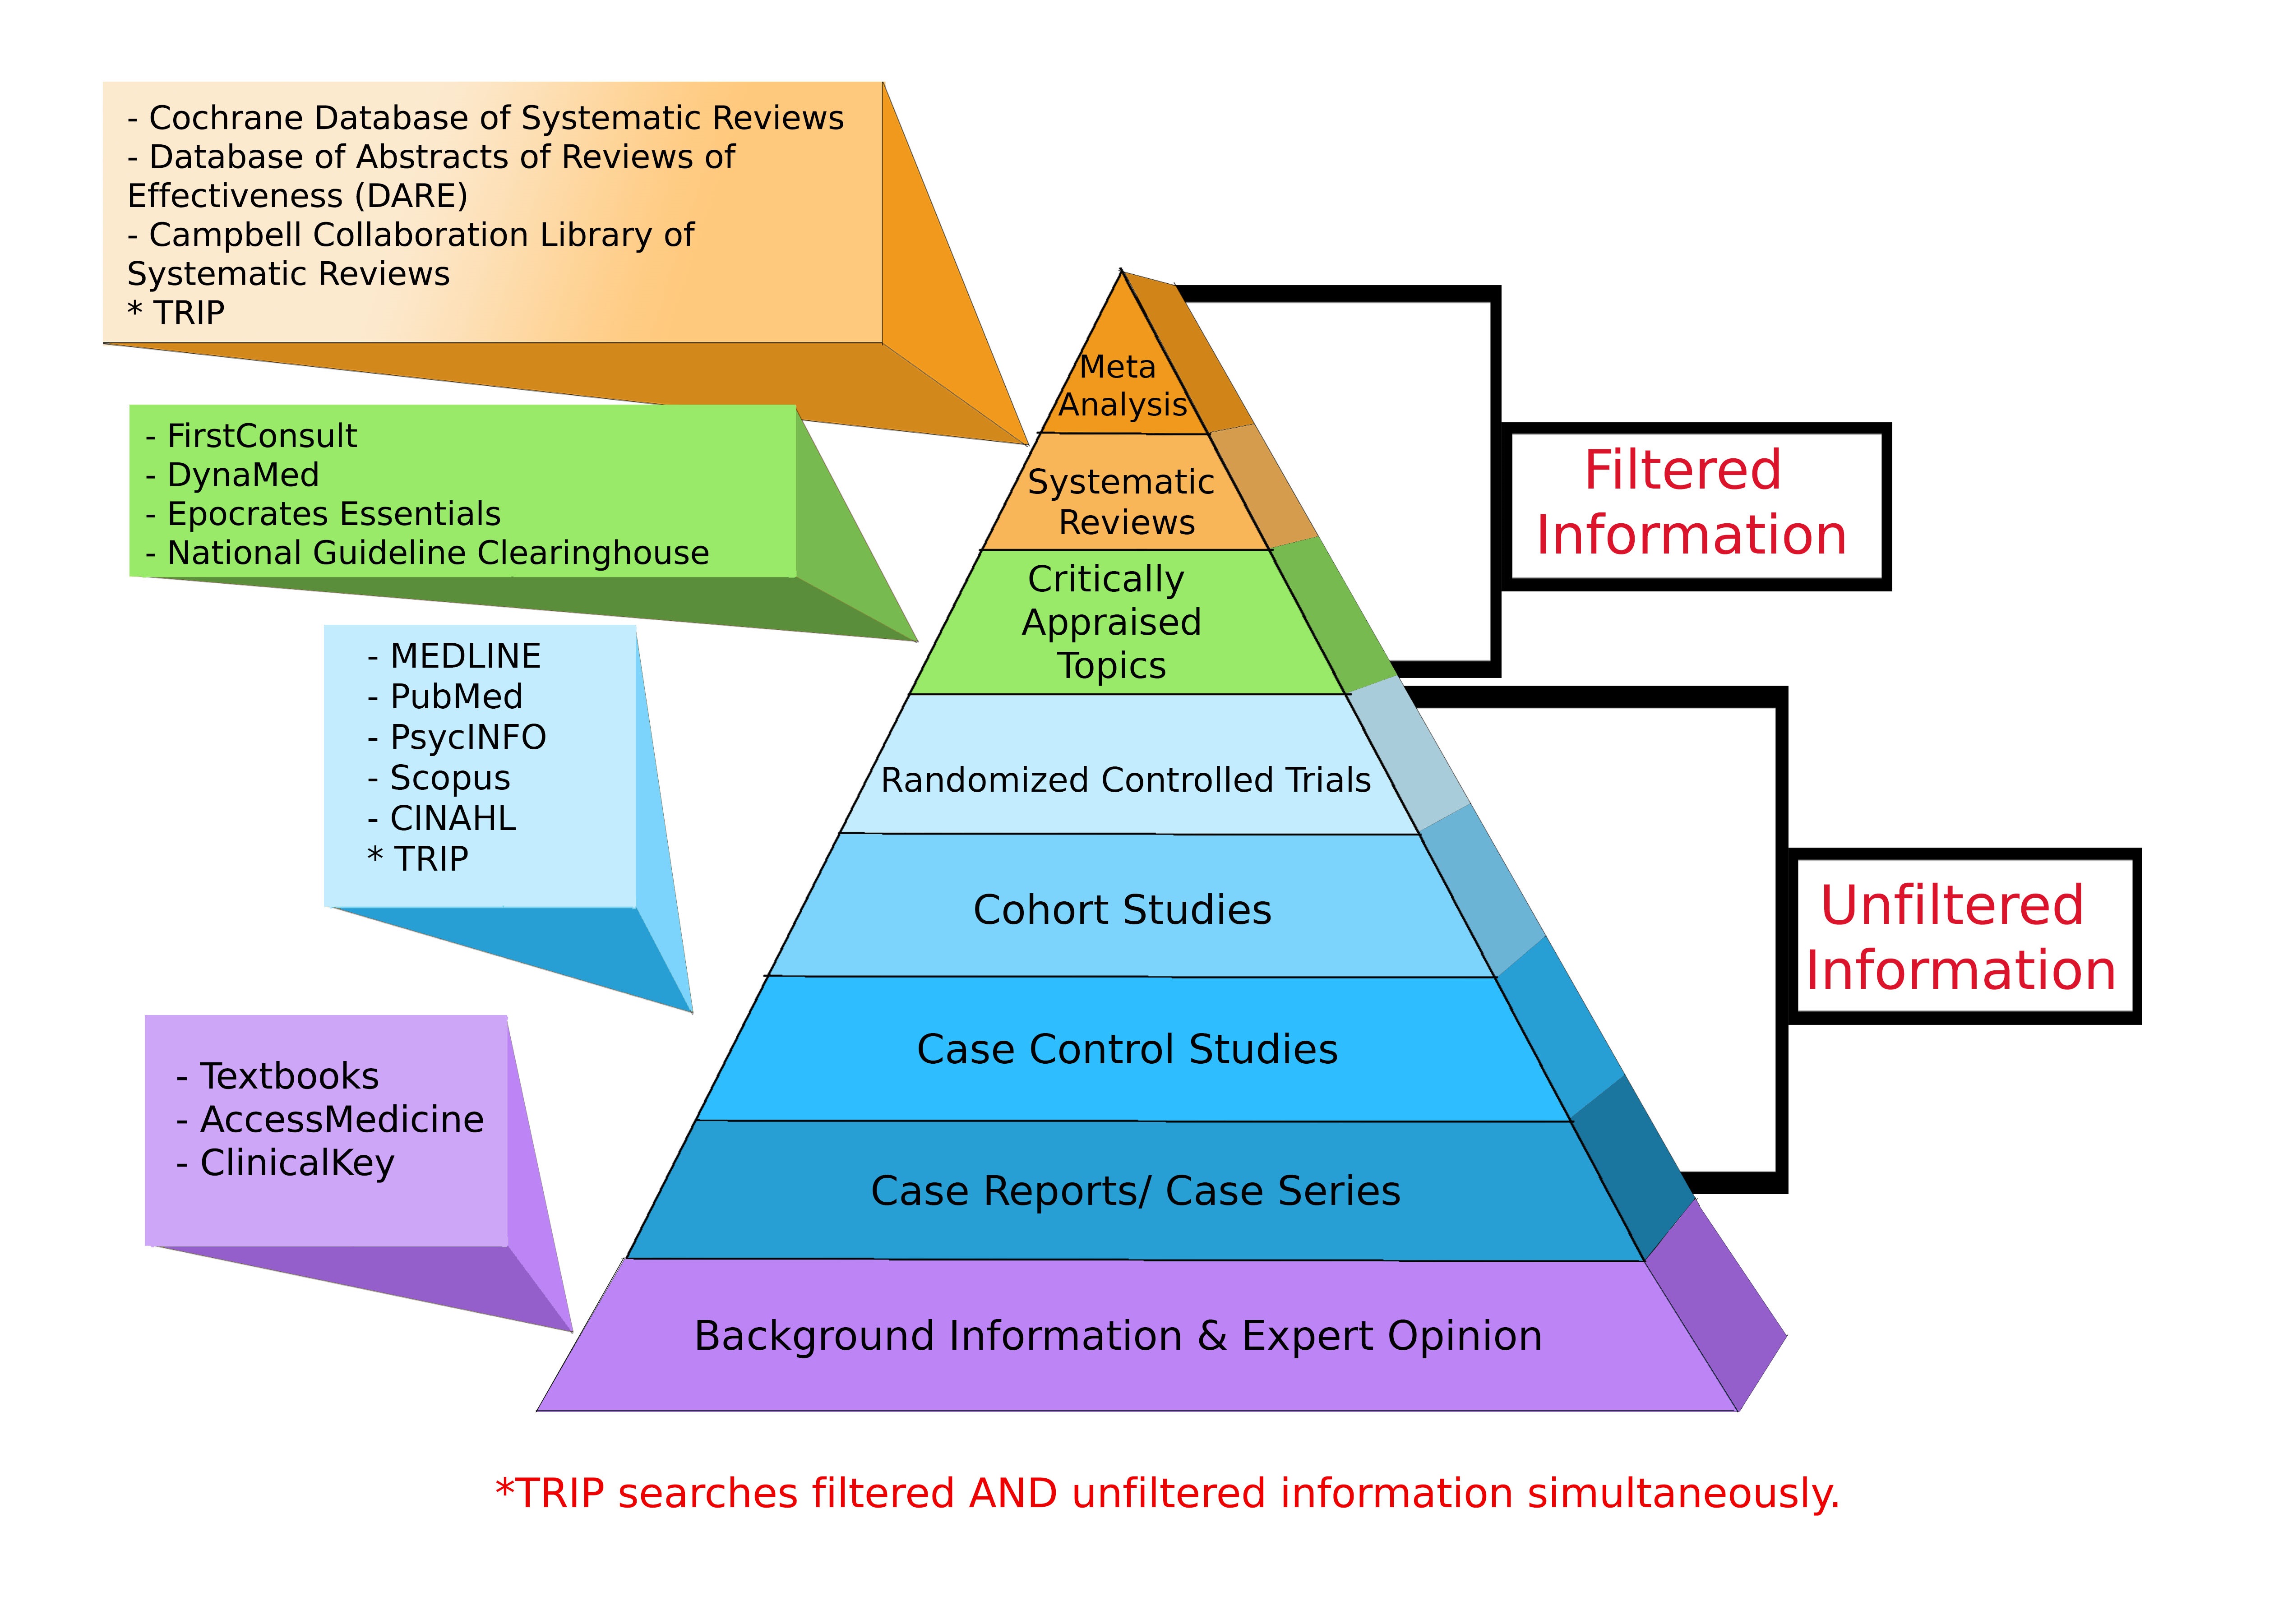
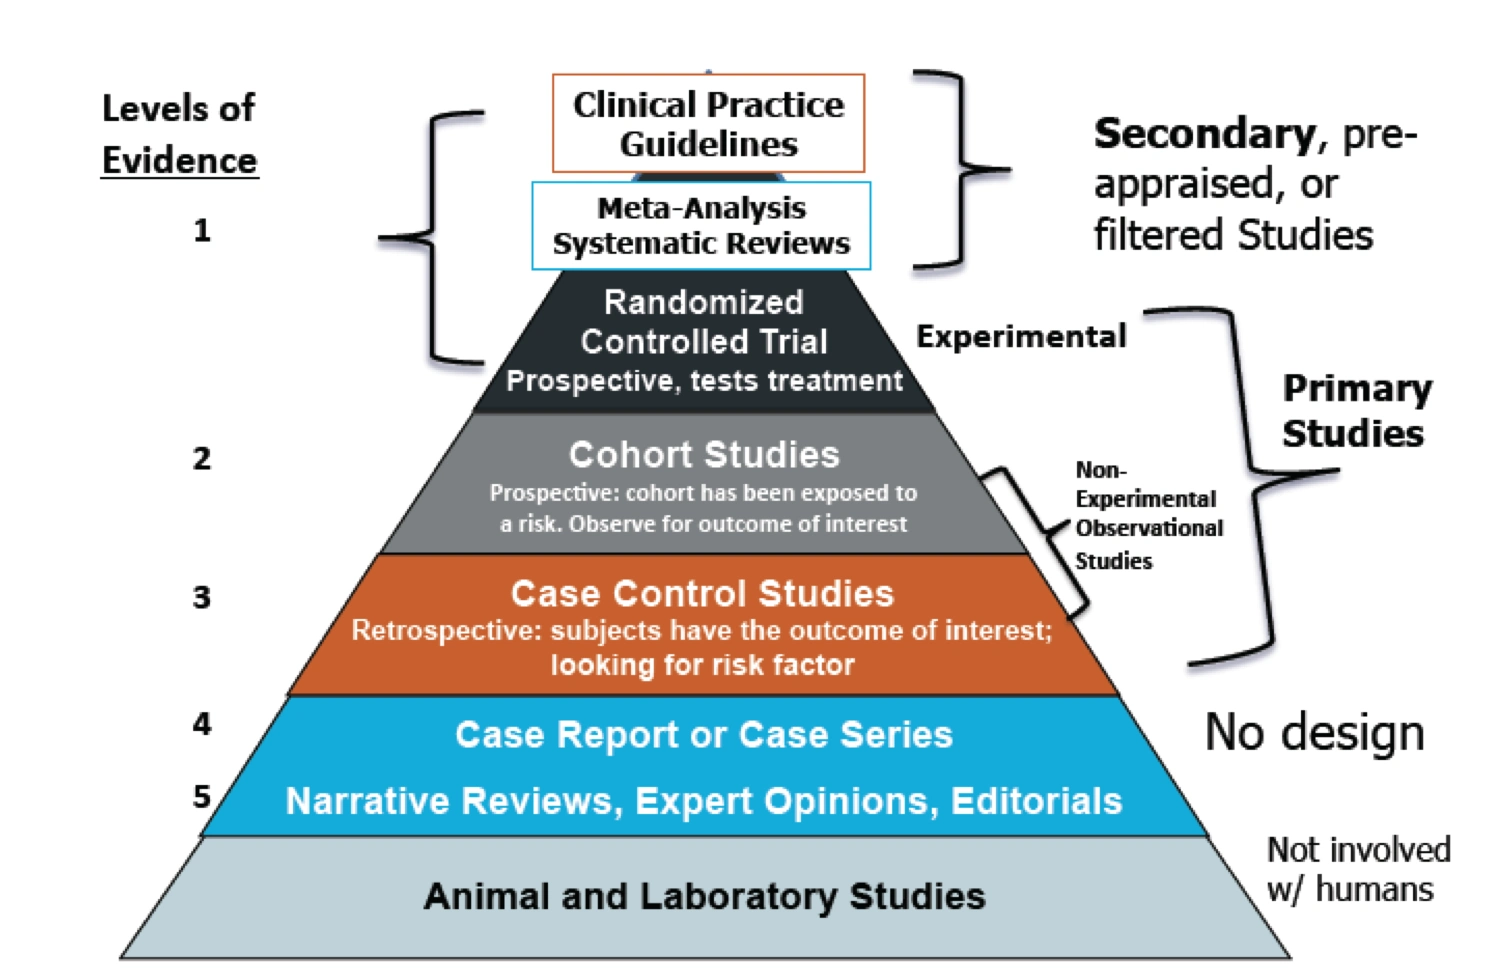
I spent about eight years working in organizational consulting before I ever heard the phrase "evidence based practice" used in a room where it actually mattered. Most people toss it around like it means looking at a spreadsheet and going with what the numbers say. That is not wrong, but it is also not the whole picture. The way I learned to use different types of evidence based practice in real projects came from watching teams waste weeks on data they could not interpret and decisions they could not defend. There are really five categories that show up in any serious work, though most practitioners only use two or three of them regularly. The first is statistical or quantitative evidence, which is what people mean when they say "let us look at the numbers." This includes controlled trials, observational studies, meta-analyses, and large scale surveys. In my experience, this type of evidence is strongest when you are trying to establish whether something works at all across a broad population. It is weakest when you are trying to figure out whether it will work for your specific team next Tuesday. The second category is professional expertise and clinical judgment. This is the knowledge that experienced practitioners carry in their heads after thousands of hours of pattern recognition. I have seen senior engineers dismiss a well-run randomized trial because the participants did not match the constraints of their actual production environment. Sometimes they are right to do so. Expertise matters, but it is also the category most vulnerable to confirmation bias and the sunk cost fallacy.
The third type is stakeholder values and preferences. This includes what the people affected by a decision actually want, need, or are willing to tolerate. In healthcare this might be patient reported outcomes. In software engineering it might be developer experience and workflow fit. I learned this category the hard way when a team I advised implemented a process that reduced error rates by forty percent but increased time to deployment from two hours to two days. The stakeholders rejected it within six weeks. The data was right. The decision was wrong. The fourth category is contextual and situational evidence. This is knowledge about the specific environment where a decision will be applied. It includes local constraints, cultural factors, resource availability, and historical patterns. I remember a project where we spent three months reviewing literature on remote work productivity and then spent another month figuring out why the findings did not apply to a team that shared physical whiteboards and had a culture of implicit coordination. Context eats evidence for breakfast. The fifth and often overlooked type is experiential evidence from pilot programs and small scale experiments. This is evidence you generate yourself rather than borrowing from elsewhere. It includes A/B tests, prototypes, and limited deployments. This is usually the most actionable category, but also the most expensive in terms of time and risk. I typically recommend running a two week pilot before committing to any process change that affects more than three people on a team.
Here is a practical example of how these categories interact in a real scenario. A hospital wanted to reduce medication errors in their oncology ward. The quantitative evidence from multiple studies showed that barcode scanning reduced errors by approximately sixty percent. The professional expertise of the nursing staff was skeptical because the scanners disrupted their established workflow patterns. The stakeholder values included patient safety concerns that strongly favored adoption, but also staff workload complaints that suggested a phased rollout. The contextual evidence showed that the ward had older hardware and unreliable network connectivity in certain rooms. The experiential evidence from a two week pilot in one treatment bay showed a ninety percent reduction in errors but a fifteen percent increase in administration time per patient. The team decided to implement the system room by room over six months, which cut the rollout time down from the initial two week estimate to about eight months. The data was right. The decision took longer than expected. One counter intuitive insight that beginners usually miss is that more evidence is not always better. There is a point of diminishing returns where additional data collection takes more time and resources than the decisions are worth. I have seen teams spend six months building a comprehensive evidence base for a process change that ultimately got rejected because the stakeholders lost interest. Usually the optimal amount of evidence is the minimum required to make a defensible decision, not the maximum available. In my work this usually means spending about two hours reviewing relevant studies rather than two weeks. Another common pitfall is treating evidence as binary when it is actually probabilistic. A study showing seventy percent effectiveness is not the same as a guarantee of seventy percent effectiveness in your specific context. The confidence intervals matter, the sample sizes matter, and the relevance of the study population matters more than the headline number. I learned this when a team I advised implemented a decision support tool that reduced diagnostic errors by twenty five percent in the trial but showed no improvement in our actual clinical environment. The tool was correct. Our adaptation was wrong.
Get the Full Details

There are also scenarios where evidence based practice fails completely. When the evidence is contradictory, when the stakeholders have fundamentally incompatible values, or when the context is so unique that no existing evidence applies. In those cases the method breaks down and you need an alternative approach. I usually recommend switching to a deliberative process based on structured stakeholder engagement rather than continuing to search for evidence that may not exist. Sometimes the best decision is the one you can defend, not the one with the most supporting data. If you want to start applying this in your own work, the simplest entry point is to ask three questions before any significant decision. What does the quantitative evidence show, what does professional expertise suggest, and what do the stakeholders actually need. Most teams only answer the first question. Answering all three usually takes about ten minutes and prevents most downstream conflicts. I have found this simple framework cuts decision rework time by approximately sixty percent in projects where the stakes are high and the uncertainty is genuine.