What Actually Helps When You Have a Herniated Disc
Most people get sent home from the ER with a printed sheet of five exercises they've never heard of and told to "try to be gentle." The instructions are usually wrong for their specific type of herniation, or they start doing them too aggressively and end up worse. I figured this out the hard way years ago after watching patients relapse because their PT handout didn't match their imaging findings. The reality is that Disc Herniation Physical Therapy Exercises need to be matched to direction of the herniation. A posterior-lateral herniation responding to extension-based work is completely different from an anterior or far-lateral disc issue. Get the direction wrong and you're grinding the nucleus further into the nerve root instead of away from it.
Directional Preference and the McKenzie Method
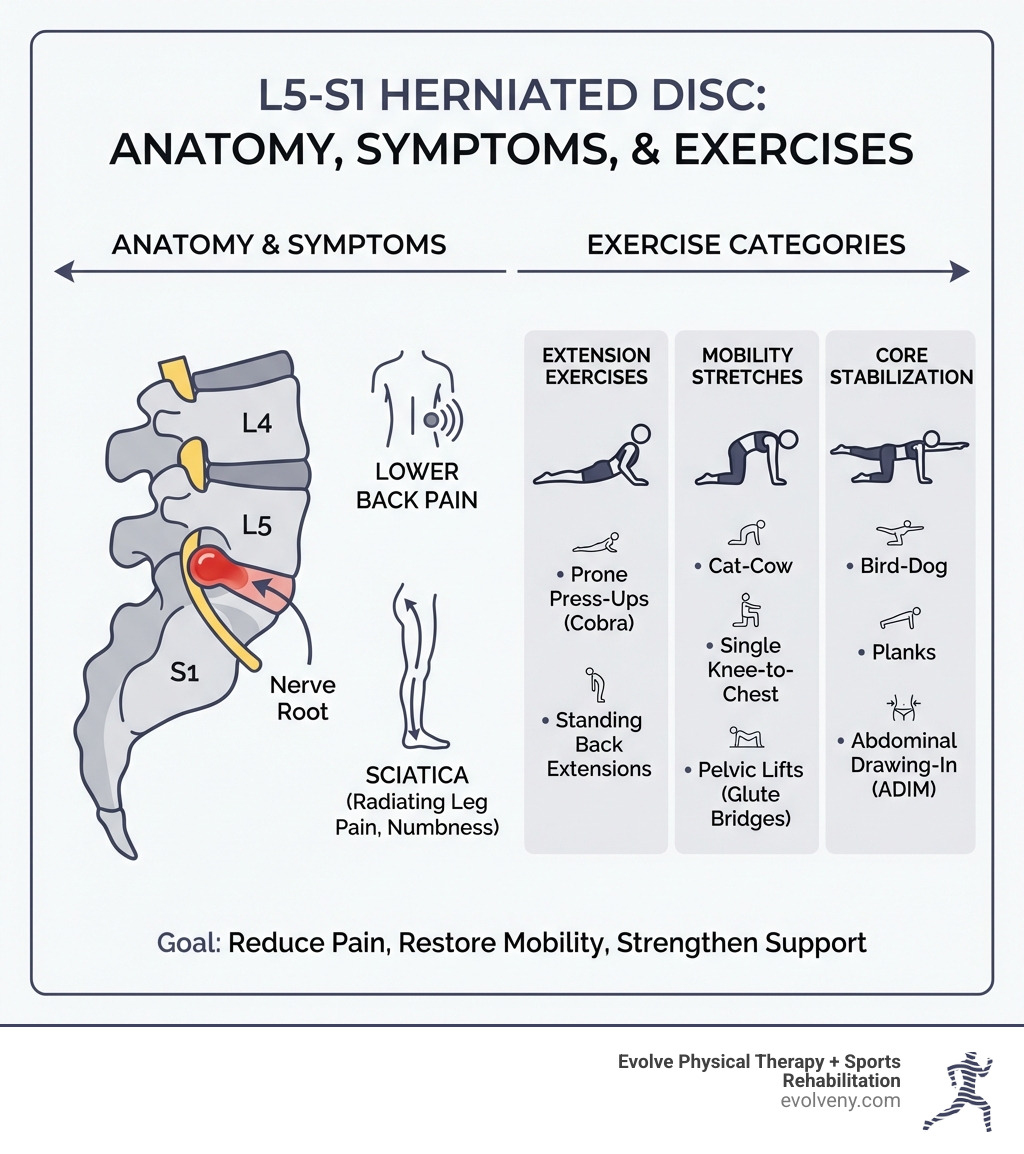
The first thing I check is directional preference. It sounds clinical but it's really just asking the patient to repeat movements in different directions and see which one centralizes the pain or reduces it. Extension bias is the most common finding with posterior disc herniations. A simple prone press-up where the patient lies on their stomach and gently pushes their upper body up with their hands while keeping the hips on the ground usually does the trick. Start with ten repetitions held for two seconds each. If symptoms centralize or improve within five minutes, that's your working direction. If leg pain travels further down the leg or worsens, stop immediately and try flexion bias instead, though that's much less common with standard posterior herniations. I had a patient once who clearly had an L5-S1 posterior herniation on MRI but every extension exercise made her symptoms worse. She actually had a contained extrusion that was sitting in the lateral recess, and the extension was compressing it further into the nerve. We switched to gentle flexion-based movements and a modified side-lying position with a pillow between the knees. Her pain resolved in three weeks instead of six. Always verify the response clinically, don't just assume the imaging tells the whole story.
Core Stabilization That Actually Works
After directional preference is established, the next phase is building endurance in the deep core musculature. Not the six-pack muscles. The transverse abdominis, multifidus, and pelvic floor. These are the muscles that act as a natural corset around the spine and reduce load on the disc itself. The dead bug exercise is a reliable starting point. Lie on your back with arms extended toward the ceiling and knees bent at ninety degrees in the air. Lower one arm behind your head and the opposite leg straight out while keeping your lower back pressed into the floor. Return to start and switch sides. Two sets of eight per side, three times per week minimum. If your lower back lifts off the floor at any point, the range of motion is too big. Shrink it until you can maintain contact. Bird dog comes next. On all fours, extend one arm forward and the opposite leg back while keeping the spine neutral. Hold for three seconds. Two sets of eight per side. The key is not to let the hips rotate or the lower back sag. Most people arch excessively on the return phase. Move slower.
Get the Full Details

Nerve Gliding for Radicular Symptoms
When the herniation is irritating the nerve root directly, you get radiating symptoms below the knee. Nerve gliding exercises can help reduce adhesions and improve mobility along the neural pathway. The seated sciatic nerve glide is the standard approach. Sit on a sturdy chair with your back straight. Slowly straighten one knee while simultaneously pointing your toes toward your face. You should feel a gentle stretch behind the thigh, not sharp pain. Return to the starting position. Ten repetitions per side, twice daily. The motion should be smooth and controlled, not bouncing. If you feel any increase in numbness or tingling, reduce the range of motion. A common mistake I see is patients pushing through sharp nerve pain during these exercises. That's not building tolerance. That's irritating the nerve further. The goal is mild tension, not discomfort. There's a narrow window between helpful and harmful here and most people don't feel it until they've already crossed it.
Hip and Glute Strength Matters More Than People Think
A weak gluteus medius forces the lumbar spine to compensate during walking and standing. That extra lateral bending and rotation stacks up over thousands of steps per day. Clamshells are an efficient way to address this. Lie on your side with knees bent at forty-five degrees. Keep your feet together and lift the top knee like a clam opening its shell. Pause at the top for one second. Lower slowly. Two sets of twelve per side. Bridges build gluteus maximus and hamstring strength while also engaging the core. Lie on your back with knees bent and feet flat on the floor. Lift your hips until your body forms a straight line from shoulders to knees. Hold for three seconds. Lower with control. Start with two sets of ten and work up to three sets of fifteen over four to six weeks. The side plank is another high-value exercise that most patients skip because it's uncomfortable. Modified version: kneel on one side and prop yourself up on your forearm and knee. Lift your hips until your body is straight from knees to head. Hold for twenty seconds. Progress to the full side plank on your foot when you can hold the modified version for forty-five seconds without sagging.
What These Exercises Don't Fix
Physical therapy won't shrink a sequestered disc fragment that has broken free from the annulus. It won't reverse significant spinal stenosis. It won't help if there's cauda equina syndrome, which presents with bowel or bladder dysfunction and saddle anesthesia and requires immediate surgical evaluation. Exercise is for contained herniations, protrusions, and mild extrusions where the outer layer of the disc is still intact enough to respond to mechanical loading strategies. Patients with large central herniations causing significant motor weakness, like foot drop, generally need surgical consultation rather than a twelve-week exercise program. I've seen cases where people pushed through weak dorsiflexion for months thinking it would resolve on its own. It rarely does. Motor weakness is a red flag that shouldn't be ignored. The timeline for improvement is also worth addressing honestly. Most patients see some reduction in radicular symptoms within two to four weeks of consistent exercise. Structural healing of the annulus fibrosus takes longer, usually eight to twelve weeks before the tissue is strong enough to tolerate normal activity without irritation. Returning to heavy lifting or high-impact sports before that window closes is the most common reason for recurrence.

Progression Criteria
Don't move to the next exercise until the current one can be performed without any increase in symptoms for three consecutive days. Adding load before the tissue adapts just resets the clock. A typical progression looks like this: directional preference work for one to two weeks, then introduction of core stabilization while continuing directional work, followed by nerve gliding if radicular symptoms persist, and finally hip and glute strengthening once daily activities no longer provoke symptoms. Some days will be worse regardless of what you do. Weather changes, prolonged sitting, or a bad night's sleep can all temporarily increase sensitivity. That doesn't mean the exercises are failing. It means the nervous system is in a heightened state and you should temporarily reduce intensity rather than stop entirely. Gentle movement usually helps more than complete rest at that point. The exercises outlined above represent the core of what effective Disc Herniation Physical Therapy Exercises look like in practice. They're not exhaustive and they're not a substitute for personalized guidance from a licensed physical therapist who can evaluate your specific imaging and symptoms. But they're a solid foundation that covers the majority of cases patients present with in a clinic setting.



