The Reality of Wrist Fracture Rehab
I see this question come up constantly on orthopedic forums, usually from people who are either dreading their first PT session or trying to figure out if they can skip it altogether. The answer depends on what kind of fracture you had, how it was treated, and what your goals are. A hairline crack that healed in a cast by week four is a different animal from a comminuted intra-articular fracture that required plate and screw fixation. Most people don't realize that the bone being healed is only one part of the equation. The surrounding soft tissue—ligaments, tendons, joint capsule, scar tissue—goes through changes that are just as clinically significant. When a wrist is immobilized for six to eight weeks, the joint capsule contracts. This isn't speculation; it's documented in the literature. Studies show measurable shortening of the volar and dorsal capsules, with dorsal capsule shortening correlating directly to loss of extension. The ligaments surrounding the carpal bones lose elasticity. Tendons glide less freely because the surrounding paratenon develops adhesive scar tissue. These are mechanical problems that stretching and controlled movement can address. Bone healing cannot be accelerated by physical therapy, but restoring range of motion absolutely can be delayed if you skip it.
Do You Need Physical Therapy After Broken Wrist
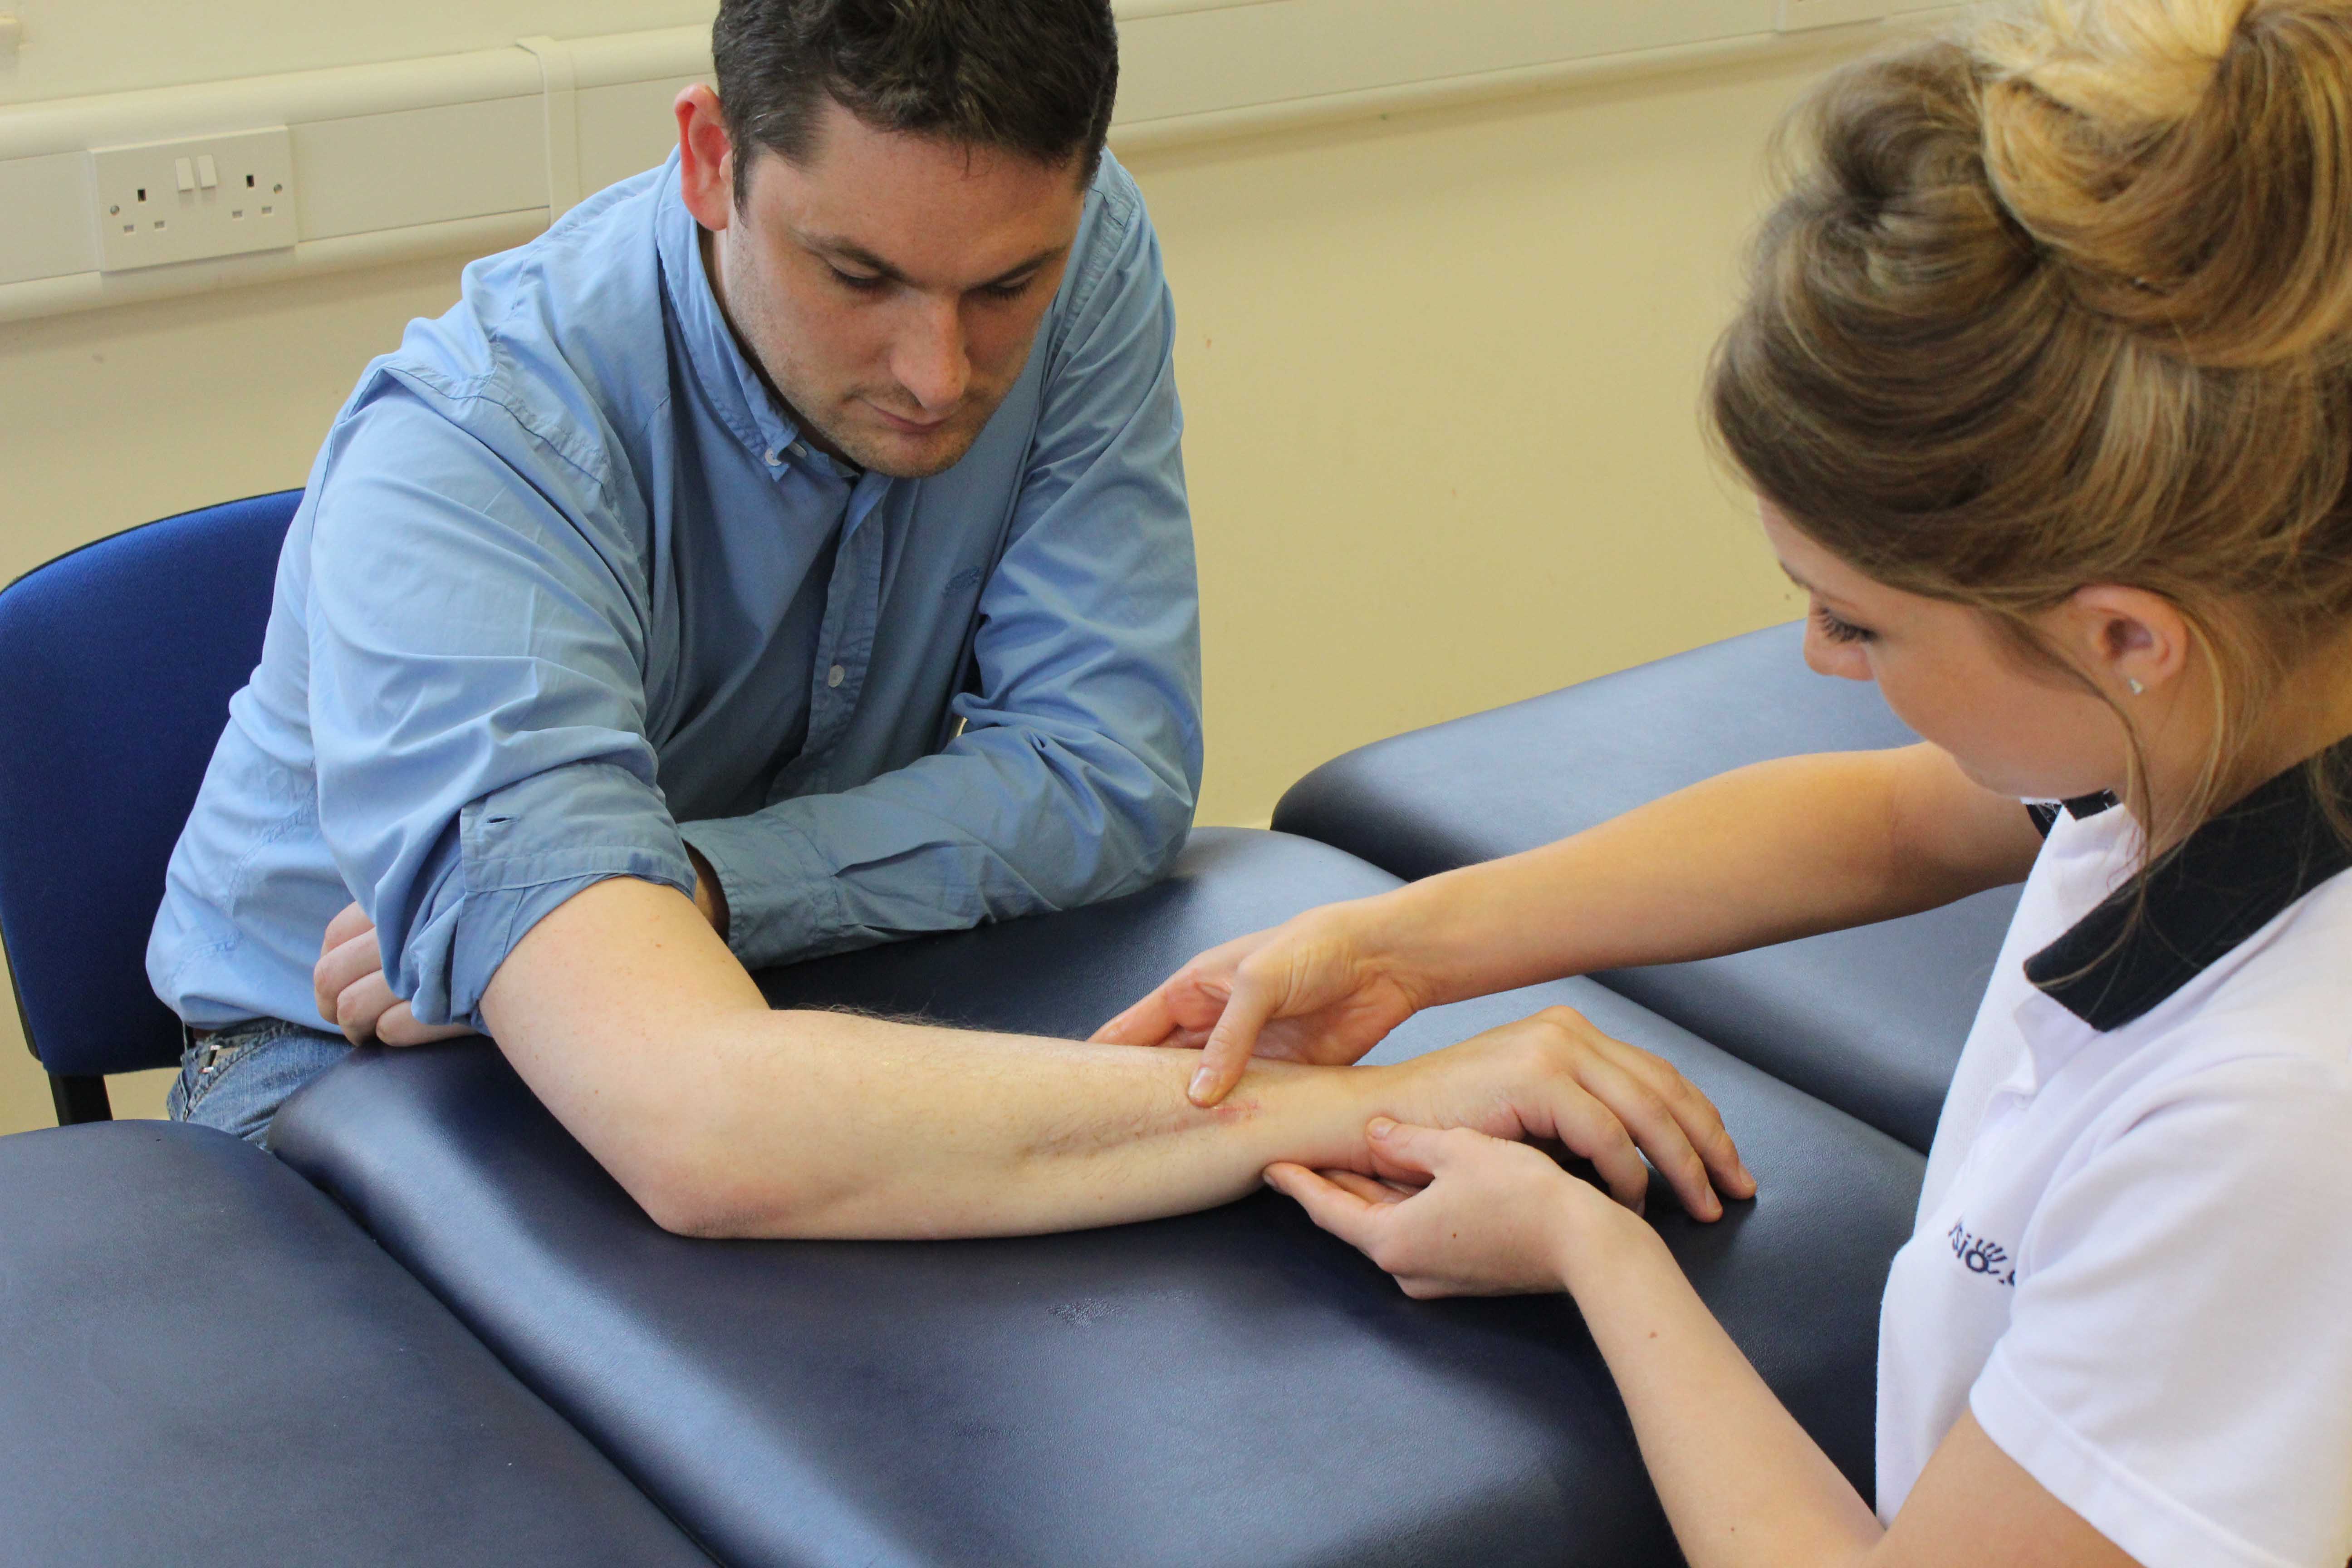
Here's the thing most people don't understand about wrist fracture rehab: the timing and type of intervention matters more than the total number of sessions. Early controlled motion—starting within the first two to three weeks post-injury or post-surgery depending on fixation stability—produces measurably better outcomes than waiting until the cast comes off and then aggressively mobilizing a stiff joint. Once adhesions mature past the eight-week mark, they become significantly more resistant to manual therapy approaches. I've seen patients who waited too long end up with permanent extension deficits in the 15 to 20 degree range despite doing their home exercises faithfully. That's not because they didn't try hard enough. It's because the window for favorable tissue remodeling had already closed. There's a common misconception that more intense stretching during rehab equals faster recovery. It doesn't. Aggressive passive stretching into restricted end-range motions often triggers a protective spasm response that actually worsens the stiffness over subsequent days. The tissue responds to trauma with more scar formation. The approach that works is gentle, sustained, low-load prolonged stretching held for 30 to 60 seconds, repeated several times daily, without forcing through sharp pain. Discomfort is expected. Sharp, biting pain is a signal to back off. I had a patient last year—a construction worker, roughly 40 years old—who'd suffered a distal radius fracture with intra-articular involvement. He'd been in a cast for five weeks, then told he didn't need formal PT because his X-rays looked fine. He came to me with 40 degrees of flexion, 30 degrees of extension, and almost no forearm rotation. Three months post-injury. We started with myofascial release techniques on the flexor and extensor compartments, combined with neurodynamic gliding for the median and radial nerves, which had clearly become adhered to surrounding structures. The nerve component was something his original surgeon hadn't addressed at all. It took about twelve sessions over ten weeks to get him back to functional use. Not full athletic range, but enough to grip a hammer and turn a screwdriver without significant pain or fatigue. He was ahead of where he would have been if he'd just tried to force the stiffness out on his own.
The type of fracture plays a huge role in whether PT is necessary and how intensive it needs to be. Extra-articular fractures with stable fixation generally respond well to structured home exercise programs. Intra-articular fractures, especially those with joint surface disruption, carry higher risk of post-traumatic arthritis and complex regional pain syndrome. These cases benefit significantly from supervised therapy because the therapist can monitor for signs of CRPS—disproportionate pain, color changes, temperature asymmetry, excessive swelling—and adjust the protocol accordingly. Left unmonitored, these complications can become chronic within weeks of onset.
Get the Full Details

What to Expect If You Start Therapy
A typical initial evaluation takes about 45 minutes and includes goniometric measurements of active and passive range of motion in all planes, grip and pinch strength testing with a dynamometer, assessment of edema and tissue quality, neurological screening, and evaluation of adjacent joints—the elbow, shoulder, and fingers often compensate for wrist dysfunction in ways that create secondary problems. Your therapist will then establish baseline measurements and create a home exercise program tailored to your specific deficits. Session frequency usually ranges from one to three times per week for the first four to six weeks, tapering as progress is made. Home exercises are where most people cut corners. They'll do the prescribed wrist flexion and extension stretches but skip the forearm pronation and supination work, or neglect the intrinsic hand muscle exercises. These are all interconnected. The forearm rotators don't function independently from wrist stabilizers. Skipping components of the program creates compensatory movement patterns that reinforce stiffness in unexpected directions. I once measured a patient who had restored 80 percent of her wrist flexion and extension but had barely improved her supination—from 45 degrees to 55 degrees over eight weeks. She'd been doing her exercises religiously but had consistently avoided the rotation movements because they felt uncomfortable. That limited supination deficit meant she couldn't use her dominant hand effectively for tasks like turning a doorknob or using a screwdriver. It was a self-inflicted limitation born from avoidance behavior. Return to work timelines vary considerably. Desk workers with simple extra-articular fractures may be functional enough to return modified duties within four to six weeks. Manual laborers typically need twelve to sixteen weeks minimum, and sometimes longer if grip strength hasn't recovered to at least 70 to 80 percent of the uninjured side. There's no reliable shortcut here. Grip strength recovery follows a fairly predictable curve, and pushing through it prematurely risks re-injury or chronic weakness. I've seen people return to heavy labor at eight weeks because they felt good, then flare up dramatically at twelve weeks when the cumulative load became too much for tissues that weren't actually ready.
When PT May Not Be Enough
Physical therapy has clear limitations. It cannot reverse established joint surface irregularities from an intra-articular fracture. If the articular surface was displaced more than two millimeters and reduced surgically, the residual incongruity remains. Therapy can improve function around that limitation, but it won't make the joint perfectly smooth. Post-traumatic osteoarthritis is a real possibility, and no amount of stretching or strengthening will prevent it entirely. Similarly, severe scar tissue contractsure that has matured beyond the six-month mark often requires surgical intervention—capsular release or tenolysis—to restore meaningful motion. PT alone cannot break down dense, organized collagen adhesions that have been present for many months. Attempting to do so through increasingly aggressive stretching only causes more inflammation and more scar tissue. It's a counterproductive cycle. Another scenario where PT has limited utility is when neurological involvement was missed. If there's nerve entrapment or significant nerve damage from the initial fracture, symptoms like persistent numbness, tingling, or weakness that doesn't improve with standard rehab warrant referral back to the orthopedic surgeon or to a neurologist. Wrist fracture rehab protocols assume intact neural function. When that assumption is violated, the timeline and approach change entirely. I worked with a patient whose median nerve symptoms were attributed to "normal post-fracture swelling" for three months. They weren't. He had a significant nerve compression that required surgical decompression. By the time it was addressed, he had developed some permanent thenar weakness. Earlier recognition would have prevented that outcome. The bottom line is that physical therapy after a broken wrist is genuinely beneficial for most patients, but it's not universally required and it's not a magic solution. The decision should be based on your specific fracture pattern, treatment approach, functional demands, and how your healing is progressing. If you're uncertain, getting an evaluation from a hand therapist—someone certified in upper extremity rehabilitation specifically, not just a general physical therapist—will give you a clearer picture of what you need and what you can realistically expect. Most insurance plans cover initial evaluations without a referral in many states, so there's little downside to getting a professional opinion before committing to or abandoning a rehab plan.