Getting past the surface-level diagrams
Most resources on dog internal organs anatomy stop at a color-coded illustration from a vet tech textbook. They show you where things sit and give you Latin names. That is useful for a class, but it does not help when you are actually trying to understand what you are looking at on an ultrasound, a CT scan, or behind the ribcage during an emergency procedure. I spent years trying to map these structures in my head before the cadaver work actually stuck. Here is what actually matters. The problem with studying this topic is that standard anatomical positions assume the dog is standing on all fours. In practice, you are rarely dealing with a dog in sternal recumbency for a long diagnostic. They are on their side for imaging, they are sitting up in the exam room, or they are critically ill and moving constantly. The organs shift. I learned this the hard way during a routine abdominal x-ray on a senior golden retriever. The spleen was positioned abnormally low on the image, and for a moment I thought it was a mass. It turned out the dog had just been rotated slightly during positioning, which dragged the splenic tip caudally enough to mimic a different pathology entirely. The workaround was simple—take a second view with the dog properly aligned. But that moment taught me that spatial awareness matters more than memorizing static positions. Let us start with what you need to actually know rather than what a textbook says you should know.
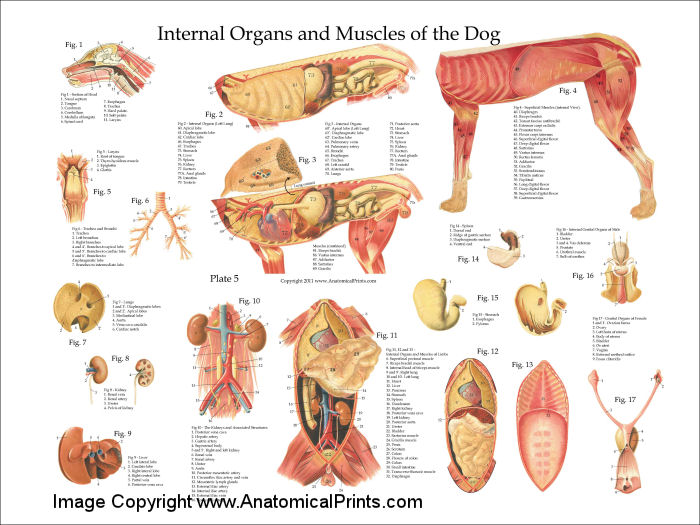
The cardiovascular system is straightforward until it is not. The heart sits in the cranial thorax, roughly between the third and sixth ribs. Four chambers. Four valves. When you are looking at radiographs, the heart should occupy less than 3 vertebrae widths on aVD view. That is the VHS score, and it is still the most practical measurement we have for cardiac enlargement. Here is something most people miss: the left atrium enlarges first in mitral valve disease, but you will not reliably see it on a two-dimensional x-ray until the right side of the heart is already involved. An echocardiogram catches this weeks earlier. The respiratory system has four lobes on the right and three on the left, which is different from humans and worth remembering because it matters for lobectomy planning. If a dog has a tumor confined to one lobe, knowing which lobes are connected by shared fissures determines whether you can remove just that section or if you need to take more. The right lung has cranial, middle, caudal, and accessory lobes. The left has cranial, caudal, and accessory. The cranial lobes of both lungs share a common bronchus, so infection in one often spreads to the other. I saw this repeatedly in aspiration pneumonia cases. The gastrointestinal tract is where most of the confusion happens for beginners. The stomach is J-shaped and sits on the right side of the abdomen in most dogs, not the left. The liver has six lobes with a gallbladder tucked into the bed of the right medial lobe. The pancreas has two parts—one near the duodenal loop and one near the splenic flexure of the colon. These parts drain into different duct systems, which matters because pancreatitis can spread along either tract independently. I once had a case where a dog had mild pancreatitis in the duodenal portion but severe inflammation around the splenic part. The clinical signs pointed to the wrong area initially because the duodenal inflammation was quieter. Ultrasound guided the real diagnosis.
The urinary system involves kidneys, ureters, bladder, and urethra. Dog kidneys are more mobile than human kidneys, which is why you can sometimes palpate them in thin animals. The right kidney sits slightly more caudal than the left. When you are performing a cystoscopy or placing a urinary catheter, knowing this asymmetry prevents complications. The prostate in males is paired and sits at the bladder neck. It is easy to mistake normal prostatic tissue for enlargement on a rough physical exam. A proper digital exam and ultrasound measurement of each lobe separately is the only reliable way to assess it.
Get the Full Details

Common pitfalls and what they look like in practice
One of the biggest mistakes I see people make is assuming symmetry. Organs are not perfectly symmetrical, and variations are normal. A dog with a large stomach filled with food and water will have its liver pushed caudally. A dehydrated dog will have kidneys that sit deeper in the abdomen and are harder to visualize on ultrasound. These are not pathologies. They are positioning and hydration effects that change how everything looks. Another issue is the assumption that textbook diagrams reflect average cases. They do not. Brachycephalic breeds, deep-chested breeds, and toy breeds all have different organ arrangements relative to body size. A greyhound's liver will appear more elongated compared to a bulldog's compact version, even if both are completely normal. When you are reading images, always account for conformation before you call something abnormal. Body condition score affects every system. An obese dog has more abdominal fat that obscures organ detail on ultrasound. You might miss a small splenic nodule or early renal changes simply because the acoustic window is poor. In those cases, switching to computed tomography or waiting until the animal loses weight before re-imaging is the practical approach. There is no substitute for good image quality, and obesity is one of the most common reasons images come back uninterpretable.
How to actually study this effectively
Reading descriptions is not enough. You need to correlate three things simultaneously: cadaver dissection, live animal imaging, and clinical cases. I used a combination of veterinary anatomy atlases with cross-sectional images and actual ultrasound machines in the clinic. The atlases gave me the baseline anatomy, the ultrasound machine showed me how it appeared in living patients, and the clinical cases grounded everything in real consequences. Without all three, your knowledge stays theoretical. If you are trying to memorize organ positions, draw them from memory first, then check against references. The act of drawing forces you to resolve uncertainties you would otherwise gloss over. I found that every time I drew the pancreas from memory, I got the relationship to the duodenum wrong until I looked it up and corrected it. That correction stuck. Flashcards and quizzes work for names. Drawing and explaining out loud works for understanding relationships between structures.
Tools and resources that actually help
There are several veterinary anatomy reference sources available online. Complete Anatomy, the Merck Veterinary Manual, and the VT Image database at Colorado State University provide high-quality cross-sectional and radiographic examples. For ultrasound specifically, the Veterinary Ultrasound Image Library at UC Davis has free cases organized by organ system. These are not flashy tools, but they are accurate and regularly updated by practicing clinicians. Avoid sources that rely solely on illustrated diagrams without correlating images from real patients. Diagrams are fine for initial learning, but they create a false sense of familiarity that falls apart when you encounter actual clinical material. Knowing where organs sit will not tell you what is wrong with them. A liver that looks normal in position can be cirrhotic. A kidney that sits in the right place can have early chronic changes that are only visible on biopsy or advanced imaging. Anatomy is the foundation, not the diagnosis. I have seen too many people confuse anatomical normality with physiological normality. Just because you can identify every structure does not mean you can assess its function. Imaging, bloodwork, and biopsy are necessary complements. If you rely on anatomy alone, you will miss functional disease until it is advanced. The same applies to surgical planning. Knowing organ positions helps you avoid collateral damage, but it does not replace preoperative imaging. A tumor that is not obvious on palpation can be completely different when you see it on cross-sectional imaging. I once planned a splenectomy based on palpation findings alone and found a second mass intraoperatively that I had completely missed. The ultrasound would have caught it beforehand. Anatomy prepared me for the procedure, but imaging prepared me for the actual surgery.