Using Dot To Dot Worksheets In Senior Cognitive Assessments
I spent about three years administering sensory-motor and cognitive screening tools to older adults in a memory clinic setting. The most common complaint from therapists wasn't about the complexity of the protocols. It was about finding age-appropriate dot to dot worksheets that actually matched the assessment criteria without feeling childish. Seniors in their seventies and eighties will shut down immediately if you hand them something that looks like it came from a kindergarten class. That disconnect ruins the data. The core issue with using these worksheets for assessment purposes is that most free printable versions online are designed for entertainment, not clinical measurement. A worksheet with fifty dots arranged in a simple animal shape tells you almost nothing about visuospatial processing, pursuit eye tracking, or fine motor steadiness unless you're measuring the right variables. I learned this the hard way when I gave a battery of standardized tasks to a 78-year-old former engineer and he completed a dot-to-dot sequence meant for a six-year-old in under twelve seconds with zero hesitation. The worksheet provided no resolution for that speed of completion.
Dot To Dot Worksheets For Seniors Assessment Test
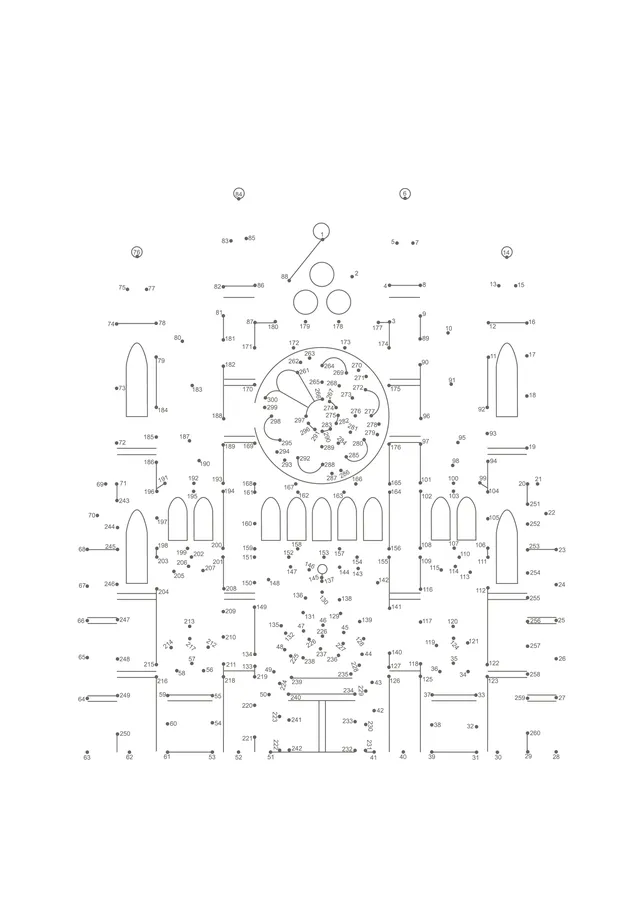
When you are building a legitimate assessment tool around dot to dot worksheets, you need to track several measurable outputs. Completion time is the first one. The accuracy of the line path is the second. Pressure consistency across the drawing surface matters if you are evaluating fine motor control. You also want to note where the person starts their dot sequence. A left-sided starting bias in a right-handed participant can indicate neglect or spatial attention issues that show up long before more obvious symptoms. I typically record all four metrics on a simple scoring sheet and compare them against a normative baseline for the person's age bracket. One thing most people miss is that the dot spacing and sequence length should vary in a deliberate progression rather than presenting one static difficulty level. If you give someone only an easy worksheet, you get a floor effect. If you only give them a hard one, you get a ceiling effect. I built a three-tier system where tier one has large spacing with eight to ten dots, tier two has medium spacing with fifteen to twenty dots in a slightly more complex polygon, and tier three uses tighter spacing with twenty-five to thirty dots arranged in an irregular pattern that requires working memory to track the correct sequence. This usually takes about twenty minutes to administer and yields enough data to flag subtle declines in processing speed or spatial reasoning. I had a specific problem with one participant who had mild tremor from Parkinson's medication. The dot to dot worksheet showed artificially slow completion times and line deviation that looked like cognitive impairment on the surface. The workaround was straightforward. I switched to a dry-erase laminated sheet and asked him to trace the sequence with his finger first, then re-do it with a pen. The finger tracing version produced clean timing data that reflected actual cognitive processing speed without the motor interference clouding the results. I noted both scores separately in the report so the occupational therapist could distinguish the motor component from the cognitive component. Without that separation, you are just generating noise.
Another counter-intuitive finding from my experience is that more dots does not always equal better assessment. A forty-two dot worksheet that creates a detailed picture looks impressive on paper, but in practice it often causes participant fatigue before you have collected reliable data. The person loses focus around dot twenty-eight, their line pressure becomes inconsistent, and the timestamps blur together. I found that a carefully constructed twenty-dot irregular sequence with deliberately ambiguous intermediate points actually produces more diagnostically useful information than a longer simplified one. The ambiguous points force the person to rely on spatial memory rather than pure serial ordering, which is where early executive function deficits tend to surface. If you are looking for sources, the most reliable free options come from occupational therapy resource sites and geriatric education departments rather than generic worksheet download sites. Sites like TherapyFunWorks and the CDC's ElderCare materials occasionally post clinically oriented versions. I also use modified versions from Purdue University's aging research page, though you have to adjust the difficulty upward since their baseline is geared toward children. When downloading, check the date stamps. Versions posted after 2018 tend to account for modern print resolution and have cleaner vector paths that reproduce better on standard home printers. The biggest limitation of dot to dot worksheets as an assessment tool is that they only measure a narrow band of cognitive and motor function. They do not assess verbal memory, language comprehension, or abstract reasoning. Relying on them alone gives you a false sense of completeness. I always pair the worksheet with a clock drawing test and a trail making portion, even a brief one, to get a fuller picture. The dot to dot section usually adds about eight to ten minutes to the total assessment window, which is manageable if you schedule it early in the session before participant fatigue sets in.
Get the Full Details

Another failure mode worth noting is participants with diagnosed macular degeneration or cataracts. The worksheets become unreliable for them because the visual acuity deficit skews the completion time and accuracy metrics independently of cognitive status. I learned this with a 81-year-old woman who scored poorly on every standard worksheet before we realized her uncorrected vision was the actual bottleneck. Once she used her prescribed low-vision magnifier, her scores jumped into the normal range for her age group. Any assessment protocol using dot to dot worksheets should include a basic vision screening step first, otherwise you are misattributing visual impairment to cognitive decline. For creating your own materials, I recommend using a simple vector drawing program to generate the dot patterns. Set your dot radius to at least four pixels and space them according to the tier system I described. Print on heavy cardstock rather than standard printer paper because standard paper buckles under pen pressure and the dots shift position during administration, which ruins timing accuracy. I keep a stock of pre-printed sheets in labeled folders and rotate them across testing sessions to prevent familiarization effects. The same worksheet given twice within a month will show improvement on the second attempt even if the person's cognitive state has not changed, and that contaminates your longitudinal data. The administration procedure itself is fairly standard. Instruct the participant to connect the dots in numerical order as quickly and accurately as possible. Start the timer the moment they begin and stop it when the final dot is connected. Do not offer corrections during the task unless the person asks for the next number, in which case note the request as a separate behavioral observation. After completion, ask them to name or describe the image they drew. This optional verification step catches participants who complete the sequence correctly but do not retain the spatial gestalt of the final image, which is a specific pattern associated with certain types of parietal lobe dysfunction.
If you need a starting point for printed materials, the American Occupational Therapy Association website hosts a member resource section with licensed clinical worksheets that include scoring rubrics. They are not free to non-members, but the download cost is modest and the materials are validated against standard geriatric populations. For those working outside clinical settings, such as senior activity directors looking for engagement activities rather than formal assessments, the free worksheets from Scholastic and Education.com can be adapted by simply increasing dot density and reducing spacing between numbers. The structural framework is the same, and the engagement value remains high even without clinical scoring parameters. The practical reality is that dot to dot worksheets for senior assessment are a useful adjunct tool, not a standalone diagnostic. They are quick to administer, require minimal equipment, and provide concrete quantitative data when used correctly. They are also easy to misuse through inappropriate difficulty selection, inadequate scoring protocols, or failure to account for sensory and motor confounds. I have seen too many rushed assessments where the worksheet was pulled from a random download, timed with a phone stopwatch, and interpreted without any normative comparison. That approach generates numbers that look meaningful but carry little actual diagnostic weight. Spend the time building a proper three-tier system, track all four metrics consistently, and you will find the data holds up well under review.