How Dual Diagnosis Group Therapy Actually Works
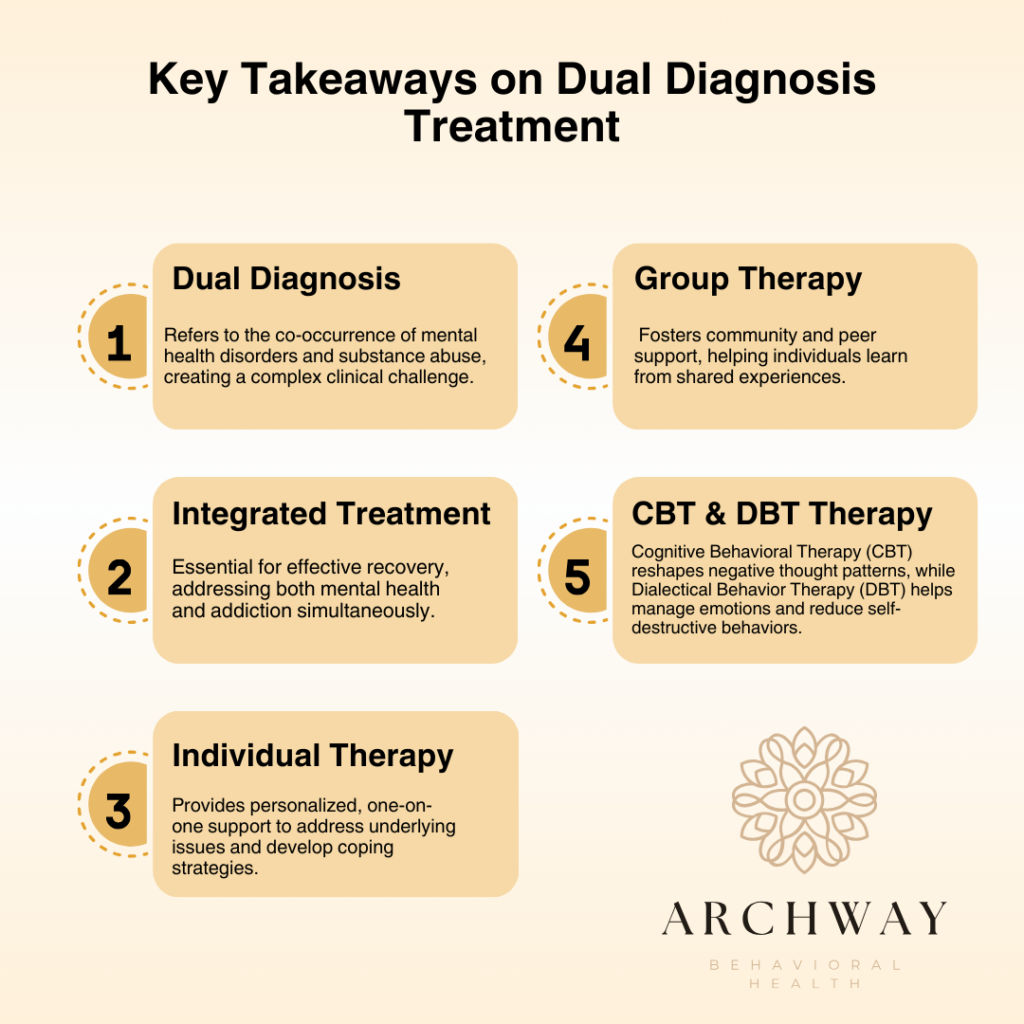
Dual diagnosis group therapy is when you put people with co-occurring disorders in the same room and let them talk through their problems under a therapist's guidance. The "dual diagnosis" part means someone has both a substance use disorder and a mental health condition at the same time. Schizophrenia plus alcoholism. Bipolar plus opioid addiction. Those combinations make individual treatment messier, and the group format tries to cut through some of that complexity by having people hear each other's experiences. It sounds straightforward in theory. In practice, running a dual diagnosis group requires a lot more structure than a standard addiction support group or a standard psychiatric group. You can't just throw twelve people with intersecting problems into a circle and hope for the best. The therapist has to manage three competing dynamics at once: the withdrawal and craving cycles, the psychiatric symptoms, and the group's interpersonal patterns. All of them overlap and trigger each other.What You Actually Do in Dual Diagnosis Group Therapy
Most programs run these sessions weekly, anywhere from 60 to 90 minutes. A typical structure looks something like this. You start with a check-in where each person states their current status on meds, cravings, and any recent crises. That takes about ten to fifteen minutes if people actually answer honestly. Then you pick a theme for the week — sleep disruption, paranoia around medication, the way mania accelerates relapse risk. You discuss it. The therapist steers conversations away from people becoming each other's unlicensed case managers, which happens constantly if you don't intervene. The therapeutic techniques pull from CBT, DBT, and motivational interviewing. You're not doing deep trauma work in a group setting usually. You're building coping skills, identifying triggers that connect the psychiatric and addictive sides, and practicing sober decision-making in real time. Role-play shows up a lot. You might have two people act out a scenario where someone is offered drugs while experiencing auditory hallucinations. The rest of the group gives feedback. It's awkward at first. It gets better after four or five sessions.A specific problem I ran into: I once had a participant in a dual diagnosis group who was newly diagnosed with borderline personality disorder and actively using cocaine. He would show up to sessions in a state of emotional dysregulation that made group discussion impossible. He'd spiral within minutes of any interpersonal tension, and the rest of the group would either disengage or try to manage his state instead of focusing on the treatment material. Standard group therapy rules don't account for this well. My workaround was to implement a brief individual check-out protocol at the end of each session where I could assess whether someone was too unstable to continue participating that day. If they were, I'd suggest they leave early and come back next week, or switch to an individual session temporarily. It felt harsh at first, but keeping that person in the group while dysregulated was actively harming the treatment of everyone else. After three weeks of this, he started using the check-out process himself — he'd recognize his own escalation and volunteer to step out before it became a group problem. That self-monitoring skill ended up being one of the most valuable things he took from the program.
The Counter-Intuitive Stuff Nobody Teaches You
One thing people miss about dual diagnosis group therapy is that the most impaired participants are often the ones who benefit the most, not the least. You'd think someone in active psychosis or severe mania should be excluded from group work. But those individuals frequently have the strongest peer feedback because their distortions are visible to others in real time. When someone with paranoid ideation accuses another participant of plotting against them, the group can collectively test that reality in a way individual therapy never allows. The therapist doesn't have to be the one challenging the delusion. The group does it naturally. Another overlooked point is that medication compliance becomes a group topic whether you want it to or not. In a regular addiction group, someone might skip their medication and nobody addresses it directly. In a dual diagnosis group, skipping psychiatric meds is usually what triggers the next relapse episode. People notice this pattern in each other faster than clinicians do. You'll have someone say "you look manic" or "have you been taking your lithium" and that intervention carries more weight coming from a peer than from a doctor who sees them once a month.When This Approach Completely Fails
Dual diagnosis group therapy is not a universal solution. It fails in several scenarios that programs don't always admit upfront. Active psychosis where the person is a danger to themselves or others is the most obvious one. You shouldn't put someone in acute schizophrenic crisis into a group setting. They need stabilization first, which usually means inpatient care or intensive outpatient treatment. People with severe antisocial personality traits also tend to disrupt these groups. They'll manipulate, lie, and derail sessions without any awareness that they're causing damage. Standard groups assume a baseline of good faith participation. When that's absent, the whole structure collapses. Another failure mode is when the substance use disorder and the psychiatric disorder are moving at completely different speeds. Someone whose bipolar disorder is well-managed on medication but who is still actively bingeing on methamphetamine isn't getting much out of a weekly group. The group can only address what's happening in the room. It can't replace the intensity of specialized addiction treatment or psychiatric care that the person actually needs. If someone falls into any of these categories, individual therapy with a clinician trained in both addiction and psychiatric disorders is the better path. Or a specialized dual diagnosis residential program. Group therapy is one tool, not the whole toolbox.What Makes a Good Dual Diagnosis Group Program
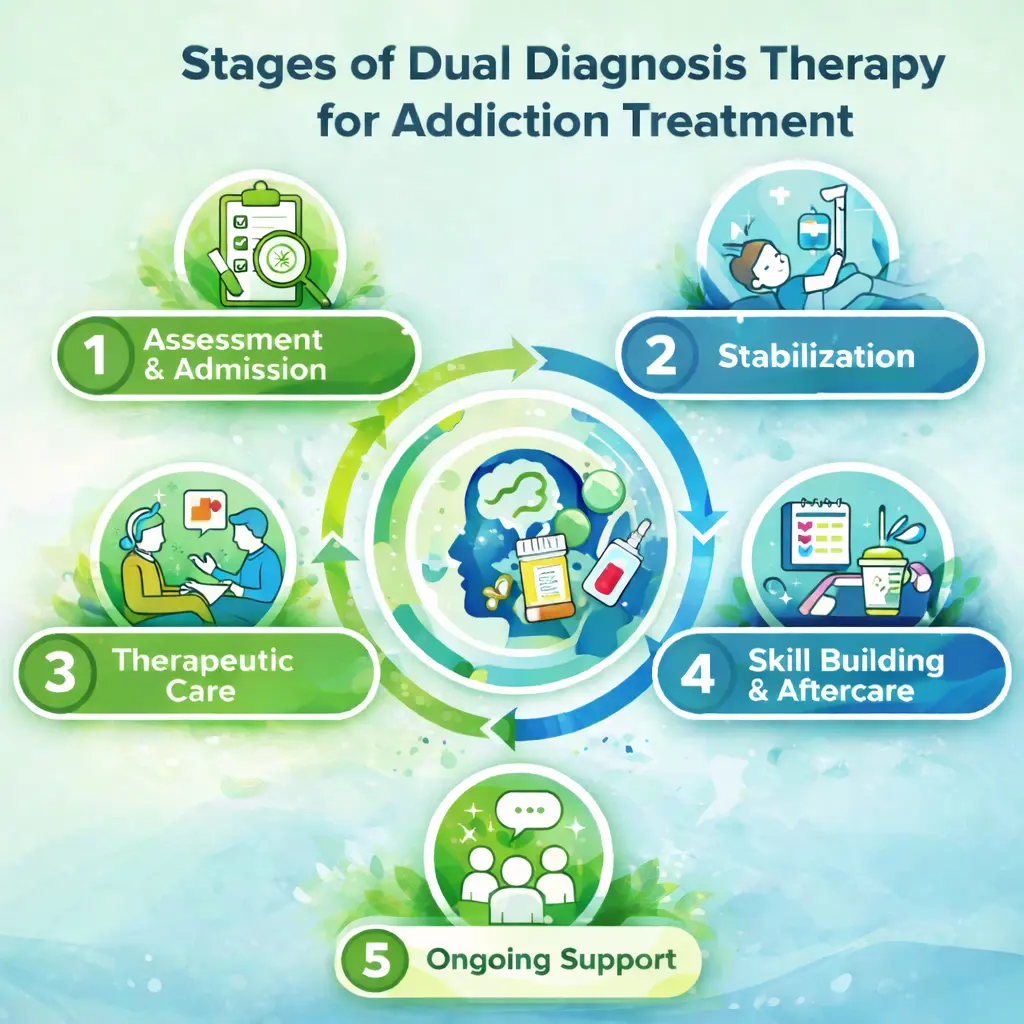
The therapists running these sessions need actual training in both addiction and mental health. General group therapy certification doesn't cover the intersection. You need someone who understands how stimulants interact with antipsychotics, how mood stabilizers affect craving patterns, how to distinguish between drug-induced symptoms and primary psychiatric conditions. That knowledge base is narrow and not universally distributed. Programs that work best also integrate the group with individual and family treatment. The group alone cannot address the full scope of a co-occurring disorder. It's most effective when it's part of a coordinated system where the group therapist communicates with the individual therapist and the prescriber. Information sharing between providers is where most programs break down due to HIPAA complexities, but it's essential for anything resembling competent care.Session frequency matters more than people realize. Once a week is the minimum. Biweekly or more is better for active cases. The weekly cadence is standard because of insurance reimbursement structures, not because it's optimal. If you can afford it, twice-weekly groups produce measurably better outcomes in the literature, particularly for maintaining psychiatric stability while addressing substance use.