What You Actually Look For When You Pull That Auricle Back
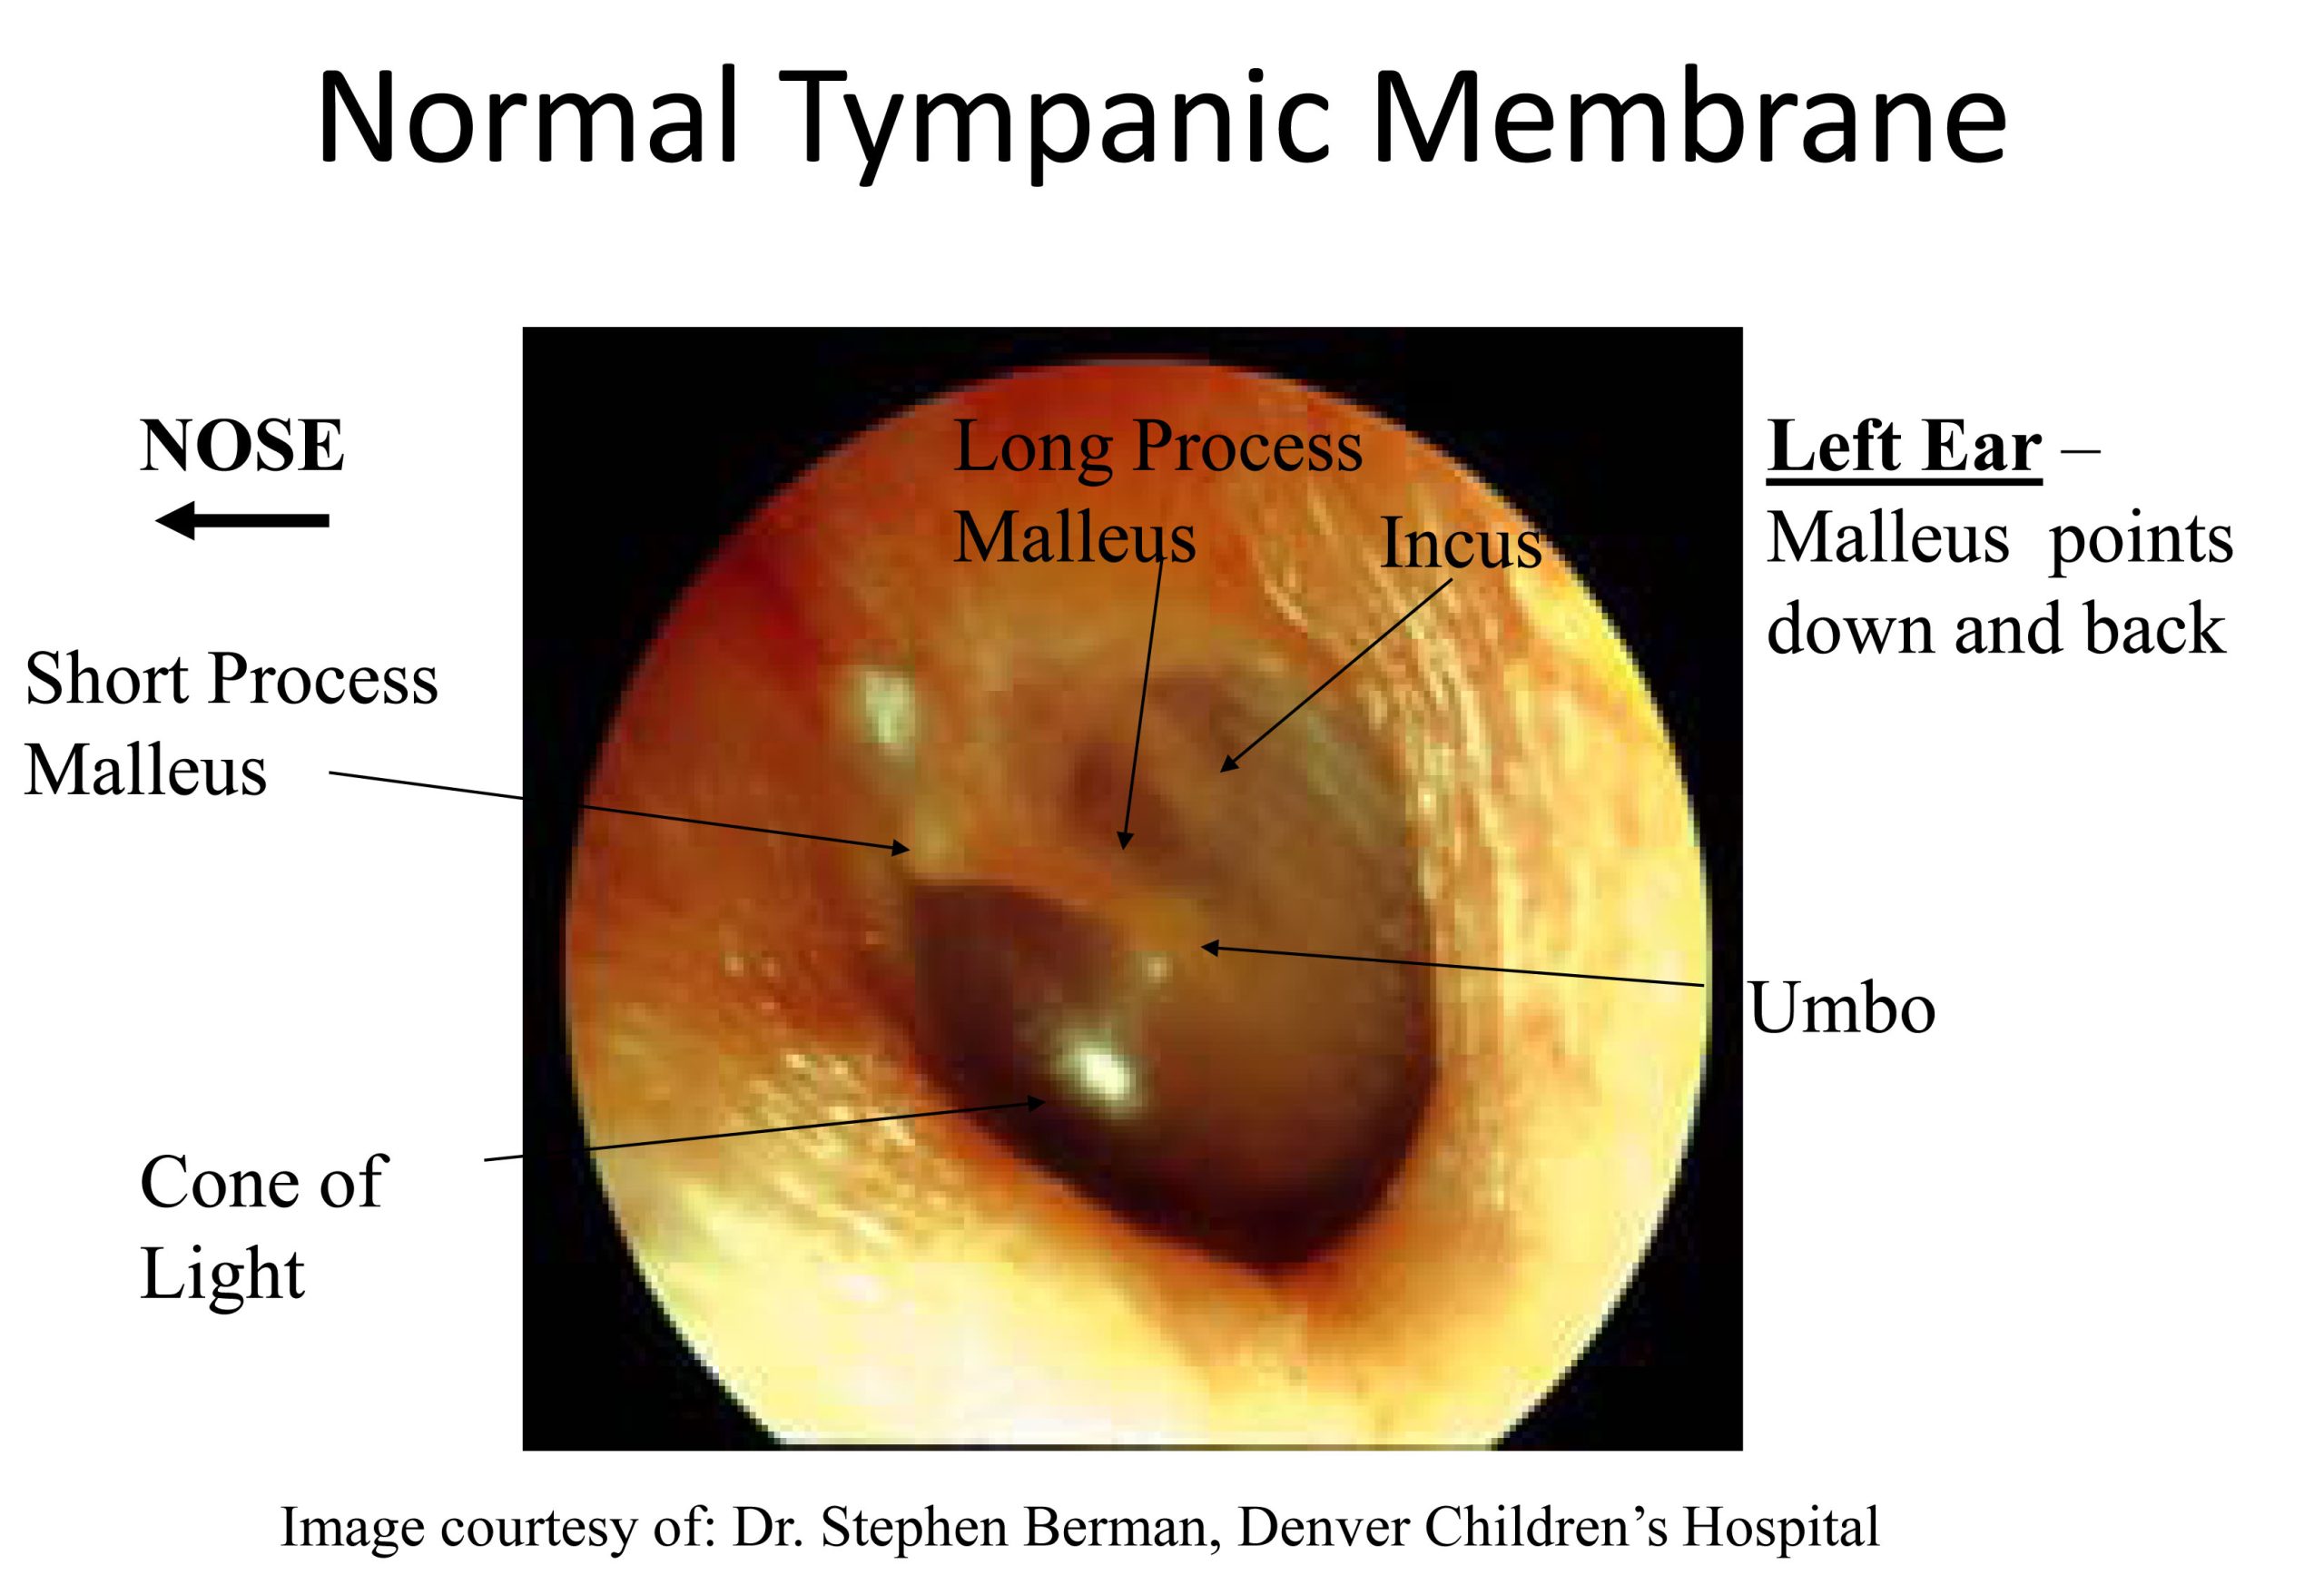
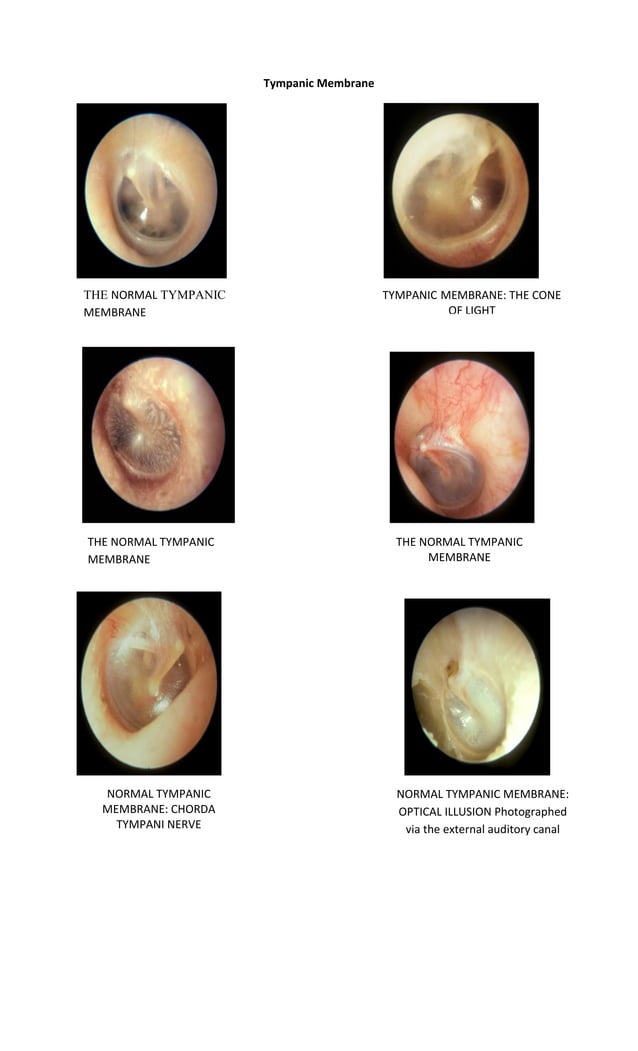
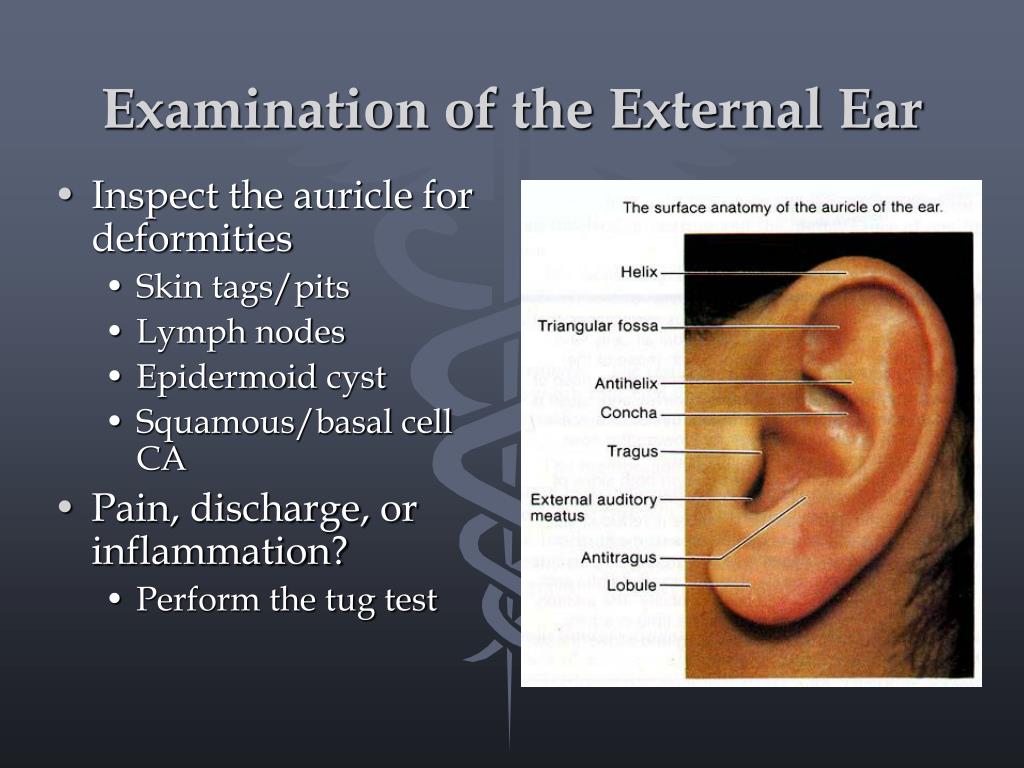
Most people think ear assessment normal findings are just about checking for infection or hearing loss. They're not. It's a systematic visual and physical inspection that takes about ninety seconds if you're not second-guessing yourself, and roughly two to three minutes if the patient is cooperative and the lighting is decent. I've been doing this since residency and I still mess up the pinna inspection when I'm rushing through a clinic list.Start with the external ear. The auricle should be symmetric, without nodules, cysts, or skin lesions. The tragus, antitragus, helix, and lobule should all be palpable without tenderness. I once missed a small preauricular sinus tract because the patient's hair was covering the area and I didn't pull it back. Took me three attempts before I caught it. Pull the hair. Always pull the hair. When you look inside with the otoscope, the tympanic membrane should be pearly gray, translucent, and cone-shaped with the light reflex visible at approximately the 5 o'clock position on the right ear and 7 o'clock on the left. The umbo should be centered. The malleus handle should be visible as a pale ridge running downward and forward. These are the basics you'll find in any textbook. The things textbooks don't tell you are where the actual errors happen. Normal canal skin is thin, pink, and hair-bearing in the outer third. The cartilaginous portion can have cerumen without pathology. Cerumen that is light brown and friable is normal. Dark, impacted wax that obscures the TM is a different conversation entirely. I had a patient last month whose TM looked entirely normal on the first look because the wax was packed behind the probe tip. I switched to a larger speculum and gentle irrigation. The drum was clear. Standard workup revealed nothing wrong. It just cost me five extra minutes I didn't have.
The tympanic membrane should move with pneumatic otoscopy. A normal study shows brisk, symmetric motion when you apply positive and negative pressure. If the drum is retracted but still mobile, that's a finding in itself — it suggests eustachian tube dysfunction rather than a middle ear effusion. A fluid level or air bubbles behind the TM indicate otitis media with effusion. Purulent material is acute otitis media. Those are the three categories you'll see ninety percent of the time in primary care. Hearing screening is usually done with a tuning fork. The Rinne test compares air conduction to bone conduction. Normal findings show AC greater than BC in both ears. The Weber test should be midline. If Weber lateralizes to one side and Rinne is abnormal on that side, you're looking at conductive hearing loss. If Weber lateralizes to the affected side and Rinne is normal, that's sensorineural — which sounds backwards but it's consistent. I still double-check this every time because I've seen resident notes that flip the interpretation and it changes the entire differential. One thing nobody warns you about is the variant tympanic membrane. Some people have a naturally retracted drum that's been like that for years. If you see retractions but the mobility is normal and there's no history of chronic ear disease, it may just be their baseline. I spent two weeks chasing a diagnosis on a patient I thought had recurrent otitis media until I pulled her records from five years prior. Same findings every time. She was fine.
Audiometry is the gold standard when you need definitive data. Pure tone audiometry tests frequencies from 250 to 8000 Hz. Normal hearing is 25 dB HL or better across all tested frequencies. Speech audiometry should show word recognition scores above 90 percent in quiet. These numbers matter because they're the baseline you return to when something changes later. The limitations of bedside ear assessment are real. Otoscopy is operator-dependent. Image quality degrades significantly with cerumen, small canals, or an uncooperative child. Pneumatic otoscopy has about 80 to 85 percent sensitivity for detecting middle ear effusion compared to tympanometry. If you're uncertain, a tympanogram will resolve it in under thirty seconds. Type A = normal middle ear function. Type B = flat, suggests effusion. Type C = negative pressure, suggests eustachian tube issues. I recommend having tympanometry available in any clinic setting where ear assessments happen regularly. It's inexpensive, quick, and catches the cases that otoscopy alone misses. I've lost count of how many times I've been confident about a normal exam only for the tympanogram to show a Type B curve confirming a silent effusion. The patient didn't have symptoms. Neither did I, initially.
Get the Full Details

Document everything systematically. The canal, the TM appearance, mobility, and the tuning fork results. If you skip the pneumatic step, someone reviewing your note will ask why. Just do it. It takes three seconds and it protects you when the follow-up visit reveals something your initial assessment missed.