Getting the Edi 837 Up and Running Without Losing Your Mind
Most people treat the 837 as just another transaction set to map and send. That mindset is why their implementations break on day one when a payer rejects a claim with a circular reference error involving segment-level qualifiers nobody bothered to validate. I have been wrestling with healthcare clearinghouses and X12 transactions since before most people knew what a HIPAA transaction was, and the 837 is still the one that makes me sigh.
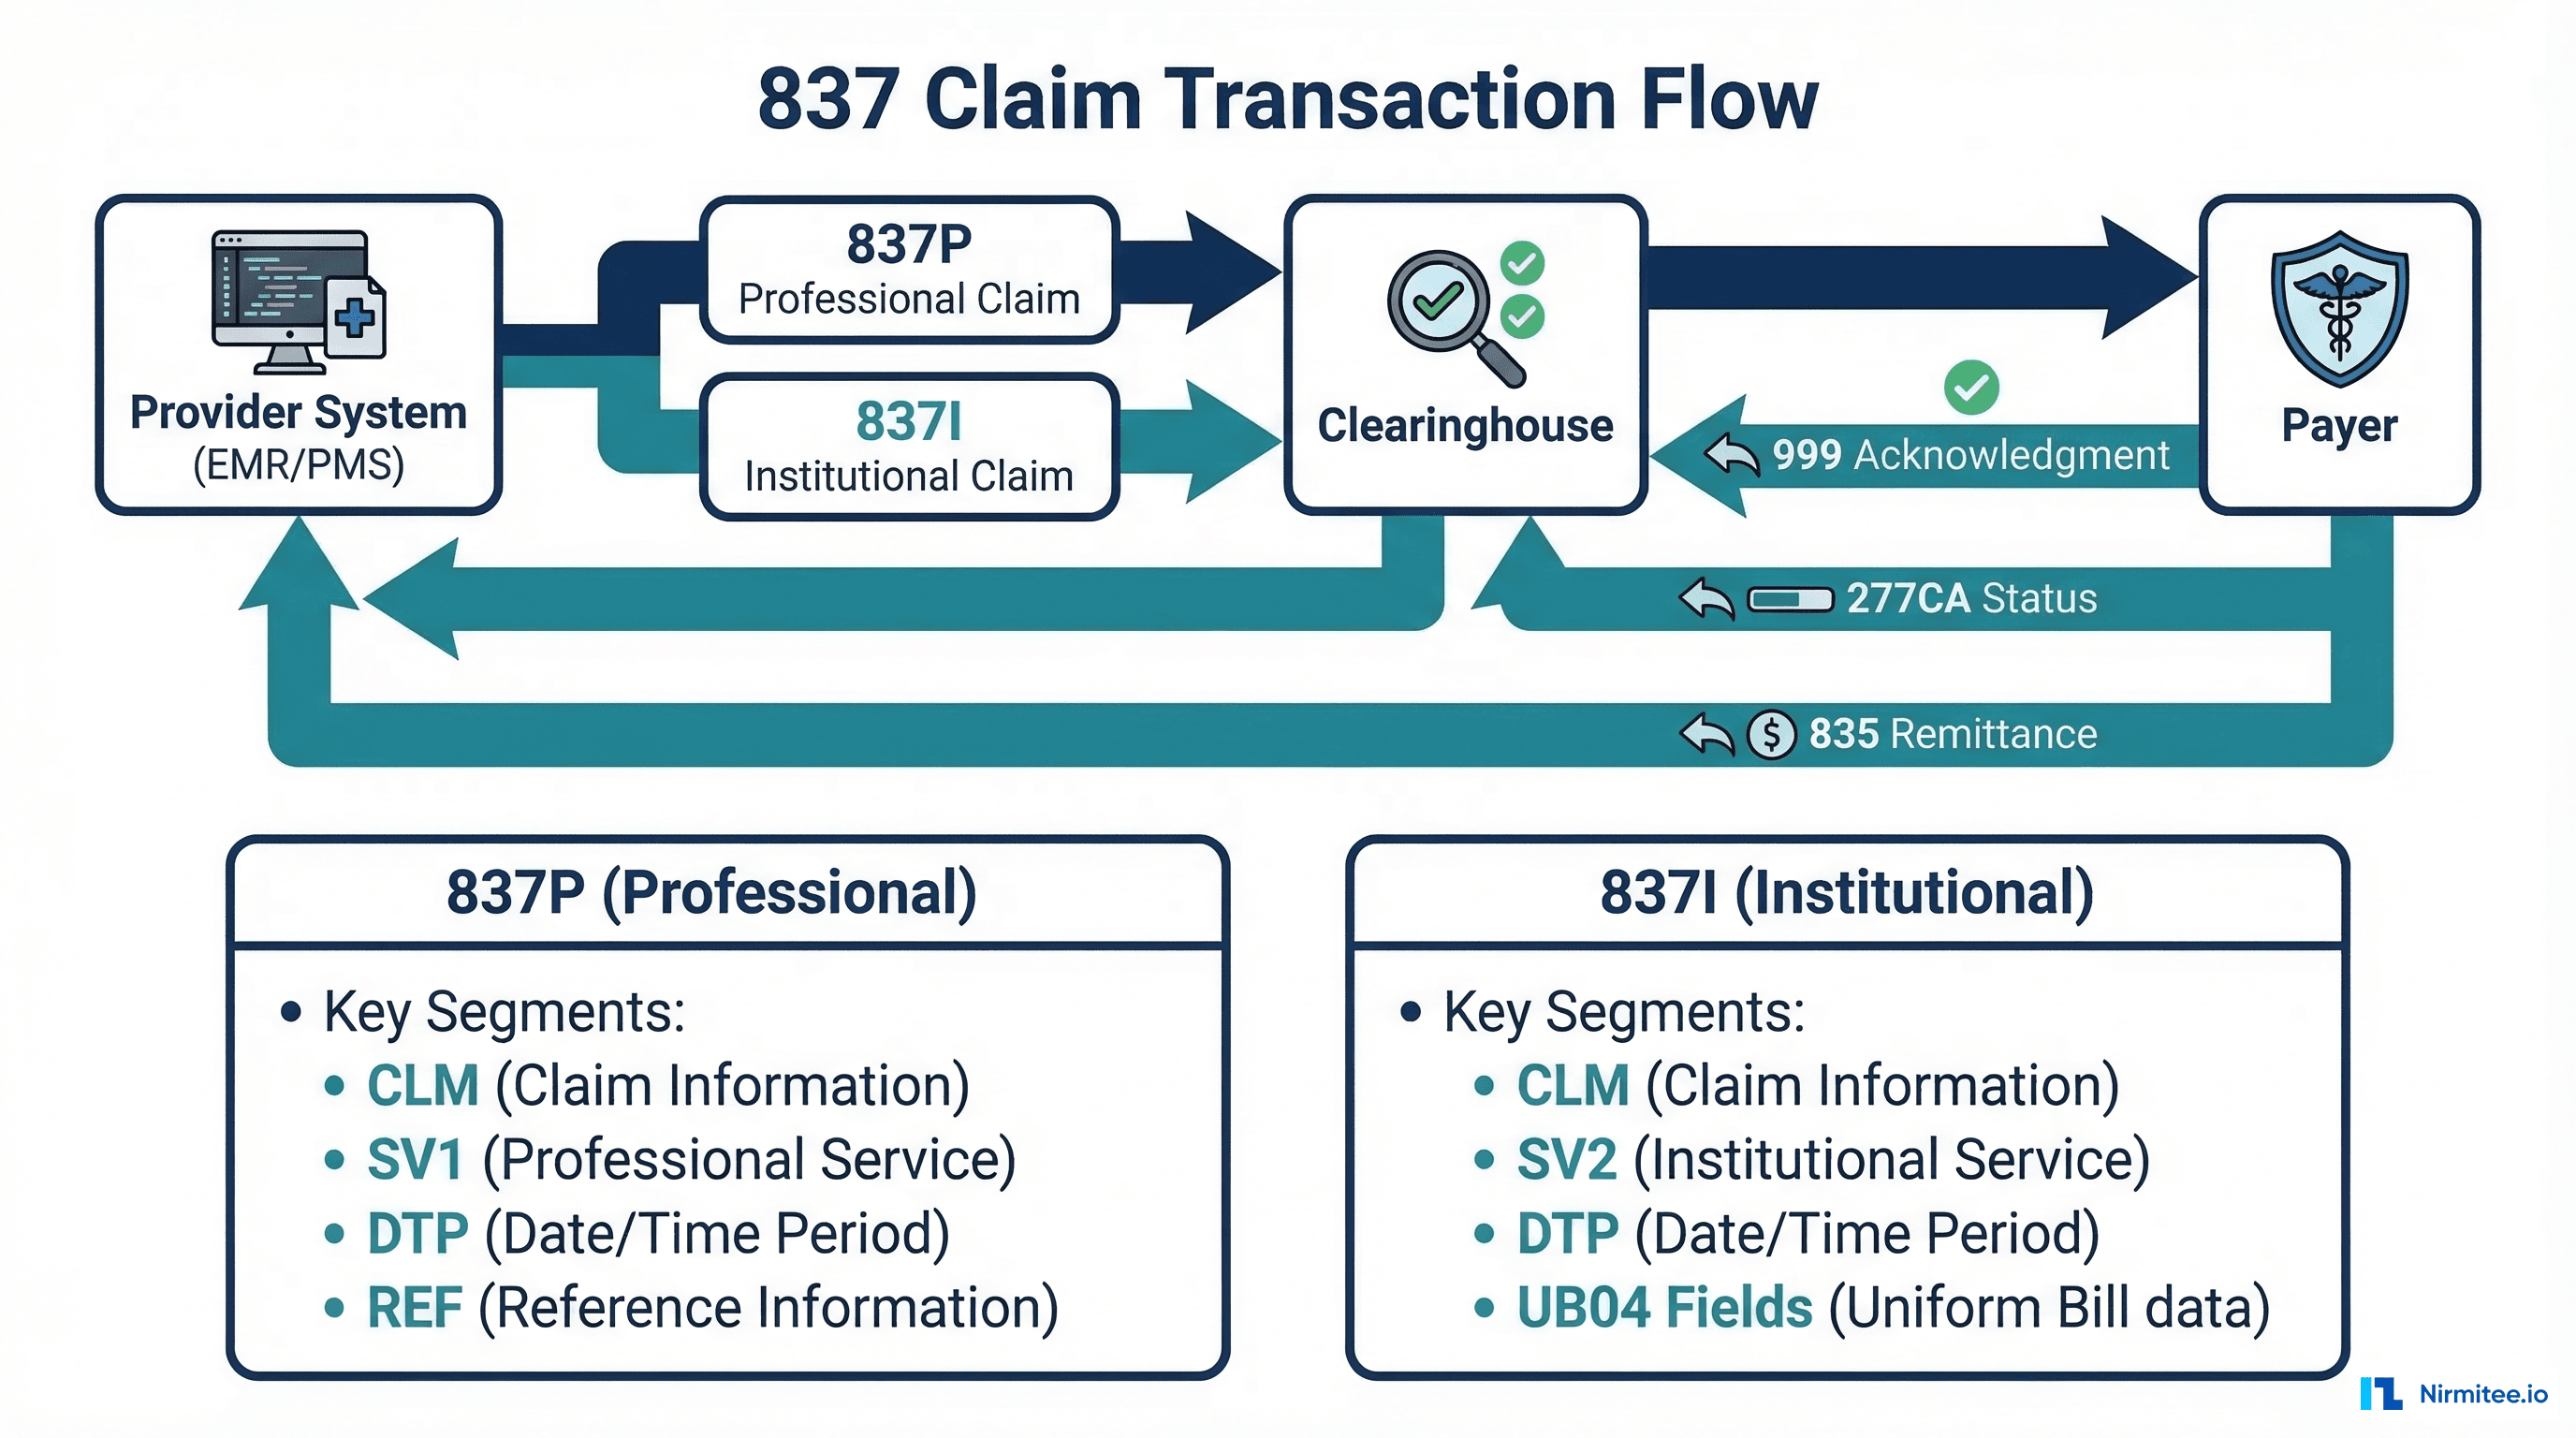
The 837 is the healthcare claim transaction used for professional, institutional, and dental claims. It came out of the HIPAA mandate when everyone in the US healthcare system had to switch from paper to electronic claim formats. The standard itself is maintained by ASC X12, and depending on what you are billing, you are dealing with one of three variants: the 837P for individual provider claims, the 837I for hospital or institutional claims, and the 837D for dental services. Picking the wrong variant is an easy way to waste a week of debugging.
Edi 837 Implementation Guide
I keep a copy of the official ASC X12 implementation guide bookmarked, but honestly the real implementation guide is whatever comes out of the payer or clearinghouse you are sending to. Payers add their own quirks on top of the standard. A commercial payer might require specific format for diagnosis pointer fields. A government payer like Medicare might enforce looping structures differently than what the base spec shows. Your first step should always be getting the payer's technical documentation before you write a single line of mapping code.
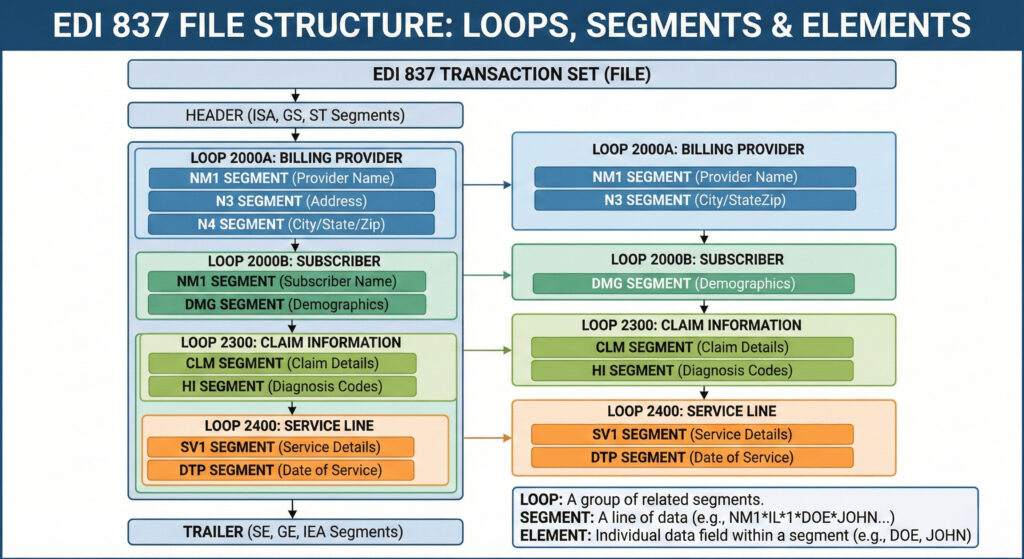
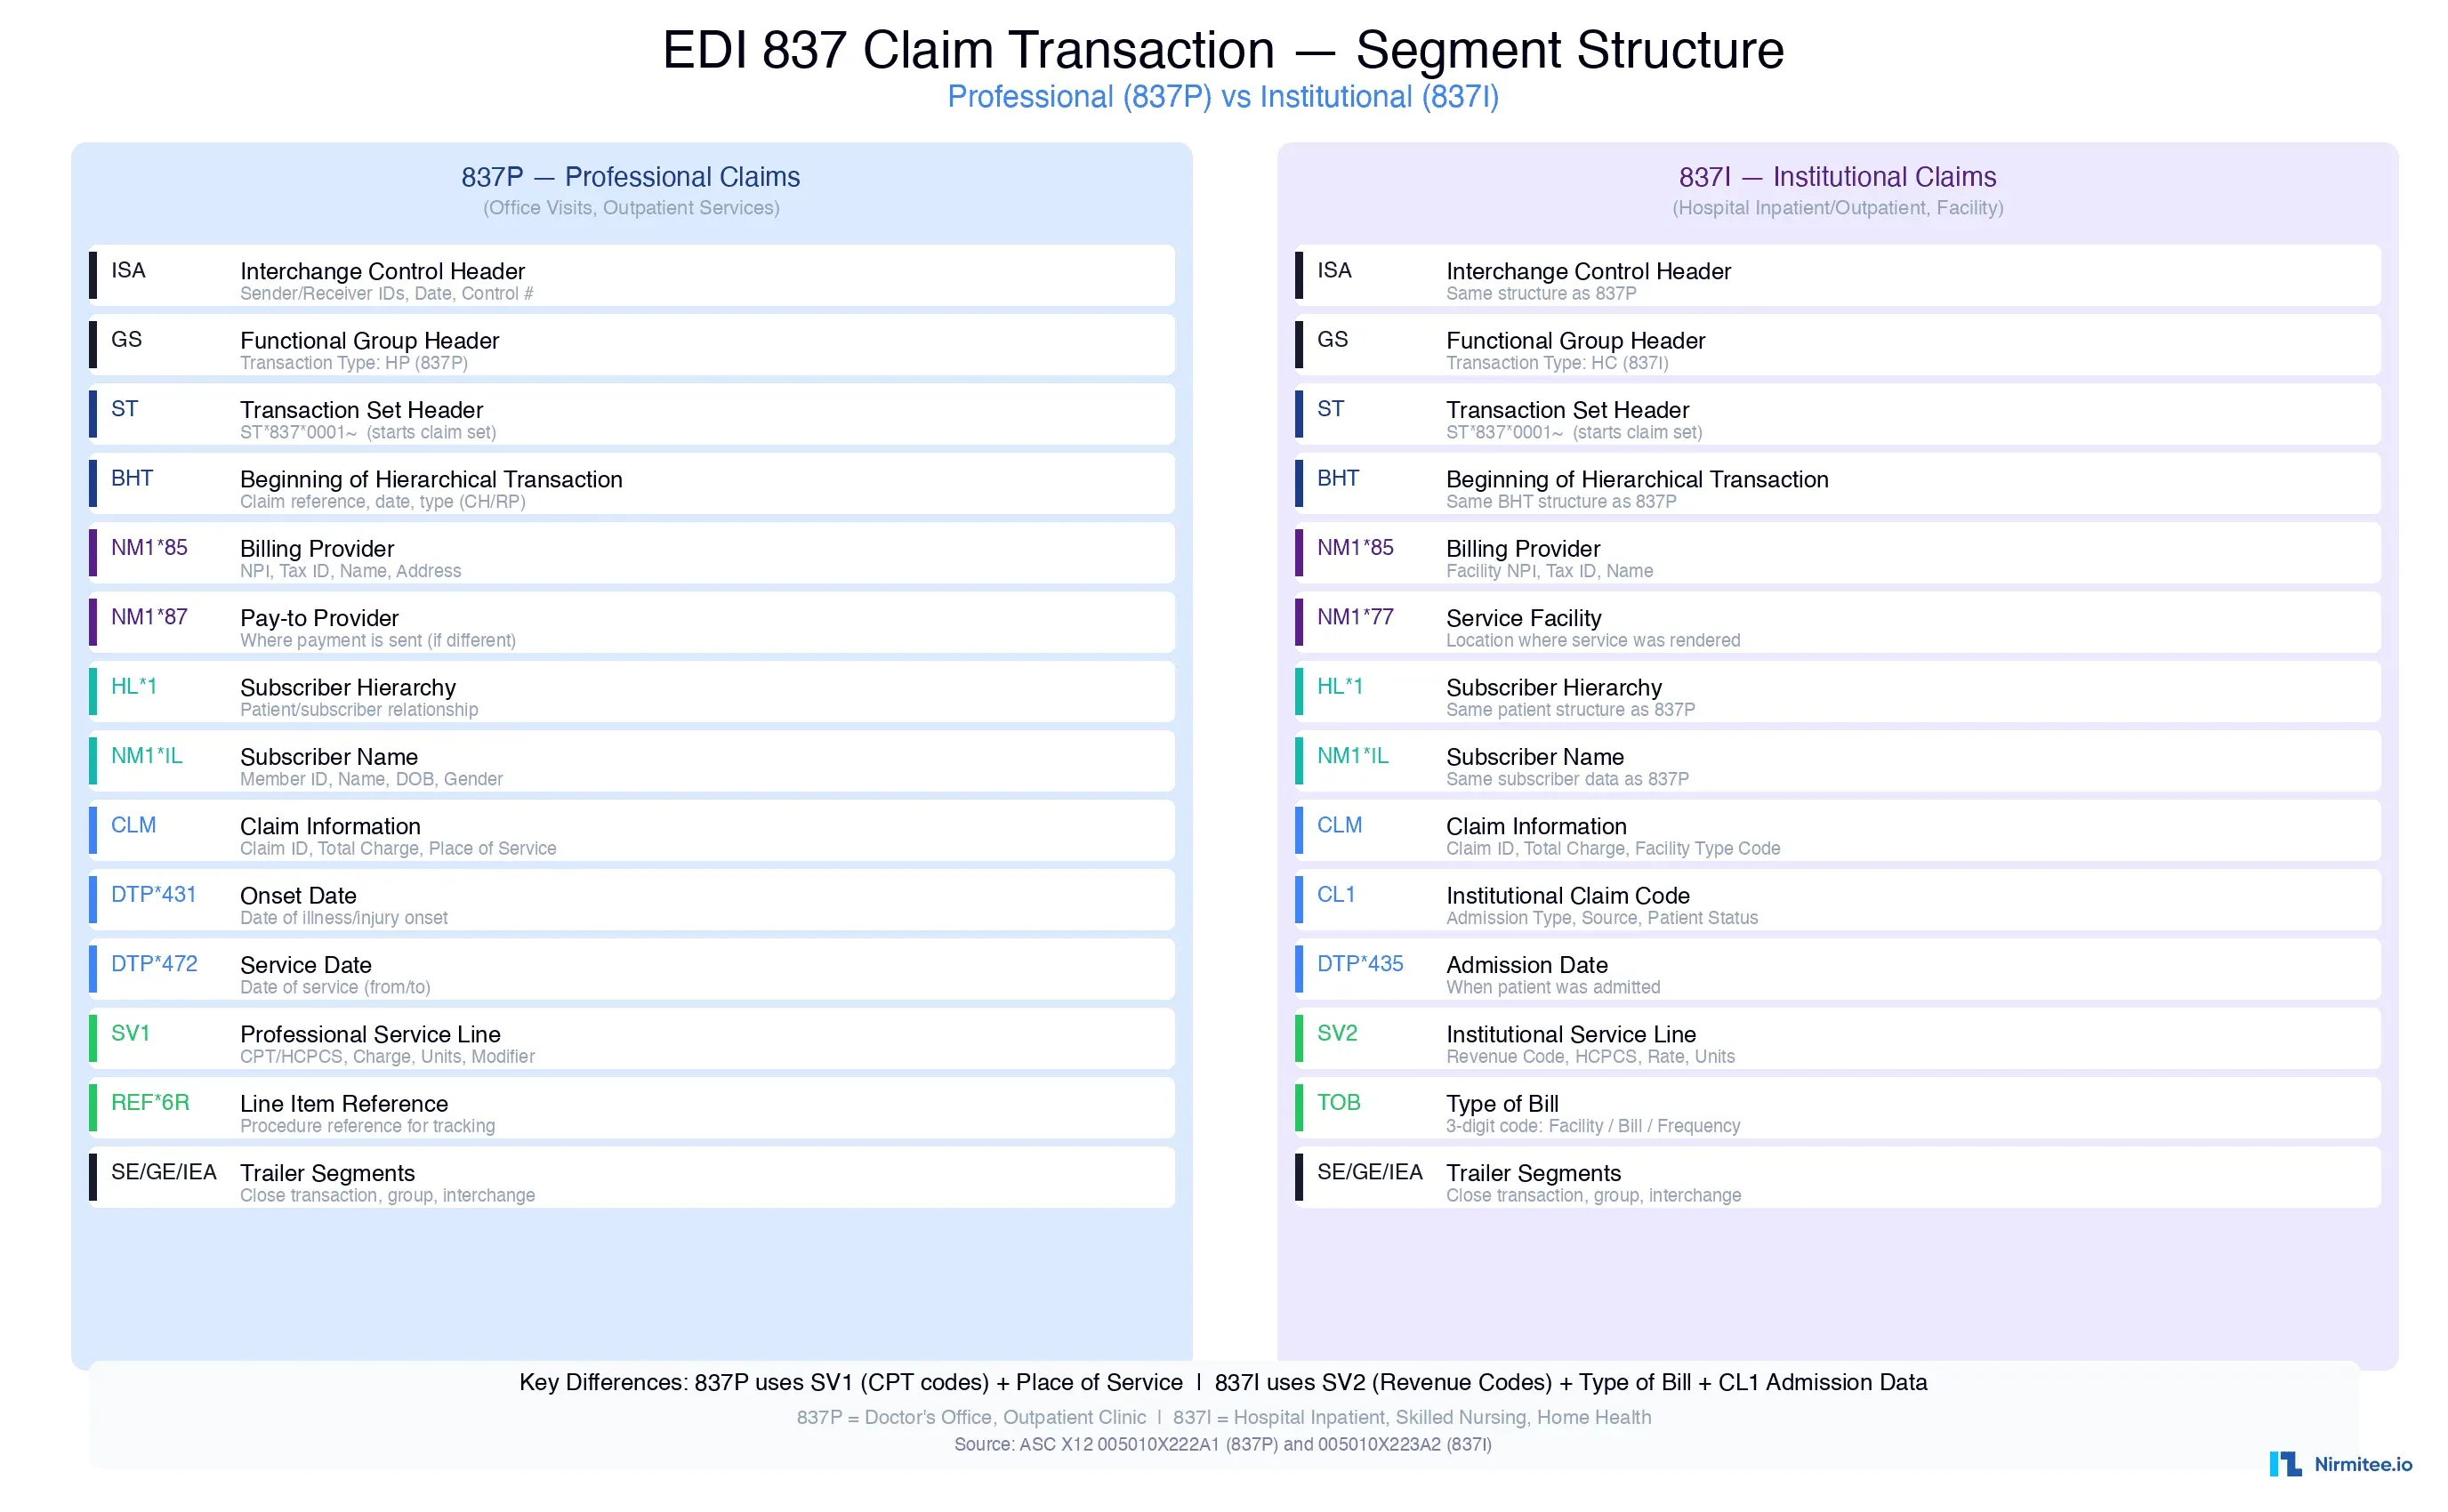
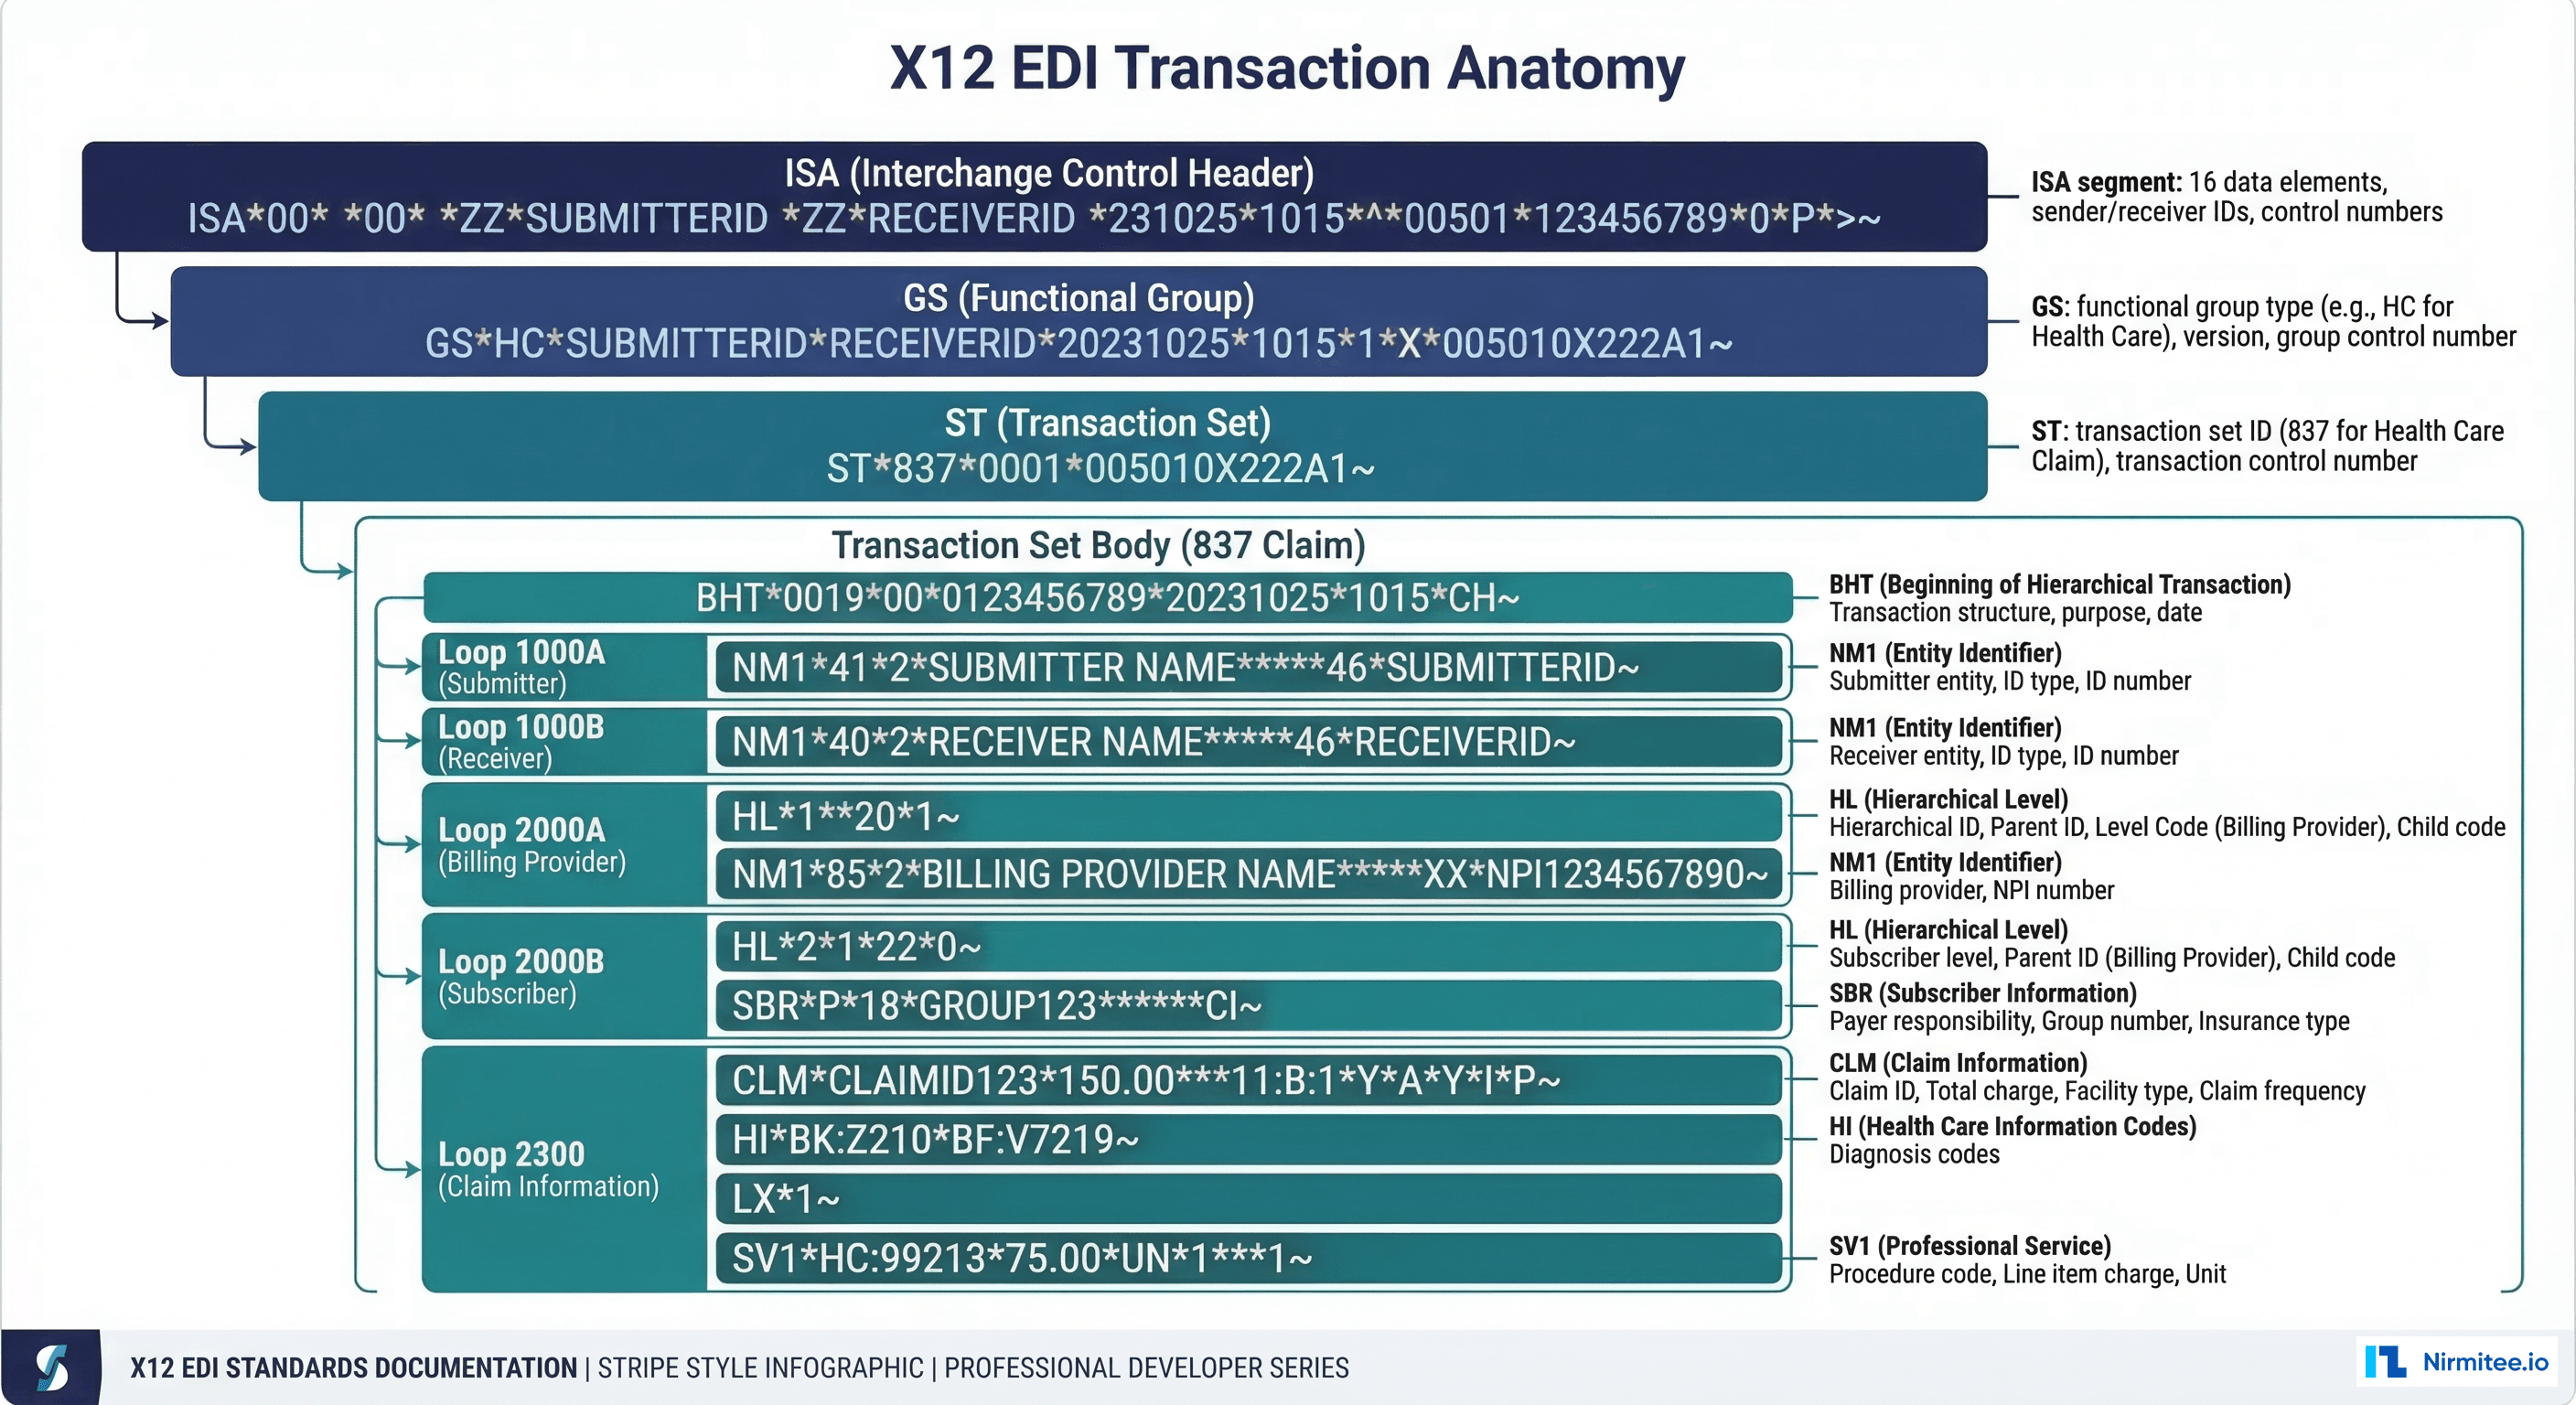
The transaction starts with the ISA segment, which handles the intercompany routing between your system and the clearinghouse. Then comes the GS segment for functional grouping, followed by the ST segment that marks the start of the actual 837 transaction. Inside the body you will find loops that carry patient information, provider details, diagnosis codes, procedures, and claim line items. The loop structure varies significantly between the P, I, and D variants, so do not assume they share the same anatomy.
One thing that trips up almost every implementation team is the NM1 loop. You will see NM1 tags used for the patient, the referring provider, the service provider, the payers, and sometimes the facility. Each NM1 occurrence has an entity type code in the NM01 field that determines what role it plays. I once spent three days chasing a rejection that turned out to be caused by an NM105 field where the payer expected a two-character qualifier but we had mapped it to a plain name field instead. The fix was straightforward, but the validation logic that should have caught it earlier was not in place.
How the Loop Structure Actually Works
The 837P uses a relatively flat structure. You get a loop for the biller or provider information, a loop for the patient, then loops for each service line. Each service line has its own diagnosis pointer references that link back to the diagnosis information stored earlier in the transaction. This linking is where things get fragile. If you have five diagnosis codes and only reference the first two across your claim lines, that is fine. But if your mapping points to a diagnosis pointer that does not exist in the DMG loop, the claim gets rejected immediately. No warning, no soft failure. Just an 837 reject code that looks completely cryptic unless you know the rejection syntax.
The 837I is structurally different because institutional claims involve revenue centers. Instead of simple line items, you have loops that bundle revenue codes with charges, procedures, and units. A single hospital stay can produce hundreds of revenue centers. The 837I also includes loop structures for the claim certification and the encounter information that do not exist in the P variant. If you are converting an institutional billing system, expect the 837I to be roughly twice as complex to map compared to the 837P.
For the 837D, the structure is closer to the 837P but adds dental-specific elements like procedure codes from the CD range, tooth locations, surfaces, and restorative materials. Dental also uses the DS modifier loop extensively. If you skip validating the DS segment against the procedure code in the CLIm loop, you will get rejections that are nearly impossible to trace back to the root cause without deep X12 parsing knowledge.
What Most People Get Wrong
The biggest mistake I see is assuming the 837 spec alone is enough. It is not. You need the payer-specific addenda, and those addenda change periodically. I worked with a client who built their entire 837P engine based on a two-year-old implementation guide from a major commercial payer. Six months later the payer updated their requirements to include a new segment for coordination of benefits details. The client's claims started failing en masse. They had no update mechanism in place and had to hot-patch their mapper while processing a backlog of rejected claims. The fix took about four hours once we identified the new requirement, but the damage to their submission pipeline was significant.
Another common failure point is the date formatting. X12 dates use the CCYYMMDD format, which sounds simple until you realize that some payers accept MMDDYYYY and some strictly reject anything else. Your validation layer should enforce CCYYMMDD globally before the data reaches the parser. I have seen entire claim batches fail because a single date field was formatted as MM/DD/YYYY instead of the required eight-digit format.
Transaction control numbers are another area where implementations routinely stumble. Each ISA and GS segment needs unique control numbers. If your system generates the same ISA06 and ISA07 values for two consecutive batches, the receiver will reject the second batch as a duplicate. I wrote a small utility that randomizes these control numbers at runtime instead of relying on sequence counters, and it eliminated a class of intermittent failures that had been plaguing our test environment for months.
Parsing and Validation Strategy
You should never rely on a naive string split to parse X12. The delimiters vary. The segment terminator is typically the carriage return character, but the component data element separator and the sub-element separator can differ between implementations. The standard defines the asterisk for data elements and the colon for sub-elements, but I have encountered clearinghouses that swapped them. Your parser needs to read the ISA01 through ISA12 header fields to determine the actual delimiters being used for that transaction.
Validation happens at multiple levels. At the segment level you check that required segments are present. At the loop level you verify that referenced pointers actually resolve. At the data element level you check formats, lengths, and valid code sets. The claim loop requires that you have at least one diagnosis pointer per service line, that the diagnosis codes in the DMG loop match valid ICD codes, and that the procedure codes in the CL1 loop match valid CPT or HCPCS codes. Missing any single piece causes a rejection.
I recommend building a schema-aware validator that can run against raw X12 files before you even attempt to map them to your internal format. This catches structural issues early. I built one using a DTD-like validation approach that checks segment counts, loop nesting, and required field presence. It reduced our error rate from about 12 percent down to under 2 percent within the first month of deployment. The remaining errors were almost always data quality issues rather than structural problems.
Testing Against Real Payers
Testing in isolation is not sufficient. You need to send test claims to actual payer portals and review the rejection reports. Most major payers provide a test environment, but the test environment does not always mirror production behavior perfectly. Medicare's test system will accept claims that would fail in production under certain conditions. Commercial payers sometimes have different validation rules in their test versus production environments. The only reliable approach is to run a parallel testing phase where you send claims to both environments and compare the results over time.
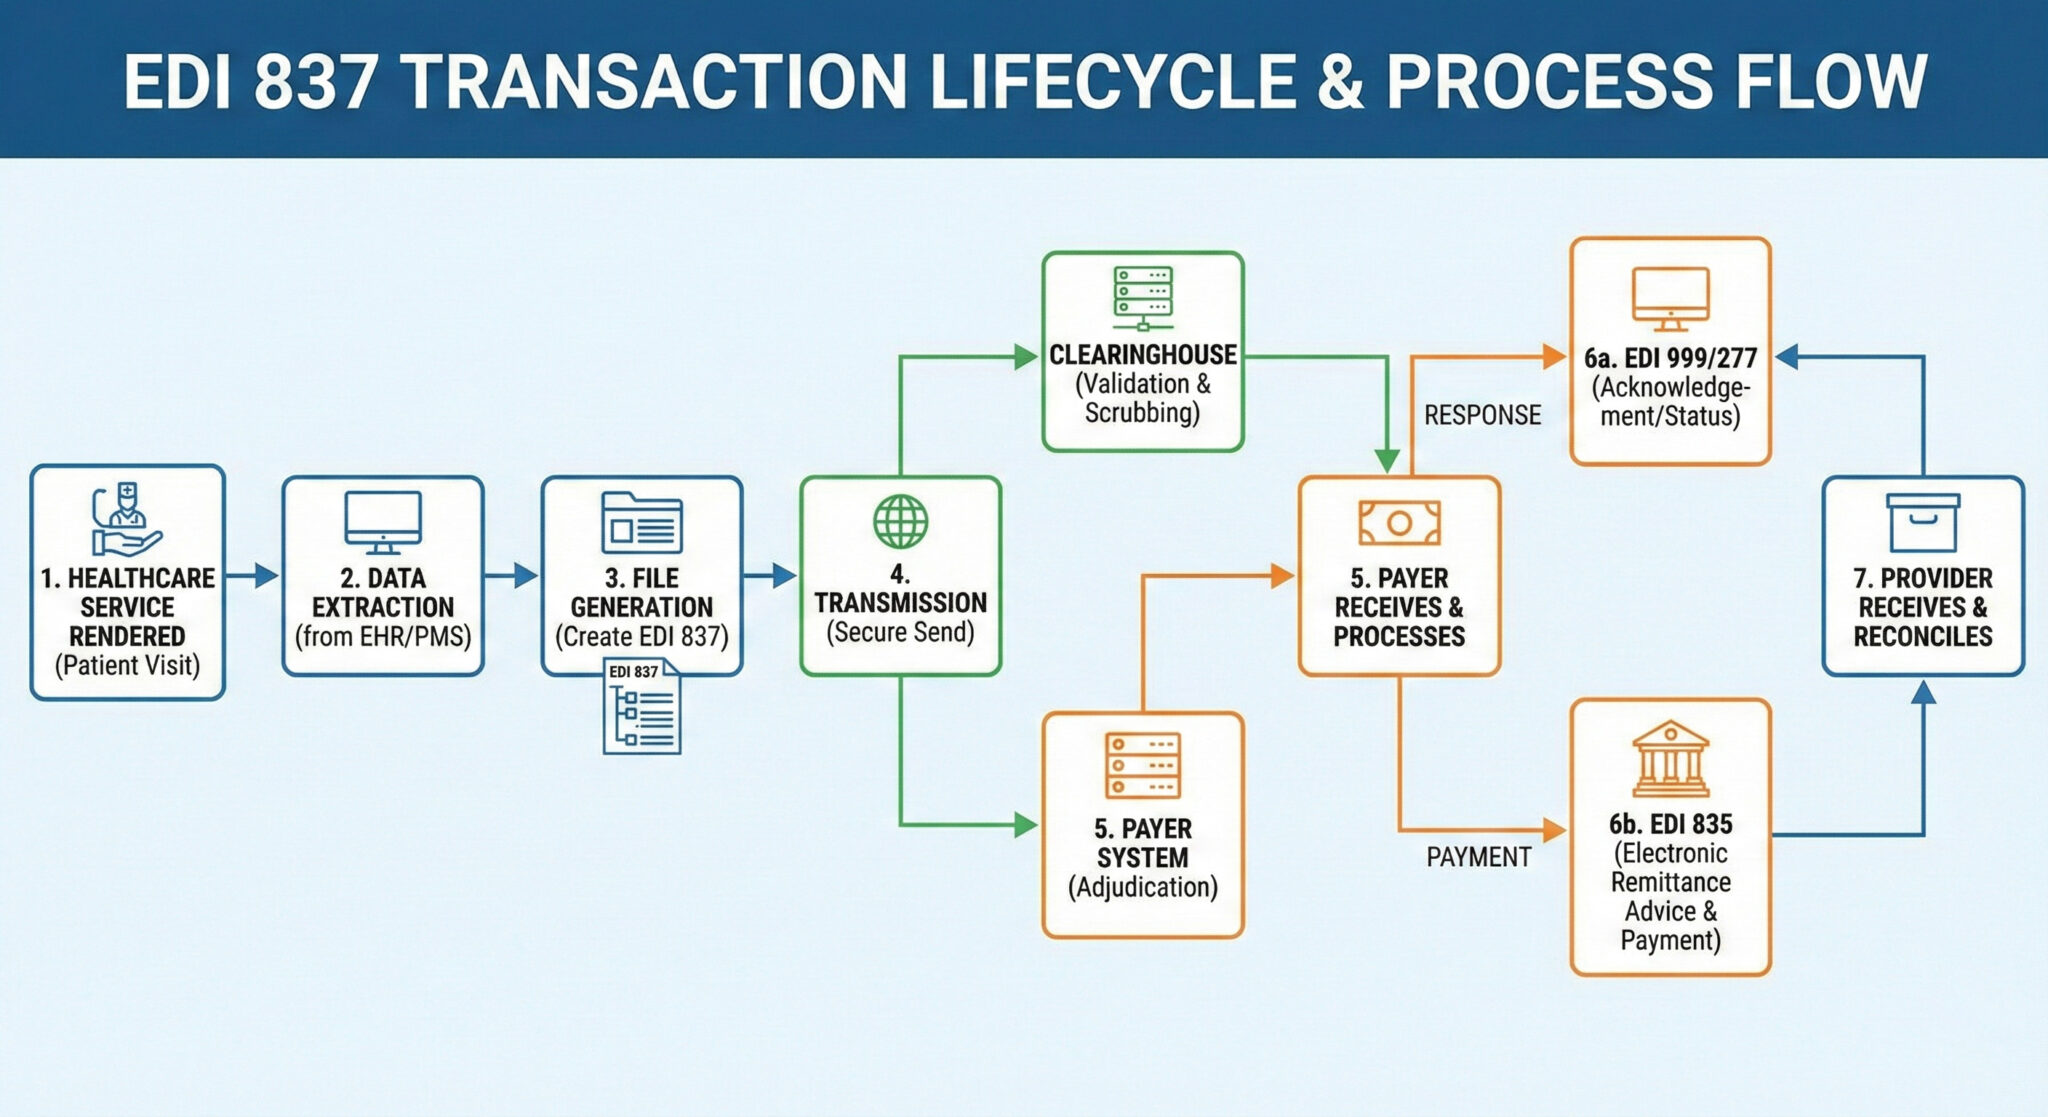
Clearinghouses can smooth this process considerably. A good clearinghouse will accept your 837 files, run their own validation, and return a report showing exactly which segments and data elements caused rejections. The reports vary in quality. Some are vague and unhelpful. Others provide precise field-level error messages that point directly to the problem. I have found that switching clearinghouses when one consistently returns poor rejection diagnostics is usually worth the effort, even if it means reconfiguring your transmission setup.
Common Pitfalls and Hard Truths
The 837 is not a universal solution. If you are billing for non-standard services like transportation, wellness programs, or non-covered procedures, the 837 may not be the right transaction at all. Using it for these purposes creates awkward mappings that neither payers nor your internal systems handle well. In those cases the 837 replacement or an alternate claim format might be more appropriate.
Handling coordinate of benefits for secondary payers adds significant complexity. The 837 supports multiple payer loops, but the ordering matters. The primary payer must be listed first, and each subsequent payer must reference the previous one correctly. Getting this wrong does not just cause a rejection. It can result in claims being submitted to the wrong payer in the wrong order, which creates payment delays and administrative overhead that can take weeks to resolve.
The transaction size limit is another practical constraint. Some clearinghouses impose maximum file sizes or maximum transaction counts per file. A large institutional claim with hundreds of revenue centers and dozens of service lines can approach these limits. If your organization processes thousands of claims daily, you need to chunk your files appropriately rather than dumping everything into a single submission.
A Real Problem I Faced
I encountered a situation where a payer was rejecting 837P claims with an error code that indicated a missing loop, but the loop was clearly present in the transaction. After spending two days reviewing the X12 syntax, I realized the issue was not structural. The payer's system was interpreting the qualifier in the NM02 field as an entity identifier rather than a name. The claim had a valid NM1 segment, but the qualifier was set to "XX" when the payer expected a specific code from their own published list. The workaround was to maintain a payer-specific qualifier lookup table that mapped internal entity types to the exact codes each payer required. This cut the rejection rate from about 8 percent to less than 1 percent for that particular payer.
What to Do Before You Start Building
Get the payer technical documents. Get the clearinghouse documentation. Build a delimiter-aware parser before you write any mapping logic. Validate date formats at ingestion. Test against live payer test environments, not just your own parser. Maintain a rejection tracking system that logs error codes and helps you identify patterns over time.
The 837 transaction set is a mature standard that has been refined over decades. It works reliably when implemented correctly, and it fails spectacularly when any assumption is left unvalidated. The difference between a clean implementation and a broken one usually comes down to whether you accounted for the edge cases that the base specification does not mention.
Gallery Edi 837 Implementation Guide
Complete Guide to EDI 837 Healthcare Claims | Dastify Solutions
837 Transaction Set Implementation Guide | PDF | Health Insurance Portability And Accountability ...
X12 EDI for Healthcare Developers: The 835/837/270/271 Transaction Guide You Actually Need
Healthcare EDI 835/837/277: The Developer's Guide to Claims Integration
X12 EDI for Healthcare Developers: The 835/837/270/271 Transaction Guide You Actually Need