
What actually happens when you walk into a home for an assessment
You go in with a clipboard, you look around, and you try to figure out which of the hundred things in that house could kill someone in the next six months. That is the gist of an Elderly Home Safety Assessment, though nobody who does this professionally uses that exact phrasing in casual conversation. We usually just call it a home safety eval or an OT home visit. Occupational therapists, geriatric care managers, and sometimes social workers do this work. I have done both, and I can tell you the difference between what the brochures say and what the job actually looks like. The process itself is straightforward enough. You spend forty-five minutes to two hours inside the residence. You walk every room. You note trip hazards, lighting levels, grab bar placement, stove safety, medication storage, the condition of walking aids, whether the bathroom has a non-slip surface, and whether the bedroom is on the main floor. You ask the resident or caregiver a bunch of questions about recent falls, dizziness, memory issues, and what daily tasks have become difficult. Then you compile a report with prioritized recommendations. That is the skeleton. The reality is messier.
The Elderly Home Safety Assessment checklist most people ignore
Here is the thing nobody puts in the intro pamphlet. The biggest risk factor in almost every home I have evaluated is not the loose rug or the step at the front door. It is the bathroom. Specifically, the transition from standing to sitting on the toilet and then back up again. Falls in that one three-foot sequence account for a disproportionate number of serious injuries. I spent three years watching people try to push themselves up from a standard-height toilet without any support and nearly slip every single time. The workaround is not always a grab bar. Sometimes it is a raised toilet seat with arms. Sometimes it is a simple transfer bench for the shower. You figure it out based on the person's actual strength, not the catalog picture. Another overlooked detail is night navigation. You will see a thousand assessments that completely skip the path from the bed to the bathroom after dark. People who wake up at 2 AM and shuffle to the toilet in the dark are walking into a minefield. The fix is usually cheap and stupidly effective: motion-sensor plug-in lights along that path. Not a nightlight in the ceiling. Actual pathway illumination. I had a client who fell twice in one month simply because she could not see the edge of a throw rug she had been stepping over for years. Motion lights cost about eighteen dollars each at any hardware store. This is the kind of intervention that changes everything and gets ignored because it sounds too simple.
How to actually do this assessment without wasting everyone's time
Start by asking the person to walk through their normal routine before you even pull out the checklist. Watch them get up from the couch, navigate to the kitchen, pour a glass of water, and return. Most evaluators skip this and go straight into pointing at things. That is a mistake. Watching the actual movement pattern reveals more in five minutes than two hours of ticking boxes. You will see limps, hesitation at thresholds, the way someone grips the wall without thinking about it, the small adjustments in balance that signal real instability. I learned this the hard way during my second year. I was doing a standard visual sweep of a living room and missed the fact that the woman was dragging her left foot slightly on every third step. She did not mention it. Nobody at the table mentioned it. I only caught it when she got up to get water and I followed her with my eyes instead of my notebook. That detail alone changed the entire recommendation plan. Bring a lux meter if you can. Light levels below seventy-five lux in common walking areas are a real problem for older adults, and most homes sit between thirty and fifty lux in those zones. A basic plug-in meter runs about thirty dollars. You measure the hallway, the stairs, the kitchen counter area, the bathroom. Record the numbers. This takes about twelve minutes total and adds objective data that caregivers and insurance reviewers actually take seriously. Verbal complaints about dim lighting get dismissed. Measured numbers do not.
Get the Full Details

Things that will surprise you if you do this work long enough
One counter-intuitive finding that comes up constantly is that removing throw rugs entirely is often the wrong call. Yes, unsecured rugs cause falls. But for some elderly people, the texture of a rug provides proprioceptive feedback that helps with balance. Smooth hardwood or tile can actually be more dangerous for certain individuals. The correct move is usually to secure the rug with double-sided tape or a non-slip pad underneath, not to yank it out. If the person has severe neuropathy in their feet, you remove the rug. If they have mild balance issues and normal sensation, you secure it. Context matters more than any generic rule. Another one: grab bars installed incorrectly are worse than having no grab bars at all. I have seen hundreds of poorly mounted bars in bathrooms. They get attached to drywall anchors instead of studs, and under even moderate weight they pull free. The person falls anyway, but now they also have a broken bone from the original fall and a second injury from falling onto the hardware or the floor. Every grab bar installation needs to go into a wall stud or use a proper toggle bolt rated for at least five hundred pounds of pull-out force. The cost of a bad installation is measured in hip fractures. It is not a metaphor.
The limitations that matter
This type of assessment has real boundaries, and you need to know them before you commit to doing this work or paying for it. A home safety eval cannot predict whether someone will fall tomorrow. It can reduce risk, sometimes significantly, but it does not eliminate it. Falls in older adults involve medical factors, medication side effects, cognitive decline, and environmental conditions interacting in ways no checklist can fully capture. An assessment might cut a household's fall risk by forty to sixty percent based on intervention studies, but that leaves a lot of residual risk. There is also the problem of compliance. You can recommend hospital beds, stairlifts, shower chairs, and medication organizers until you are blue in the face, and the family will still not install the ramp because it looks ugly on the porch. Or the person refusing help will cover the grab bar with a towel rack because they do not want to admit they need it. I once spent an hour trying to convince a seventy-eight-year-old man to install a handheld shower head. He did not install it. Six months later he fell in the tub and broke his wrist. He told me afterward that the grab bar I recommended was in the box in his closet and he had not opened it. You can do the assessment perfectly. You cannot control the outcome. A related limitation is that many assessments are one-time events. You visit, you write a report, you leave. But home safety is not static. A person's mobility changes. New medications get prescribed. Weight fluctuates. Furniture gets rearranged. A report written in January may be obsolete by March. The most useful assessments are part of a recurring review, ideally every six months or whenever there is a significant health change. If you are doing this professionally, build follow-up scheduling into the initial visit. If you are hiring someone, ask about it upfront.
What a real assessment report should contain
A proper Elderly Home Safety Assessment report has three sections. The first is findings, organized by room and by risk level. The second is prioritized recommendations with specific product types and installation guidance where relevant. The third is a short narrative summary for the family or care coordinator that explains the rationale in plain language. Too many reports I have read are just lists of items with no context. "Throw rug removed" means nothing without understanding which rug, why it mattered, and what replaced it. The narrative section is where you actually communicate. It is also the section most evaluators rush through or skip entirely. Cost estimates belong in the report too. A family deciding between spending five hundred dollars on grab bars and lighting upgrades or two thousand dollars on a stairlift needs to see those numbers in front of them, not buried in a footnote. I include a rough cost range for each recommendation, categorized as low, medium, or high. Low is under fifty dollars. Medium is fifty to three hundred. High is above three hundred. This helps families triage what to address first when money or willpower is limited.
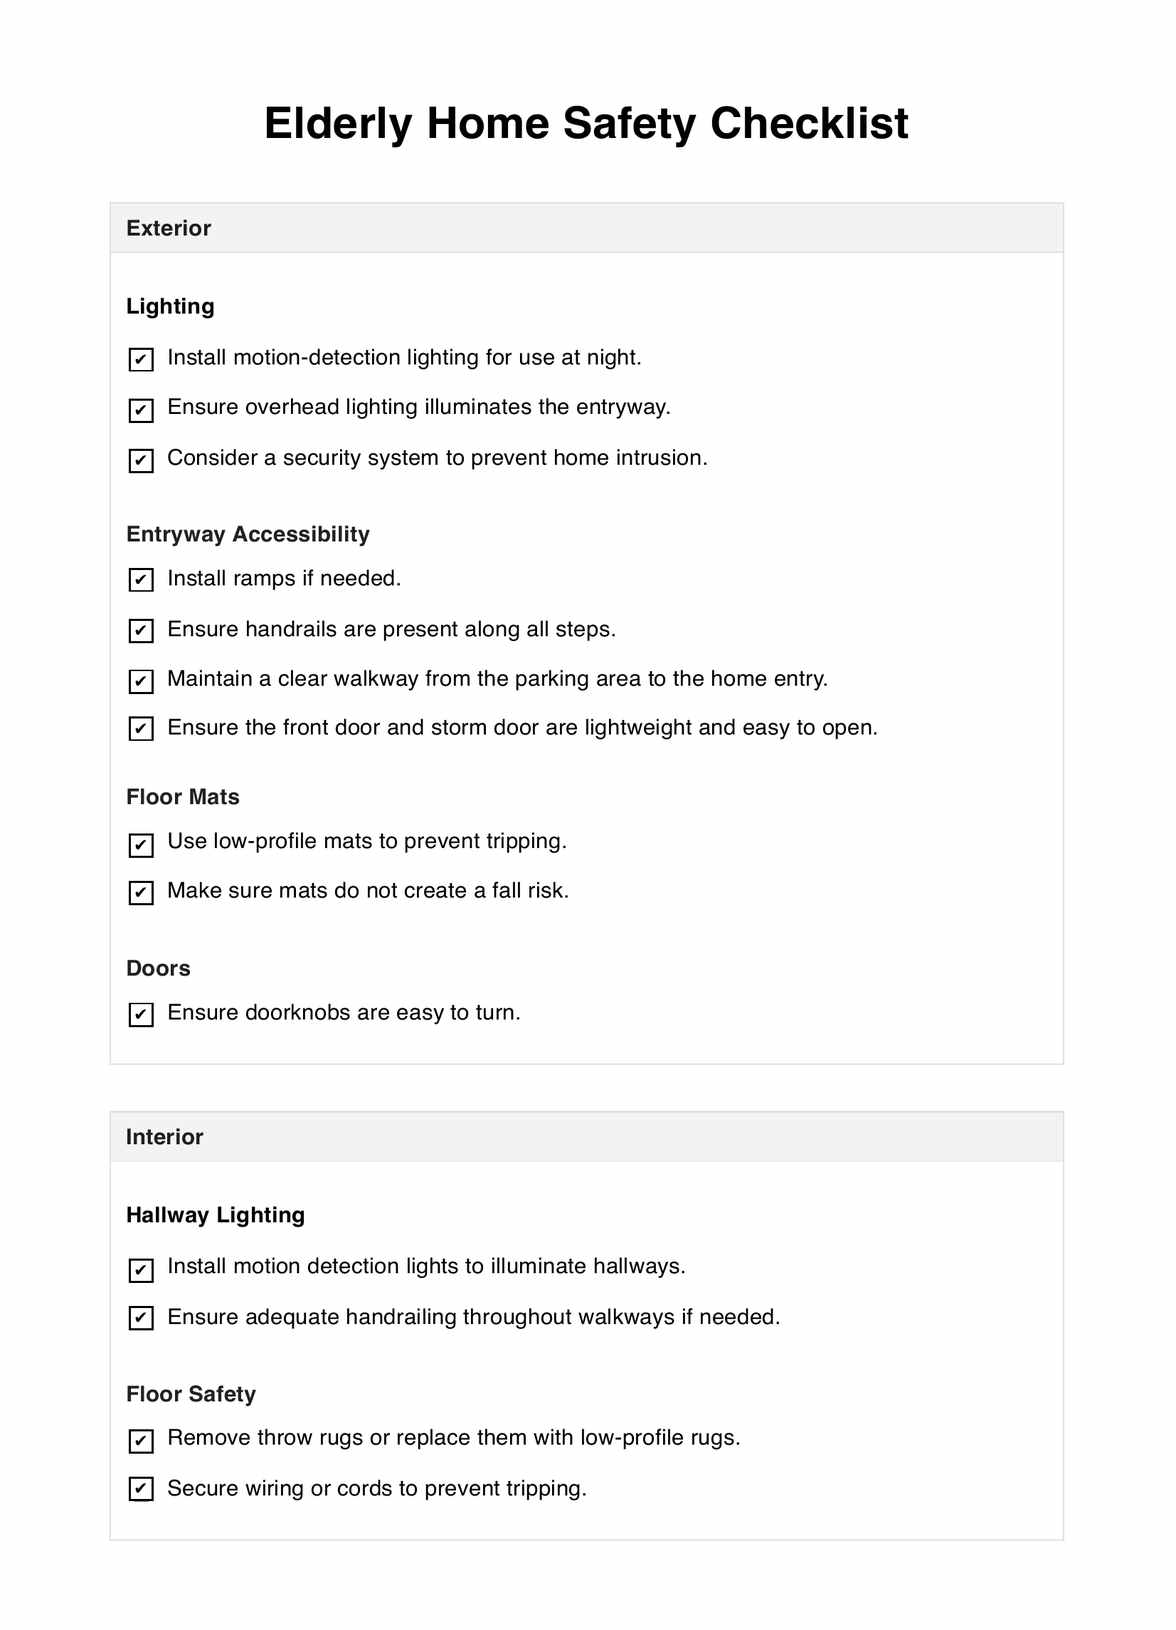
When to call in someone else
Not every home safety issue falls within the scope of a standard assessment. If you encounter significant structural problems, severe cognitive impairment where the person is a danger to themselves in ways a grab bar cannot address, or advanced mobility restrictions that require equipment like Hoyer lifts and stairchair lifts, you need to bring in specialists. Physical therapists for gait and balance evaluation. Geriatricians for medication review. Home modification contractors for structural changes. The assessor's job is to identify the problem and flag when it is beyond the scope of home safety interventions. Staying in your lane is better than giving advice you are not qualified to give. There is also the matter of documentation. If this assessment is for insurance purposes, for Medicaid waiver programs, or for legal guardianship proceedings, the report needs to meet specific formatting and credentialing requirements that vary by jurisdiction. A standard home safety eval done for a private family will not satisfy a state agency. Know which category you are working in before you start, because the depth of documentation required changes the time commitment from two hours to potentially half a day or more per case.
The practical toolkit
You do not need expensive equipment. A basic kit includes a clipboard or tablet with a checklist, a lux meter, a tape measure, a level for verifying grab bar installation angle, a flashlight for checking dark areas, and a camera for documenting conditions. Some people use a standardized tool like the HEAVEN or the HOME Safety Profile. Others build their own. I built mine over eight years and it is nowhere near as polished as the commercial versions, but it covers the scenarios I actually encounter. If you are starting out, pick an existing tool rather than writing from scratch. The evidence base behind validated instruments matters more than customizing your own format. The single most useful habit I developed is taking a photo of every hazard and noting its location in the report. Families respond to visuals. Telling someone their staircase is dangerous gets filtered out as background noise. Showing them a photo of the uneven step with an arrow pointing to it and the words "this is where you tripped last month" gets action. It is basic communication, not a trick, but it makes a measurable difference in follow-through rates.



