Understanding How Electroconvulsive Therapy Actually Works in Practice
ECT is a psychiatric procedure where a controlled electric current is passed through the brain to trigger a brief seizure. It sounds archaic if you're hearing about it for the first time, but modern ECT bears almost no resemblance to the horror stories from mid-century films. The patient is fully anesthetized, given a muscle relaxant, and monitored continuously throughout the procedure. What happens next is a carefully calibrated medical event, not something left to chance. The abbreviation ECT stands for electroconvulsive therapy. When you see Electroconvulsive Therapy Abbreviated Ect Involves on a forms or in research papers, it's simply referencing the same procedure. The shorthand exists because clinicians use it constantly and patients end up encountering it everywhere once they enter the system.
Electroconvulsive Therapy Abbreviated Ect Involves: The Procedure Breakdown
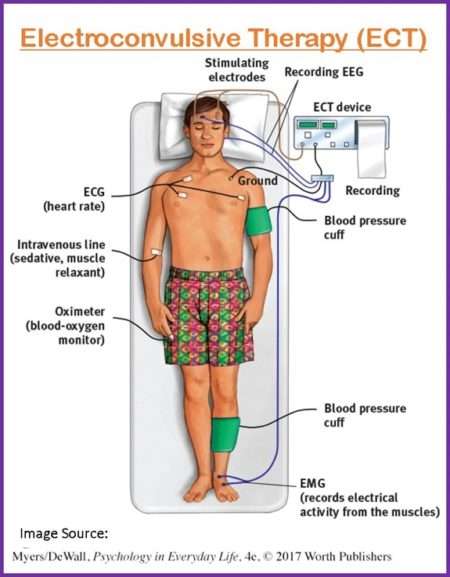
Here's what actually happens during a standard ECT session, from the moment the patient walks into the suite to the point they're cleared for discharge. First, an IV line is placed and anesthesia is administered—typically methohexital or propofol. Oxicom and a short-acting muscle relaxant like succinylcholine follow. The patient goes under within seconds. A Bite block is placed to protect the teeth, which matters more than people realize because the seizure activity can be vigorous before the muscle relaxant takes full effect. Electrode placement is where things diverge. The two main approaches are unilateral and bilateral. Unilateral places electrodes on one side of the head, usually the right side. Bilateral places them on both sides. Right unilateral is the more common choice today because it tends to produce fewer cognitive side effects. That doesn't mean it's free of them, but the difference is significant enough that most clinics default to this approach unless there's a specific reason not to.
The actual stimulus is delivered by a modified ECT device. The charge is calculated based on the patient's seizure threshold, which is determined during the first few treatments. You start low and titrate up. A typical acute course runs anywhere from six to twelve sessions, administered three times per week. Maintenance ECT can extend for months or even years after that, with sessions spaced further apart. During the seizure, which usually lasts between twenty and sixty seconds, the patient shows no external signs beyond what the anesthesia and muscle relaxant allow. There might be a slight twitch here or there. An EEG monitors the brain activity continuously, and the seizure duration is tracked precisely. If the seizure is too short—below about twenty-five seconds—you're looking at a subtherapeutic treatment. If it runs too long, above two or three minutes, that's a complication that requires intervention. After the seizure, the patient is placed in a recovery position and monitored until they wake up. Total time in the suite is roughly forty-five minutes to an hour. They go home the same day. No hospital stay required for standard cases.
Get the Full Details

I ran across a problem early in my time working with ECT protocols that I hadn't anticipated. A patient with a lower seizure threshold was consistently having seizures that terminated prematurely, around fifteen seconds, despite escalating the dose. The standard workaround was switching from right unilateral to bitemporal electrode placement, which typically produces a larger seizure volume. In that specific case it worked, but it came with a hit to memory function that the patient and family had to weigh against the benefit of adequate seizure duration. There's no perfect answer there, just tradeoffs.
What ECT Is Actually Used For
Major depressive disorder, particularly treatment-resistant cases, is the primary indication. Catatonia responds to ECT with remarkable speed—often within the first few sessions, sometimes just one or two. Bipolar disorder, both the depressive and manic poles, is another solid indication. Schizophrenia can be helped, especially when catatonic features are present or when adjunctive treatment is needed. One thing beginners often miss is that ECT doesn't work the way antidepressants do. It's not a chemical adjustment over weeks. The mechanism involves profound neurochemical and neuroplastic changes triggered by the seizure itself. We still don't fully understand the mechanism, but the clinical response is well-documented. Response rates for severe depression are in the eighty to ninety percent range. That's higher than most pharmaceutical options for the same population. The recall issues are real though. Short-term memory loss around the treatment period is nearly universal. Some patients report gaps that extend weeks or months backward. For most this resolves over time, but for a minority it persists. I've seen cases where patients couldn't recall events from several months before their treatment course, and in a handful it never fully came back. It's worth being honest about that with anyone considering the procedure.
Contraindications are relatively few but important. Raised intracranial pressure is a hard no. Recent myocardial infarction carries significant risk. Space-occupying lesions in the brain are another absolute contraindication. Relative concerns include certain cardiovascular conditions and glaucoma. A thorough medical workup before starting is non-negotiable. If ECT isn't appropriate or the patient can't tolerate it, transcranial magnetic stimulation is the closest alternative, though it's generally less effective for severe cases. Ketamine infusion has also emerged as a rapid-acting option for treatment-resistant depression, but the evidence base isn't as extensive as it is for ECT. Pharmacological optimization with combinations like lithium plus an SSRI, or adding atypical antipsychotics, remains the first line for most patients before anyone considers ECT. The procedure itself is straightforward once the logistics are sorted. Insurance coverage is typically available for approved indications. The main bottleneck isn't medical feasibility—it's access. Many regions have very few ECT-capable centers, and wait times can be significant. Finding a qualified psychiatrist and an anesthesiology team that works together smoothly makes a difference in outcomes, so don't treat that as a secondary concern.