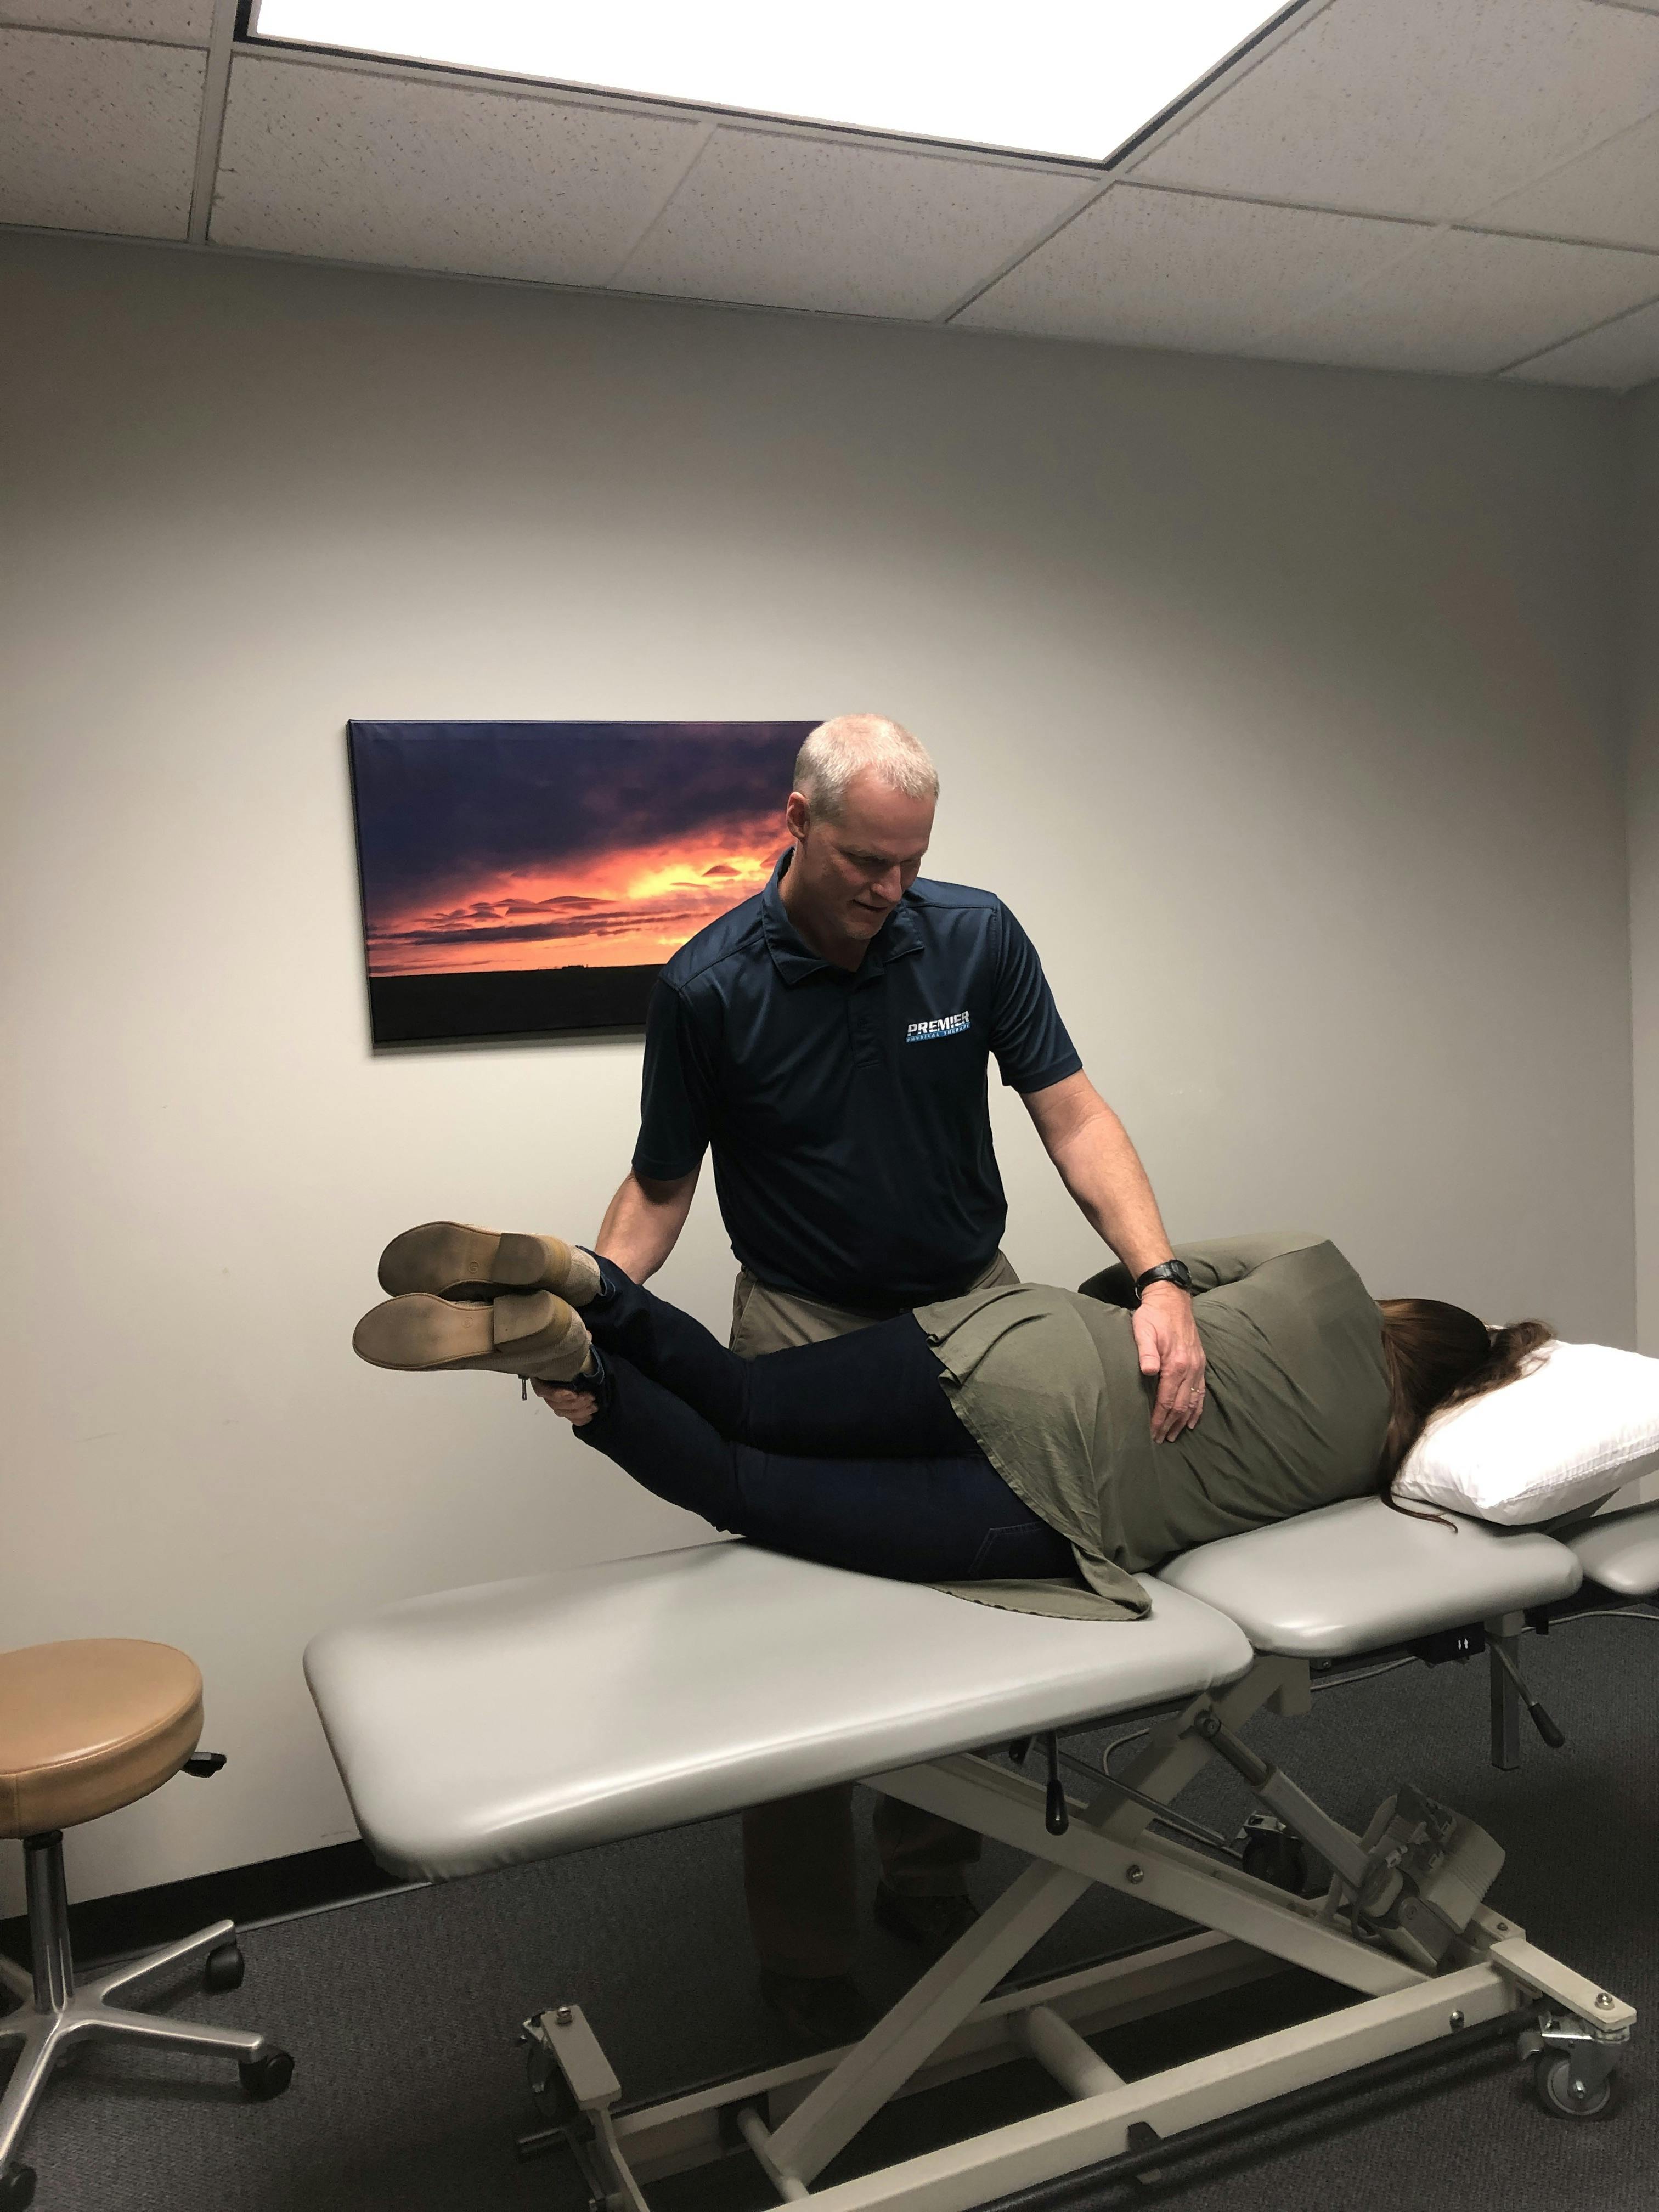
A Practical Guide to the Energy Technique in Physical Therapy
Most people who come across the Energy Technique in a physical therapy context are looking at a combination of applied movement principles and bioenergetic assessment methods. It is not one single standardized protocol. Different clinics teach variations. I have used several versions over the years and what follows is based on real clinical application, not textbook definitions. The core approach involves assessing tissue energy states through palpation and then applying directed movement or pressure to restore normal function. In practice, you press into a area of tissue until you feel a change in resistance, hold for 90 seconds, then release while guiding the patient through a specific range of motion. That 90-second hold is the key detail most beginners skip. They press, wait five seconds, release, and wonder why nothing changed. I once had a patient with chronic thoracic outlet symptoms where the standard nerve glides and stretching protocols failed completely for three sessions. The issue was not the scalenes or the pectoralis minor, which everyone focused on. The problem sat at the anterior tubercle of the C6 transverse process where the prevertebral fascia had become rigid and conducted zero energy feedback during palpation. I applied sustained pressure at that exact point for the full 90 seconds, then had the patient perform slow lateral flexion away from the affected side. By the third repetition the entire arm dropped into neutral without the usual guarding pattern. We only needed two more sessions over the next week. This is the kind of edge-case that does not appear in any training manual.
How to Perform the Basic Application
Start by having the patient positioned comfortably, usually supine for most techniques. Identify the target tissue zone through light palpation and note where the tissue feels dense or unyielding compared to surrounding areas. Apply medium-pressure contact with your fingers or thumb. The pressure should be firm enough to reach the fascial layer but not so hard that it causes guarding response. Maintain this pressure for 90 seconds without moving. Do not massage. Do not pump. Just hold still and wait for the tissue to soften. When you feel the resistance drop, which is usually noticeable after about 60 to 90 seconds, release the pressure slowly and guide the patient through the targeted movement pattern. Two to three repetitions of the movement is usually sufficient. More than that tends to re-trigger the protective response. Common mistakes include applying too much pressure from the start, which causes the patient to tense up and blocks the technique entirely. Another mistake is releasing too quickly after the hold. The transition from pressure to movement needs to be smooth, almost seamless, so the nervous system does not register a threat and contract the tissue again.
Limitations and When to Avoid This Approach
This technique does not work for acute inflammatory conditions, fractures, or areas with vascular compromise. I would never apply sustained pressure near a known deep vein thrombosis site, for instance. There was a case early in my career where a patient had undiagnosed peripheral arterial disease and the pressure application to the lower extremity tissue caused significant discomfort that required immediate cessation and referral. After that I always screen for vascular issues before proceeding. The technique also has a steep learning curve for the practitioner. You need developed palpation skills to distinguish between normal tissue density and pathological changes. This typically takes 6 to 12 months of consistent practice under supervision. Beginners often mistake normal anatomical variation for pathology and apply unnecessary pressure, which can worsen symptoms rather than improve them. If you are still early in your training, stick with more established methods like standard muscle energy techniques and gradual progression before incorporating the energy assessment component. For patients with fibromyalgia or widespread central sensitization, the pressure component can be counterproductive. The tissues respond to light touch with amplified pain signals. In those cases I switch to very superficial contact with no sustained pressure and focus on breathing coordination instead. The results are slower but they do not aggravate the condition.
Get the Full Details
Advanced Nuances That Separate Competent Practitioners From Beginners
One thing most guides do not mention is the importance of patient breathing during the hold phase. When the patient exhales fully and holds briefly, the vagal tone increases and the parasympathetic response allows deeper tissue release. I time the 90-second hold to begin on the patient's exhale and end just before their next inhale. This timing matters more than the absolute duration. A properly timed 60-second hold often outperforms a poorly timed 90-second hold. Another nuance is the direction of the release. The tissue does not simply relax uniformly. It releases along the path of least resistance, which usually follows the fascial lines. If you feel the tissue wanting to move in a specific direction during the hold, follow that direction rather than forcing a particular movement pattern. Fighting the tissue's natural release vector is a common reason for treatment failure in the first few sessions. The energy assessment portion also requires differentiation between sympathetic dominance and parasympathetic dominance states. A patient whose sympathetic system is highly activated will show different tissue responses compared to someone in a parasymphepathic dominant state. The assessment tells you which state the patient is in and adjusts your approach accordingly. Sympathetic-dominant patients need slower pressure application and longer holds. Parasympathetic-dominant patients respond faster but can overshoot into relaxation that compromises their postural support during movement.