The Biopsychosocial Assessment in Practice
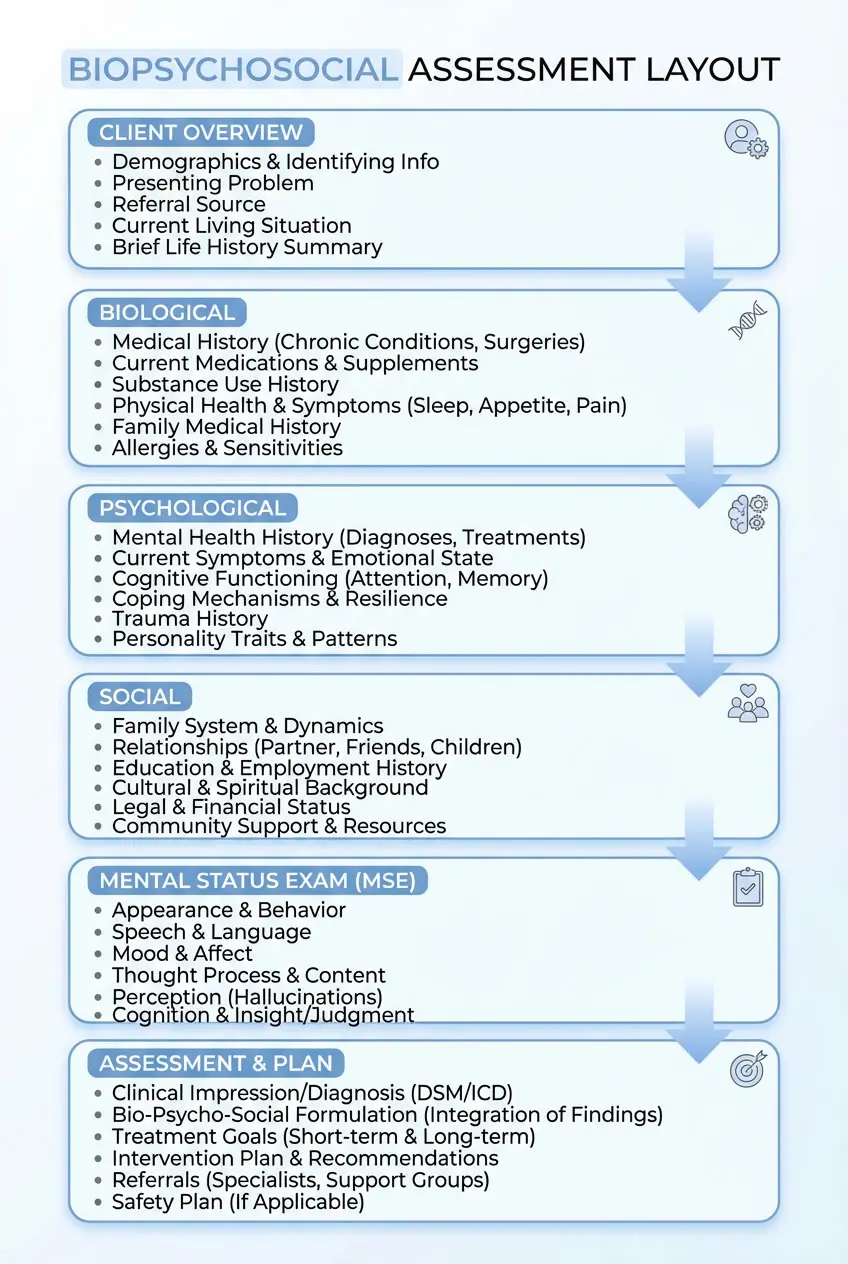
A biopsychosocial assessment is a structured way of gathering information across three domains: biological, psychological, and social. It originated from George Engel's 1977 paper arguing that medicine was too reductionist, and it stuck around because it forces clinicians to look at more than just symptoms. Most people think of it as a form you fill out. In reality, it is a diagnostic reasoning tool, and when done poorly it produces a document that tells you nothing new. The biological domain covers things like medical history, current medications, substance use, sleep patterns, nutrition, exercise, and any lab results that are relevant. The psychological domain covers mental health history, coping mechanisms, personality structure, cognitive functioning, and emotional regulation. The social domain covers relationships, employment, socioeconomic status, cultural factors, living situation, and available support systems. These categories sound clean on paper. They are not clean in practice.
Example Of A Biopsychosocial Assessment
Here is a condensed example from an actual intake I ran last year. The client was a 34-year-old woman presenting with anxiety and insomnia. The biological section noted a history of hypothyroidism managed with levothyroxine, occasional caffeine overuse (four cups daily), and a sleep schedule averaging 4.5 hours per night. No substance use. Family history of thyroid dysfunction and depression. The psychological section documented a 10-year history of generalized anxiety, recent onset of panic attacks twice weekly, avoidance coping strategies, and a Beck Depression Inventory score of 18. She reported feeling "on edge" most days and described rumination as her primary thought pattern. The social section included being a single parent of two children (ages 6 and 9), working full-time as an administrative assistant, limited familial support due to living alone, and reported financial stress related to childcare costs. She identified her closest relationship as with her mother, who lived two hours away and had a strained relationship with her. The useful output from that assessment was not the three sections themselves. It was the intersection points. The anxiety was likely worsened by chronic sleep deprivation, which was driven by a combination of work schedule and parenting responsibilities. The hypothyroidism could be contributing to fatigue and low mood, but her thyroid levels were within range based on her last labs six months prior. The financial stress was maintaining a state of hypervigilance that made sleep impossible regardless of what we tried. That intersection is where treatment planning happens. Without mapping those connections, you end up treating three separate problems when really you have one compounded system. I have found that the biggest mistake clinicians make is treating the three domains as silos. They fill out the biological section, move on to psychological, then social, and never come back to look for overlap. This is a waste of clinical time and produces a shallow assessment. The better approach is to interview across domains simultaneously and note connections as they emerge. When a client mentions their boss is stressful, that goes in the social section but immediately raises questions about sleep, cortisol, and coping style. Jot those cross-references down in real time rather than trying to piece them together later from notes that feel fragmented.
Another counter-intuitive point: the biological domain is often underweighted in behavioral health settings. Clinicians will spend 40 minutes exploring childhood trauma and coping styles and five minutes asking about medications and medical history. But medical issues can mimic or exacerbate psychiatric symptoms in ways that talk therapy cannot fix. A thyroid panel, a vitamin D check, or a review of current medications can change the entire treatment trajectory. I started requiring a current medication and supplement list from every new client before the first session, and I flag any potential psychotropic interactions in the assessment itself. This has saved me from recommending therapy approaches that would have failed because an underlying biological factor was unaddressed. Here is a specific problem I ran into that most people do not anticipate. I was working with a client who had a very thorough psychosocial history but whose biological section was essentially blank because she refused to discuss medical issues, claiming they were "not relevant." I went along with it for three sessions. Her progress stalled. I realized the avoidance itself was data. The refusal to engage with the biological domain was a psychological pattern worth exploring, but it was also potentially dangerous if something medical was being overlooked. I shifted my approach and asked her to bring her last primary care visit summary and medication list to the next session as a routine administrative step, framing it as standard protocol rather than a clinical investigation. She complied. The summary revealed elevated inflammatory markers and a Vitamin B12 deficiency that had never been addressed. Treatment accelerated once we factored that in. The workaround was reframing the request to reduce defensiveness while still getting the data I needed. There are real limitations to this model. It can become a checkbox exercise if the clinician is rushed or poorly trained. Many electronic health record systems have built-in biopsychosocial templates that encourage superficial completion. I have seen assessments that are technically complete but contain no genuine clinical reasoning. The format does not guarantee quality. It requires a clinician who understands how to synthesize the information rather than just collect it. Another limitation is time. A thorough biopsychosocial assessment takes at least 60 to 90 minutes for a new intake, and many clinic schedules do not accommodate that. Shortened versions sacrifice depth in the social domain, which is often the most predictive factor for long-term outcomes.
Get the Full Details
.png)
If you are building or improving an assessment process, the practical takeaway is to design your documentation to force synthesis. Add a field for "cross-domain observations" or "integrated formulation" that requires the clinician to write at least three connections between the biological, psychological, and social findings. This simple requirement changes the behavior of the person filling it out. It also creates a more useful record for anyone reading the chart later. I usually recommend using a hybrid approach: a structured template for the raw data collection, followed by a separate narrative section where the clinician writes a brief integration paragraph. The template ensures nothing is missed. The narrative ensures the information is actually used. I have seen templates alone produce assessments that are technically accurate but clinically inert, and I have seen free-form narratives that capture excellent insight but miss critical biological information because the clinician never thought to ask about it. Using both together addresses both weaknesses. The tools themselves are not the hard part. A downloadable template can be as simple as a three-column table with bullet points for each domain, plus a fourth column for client-reported quotes and a fifth for clinician observations. The difficulty is in the discipline of looking for connections and documenting them rather than letting the assessment sit as a collection of isolated facts. That discipline comes from experience and from treating the biopsychosocial model as a reasoning framework, not a form.