
Understanding the Psychosocial Assessment
A psychosocial assessment is a structured evaluation that looks at how a person's mental health and social environment interact. It's commonly used in clinical psychology, social work, healthcare, and legal settings. The purpose is to understand the whole person — not just symptoms, but living conditions, relationships, employment, substance use, trauma history, and coping mechanisms. Most professionals use a combination of standardized tools, clinical interviews, and collateral information from family or case files. The result is a report that guides treatment planning, risk assessment, or eligibility decisions for services.
Example Of A Psychosocial Assessment
Here's what a real assessment looks like when put into practice. I sat down with a 34-year-old male client who had been referred for a community mental health intake. He presented with chronic depression and a history of substance use. The assessment took about 90 minutes and followed a standard biopsychosocial framework. The format broke down into several sections: Presenting Problem: The client reported persistent low mood for approximately two years, worsening over the past six months. He described difficulty sleeping, loss of appetite, and a lack of motivation to attend work. His wife had filed for separation three months prior.
Psychiatric History: No prior hospitalizations. Treated as an outpatient since 2019 with sertraline, dosed at 100mg daily. Adherence was sporadic — the client admitted to missing doses regularly. No history of suicide attempts, but he disclosed passive suicidal ideation without a plan. Substance Use History: Alcohol use disorder, moderate severity. Approximately seven to ten drinks per week, mostly on weekends. No illicit drug use reported. Last use was three days before the interview. Social History: Born and raised in the area. Graduated high school, completed two years of community college before dropping out due to financial constraints. Worked as a warehouse supervisor until quitting six months ago. Currently receiving unemployment benefits. Lived with his wife for eight years; they have no children. His relationship with his parents is strained — he speaks to his mother monthly but has not spoken to his father in four years.
Coping and Strengths: The client reported engaging in regular exercise previously but had stopped six months ago. He identified his religious faith as a source of strength and attended church weekly before the separation. He had no close friends but maintained a decent relationship with his sister. Risk Assessment: No active suicidality or homicidality. Low to moderate risk for self-harm given the combination of depression, recent relationship loss, and social isolation. Substance use posed a moderate risk factor for relapse under stress. Diagnostic Impression: Based on DSM-5-TR criteria, the clinical picture was consistent with Major Depressive Disorder, recurrent, moderate. Alcohol Use Disorder, moderate, in early remission.
Get the Full Details
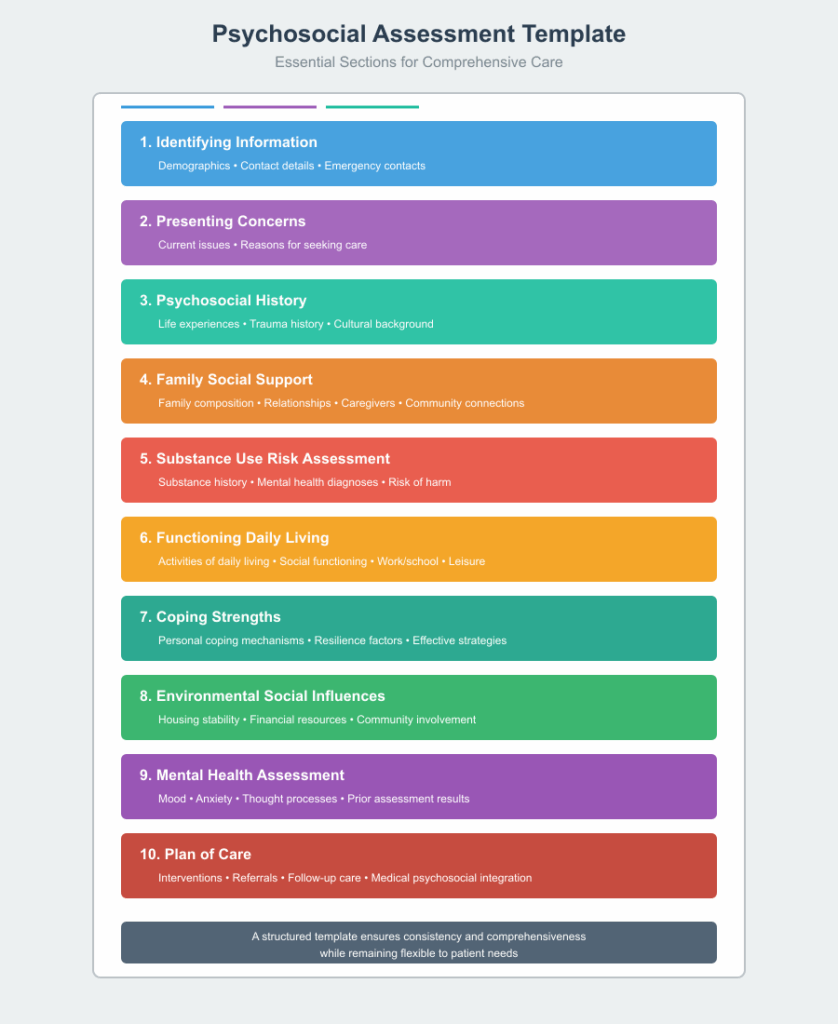
Treatment Recommendations: Continue sertraline with a psychiatry follow-up for dose adjustment. Refer to individual CBT therapy, twice weekly. Consider a substance use support group. Encourage re-engagement with exercise and social activities. Schedule a follow-up assessment in 30 days. That's a typical flow. It's not complicated, but it requires careful attention to detail. Missing even one section can create gaps in the treatment plan.
How to Conduct a Psychosocial Assessment
I've done hundreds of these across different settings — inpatient units, community clinics, forensic evaluations, and private practice. The core methodology is fairly consistent, but the approach shifts depending on the context. Here's how I break it down. Step One: Gather Collateral Information Before the Interview Most new clinicians jump straight into the clinical interview. That's a mistake. Spend at least 20 to 30 minutes reviewing existing records, past assessments, medication lists, and any prior treatment notes. This gives you context and helps you identify areas that need deeper exploration. In my experience, about 40% of the critical information in an assessment is already documented somewhere — you just need to know where to look.
Step Two: Structure the Clinical Interview The interview is the backbone of the assessment. I typically use a semi-structured format that covers the following domains: 1. Identifying information and reason for referral
2. Presenting symptoms and their duration 3. Psychiatric history (hospitalizations, treatments, medications) 4. Medical history and current health status
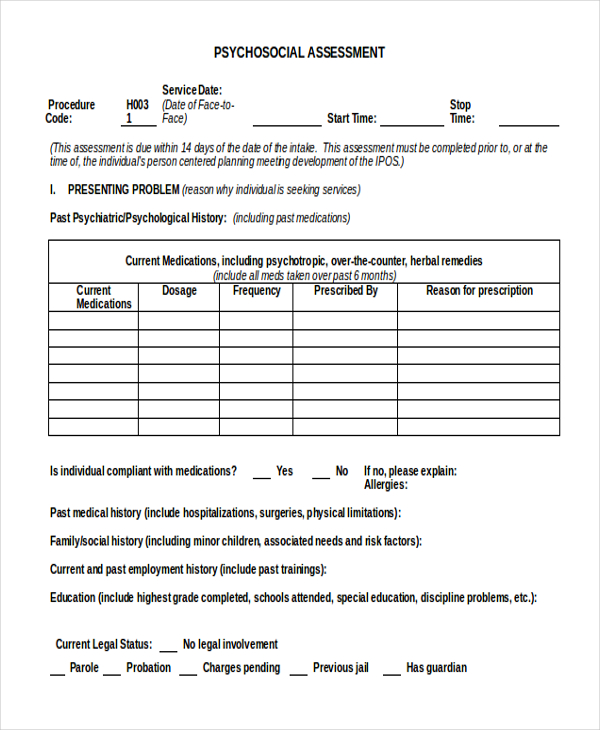
5. Substance use history 6. Developmental and family history 7. Educational and occupational history
8. Social and relationship functioning 9. Legal and forensic history, if relevant 10. Strengths and coping strategies
11. Risk assessment (suicide, violence, self-neglect) 12. Mental status examination findings Don't treat this as a checklist to rush through. Each domain informs the others. A gap in employment history might connect to a traumatic event disclosed later. A vague response about relationships might signal intimate partner violence that you need to explore carefully.
Step Three: Document Your Findings Writing the report is where most people struggle. The key is to be specific, objective, and concise. Avoid vague language like "the client appears to have issues with relationships." Instead, write "The client reports having no close friends and describes a pattern of conflict in romantic relationships lasting over three years." Use diagnostic terminology correctly. If you're diagnosing Major Depressive Disorder, cite the specific DSM-5-TR criteria met. Most institutional templates require this level of precision, and it protects you legally if the assessment is ever reviewed.

Step Four: Formulate Recommendations Recommendations should be directly tied to the findings. If the client has mild depression and strong social support, recommending intensive residential treatment is inappropriate. If the client has a severe substance use disorder and a history of relapse, suggesting only a single support group session is insufficient. I usually recommend two to five specific actions. Too many recommendations dilute the usefulness of the report. Too few and you haven't provided adequate guidance.
Common Mistakes to Avoid
I see the same errors repeatedly, especially among trainees and people new to this work. Over-relying on self-report. Clients will minimize or exaggerate symptoms depending on their motivation. A client seeking disability benefits may amplify symptoms. A client facing custody evaluation may minimize them. Cross-check self-report with collateral sources whenever possible. Ignoring cultural context. A client's presentation of distress is shaped by their cultural background. Somatic complaints may be the primary expression of depression in some cultures. Direct eye contact may be disrespectful, not evasive. These nuances matter and they're easy to miss if you're operating from a narrow clinical framework.
Using outdated diagnostic criteria. Make sure you're working from the DSM-5-TR or ICD-11, depending on your jurisdiction. The differences matter, especially for conditions like PTSD, where the DSM-5-TR added a dissociative specifier. Failing to assess risk adequately. This is the most dangerous oversight. Every assessment must include a thorough risk evaluation. If a client discloses suicidal ideation, document it explicitly — including the presence or absence of a plan, intent, means, and protective factors. Vague risk assessments are a liability.
Tools and Standardized Instruments
You don't need to reinvent the wheel. Several validated instruments can supplement your clinical judgment and add objectivity to your assessment. The Mini-International Neuropsychiatric Interview (MINI) is a brief structured diagnostic interview that covers the major DSM and ICD disorders. It takes about 15 to 20 minutes and is freely available for clinical and research use. The Composite International Diagnostic Interview (CIDI) is more comprehensive and used extensively in epidemiological research. It's longer — roughly 45 minutes to an hour — but provides detailed diagnostic information.

For personality assessment, the Millon Clinical Multiaxial Inventory (MCMI-IV) is widely used in clinical settings. The Personality Assessment Inventory (PAI) is another solid option, taking about 45 minutes to complete. Suicide risk tools like the Columbia-Suicide Severity Rating Scale (C-SSRS) are evidence-based and take less than five minutes. I recommend administering this with every client, regardless of presenting concern. Substance use screening can be done efficiently with the Alcohol Use Disorders Identification Test (AUDIT) and the DASS-21 for depression, anxiety, and stress.
These tools don't replace clinical judgment. They supplement it. A high score on a depression inventory doesn't equal a diagnosis. Context matters.
A Realistic Edge Case I Handled
Here's a situation that caught me off guard during a forensic psychosocial assessment. The client was a 41-year-old male evaluated for competency to stand trial on fraud charges. On paper, his presentation was straightforward — he was cooperative, oriented, and answered questions appropriately. Standard cognitive screening was intact. But something felt off. His responses were too polished, too rehearsed. I kept returning to the same questions and getting the same answers, word for word. I brought in a collateral interview with his public defender, who mentioned that the client had been studying legal terminology in his cell and had been practicing his responses with other inmates. The workaround was to switch to unstructured, open-ended questioning and embed validity indicators throughout the interview. I asked him to describe his morning routine in detail, then asked again twenty minutes later after a distraction task. The answers differed significantly. I also administered the Structured Inventory of Malingered Symptomatology (SIMS), which came back in the clinically significant range for feigning cognitive difficulties.
The final assessment concluded that the client was malingering cognitive impairment and was competent to stand trial. Without that deeper probing, I would have produced a superficial and potentially misleading report. This is why rigid adherence to a template can fail you — human behavior doesn't always fit neatly into the boxes you set up.

Limitations and When It Doesn't Work
Let's be honest about where psychosocial assessments fall short. They are snapshots in time. A client's condition can change significantly between the assessment and the actual intervention. I've seen clients present as stable during an assessment and decompensate within two weeks. Don't treat the assessment as a definitive prediction of future functioning. They are resource-intensive. A thorough assessment can take two to three hours of direct contact time, plus additional time for record review and report writing. In high-volume settings like community mental health centers, that's often impossible. Clinicians sometimes compress the process into a single 45-minute session, which sacrifices depth for efficiency. That's a trade-off you need to be aware of.
They are subjective. Despite standardized tools, the assessment is still filtered through the clinician's interpretation. Two qualified clinicians can arrive at different diagnostic impressions from the same client. This isn't necessarily a flaw — it reflects the complexity of human behavior — but it's important to acknowledge. If you're working in a setting where a full psychosocial assessment isn't feasible, consider a brief mental status exam combined with a triage risk assessment. These are faster and still provide essential information. The PHQ-9 for depression screening and the GAD-7 for anxiety screening are valid alternatives when time is limited. For situations involving legal or forensic concerns, a full assessment is non-negotiable. Abbreviated versions in those contexts can have serious consequences.
Final Notes
The psychosocial assessment is one of the most important tools in clinical practice. It shapes treatment, influences legal outcomes, and determines access to services. Treat it with the seriousness it deserves. Don't rush through it. Don't treat it as a paperwork exercise. Listen carefully, document thoroughly, and make sure your recommendations are actionable and appropriate to the client's specific situation. If you're looking for templates or structured forms, most state health departments and professional organizations like the American Psychological Association and the National Association of Social Workers provide free downloadable templates. The SAMHSA website also has resource guides for conducting psychosocial evaluations in various settings.
The skill comes with practice. The first dozen assessments will feel clunky and incomplete. By the fiftieth, you'll have a rhythm. The key is to stay curious, stay methodical, and never stop paying attention to the details.
