Getting A SWOT Analysis To Actually Mean Something In Healthcare
I spent three years watching clinic administrators do SWOT analyses that amounted to nothing more than a group brainstorm on a whiteboard before lunch. They'd list "good doctors" as a strength and "budget cuts" as a threat, then file it away. The exercise is fine in theory, but in healthcare it falls apart fast unless you know what you're actually measuring. Here's how I got it to work without wasting everyone's time. The first problem most people hit is that healthcare data lives in terrible places. Your strengths and weaknesses aren't going to come from a dashboard. You'll need to pull them from actual operational data. For a mid-size clinic or a hospital department, here's what a usable process looks like.
How To Run A Real SWOT In A Clinical Setting
Pick a single unit or service line first. I recommend starting with something contained like an ambulatory surgery center, an urgent care location, or a specific specialty department. Don't try to SWOT the entire hospital system. That produces noise, not signal. Define the scope in one sentence. If you can't write it on a sticky note, it's too broad. Gather internal data for strengths and weaknesses. Pull the last 12 to 24 months of operational metrics. I usually ask for these specific data points from whatever EHR or billing system the facility uses: patient volume trends, no-show and cancellation rates, average revenue per encounter, staff turnover by department, provider burnout survey scores, patient satisfaction percentiles from Press Ganey or similar tools, length of stay averages, readmission rates for the relevant population, and supply cost variance. That last one matters more than people think. If your OR supplies cost 18 percent above regional benchmarks, that's a concrete weakness, not a vague complaint. For external factors, you don't need a fancy consulting report. Look at three things: local competitor moves over the past two years, payer mix shifts in your zip codes, and state-level regulatory changes affecting your service type. The HHS website and your state's department of health publications list these. CMS publishes utilization and quality data by region. Cross-reference that with your own demographics and you'll see where threats and opportunities actually sit.
Here's the part people skip and regret later. Don't just fill the four quadrants. Force every item onto a 1 to 5 impact scale and a 1 to 5 likelihood or probability scale. Internal items get likelihood ratings from 0 to 5 based on historical consistency. External items get likelihood based on how likely a change is within your planning window, usually 12 to 24 months. This turns the SWOT from a decorative list into something you can actually prioritize.
Get the Full Details

Examples Of Swot Analysis In Healthcare
Let me walk through two real examples from my experience rather than making up fictional ones. The first was a 40-bed community hospital in the Midwest that wanted to evaluate whether to expand their cardiology services. Strengths they identified included a long waiting list for elective cardiac procedures, which converted directly into revenue when slots opened. Their cardiology attendings had national speaking profiles, which helped with marketing. They had a dedicated cardiac rehab program with 78 percent completion rates, well above the regional average. The weakness was stark: their cardiologists were aging out, and recruitment pipelines produced fewer than two qualified applicants per open position over a three-year span. Their telemetry staffing ratio was 1 nurse to 6 patients during nights, which passed state minimums but was a strain during surges. External threats included a nearby academic medical center opening a new heart hub two years prior, pulling their highest-acuity cases. Payer contracts were shifting toward value-based models that penalized readmissions, and this hospital's 30-day readmission rate for heart failure sat at 22 percent, meaning they were already at risk of financial penalties. An opportunity was the passing of a state Medicaid expansion amendment that added coverage for 14,000 residents in their catchment area within six months. Another opportunity was that remote monitoring technology for heart failure had dropped in cost by about 40 percent since 2021, making a proactive care model cheaper to implement.
The second example was an outpatient orthopedic clinic chain evaluating a new robotic-assisted surgery program. Their strength was that attending surgeons had already completed fellowships in robotic techniques, so training costs were minimal. They also had strong preoperative compliance scores, meaning patients showed up prepared and surgical delays were low. Their weakness was that they leased their imaging equipment, and lease payments consumed roughly 9 percent of operating margin. A threat was the dominant insurer in the market announcing they would only reimburse robotic procedures at the same rate as open surgery for the next two years, which would make the economics of the program impossible at current volumes. The opportunity was a demographic shift toward a younger, active population in the suburban counties around two new locations they were considering. What these examples show is that the SWOT format itself is boring. The value comes from forcing specificity. Vague entries like "strong leadership" or "rising costs" are useless. "Attending physician retention rate of 91 percent over 18 months" tells you something. "Supply chain costs rose 12 percent year over year due to single-source vendor dependency" tells you exactly what to fix.
Common Pitfalls I've Seen Destroy These Analyses
The biggest mistake is treating all four quadrants as equally important. In practice, two or three items will drive 80 percent of your decisions. Everything else is background. I usually tell teams to pick the top three from each quadrant and then cross-reference them. When a strength directly mitigates a threat, that's a strategic priority. When a weakness amplifies an opportunity, that's a vulnerability worth addressing immediately. Another pitfall is ignoring the time horizon. Healthcare changes slowly compared to tech, but regulatory and payer shifts can happen overnight. A threat that seems unlikely today can become real within a quarter if a state legislature acts. I always separate near-term factors from longer-term ones. Near-term means 0 to 18 months. Longer-term means 18 to 36 months. This prevents your plan from looking like wishful thinking when something materializes faster than expected. There's also the problem of self-assessment bias. Clinicians tend to overstate strengths and understate weaknesses because admitting operational flaws feels personal. I've handled this by having finance or operations staff prepare the data portion before the clinical team discusses it. When the numbers are on the table, the conversation changes from defensive to analytical. It takes about five minutes to explain this framing, and it saves hours of circular debate later.

What SWOT Doesn't Do Well In Healthcare
SWOT is blunt. It doesn't tell you how to allocate limited capital across competing initiatives. It won't account for the interplay between staff morale and patient outcomes beyond a vague connection. It also doesn't capture qualitative nuances like physician culture or patient trust, which are often the real drivers of success or failure in healthcare. For those, you need supplementary tools like root cause analysis, lean process mapping, or structured stakeholder interviews. If your organization has complex interdependencies, like a hospital network with multiple service lines sharing staff and resources, SWOT becomes messy because a weakness in one area may be irrelevant in another. In those cases, I recommend pairing SWOT with a simple decision matrix that weights each factor by financial impact and strategic alignment. That takes maybe an extra hour and makes the output far more actionable. I once worked with a rural health system where the SWOT revealed a glaring opportunity in telehealth expansion, but the weakness was nonexistent broadband infrastructure in their service area. The analysis correctly identified the gap, but the fix wasn't on the SWOT. It required partnering with a local ISP and applying for FCC rural broadband grants. The SWOT pointed at the problem. The workaround required a completely different skill set. That's worth remembering. A good SWOT tells you where to look, not what to do next.
A Practical Shortcut That Actually Works
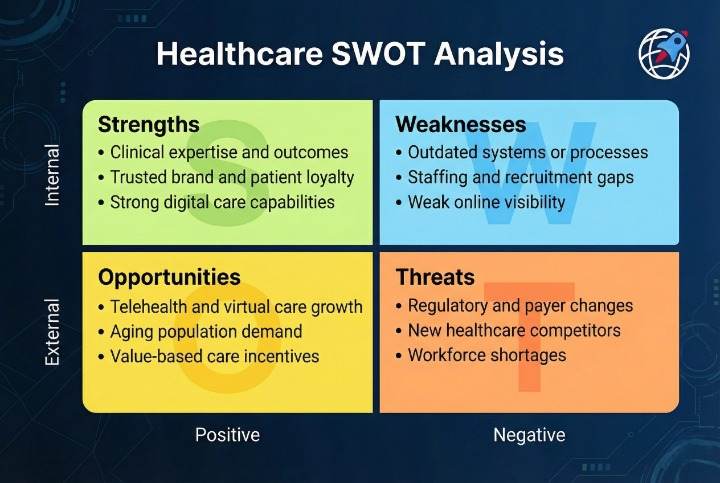
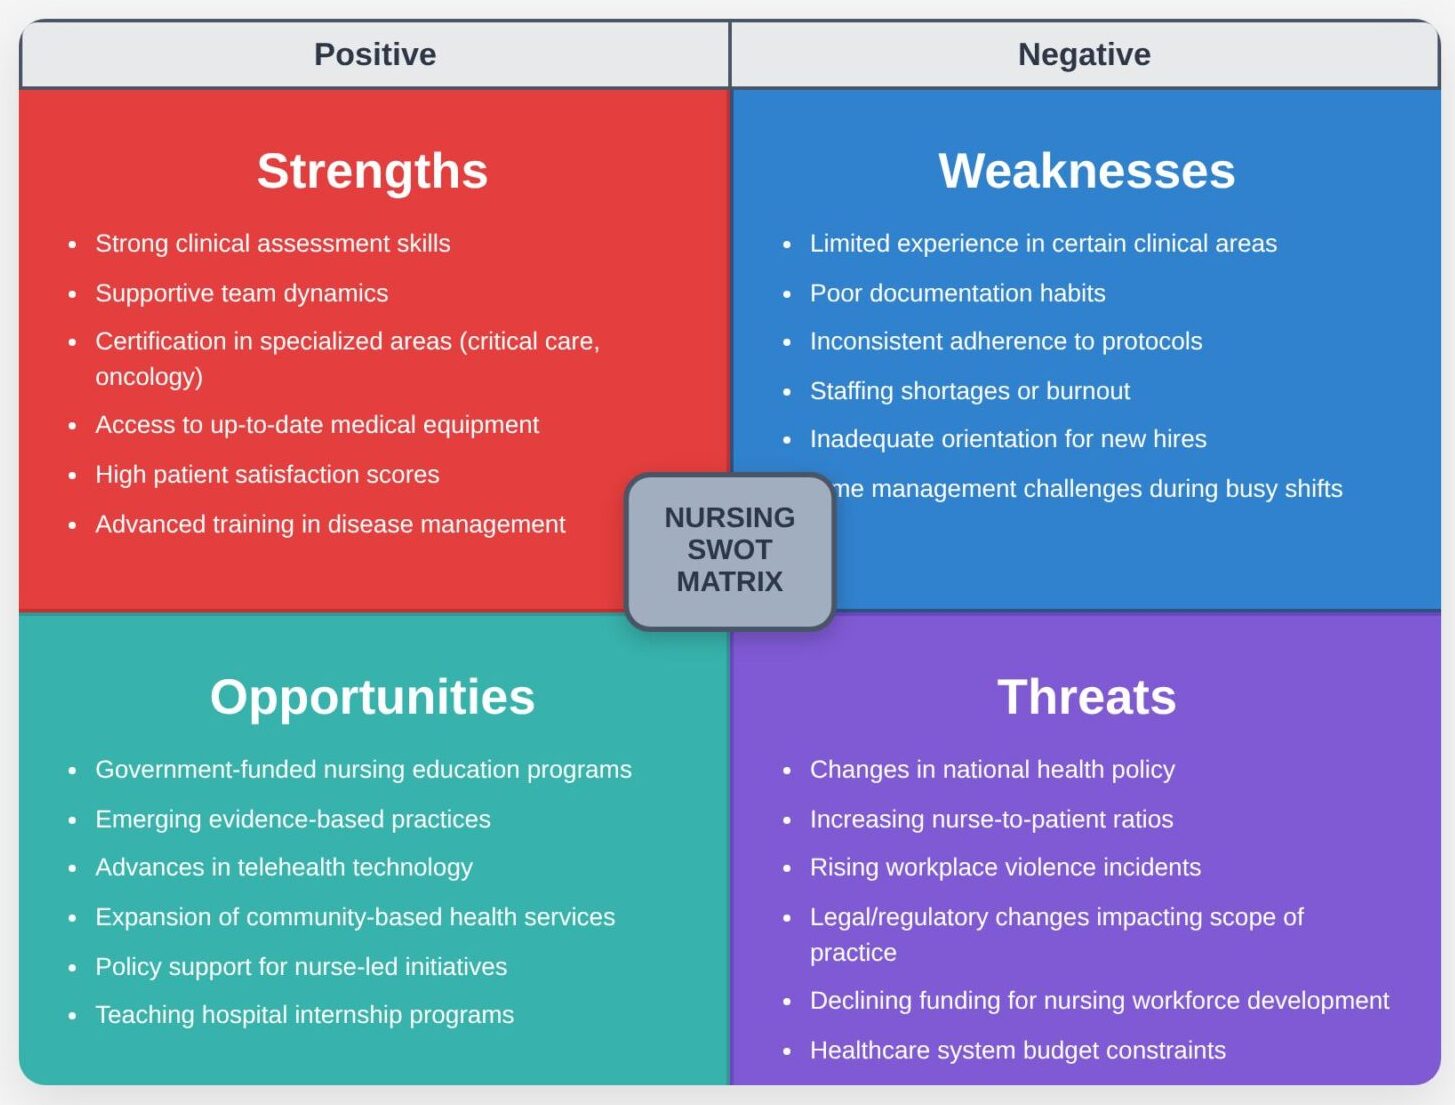
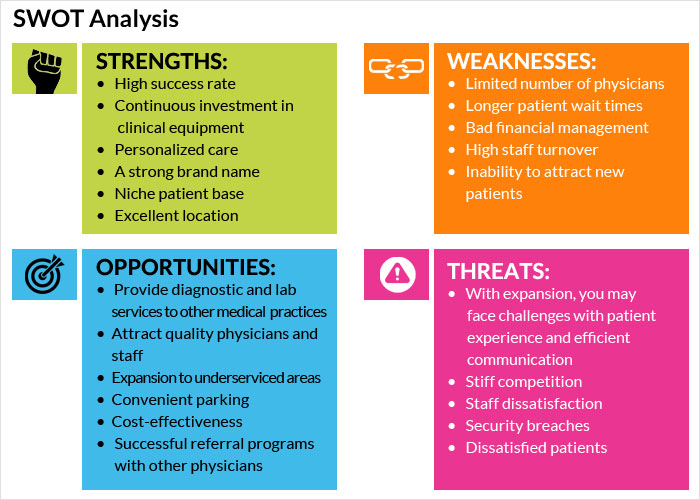
When you need to move fast, here's a condensed version I use when executive teams don't have time for a full session. Take your top five internal factors and top five external factors. Put them in a 2x2 matrix labeled "Advantage" and "Disadvantage" on one axis, and "Internal" and "External" on the other. Rate each item on impact from 1 to 5. Then multiply impact by probability. The resulting scores rank your factors objectively. The top three by score become your action list. This typically takes 45 minutes to an hour for a focused team, compared to the usual half-day retreat that produces nothing memorable. The key is discipline. Stick to measurable factors where possible. Flag anything you can't measure and note why. Don't pretend a gut feeling is data. The people who do this end up with a document that looks good in a boardroom presentation but falls apart the moment someone asks for proof. If you want a template to start from, many health information management associations publish free SWOT frameworks adapted for clinical settings. The American Hospital Association and American Medical Association both have generic versions you can adapt. Just remember to replace every generic box with something specific to your facility's actual data before you present it to anyone who matters.