Reading the Anterior Surface of the Heart
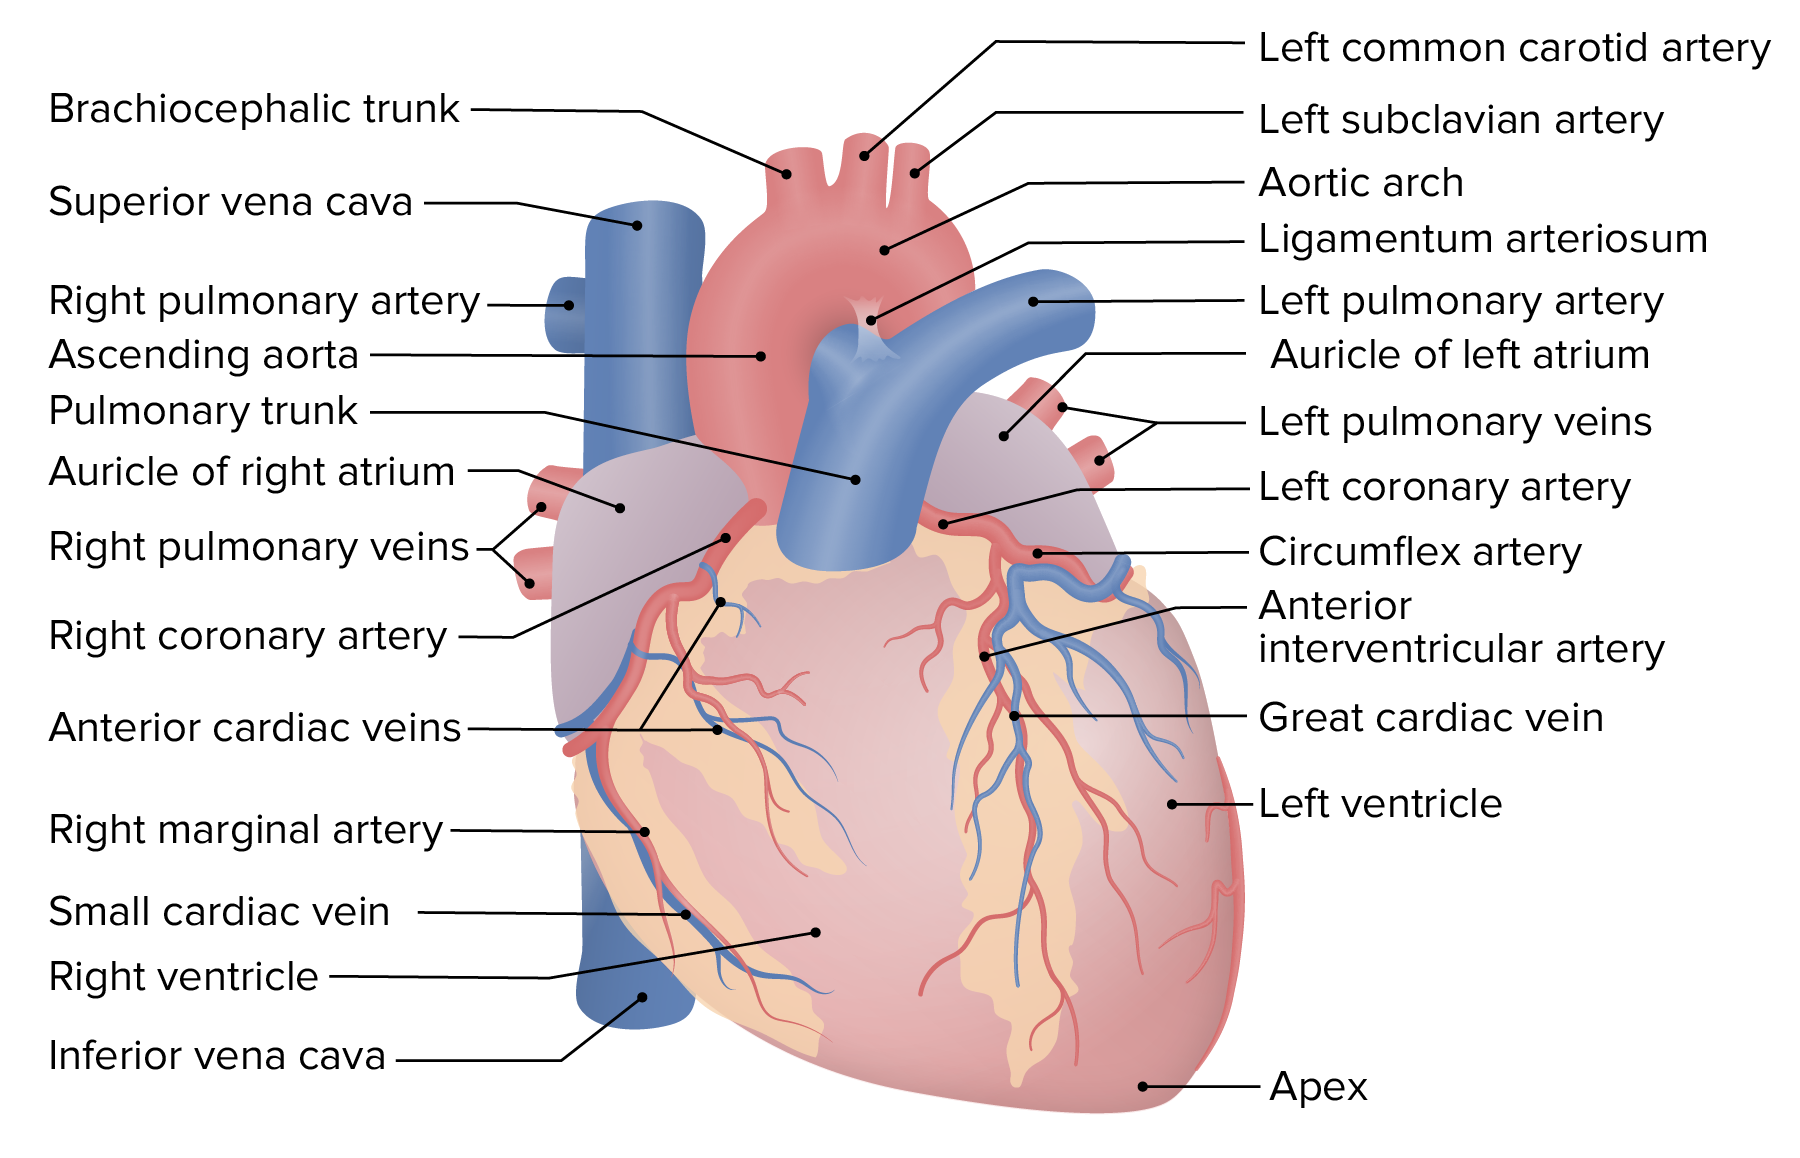
Most anatomy diagrams you see online are misleading because they show the heart sitting perfectly symmetric in the chest. That is not how it actually looks during surgery or when you are working with a real specimen. The anterior view reveals a heart that is rotated, tilted, and built differently than every textbook illustration suggests. Here is how to actually navigate it. From the front, the heart presents mostly the right ventricle. That single fact changes everything about how you interpret the surface landmarks. The left ventricle contributes only a small sliver on the left lateral margin, which is why palpating the apex beat requires understanding where that chamber actually sits underneath the rib cage rather than trusting the diagram. The coronary sulcus runs horizontally around the heart and marks the boundary between the atria above and the ventricles below. From the anterior perspective, it appears as a shallow groove filled with adipose tissue and the coronary vessels. It is easy to mistake the atrioventricular groove for something more significant than it is. Do not overcomplicate it.
Key Landmarks on the Anterior Surface
The right ventricle occupies the majority of the anterior surface. It is thin-walled compared to the left ventricle and forms the bulk of what you are looking at. The left ventricle runs along the left border and contributes to the cardiac apex. When studying dissections or surgical approaches, confusing which ventricle you are viewing is the most common beginner error and it happens because both chambers sit in the same anterior plane. The interventricular sulci are your primary guides. The anterior interventricular sulcus, also called the anterior longitudinal sulcus, runs vertically and marks the external division between the two ventricles. It contains the anterior interventricular artery, a branch of the left coronary artery. This vessel is clinically significant because occlusion here causes anterior wall myocardial infarctions. The sulcus itself is often filled with fat, which can obscure its course in older specimens or patients with higher body mass. The cardiac apex points inferiorly, anteriorly, and to the left. It is formed exclusively by the left ventricle. The apex beat corresponds to this point and is palpable in the fifth intercostal space at or just medial to the midclavicular line in most adults. This landmark matters because central venous catheterization and certain surgical approaches reference it.
Coronary Vessels as Surface Markers
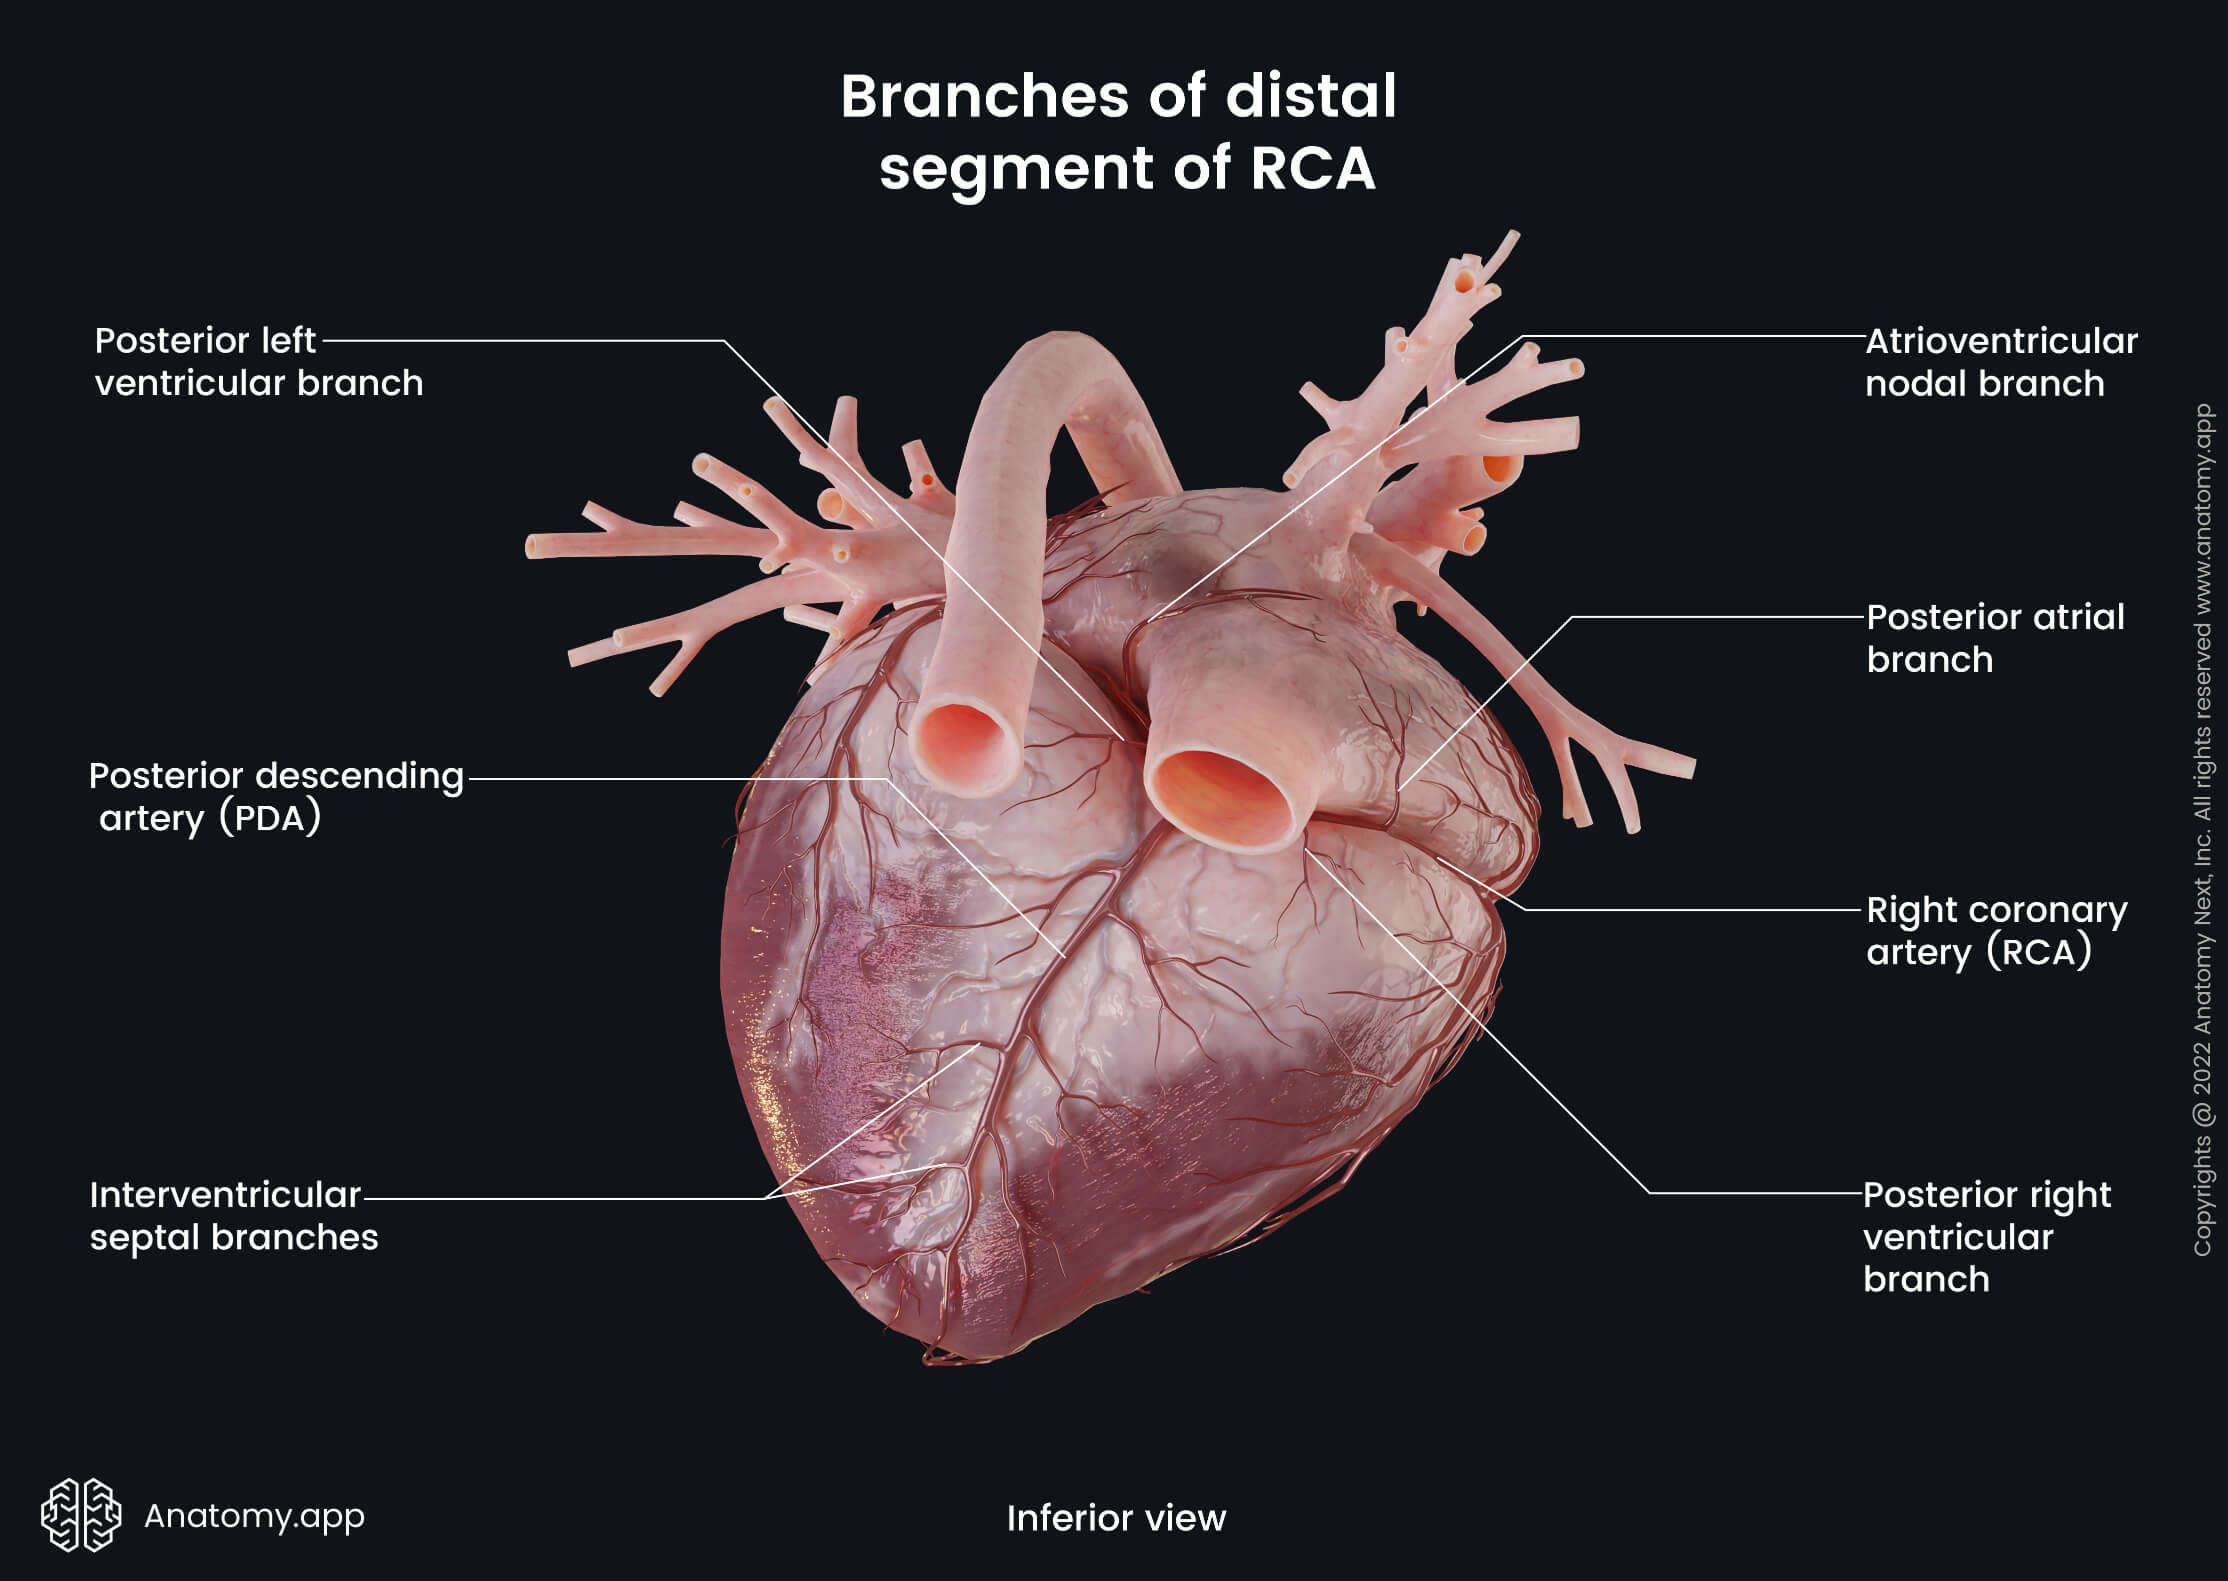
The coronary arteries and veins trace along the surface of the heart within the coronary sulcus and the interventricular sulci. From the anterior view, the left coronary artery bifurcates into the anterior interventricular branch and the circumflex branch. The right coronary artery courses through the right portion of the coronary sulcus before giving off branches that supply the right ventricle and often the posterior descending artery. Understanding the venous drainage is equally important. The great cardiac vein accompanies the anterior interventricular artery. The middle cardiac vein runs alongside the posterior interventricular artery on the opposite surface. From the anterior perspective, you primarily see the anterior cardiac veins draining directly into the right atrium. These small veins cross the right ventricular surface and are easily damaged during surgical procedures in this region.
Get the Full Details

A Practical Problem I Encountered
During a cadaveric dissection session, I spent nearly twenty minutes trying to identify the anterior interventricular artery because the surrounding adipose tissue was unusually thick. The fat obscured the sulcus almost completely and made the vessel nearly invisible to the naked eye. Standard dissection technique with blunt spreading was not working. I switched to using fine scissors for careful incremental trimming of the fat while keeping the blade angled away from the underlying vessel. This reduced the risk of accidental laceration and took about five minutes once I changed approach. The artery was there the whole time, just buried under varying amounts of pericardial fat that differs significantly between individuals. The heart sits in the mediastinum at an oblique angle, not vertically. The base is positioned higher and more posterior than the apex, which sits lower and more anterior. This orientation means that what appears as the "top" of the heart in a diagram is actually the posterior aspect receiving the pulmonary veins. Students frequently get confused because they assume the diagrammatic superior direction matches anatomical superior. Another counter-intuitive point: the right ventricle is actually the most anterior chamber despite being the thinner-walled one. The left ventricle is more posterior and leftward, which is why some of its surface area is hidden from a purely anterior perspective. This anatomical arrangement explains why right ventricular infarctions present differently than left ventricular ones and why anterior surgical approaches primarily encounter right ventricular tissue.
The triangle of cardiac surgery, sometimes called the safe triangle, is bounded by the phrenic nerve laterally, the superior vena cava superiorly, and the anterior interventricular artery medially. Entering through this triangle during pericardiotomy minimizes damage to critical structures. This is not taught consistently in introductory courses but it is essential knowledge for anyone working in cardiothoracic surgery or interventional cardiology.
Limitations of the Anterior View Approach
The anterior view has serious limitations. It does not adequately display the left atrium, which forms most of the base of the heart and is largely posterior. Pulmonary vein ostia, the left atrial appendage, and the posterior aspects of the coronary sinus are invisible from this perspective. If you need to evaluate mitral valve pathology or left atrial size, the anterior view will not give you enough information. Transesophageal echocardiography or posterior dissection is necessary instead. Surface anatomy derived from anterior diagrams is unreliable for patients with cardiomegaly, severe COPD with barrel chest, or significant pectus deformities. The apex beat location shifts considerably in these populations, making any rigid rule about the fifth intercostal space inaccurate. Clinical examinations must account for these variations rather than relying on textbook landmarks alone.
How to Study This Effectively
Use a combination of real specimens, cross-sectional imaging, and 3D reconstructions. Diagrams are useful for initial orientation but they flatten three-dimensional relationships into two dimensions. CT scans and MRI studies show the heart in situ with surrounding structures, which helps you understand spatial relationships that diagrams cannot convey. Look at actual surgical videos when possible. Watching a median sternotomy or minimally invasive cardiac procedure reveals how the anterior surface is encountered in real clinical settings. Palpate your own apex beat. Stand or sit upright, lean slightly forward, and press lightly along the left sternal border at the fourth and fifth intercostal spaces. Finding it confirms the relationship between surface anatomy and underlying structure better than any image ever could. Most people can locate it within a minute if they know what they are feeling for. The anterior view of the heart's external anatomy is deceptively straightforward. The right ventricle dominates the surface, the coronary vessels provide essential landmarks, and the apex marks the left ventricular contribution. Understanding what is visible from this angle and, just as importantly, what remains hidden behind it, is what separates adequate anatomical knowledge from functional clinical understanding. Practice with actual specimens when you can, use imaging to fill in the gaps, and always remember that every heart varies slightly from the standard description you memorized.


