What Most People Get Wrong About Fall Risk Assessment
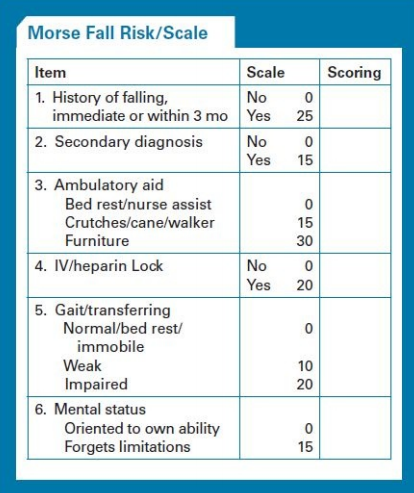
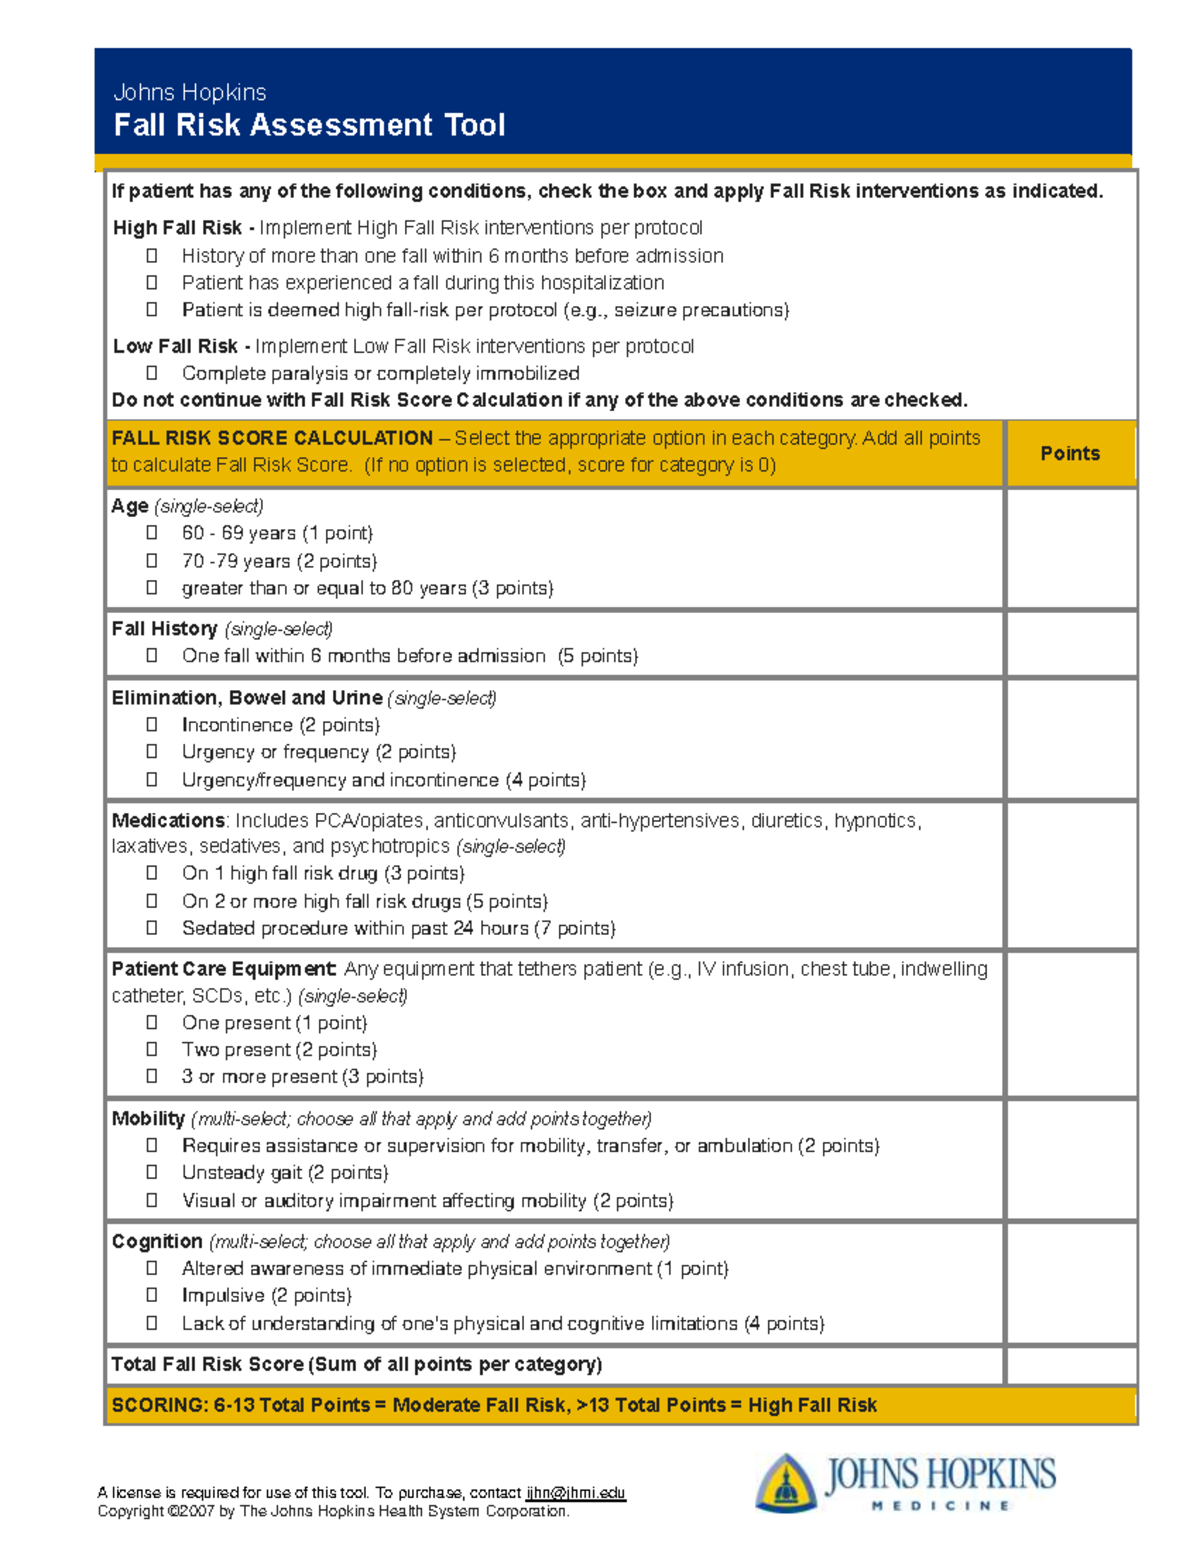
A fall risk assessment is a structured clinical tool used to evaluate a person's likelihood of falling, usually within a hospital, skilled nursing facility, or home health setting. The Fall Risk Assessment Scale isn't one single instrument — it's a category. There's Morse, there's Hendrich II, there's the STRATIFY tool, and several hospital-specific versions. Picking the wrong one for your population will give you data that looks accurate but means nothing when someone actually takes a tumble. The Morse Fall Scale is the most common in acute care hospitals. It's quick, uses six items, and gives a score between 0 and 125. Anything above 45 is considered high risk. The Hendrich II Fall Risk Model is more weighted toward medication use and cognitive status, which makes it better for medical-surgical floors where polypharmacy is the norm. STRATIFY is designed for rapid screening in emergency departments and early discharge planning — it's five items, takes about 90 seconds, and trades granularity for speed. I worked at a 200-bed hospital where we ran into a real problem about three years ago. We were using the Morse exclusively on our geriatric orthopedic unit, and we kept scoring patients as low risk when they fell within 48 hours. The issue was that the Morse doesn't account for post-operative delirium or acute confusion well. Our hit rate for missed high-risk patients was sitting around 22 percent. The workaround was straightforward but annoying to implement: we layered a cognitive screen on top. Nurses would run a quick Mini-Cog or AMT-4 alongside the Morse for anyone over 70 with a hip fracture or who'd received opioid analgesics in the prior shift. That dropped our miss rate to under 8 percent within six months. It added maybe four minutes per assessment, which is nothing compared to the cost of a single fall with injury.
How to Administer the Morse Fall Scale Properly
The Morse has six domains: history of falling, secondary diagnosis, ambulatory aid, IV or heparin lock, gait, and mental status. Each has a point value attached. The "history of falling" item alone is worth 25 points — it's the single heaviest factor. If a patient has fallen within the last three months, that's automatic high-risk territory regardless of how steady they look on their feet right now. This is the part people skip because it requires chart review or a conversation with the patient, not just a visual check. For ambulatory aid, you're evaluating what the patient actually uses, not what they own. A lot of nurses will see a walker in the room and automatically score "none" under ambulatory aid. That's incorrect. The Morse specifically asks about the patient's usual method of ambulation. If they normally walk with a cane but got a walker after admission, score "cane" or "crutches," not "none." This distinction matters because it affects the point total significantly. Gait assessment is where most people get sloppy. The instructions say to observe the patient walking, not to ask them how they walk. I've seen nurses assign a "poor" gait score based entirely on how a patient describes their own balance, which inflates the score and creates unnecessary alarms. The gait item should be scored only after direct observation — even if it's just a ten-foot walk across the room. Mental status is another frequent pain point. The Morse asks whether the patient "forgets their limitations," meaning they act more independently than they safely can. This is a clinical judgment call, not something you can verify from a vitals sheet. Document what you actually observed rather than guessing from the problem list.
Limitations and When the Scale Completely Fails
The biggest blind spot across virtually all fall risk scales is orthostatic hypotension. None of the mainstream tools include a standing blood pressure check as a scored item, yet orthostatic drops are a leading cause of falls in older adults, particularly after diuretic adjustments or antihypertensive changes. If you're relying solely on a points-based scale without checking orthostatics, you're missing a mechanism entirely. I recommend adding a standing BP protocol for any patient over 65 who scores above 50 on the Morse but hasn't been evaluated for autonomic function. Another failure mode is the "honeymoon effect." When a new scale gets implemented, fall rates often drop temporarily because staff are more vigilant. The improvement isn't because the scale is working — it's because everyone's paying attention. Six to twelve months later, vigilance erodes and the data usually reverts. I've seen this happen at three different facilities. The scale itself didn't change; the compliance with the underlying interventions did. A score of 115 on the Morse means exactly nothing if the bed alarm isn't being applied, non-slip footwear isn't being provided, and hourly rounding isn't happening. The scale identifies risk. It doesn't manage it. Scales also struggle with intermittent risk. A patient might score low in the morning and develop a urinary tract infection by afternoon, pushing their actual risk up dramatically. Static reassessment intervals — typically every 8 hours or upon transfer — don't catch these shifts unless a trigger event is documented and the scale is re-run. The Hendrich II has slightly better handling here because it includes medication changes as an item, but even that lags behind real-time clinical deterioration.
Get the Full Details

Practical Workflow for Running a Fall Risk Assessment Scale Assessment
Start with a brief med review. Anticonvulsants, benzodiazepines, antidepressants, and antihypertensives are the usual suspects. Note any recent additions or dose increases — that's an automatic flag regardless of the patient's baseline score. Then assess gait directly. Have them walk from the bedside to the chair and back. Don't time them. Just watch for hesitation, truncation of stride, or handrail dependence. Next, check history of falls in the past three months. Review the chart, ask the patient if they're alert enough to recall, and check prior shift handoff notes if available. Finally, evaluate mental status using the "forgets limitations" criterion. If they attempted to ambulate unassisted despite a known walking aid being at the bedside, that's a positive finding. Score the total and document the category: low, moderate, or high. Then immediately map interventions to that category. A high score without an intervention plan is just a number on a form. The intervention bundle for high-risk patients typically includes bed alarm, non-slip footwear, toileting schedule, family education, and a physical therapy consult for gait training. Moderate risk gets a subset — usually education and footwear at minimum. Low risk still gets basic safety counseling because complacency is where most injuries happen. If you need a printable or digital version of the Morse Fall Scale, the original instrument is in the public domain and available through the University of California, San Francisco School of Nursing website. Most hospital EHR systems also have built-in versions that auto-calculate. The Hendrich II is proprietary and requires a license, but it's widely distributed through fall prevention program vendors like PreventionPoint and AHRQ-affiliated networks. STRATIFY is freely available through the UK's National Institute for Health and Care Excellence guidelines.