So you need to understand synovial joint anatomy
I've been going over this material with students for years, and it's always the same pattern. They memorize the five parts, draw them on a diagram, and think they know it. Then they see a real specimen or an MRI scan and immediately get confused. The gap between textbook diagrams and actual biological tissue is wider than most introductory courses admit. Here's the thing about the Parts Of A Synovial Joint — they work together in ways that aren't obvious from a labeled illustration. Each piece has a mechanical function, and when one fails, the others compensate until something else gives. That's why understanding the parts in isolation doesn't help you understand joint pathology.
The Parts Of A Synovial Joint Explained In Practice
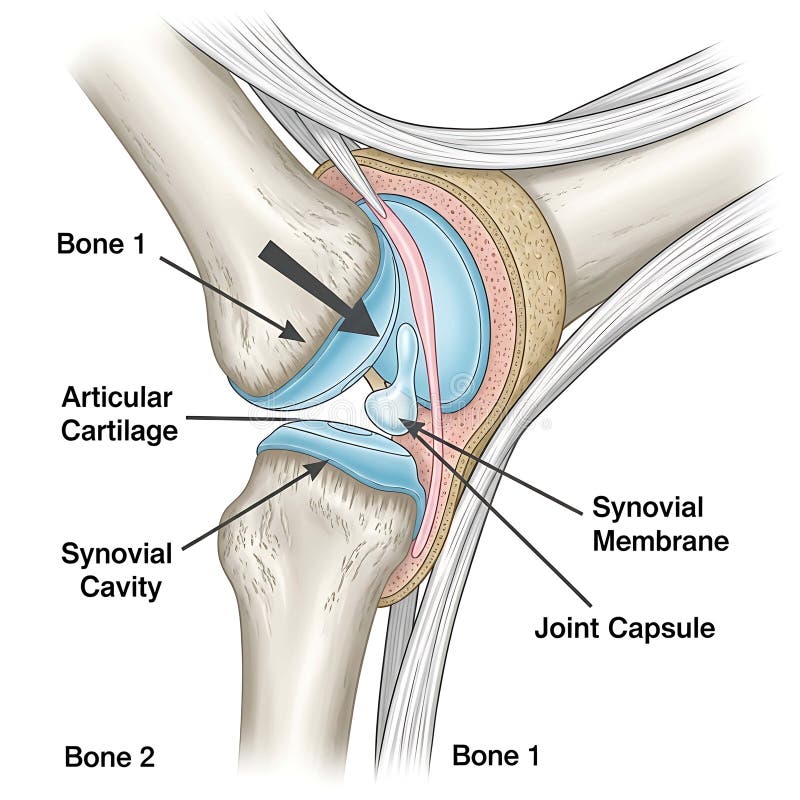
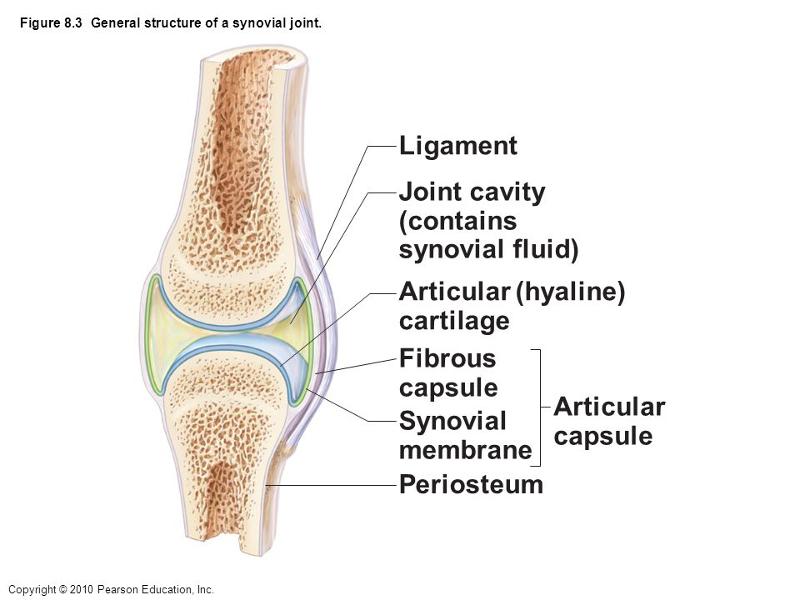
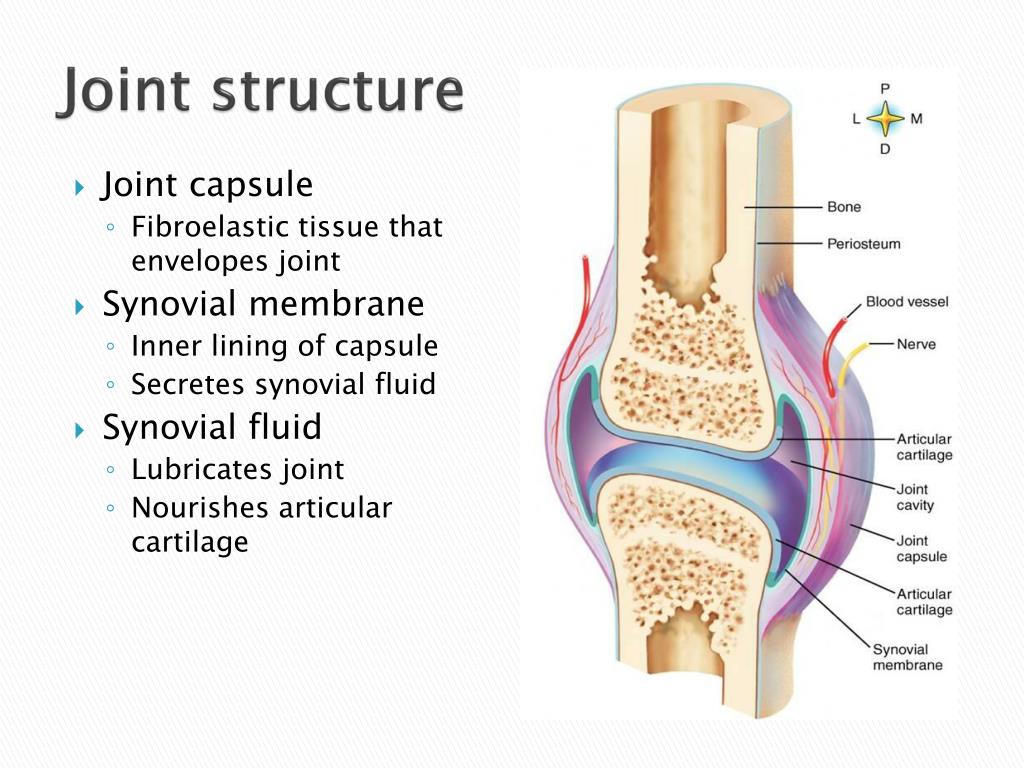
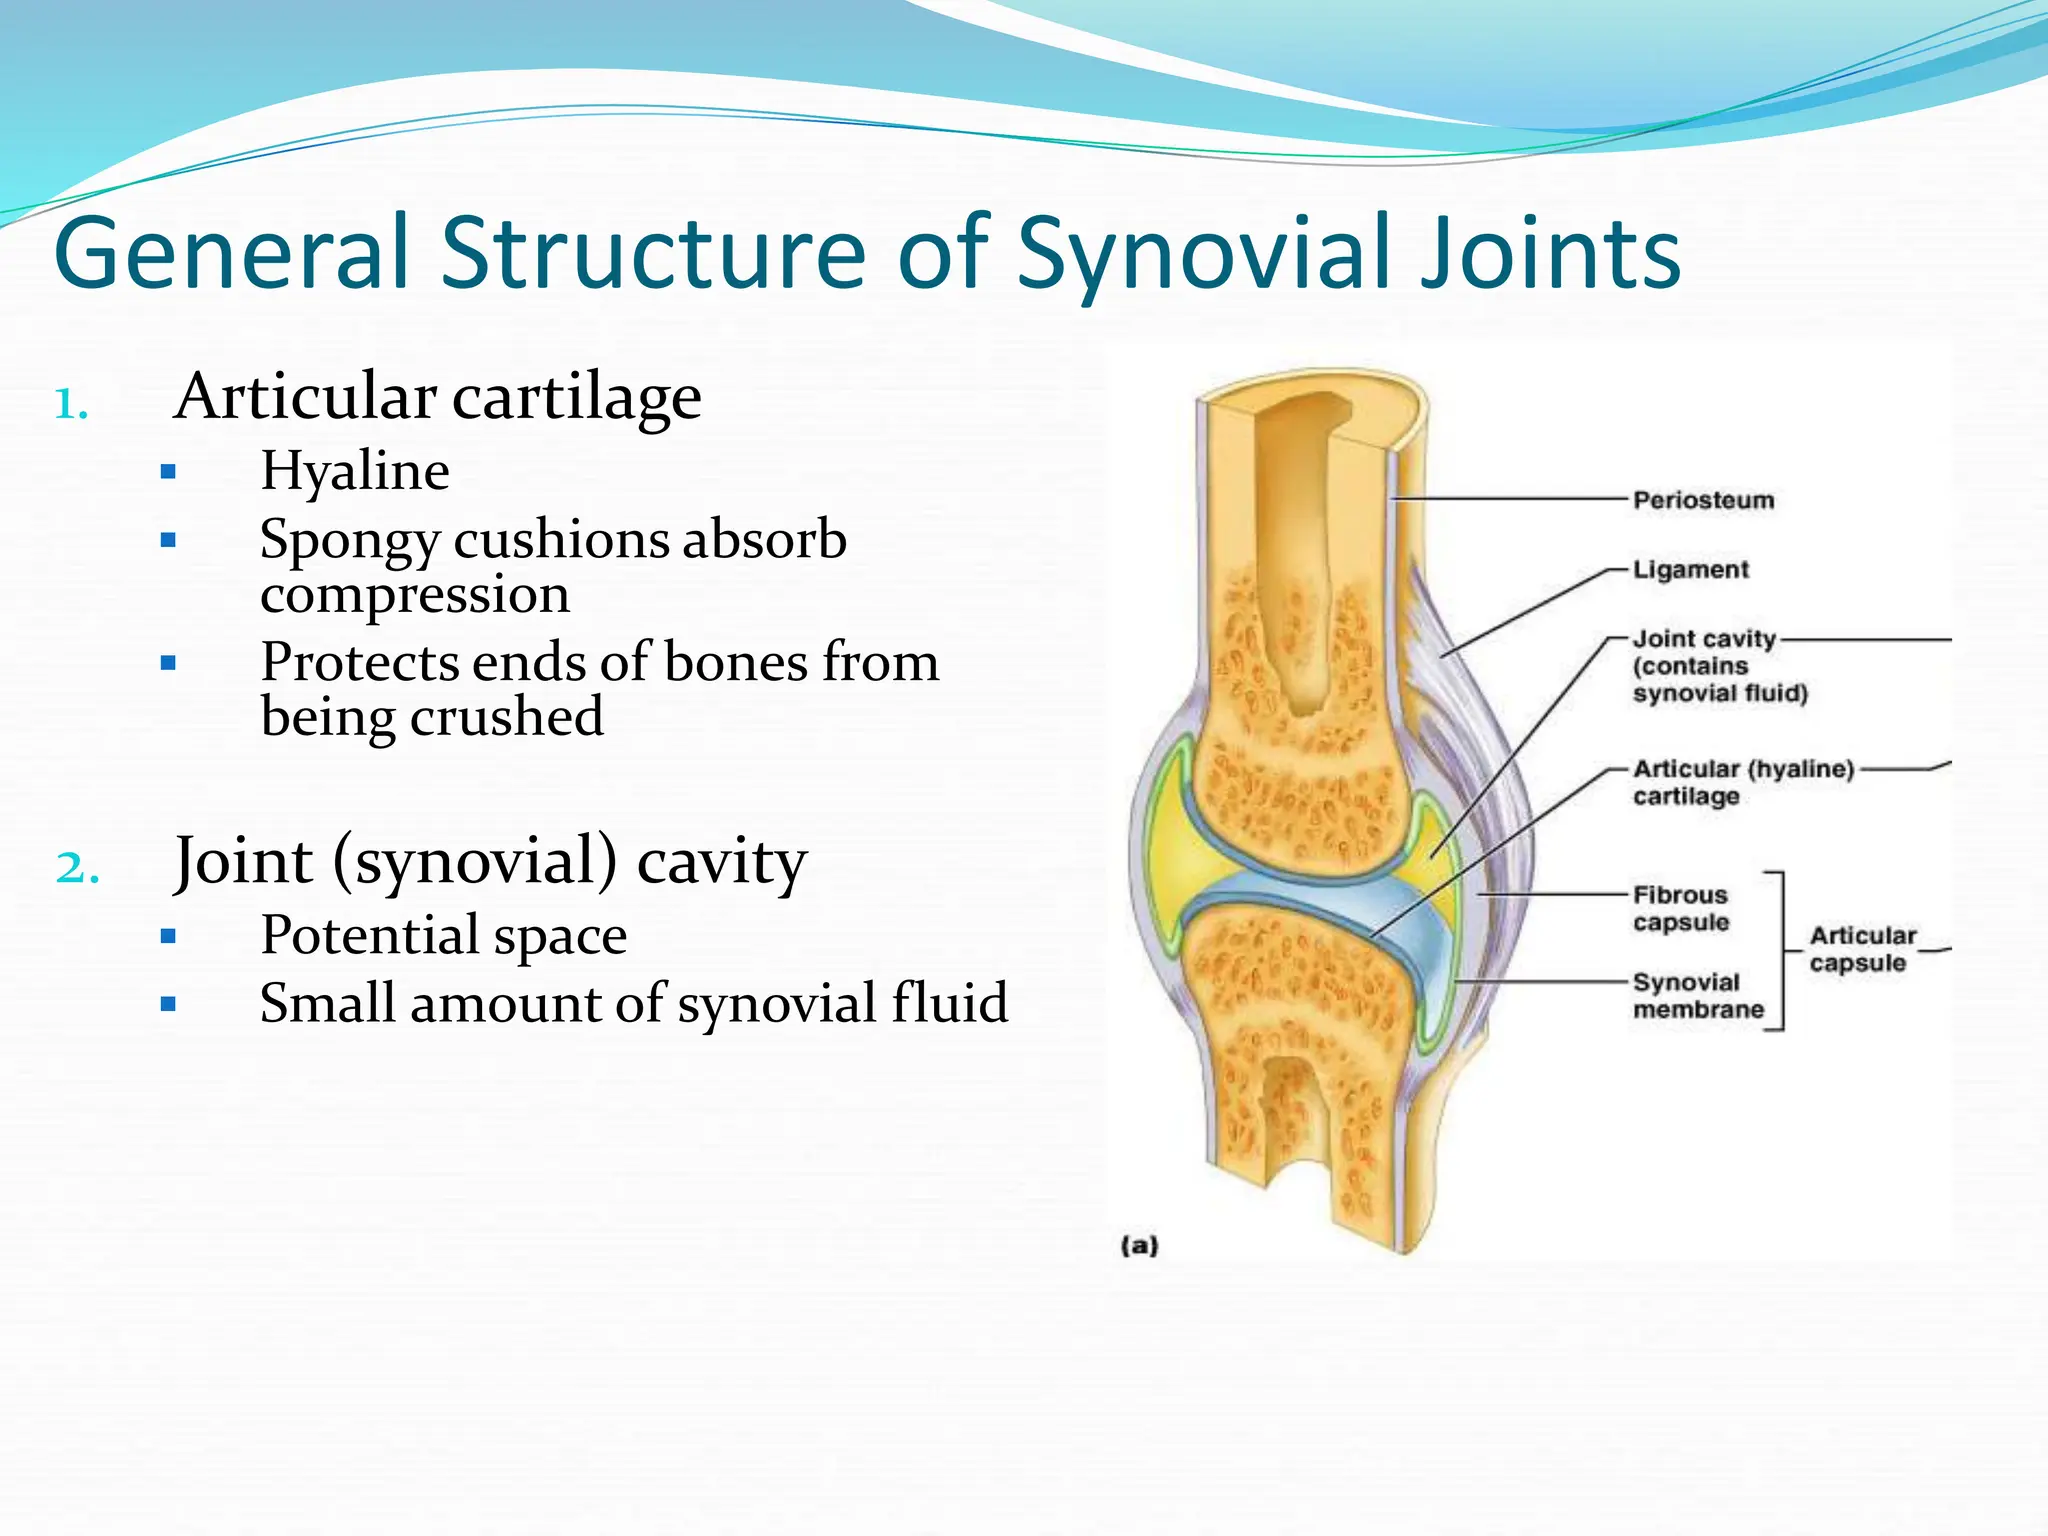
The six components are articular cartilage, the joint (synovial) capsule, the synovial membrane, synovial fluid, ligaments, and accessory structures like bursae and fat pads. Let me walk through each one and where people regularly go wrong. Articular cartilage covers the ends of bones where they meet inside the joint. It's hyaline cartilage, mostly type II collagen and aggrecan. The surface is extremely smooth when healthy — friction coefficient lower than ice on steel. But here's what most sources don't emphasize enough: articular cartilage is avascular. It has no blood supply. It gets nutrients from the synovial fluid through diffusion and compression-decompression cycling. That means joint movement is literally part of cartilage metabolism. A sedentary person isn't just risking obesity for their knees; they're starving their cartilage at a mechanical level. I once had a patient whose early osteoarthritis progression traced directly to prolonged immobilization after a unrelated ankle fracture. The knee wasn't injured, but it wasn't moving either. The joint capsule is a fibrous sac that encloses the joint cavity. It has two layers. The outer fibrous layer is dense irregular connective tissue — tough, sturdy, and relatively inelastic. The inner synovial membrane is where things get interesting. The capsule's tension varies by joint. In the shoulder, it's loose enough to allow massive range of motion but that looseness is exactly why anterior dislocations are so common. In the hip, it's tighter and reinforced with three major ligamentous thickenings (iliofemoral, pubofemoral, ischiofemoral), which is why hip dislocations require significant trauma. The capsule isn't just a bag; its tension properties define the joint's stable range of motion.
The synovial membrane lines the inner capsule and produces synovial fluid. It lacks a continuous basement membrane, which is unusual for a tissue layer and explains why inflammatory cells invade it so readily during arthritis. Type B synoviocytes secrete hyaluronic acid and lubricin. Type A synoviocytes are macrophage-like and clean up debris. When you hear about "sloughing" in degenerative joints, that's often Type A synoviocytes struggling to clear the increased particulate matter from cartilage breakdown. Synovial fluid is a filtrate of blood plasma with added hyaluronic acid and lubricin. Normal volume in a knee joint is about 2 to 4 milliliters. The viscosity is non-Newtonian — it becomes less viscous under shear stress, which is why it lubricates better during movement than at rest. This is called shear-thinning and it's critical for joint function. I spent a lot of time explaining this to rheumatology residents who were surprised that the fluid's lubrication properties actually improve with activity. They expected the opposite based on how most industrial lubricants behave. Ligaments connect bone to bone within the joint. They're not just static restraints. Ligaments contain mechanoreceptors — Ruffini endings, Pacinian corpuscles, and Free nerve endings — that provide proprioceptive feedback. When you sprain a ligament, you're not just losing structural integrity; you're destroying a significant proprioceptive organ. That's why rehab after ligament injury always emphasizes neuromuscular retraining, not just strengthening. I worked with a sports medicine surgeon who told me his ACL reconstruction patients often felt "unnatural" for months even when the graft was perfectly placed. The missing piece was always the proprioceptive input that came with the original ligament.
Get the Full Details

Accessory structures include bursae, tendon sheaths, fat pads, menisci, and articular discs. These aren't always present but modify joint function significantly when they are. The infrapatellar fat pad (Hoffa's fat pad) is one of the most clinically relevant structures people overlook. It fills space behind the patellar tendon, provides cushioning, and contains a rich nerve supply. Fat pad impingement is a real source of anterior knee pain that gets misdiagnosed constantly. During arthroscopy, if you see a swollen, fibrosed fat pad, that's Hoffa's syndrome and it explains pain that no meniscal tear or ligament injury accounts for.
Where This Breaks Down
There are scenarios where the standard model of Parts Of A Synovial Joint doesn't apply cleanly. The sternoclavicular joint has an articular disc but no true synovial cavity in the classical sense. The sacroiliac joint transitions from fibrous to synovial characteristics along its surface. The temporomandibular joint has a disc but its superior compartment behaves differently from the inferior compartment during opening and closing — they're functionally two separate joints within one capsule. Also, the term "synovial joint" itself can be misleading. Not every joint with a synovial membrane is freely movable. The anterior interpubic joint has a fibrocartilaginous disc and a synovial cleft but minimal movement. Calling it a synovial joint is technically correct but functionally confusing. In clinical contexts, people use "synovial joint" to mean any freely movable joint, which is close enough for most purposes but worth noting when you're reading research papers that classify joints differently. Another practical limitation: imaging the Parts Of A Synovial Joint comprehensively is harder than it sounds. X-rays show bone and calcified structures. MRI shows soft tissue but requires the right sequences — T1 for anatomy, T2 with fat saturation for pathology. Ultrasound is operator-dependent and excellent for superficial joints like the knee and shoulder but useless for the hip in most patients. CT arthrography, where contrast is injected into the joint space, is the gold standard for labral and capsular pathology but it's invasive. No single modality gives you the full picture, and that's something students rarely learn before they encounter real diagnostic work.
A Note On Common Pitfalls
The biggest mistake I see is treating the parts as independent components rather than an integrated system. Take osteoarthritis. It's not just "cartilage wearing down." The synovial membrane becomes inflamed, producing degraded fluid with lower lubricin content. The capsule thickens and contracts, reducing range of motion. Ligaments may become lax due to altered joint mechanics, creating instability. Bone forms osteophytes at the margins. The entire joint remodels pathologically. You can't fix the cartilage without addressing the fluid, and you can't fix the fluid without addressing the synovium. That's why isolated cartilage treatments have such variable success rates — they treat one part while the rest of the system continues to degrade. When studying this, I'd recommend building a mental model where each part feeds into the others mechanically and biochemically. Draw the joint, label the parts, then trace what happens when one component changes. It takes about fifteen minutes per joint and it transforms how you understand joint pathology. Most people skip that step and wonder why they can't connect the anatomy to the clinical presentations.