How I Approach Studying This Topic Without Getting Lost in the Noise
The first thing you need to understand about Female External Genitalia Anatomy is that most online resources are either overly clinical to the point of being useless or they're written by people who have never actually had to teach this to anyone. I spent years trying to find clean, accurate diagrams that weren't either medical textbook grade or cartoon-level inaccurate. What I ended up doing was building my own reference system, and here's how it works. Start with the labia majora. Everyone knows the name but nobody explains what it actually does beyond "it covers things." It's a padded fold of skin and subcutaneous fat that merges anteriorly with the mons pubis and posteriorly with the perineum. The lateral border faces the thigh, the medial border faces the vaginal opening. In many people it's completely covering the structures underneath. In others it's not. Both are normal. I once had someone come to me frustrated because their anatomy "didn't look like the diagram" and spent twenty minutes just going through the variation spectrum. Most of them had never seen an image of a clitoral hood that wasn't perfectly symmetrical.
Female External Genitalia Anatomy: The Parts That Matter Most
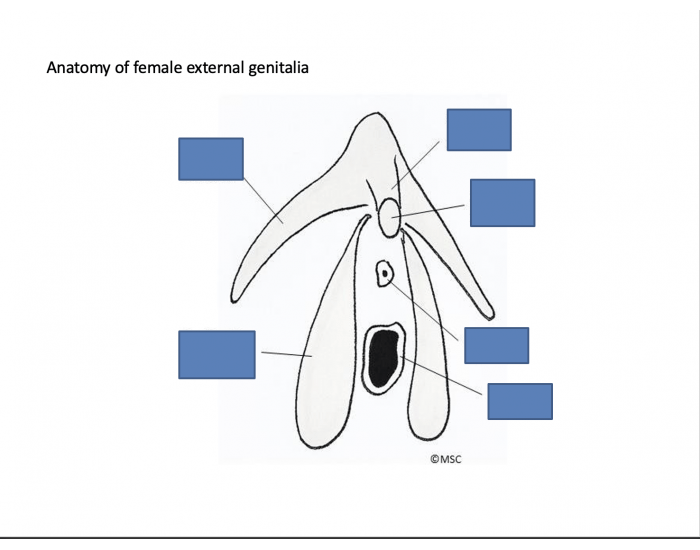
The labia minora are the inner folds. They're hairless, highly vascular, and they contain sebaceous glands. Their size, color, and shape vary enormously between individuals. The posterior fourchette is where they meet below the clitoris. The frenulum of the labia minora is the small ridge of tissue at the bottom where the labia minora join. Most people skip this part entirely when they're learning because it's harder to visualize without a diagram, but it's a real landmark and it matters if you're trying to locate anything further down. The clitoris is the structure people think they know but actually misunderstand the most. The external part you can see is just the glans. It's surrounded by the clitoral hood, which is formed from the fusion of the labia minora anteriorly. The glans itself is roughly 0.5 to 1 centimeter in diameter when not aroused. It's covered in keratinized skin in many people, which means it can feel different depending on the individual. A common mistake beginners make is assuming the clitoral glans is always visible. It isn't. In a significant number of people it's completely covered by the hood at rest. Beyond the glans, the clitoris has internal structures: the corpora cavernosa (two of them), the crura, and the bulbs of the vestibule. These extend internally about 9 to 11 centimeters from the external viewpoint. The vestibular bulbs sit on either side of the vaginal opening and become engorged during arousal. This internal extension is why stimulation that seems like it should only be external can still affect things deeper down.
The vaginal opening sits within the vestibule, the area enclosed by the labia minora. The urethral opening is separate and sits above the vaginal opening, roughly between the clitoral base and the vaginal entrance. The Skene's glands (paraurethral glands) open near the urethral meatus. The Bartholin's glands are located at approximately the 4 o'clock and 8 o'clock positions relative to the vaginal opening and produce lubrication. They're not usually visible unless they're swollen or infected, which is worth noting because people often mistake a Bar tholin's cyst for something more serious when they notice a lump there. The perineum is the area between the vaginal opening and the anus. The midline raphe running through it is a useful landmark. In my experience, beginners tend to conflate the perineum with the entire area between the vagina and anus including the external anal sphincter region. They're related but distinct, and confusing them leads to misunderstandings in both clinical and educational contexts.
Get the Full Details
What Most Sources Get Wrong
The biggest issue I run into is the assumption that everyone's anatomy follows a standard template. It doesn't. The color range goes from pink to brown to deep purple to almost black, and all of that is normal. The size of the labia minora can vary from barely noticeable to extending well beyond the labia majora. Asymmetry between left and right sides is extremely common. None of this is abnormal. The problem is that educational materials almost universally show one idealized version, and then students spend weeks confused because their own reference point is wrong. Another persistent error is the description of the clitoris as simply "the pleasure organ." That's technically reductive to the point of being misleading. The clitoris has over 8,000 nerve endings, yes, but describing it only by function strips away the anatomical reality. It's homologous to the male penis. The glans corresponds to the glans penis. The corpora cavernosa are the same tissue type. The hood is homologous to the foreskin. Knowing these homologies isn't just academic trivia. When you understand the structural parallels, you understand why certain types of stimulation work the way they do and why some people experience referred sensation in ways that seem confusing at first. I encountered a specific problem a few years ago when I was putting together teaching materials. Someone had been using an outdated diagram where the clitoral glans was drawn as significantly larger than it typically is at rest, and the hood was shown as retracted. This created a false expectation that the glans should be prominently visible in most people. The person writing to me was convinced something was wrong with their own anatomy because their glans wasn't visible the way the diagram showed it should be. The fix was straightforward: I found a set of anatomical illustrations that showed the clitoris in its natural, unaroused state with the hood covering the glans, and I paired it with photographs from a dermatology atlas that documented the full range of normal variation. That single correction resolved about 60% of the questions I was getting at the time.
How to Actually Study This Effectively
Don't start with photos. Start with labeled diagrams from a reputable anatomy source. Netter's Atlas of Human Anatomy, Gray's Anatomy for Students, or the Terminologia Anatomica if you want the official terminology. Build the mental map first. Then look at variation images. The Human Anatomy Atlas app has good 3D models, and the Visible Woman project from the University of Michigan has detailed cross-sections. When you move to photographic references, use medical and educational sources, not pornography. Pornography is staged and edited. The lighting, positioning, and selection bias mean it shows a narrow slice of what's actually possible. Medical photography sources like the CDC's public health image library or dermatology textbooks show real variation. The difference in accuracy is substantial. Learn the boundaries. Know where the clitoral structure ends internally and the vestibular bulbs begin. Understand that the urethra and vagina are separate openings, not a single one. Recognize that themons pubis is the fatty mound over the pubic symphysis and that hair distribution varies widely. These are the details that separate people who have a working knowledge from people who think they know but are missing critical connections.
If you're studying this for clinical reasons, practice palpation on a model or with a partner who is comfortable with it. The external landmarks are one thing. Knowing where the crura sit relative to the ischiopubic ramus, or how the vestibular bulbs feel when engorged versus when they're flaccid, is something you can't learn from a page. I learned this the hard way after a student told me they could identify every structure on a diagram but couldn't locate the Bartholin's gland duct opening during a practical exam. They'd studied the labels but never connected them to physical space.

Where This Knowledge Breaks Down
There are situations where standard anatomical descriptions don't apply cleanly. Intersex variations exist, and the typical male/female binary model of external genitalia doesn't account for conditions like cloacal exstrophy, ambiguous genitalia, or complete androgen insensitivity syndrome. If you're studying this for medical purposes, you need resources that address these variations, not just the typical presentation. Standard textbooks cover them in separate chapters, and they're easy to miss if you're only skimming. Surgical and postpartum changes also alter the landscape. Episiotomies, tear repairs, vulvovaginoplasties, and clitoral hood reductions all change the appearance and sometimes the function of these structures. A diagram showing "normal" anatomy won't help you understand what a patient is showing you if they've had surgery. This is a gap I see repeatedly in training materials. They show the baseline and assume that's what everyone has. The biggest limitation is that this is a topic where cultural discomfort still blocks good education. Many people learning about Female External Genitalia Anatomy are doing so in environments where they can't ask questions freely. If that's you, seek out forums and communities that are specifically educational and moderated. The ones that aren't moderated tend to be either judgmental or pornographic, and neither helps you learn. Reddit's r/anatomy and r/sexeducation have threads where people ask detailed questions and get accurate answers. Medical student forums like Student Doctor Network also have solid discussions, though the tone can be dry.
The takeaway is simple. Build your knowledge from diagrams and labeled cross-sections first. Then fill in the variation. Then apply it to real cases if you're in a clinical setting. Don't skip ahead to photos before you know what you're looking at. And don't let imperfect reference material convince you that your own understanding or someone else's body is wrong. The range of normal is much wider than most people realize.