What Actually Happens During a Firefighter Annual Physical
The Firefighter Annual Physical Exam is a routine requirement for most departments, but the way it is administered varies enough that you will waste time if you assume every department does it the same way. I have been around enough of these over the years to know the general shape of the process, and I also know the specific spot where most people get tripped up without realizing it until they are already behind schedule. A standard annual physical for a firefighter covers much of what a regular occupational health screening includes, but with extra weight placed on cardiopulmonary fitness, musculoskeletal evaluation, and certain infectious disease screenings that are less emphasized in civilian physicals. You can expect a blood panel, urinalysis, lung function testing, vision and hearing checks, blood pressure, and a cardiovascular exam. Some departments also require a TB skin test or chest X-ray on a rotating schedule rather than every single year. The timing of these exams is usually tied to your hire date or anniversary date, not your birthday. Departments track this through their medical coordinators or third-party occupational health clinics. I have seen firefighters show up two weeks late because they assumed the calendar year reset would handle the tracking. It does not. The department's safety office or health unit maintains the schedule, and you are responsible for making sure your paperwork gets submitted before the deadline.
How to Prepare for Your Firefighter Annual Physical Exam Without Wasting Time
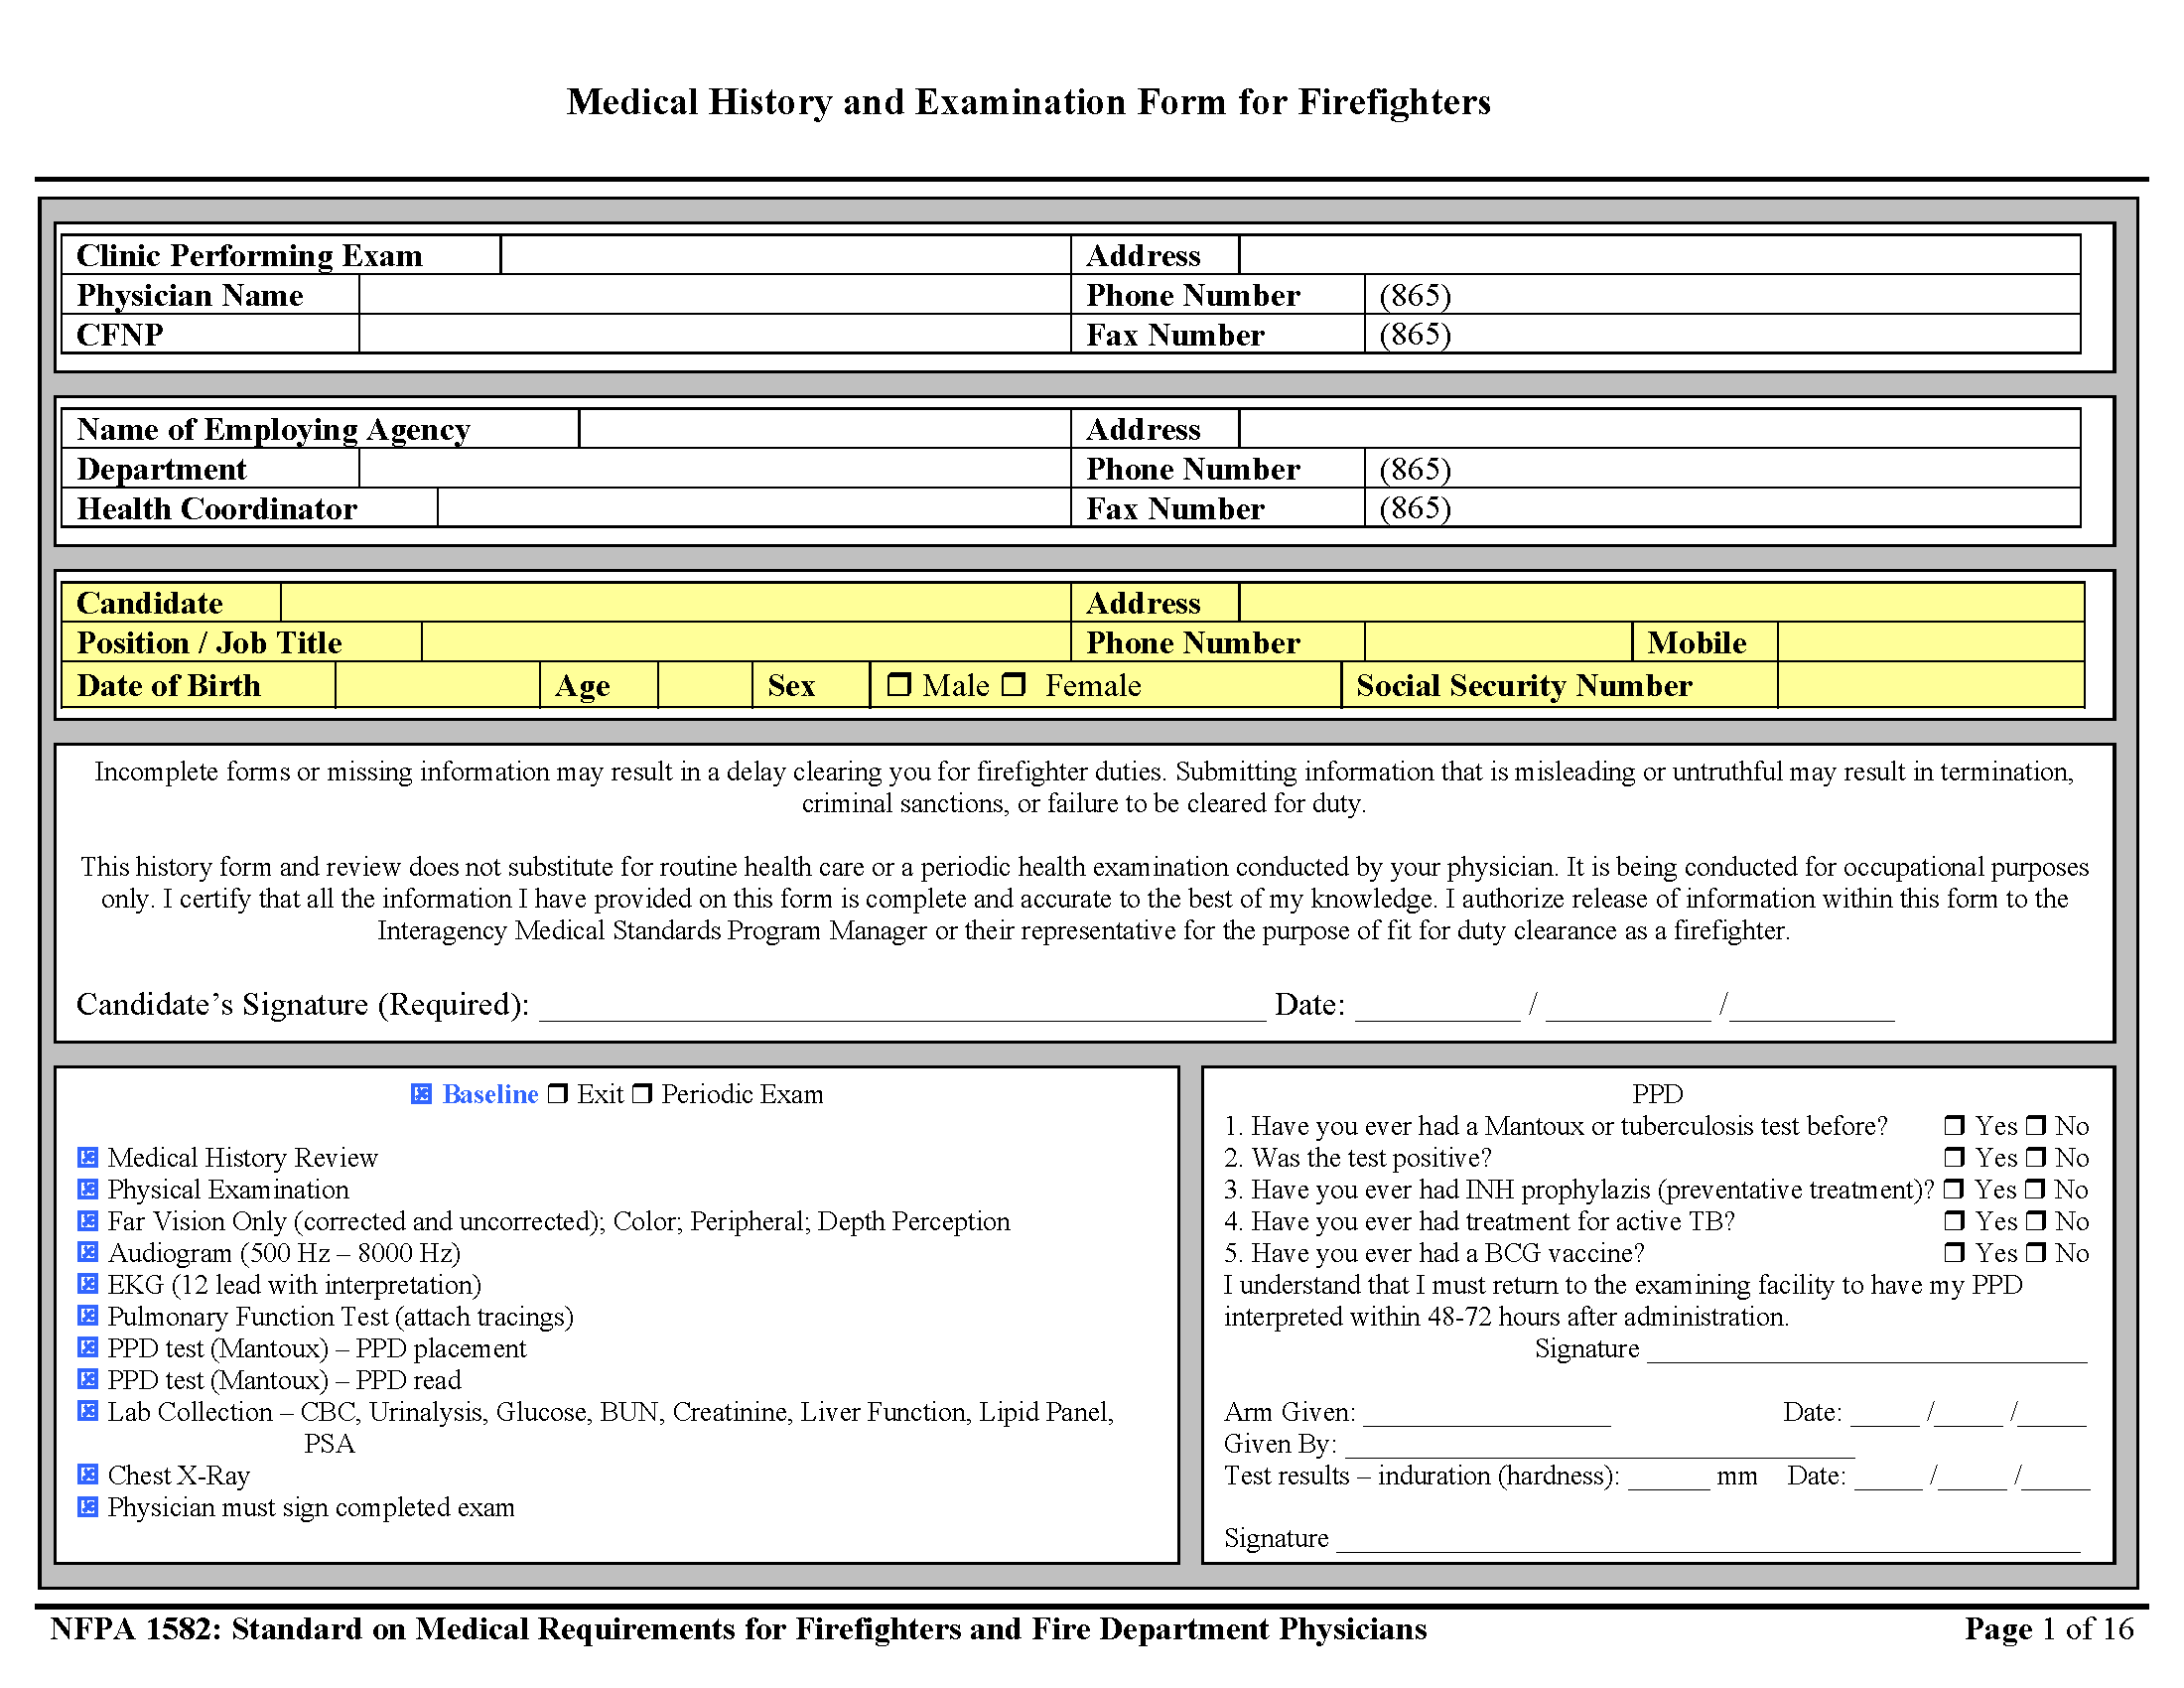
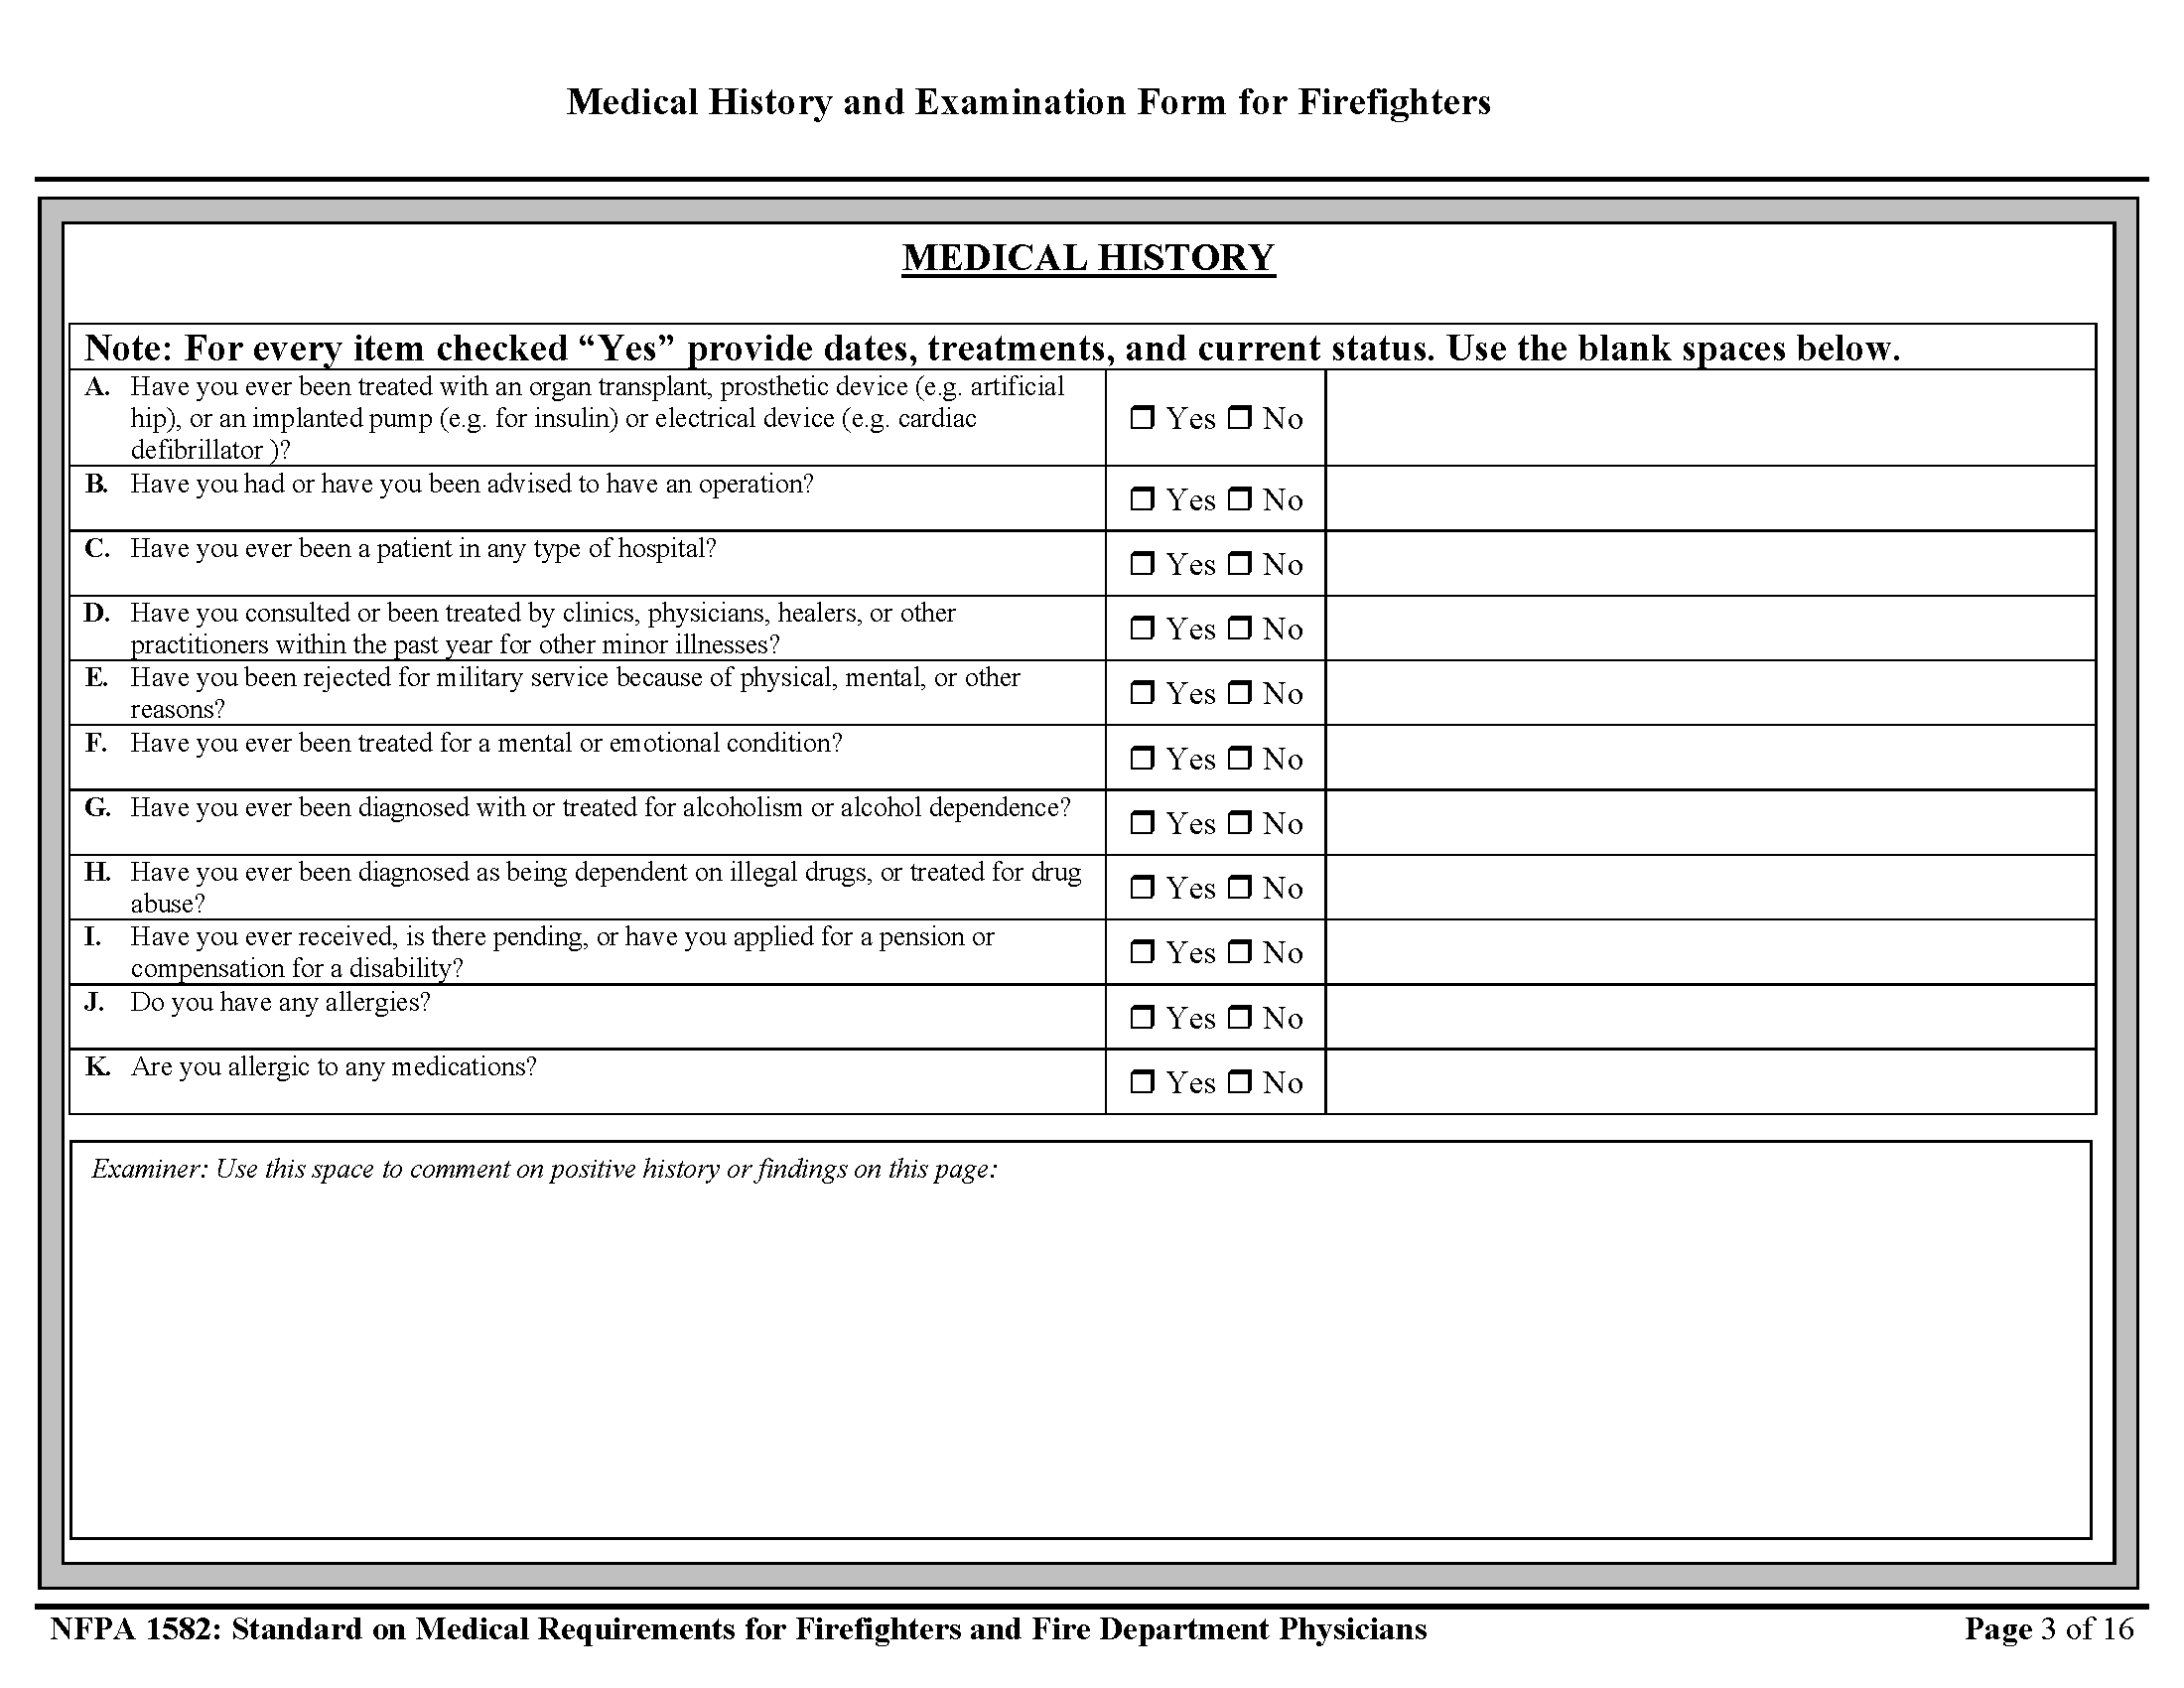
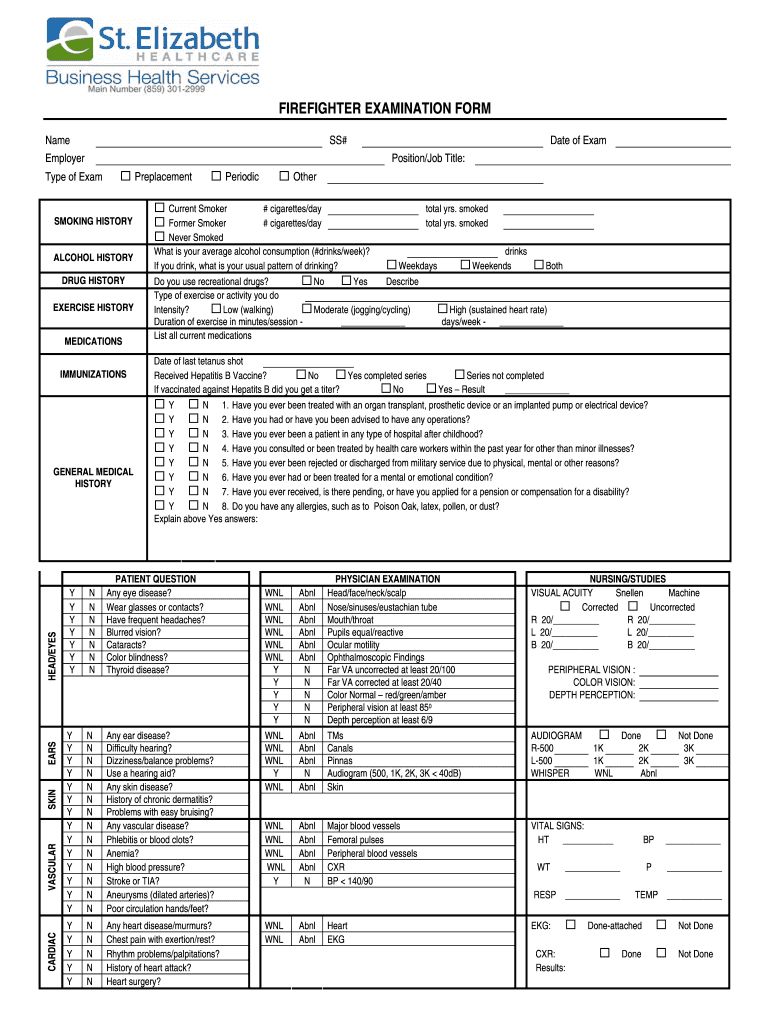
Here is how the process actually goes if you want it done in one visit and without surprises. You need to request your department's specific physical exam form or packet from your training officer, safety liaison, or health coordinator. Not every department uses the same form. Some use a standard NFPA 1582 reference sheet. Others have their own internal version. The difference matters because the form determines which tests are required and which are optional based on your rank, assignment, and exposure history. Bring a list of all medications you are currently taking, including dosages and prescribing physician names. The examiner needs this information, and they will not fill it out for you. I have watched people try to wing this part and end up spending an extra hour at the clinic chasing down old prescriptions through their pharmacy. The pharmacy can send records, but that takes three to five business days on a typical weekday, and by then you are already past your department's deadline.
The night before your exam, do not drink alcohol. Avoid heavy caffeine. Get a normal night's sleep. These are not suggestions that some clinic writes on a flyer. They matter for blood pressure and liver enzyme readings. A single elevated blood pressure reading on the day of the exam will often trigger a follow-up visit requirement. One additional appointment. That is what you get for a salty dinner and two beers the evening before. If you have a history of asthma, hypertension, or any cardiac condition, bring your specialist's most recent clearance letter and your last six months of relevant lab results. Some departments accept prior results within a certain window. Others require everything to be pulled from the current exam cycle. Clarify this before you walk into the clinic, because the clinic staff will not ask you about it and they will document everything as a brand-new baseline.
Get the Full Details

The Edge Case That Cost Me a Full Day
Here is a specific problem I ran into that most people never see coming. I was completing my annual physical at a contracted occupational health clinic. The department I worked for at the time used a regional health network that pulled results into a centralized electronic system. My previous year's labs were still sitting in that network from the exam I had completed twelve months earlier. When the examining physician ordered the new panel, the system auto-populated the prior results instead of running fresh draws. The phlebotomist drew blood, but the lab report that came back included last year's lipid panel and a recent hemoglobin A1c from a diabetes screening I had never received. I passed the physical on paper, but three weeks later the department medical review board flagged it because the A1c number came from a different diagnostic context than what they expected. I had to go back, get the test repeated under the proper designation, and submit it separately with a covering note from the ordering physician. That took another appointment and nine additional days of waiting. The workaround is simple and it prevented this from happening again. Before the draw, I asked the clinic to run all existing results through an adjudication log and confirm they were marked as current-cycle tests. I also wrote a brief note on my copy of the form stating which labs I wanted freshly drawn versus which prior results I authorized for reuse. The clinic put it in the chart. The medical board accepted it without question.
This kind of administrative edge case is not discussed during department orientations. It happens because the system assumes continuity where none was explicitly established. The fix takes about thirty seconds to implement on your end.
Common Pitfalls People Miss
The first thing that goes wrong is hearing and vision screening. Many departments use OSHA-level audiometry and Snellen charts. If you wear hearing protection or prescription lenses, bring them. The examiner will test with and without your correction. If you fail the uncorrected portion, you may still pass with correction. But if you forget to bring your glasses or your hearing aids, the result gets recorded as a failure and you will be scheduled for a remediation visit. The second pitfall involves the drug screen. Some departments include a standard five-panel or ten-panel screen as part of the annual physical. Others do not, and only conduct random or post-incident testing. If your department does include it, be aware that certain over-the-counter medications, particularly decongestants containing pseudoephedrine, can trigger false positives on amphetamine screens. I have seen two firefighters in my network flag positive for amphetamines because they had taken a cold medication the night before their physical. Both tested clean on the follow-up immunoassay confirmation, but the delay was real. If you take any OTC medication daily, ask your department's medical coordinator whether it is an issue and whether pre-authorization can be added to your record ahead of time. Cardiac screening is where most people feel the most pressure. The standard resting EKG is a routine part of the physical. A normal reading clears you. An abnormal reading does not automatically disqualify you, but it will trigger a cardiology referral. Early repolarization, benign premature ventricular contractions, and minor conduction delays show up on EKGs frequently and are usually not clinically significant. However, the review process takes time. Scheduling a cardiology consult outside the department network can add four to six weeks to your clearance timeline. If you have a known cardiac history, get a recent cardiology note before your annual physical so you can submit it proactively and potentially skip the referral step.

What the Physical Does Not Cover
It is important to understand the limitations of the annual physical. It is not a comprehensive diagnostic workup. It is a baseline screening tool designed to confirm that you meet the minimum medical standards for fire service duty. It will not catch early-stage conditions that do not present with measurable changes in blood work or vital signs at the time of testing. If you have been experiencing fatigue, unexplained weight changes, or joint pain that has developed gradually, the annual physical is the wrong venue to address it. Schedule a separate visit with your primary care provider and treat the physical as its own thing. There is also a gap between what the physical screens for and what NFPA 1582 actually requires for full certification. The annual physical is generally a surveillance-level assessment. NFPA 1582 has specific criteria for occupational medical fitness that go beyond the standard exam, including more rigorous cardiovascular evaluation and respiratory function thresholds for certain hazard assignments. If you are moving into a specialized unit like hazmat, technical rescue, or incident command, your department may require an additional NFPA 1582 compliance review that is separate from the annual physical. Check with your training officer before you assume the annual exam satisfies every requirement.
After the Exam
Once the exam is complete, the clinic sends results to your department's medical coordinator. You will typically receive a copy as well, either electronically or by mail. Review your results within a week. If anything looks incorrect or inconsistent with your known health history, contact the clinic and your department's health unit simultaneously. Discrepancies in lab values or recorded vitals get resolved faster when both offices are aware of the issue at the same time. Keep a personal file of every physical you have ever completed. Include the date, the clinic name, the forms used, and copies of all results. This becomes useful when you change departments, apply for disability reviews, or go through any subsequent medical evaluation. Starting from zero each time is unnecessary and slows down every process you will face in a career that spans decades. Firefighter Annual Physical Exam paperwork is not something you want to be rushing through on a Friday afternoon before a holiday. The structure is straightforward, but the details that matter are the ones nobody reminds you about until you are already in the room. Pay attention to the form your department requires, bring your medication list, clarify which labs need to be fresh versus reused, and keep your own records organized. That is the practical path through it.