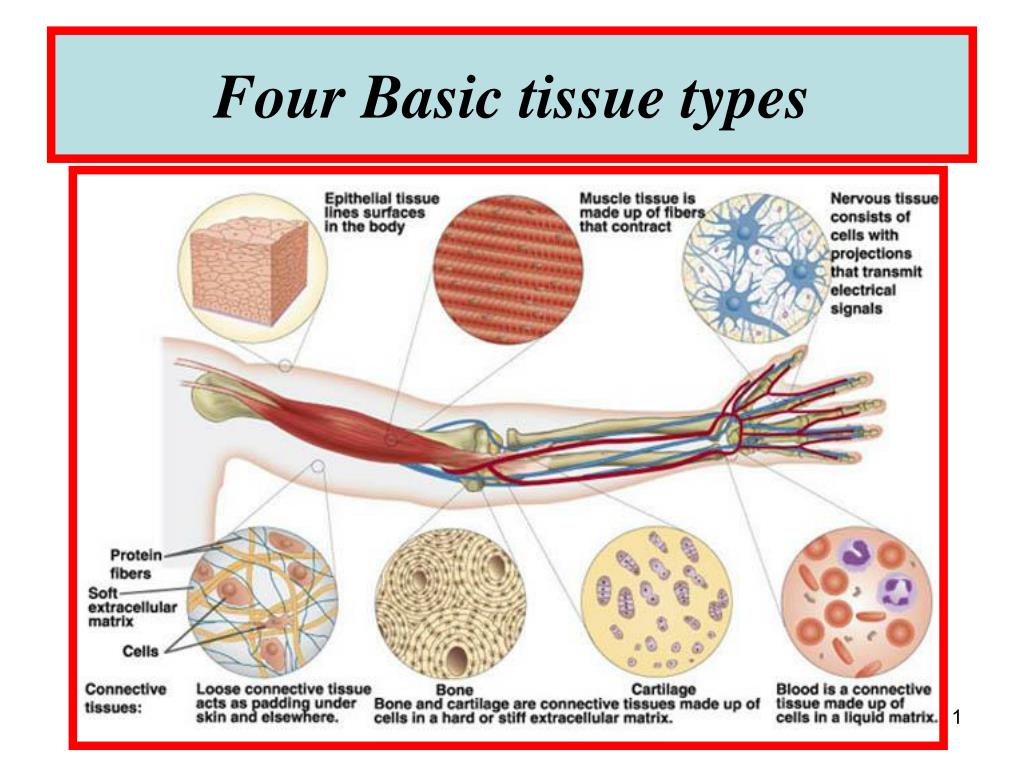
Four Basic Tissue Types
Most people learn about tissue types in a single semester of biology and then never touch the subject again. That works fine for passing an exam, but if you are actually working in histology, pathology, or even just trying to understand what is happening in a biopsy report, the classroom definitions leave out a lot of practical reality. I spent about six years running a clinical lab where we processed roughly forty thousand tissue sections a year. Most of those slides involved distinguishing between the four basic tissue types, and the ones that kept me up at night were rarely the textbook examples. Epithelial tissue lines surfaces, covers structures, and forms glands. It comes in a bewildering array of shapes and layers, but the core principle is that the cells are tightly packed with very little extracellular matrix between them. The basement membrane anchors everything to the underlying connective tissue, and loss of that boundary on a slide is usually the first red flag that something malignant is going on. I remember one case where a pathologist called me about a skin lesion that looked benign on low power but showed subtle disruption of the basement membrane at higher magnification. We revised the diagnosis from a simple keratosis to an early squamous cell carcinoma. That single detail saved the patient from waiting another six months to find out the truth. Connective tissue is the most diverse category, and that diversity is exactly why it causes so much confusion. You have loose areolar tissue, dense regular and irregular variants, adipose tissue, cartilage, bone, blood, and lymph. The common thread is that the cells are separated by a substantial extracellular matrix, which may be fluid, gelatinous, fibrous, or calcified. When I was training, the hardest part was learning to identify the different types of collagen fibers and how their arrangement changed based on mechanical stress. Dense regular connective tissue in a tendon looks nothing like dense irregular connective tissue in the dermis, even though both are predominantly collagen. Mixing them up on an exam is embarrassing, but misreading them in a diagnostic setting can change surgical margins significantly.
Muscle tissue has three subtypes, and each responds differently to injury and disease. Skeletal muscle is voluntary and striated, cardiac muscle is involuntary and striated with intercalated discs, and smooth muscle is involuntary and non-striated. The clinical relevance became obvious to me when we started seeing more cases of rhabdomyolysis in the emergency department. Patients who had been on statins or who had severe trauma would present with dramatically elevated creatine kinase levels, and the muscle biopsy would show extensive necrosis of the skeletal muscle fibers. The distinction between the muscle types matters because the regeneration capacity varies enormously. Skeletal muscle can regenerate fairly well through satellite cells, but cardiac muscle has almost no regenerative ability after a heart attack, which is why the scarring is permanent. Nervous tissue is the simplest to recognize and the hardest to work with properly. Neurons and glial cells form the parenchyma, and the tissue is almost entirely devoid of extracellular matrix. The problem is that nervous tissue preserves poorly in standard formalin fixation. Autolysis begins within minutes of death, and the characteristic Nissl substance in neuronal cell bodies degrades rapidly. In my experience, the best results come from using Carnoy's fixative or frozen sections when you need to examine neural architecture. We adopted a protocol where all brain biopsies were immediately snap-frozen in liquid nitrogen before any chemical fixation, and that made the difference between a diagnostically useful section and an unusable one every single time.
Four Basic Tissue Types in diagnostic practice
Understanding the four basic tissue types is not just an academic exercise. When you are reading a pathology report or examining a H&E stained slide, your brain should automatically categorize what it sees into one of these four groups. This classification guides everything from differential diagnosis to treatment planning. For instance, carcinomas arise from epithelial tissue, sarcomas from connective tissue, lymphomas from hematopoietic elements (which fall under connective tissue), and gliomas from nervous tissue. The distinction determines whether you are looking at a surgically removable mass or a systemic disease requiring chemotherapy. One common pitfall I encountered repeatedly involves mesenchymal tumors. These neoplasms can be confused with epithelial malignancies because they often display a nested or trabecular growth pattern. The key is to look for the presence or absence of basement membrane material and to use immunohistochemical stains appropriately. Cytokeratins mark epithelial differentiation, while vimentin is more broadly expressed in mesenchymal tissues. Desmin and smooth muscle actin help identify muscle origin, and S100 protein highlights neural crest derivatives. In one particularly tricky case, a tumor in the retroperitoneum was initially called a poorly differentiated carcinoma based on morphology alone. The immunoprofile eventually revealed it was a solitary fibrous tumor of mesenchymal origin, which completely changed the management strategy from aggressive chemotherapy to surgical resection alone. The four basic tissue types also interact constantly in physiological and pathological processes. Wound healing involves epithelial regeneration, connective tissue deposition, and sometimes smooth muscle involvement in blood vessel repair. Inflammation recruits cells from the hematopoietic system (connective tissue) into all other tissue types. Cancer metastasis follows specific routes that depend on tissue tropism, with epithelial cancers favoring lymphatic spread and sarcomas preferentially using hematogenous dissemination. These patterns are not absolute, but they are statistically significant enough to influence clinical decision-making.
Get the Full Details

Another area where the tissue classification proves useful is in regenerative medicine and stem cell therapy. Each of the four basic tissue types has a different reservoir of resident stem cells. Epithelial stem cells reside in the basal layer of stratified epithelia and in the crypts of the intestinal epithelium. Mesenchymal stem cells are found in bone marrow stroma, adipose tissue, and the perivascular niche of connective tissues. Cardiac stem cells remain controversial, while neural stem cells persist in the subventricular zone and hippocampus of the adult brain. Understanding where these cells live and how they behave under stress conditions has direct implications for tissue engineering strategies and personalized medicine approaches.
Limitations of the four-type model
Despite its ubiquity in education, the classification into four basic tissue types is a simplification that does not always map cleanly onto biological reality. Some tissues contain significant contributions from multiple categories, making pure classification impossible. The skin, for example, contains epithelial epidermis, connective tissue dermis, smooth muscle arrector pili, and nervous tissue endings, all working together as an integrated organ. Calling skin an epithelial tissue is like calling an orchestra a string section. The model is useful for teaching and for organizing diagnostic frameworks, but clinicians and researchers who treat it as a rigid taxonomy will occasionally run into problems. Developmental biology also complicates the picture. Neural crest cells migrate throughout the embryo and contribute to connective tissue, pigmented cells, peripheral neurons, and even smooth muscle in the vasculature. This single cell population generates derivatives that fall into at least three of the four basic tissue types, demonstrating that the categories are more useful analytically than they are fundamentally distinct during embryogenesis. Similarly, the endothelial cells lining blood vessels occupy a unique position between epithelial and connective tissue characteristics, possessing tight junctions like epithelia but residing within connective tissue compartments. Some histologists have proposed adding a fifth category for endothelial and lymphatic tissues, but this has not gained universal acceptance. In certain pathological conditions, tissues undergo metaplasia, transforming from one differentiated state to another. Barrett's esophagus represents a classic example where stratified squamous epithelium is replaced by columnar epithelium with goblet cells, presumably as an adaptation to chronic acid exposure. This transformation blurs the boundaries between tissue types and creates a premalignant condition that requires surveillance. The four basic tissue types framework helps us understand that such changes are possible, but it cannot predict when or why they will occur in any given patient. That requires understanding of genetic, environmental, and inflammatory factors that operate beyond the scope of basic histological classification.
Practical tips for studying and working with tissue types
If you are learning the four basic tissue types for the first time, start by examining real slides rather than relying solely on textbook illustrations. Digital slide repositories like the Digital Pathology Association or university teaching collections offer free access to thousands of high-resolution images. Practice identifying the hallmark features of each type under different magnifications. Epithelial tissue should show cellular polarity, connective tissue should reveal the matrix-to-cell ratio, muscle tissue ought to display striations or spindle shapes depending on the subtype, and nervous tissue should present neurons with their characteristic nuclei and nucleoli surrounded by smaller glial nuclei. Immunohistochemistry has revolutionized the way we distinguish tissue types and their derivatives. Panel selection depends on the diagnostic question, but a basic battery including cytokeratin, vimentin, desmin, S100, CD45, and SMA will resolve most classification dilemmas encountered in general practice. Take the time to understand what each marker highlights and what its absence means. A tumor that is cytokeratin-positive and vimentin-negative is likely epithelial, while the reverse profile suggests mesenchymal origin. Double-positive tumors exist and may indicate divergent differentiation or collision tumors, requiring additional markers for clarification. When working with clinical specimens, fixation quality directly affects your ability to distinguish the four basic tissue types. Under-fixed tissue appears pale and structureless, while over-fixed tissue becomes overly brittle and stains too darkly. The ideal fixation time for most organs is six to forty-eight hours in ten percent neutral buffered formalin, depending on specimen size. Bone biopsies require decalcification before processing, and the choice of decalcifying agent affects subsequent immunostaining. We found that formic acid decalcification preserved antigenicity better than hydrochloric acid-based solutions, allowing reliable detection of osteocalcin and other bone-specific markers. This small adjustment improved our diagnostic accuracy for bone lesions significantly without extending turnaround time.

Edge cases and uncommon presentations
Some pathologies challenge the standard classification system. Teratomas contain derivatives of all three germ layers and therefore may include mature or immature elements of all four basic tissue types, sometimes arranged in confusing patterns. A well-differentiated teratoma might show recognizable thyroid follicles, intestinal epithelium, cartilage, bone, and neural tissue in a single mass, making simple categorization impossible. The clinical behavior depends more on the presence of immature elements and their proportion than on the tissue composition itself. Malignant transformation within a teratoma represents a separate entity requiring distinct management. Chronic inflammatory conditions can obscure tissue architecture to the point where classification becomes difficult. Crohn's disease produces granulomatous inflammation that invades the bowel wall, disrupting the normal relationship between mucosal epithelium and submucosal connective tissue. Pericryptic fat wrapping and transmural inflammation are helpful clues, but in severe cases the tissue may appear so distorted that even experienced pathologists disagree on the diagnosis. In these situations, clinical correlation and sometimes molecular studies become necessary to reach a definitive conclusion. The four basic tissue types remain the foundation for understanding what is being disrupted, but they do not always provide clear answers when disease has advanced significantly. Age-related changes also affect tissue appearance. Thymic involution replaces lymphoid epithelial tissue with adipose connective tissue over decades, a process that can be mistaken for a neoplastic condition if the pathologist is unaware of the patient's age. Aortic stiffness increases with accumulated collagen cross-linking and calcification, changing the mechanical properties of the vessel wall without altering the fundamental tissue classification. Prostate glandular epithelium undergoes hyperplastic changes in older men, producing nodules composed of both stromal and epithelial components. Recognizing these normal variations prevents overdiagnosis and unnecessary interventions in elderly patients.
Why this classification still matters
Despite its limitations and the existence of exceptions, the model of four basic tissue types remains the most practical framework for organizing biological knowledge. Medical education, diagnostic pathology, surgical planning, and research all benefit from a shared vocabulary that classifies human anatomy into these fundamental categories. When a surgeon discusses resecting a sarcoma versus a carcinoma, the distinction determines whether lymph node dissection is indicated. When a pharmacologist develops a new drug targeting a specific receptor, knowing whether that receptor is expressed in epithelial, connective, muscular, or neural tissue predicts potential side effects and therapeutic windows. The four basic tissue types also provide a scaffold for understanding comparative anatomy and evolutionary biology. All vertebrates share these fundamental organizational principles, though the relative importance and specialization of each type varies across species. Birds emphasize epithelial adaptations for flight and reproduction, mammals show extensive connective tissue modifications for thermoregulation and locomotion, and amphibians retain permeable epithelial surfaces suited to their dual aquatic-terrestrial life. Recognizing these patterns helps biologists and veterinarians anticipate species-specific responses to injury, disease, and environmental change. The framework proves robust enough to transcend the particularities of human anatomy while remaining grounded in observable histological reality.


