Understanding Free Fluid Likely Physiologic in Clinical Practice
Free fluid likely physiologic is one of those phrases you'll see pop up on pelvic and abdominal ultrasounds more often than you'd think. It's not a dramatic finding. It's often nothing at all. But it trips people up, and I've spent enough years reading these reports to know where the confusion lands. The phrase appears when there's a small amount of anechoic fluid in the peritoneal or pelvic cavity, typically in the pouch of Douglas or around the liver. The sonographer or radiologist adds "likely physiologic" because the quantity is small, the appearance is simple, and the clinical context suggests a benign cause. In postmenopausal women, the calculus shifts significantly. Free fluid in that population demands more scrutiny.
What Free Fluid Likely Physiologic Actually Means
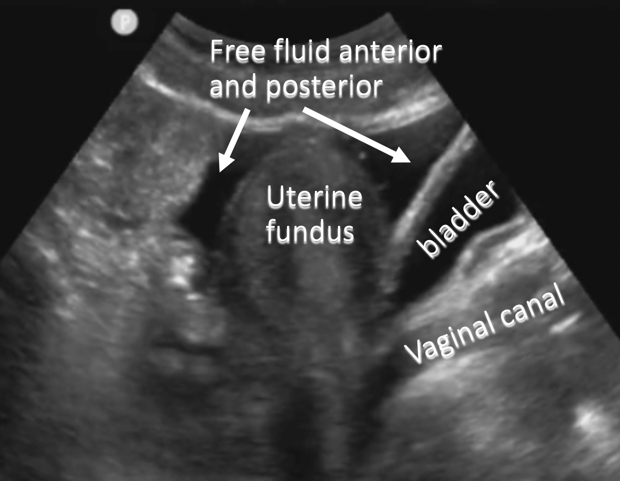
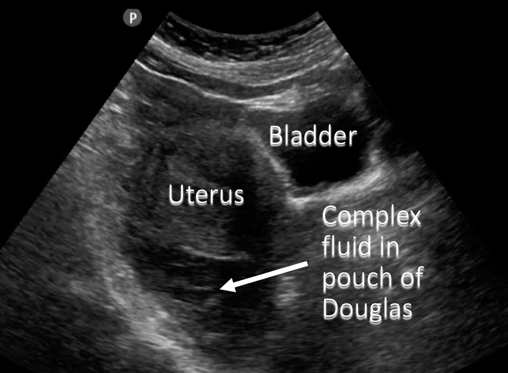
Physiologic free fluid is normal. Women of reproductive age frequently have small amounts of fluid in the pelvis, especially around ovulation when follicular fluid leaks from the ruptured follicle. The amount is usually less than two centimeters in deepest vertical dimension on transvaginal scan. It collects in the most dependent portion of the pelvis because of gravity. That's it. That's the whole concept. The ultrasound machine picks it up as anechoic black space between structures. It has no internal echoes, no septations, no debris. Simple fluid. On CT it shows up as water-density material hugging the bowel loops or settling in the paracolic gutters. The report writer sees it, measures it, and qualifies it as likely physiologic based on size and appearance. Here's where beginners get tripped up. The word "likely" in the report is doing a lot of work. It means the reader isn't certain. They're leaning toward benign but haven't ruled out other causes definitively. That's honest reporting. It's also a phrase that patients latch onto and google at 2 AM.
How I Actually Read These Findings in Practice
I don't treat the phrase as a diagnosis. I treat it as a descriptor that needs clinical correlation. The first thing I check is the patient's age and sex. A premenopausal woman with a small fluid collection and a normally appearing ovary on the same side gets far less attention than a postmenopausal woman with the same finding. In my practice, any free fluid in a postmenopausal patient triggers a review of the ovaries, the omentum, and the liver surface. If everything else looks clean, I still recommend follow-up in six months because the consequences of missing something are asymmetrical. I also look at the volume. Two centimeters of fluid is different from five centimeters. The measurement matters more than the qualifier. A collection greater than three centimeters in the pouch of Douglas in a woman who isn't mid-cycle usually gets a second look or a repeat scan in the early follicular phase, before ovulation would create fluid anyway. One edge case I run into repeatedly involves post-operative patients. After any abdominal surgery, particularly gynecologic surgery like hysterectomy or ovarian cyst removal, small amounts of free fluid are expected. The body produces inflammatory exudate as part of normal healing. I've had residents flag these as pathological on initial read because they saw fluid and panicked. The workaround is straightforward: check the surgical history. If the patient had an operation within the past few weeks, a small amount of free fluid is a normal postoperative finding and doesn't require intervention. I document the surgery date in the impression section so the next clinician reading the report doesn't repeat the alarm.
Get the Full Details

Common Pitfalls That Waste Time
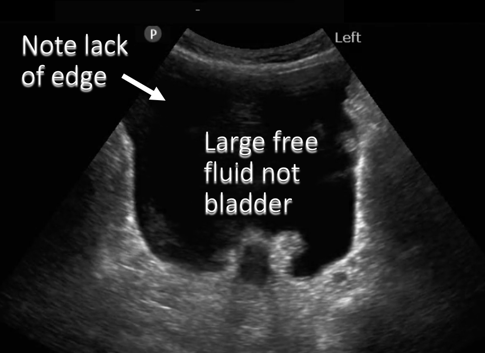
The biggest mistake I see is treating every instance of free fluid as a problem to solve. It isn't. In young women with mild pelvic pain, the fluid is often just ovulation-related and resolves on its own within a week. Ordering a CT after an ultrasound already characterized the fluid as simple adds radiation exposure and cost without changing management. I've seen this happen in my own hospital. A patient came in with right lower quadrant pain, got a pelvic ultrasound that showed free fluid likely physiologic, and then someone ordered a CT abdomen pelvis with contrast because they didn't trust the ultrasound interpretation. The CT showed the same thing. No appendicitis. No diverticulitis. Just fluid. The patient absorbed both the radiation and the anxiety for no clinical benefit. Another pitfall is ignoring the clinical context entirely. Free fluid in a patient with known cirrhosis is almost certainly ascites, not physiologic fluid. The report phrase might be identical, but the management pathway diverges completely. I always flag when the clinical history changes the interpretation. A line in the impression like "in the setting of known portal hypertension, this fluid is more consistent with early ascites" is worth more than a vague description. There's also the issue of technical artifacts. A poorly positioned transducer or excessive pressure from the probe can sometimes create an artifact that mimics a small fluid collection. I've encountered this a handful of times where what looked like free fluid on a quick scan disappeared when I repositioned the patient or used a different approach. Always double-check suspicious findings before committing them to the report. It takes ten seconds and prevents unnecessary follow-up studies.
When to Escalate and When to Wait
The scenarios that actually matter are the ones where the fluid isn't simple. Septated fluid, echogenic fluid, or fluid with debris suggests hemorrhage, infection, or malignancy. Those findings don't get labeled likely physiologic and they shouldn't be managed expectantly. If the report uses that qualifier, the fluid is simple and the amount is small. That's the entire decision tree. For asymptomatic premenopausal women, no follow-up is needed. The fluid will resolve. For symptomatic patients, treat the symptoms and reassess if they persist beyond the expected timeframe. For postmenopausal women, even small amounts warrant a conversation with the patient and often a follow-up scan, because the baseline risk profile is different. I generally recommend transvaginal ultrasound as the primary imaging modality for pelvic free fluid evaluation. It provides better resolution than transabdominal scanning for small collections. If the transvaginal study is inconclusive or the fluid extends higher into the abdomen, a limited transabdominal scan or CT can characterize the extent. I rarely order MRI for this indication unless there's a specific question about the uterine or ovarian parenchyma itself.
The phrase Free Fluid Likely Physiologic is not a crisis. It's a snapshot of a common finding that sits somewhere between normal and worth watching. The trick is knowing which side of that line any given patient falls on, and that depends almost entirely on context that the imaging report alone doesn't provide.