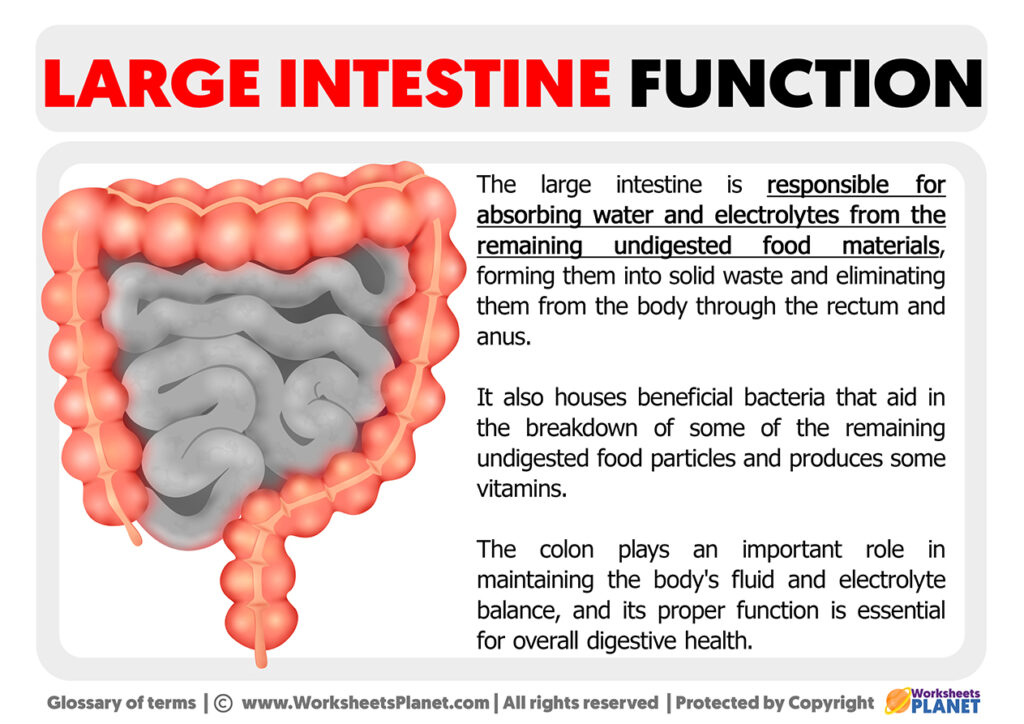
The large intestine receives a watery slurry of partially digested food from the small intestine and gradually turns it into solid waste. Most people know that much. What they don't realize is that the organ does far more than just dry out stool, and getting the details wrong is what causes most GI complaints in the first place.
The Function Of Large Intestine spans water and electrolyte reclamation, bacterial fermentation, mucus secretion, and the controlled storage and expulsion of feces. Each of those tasks happens in a different section, and the mechanisms are not interchangeable.
The Core Function Of Large Intestine Explained
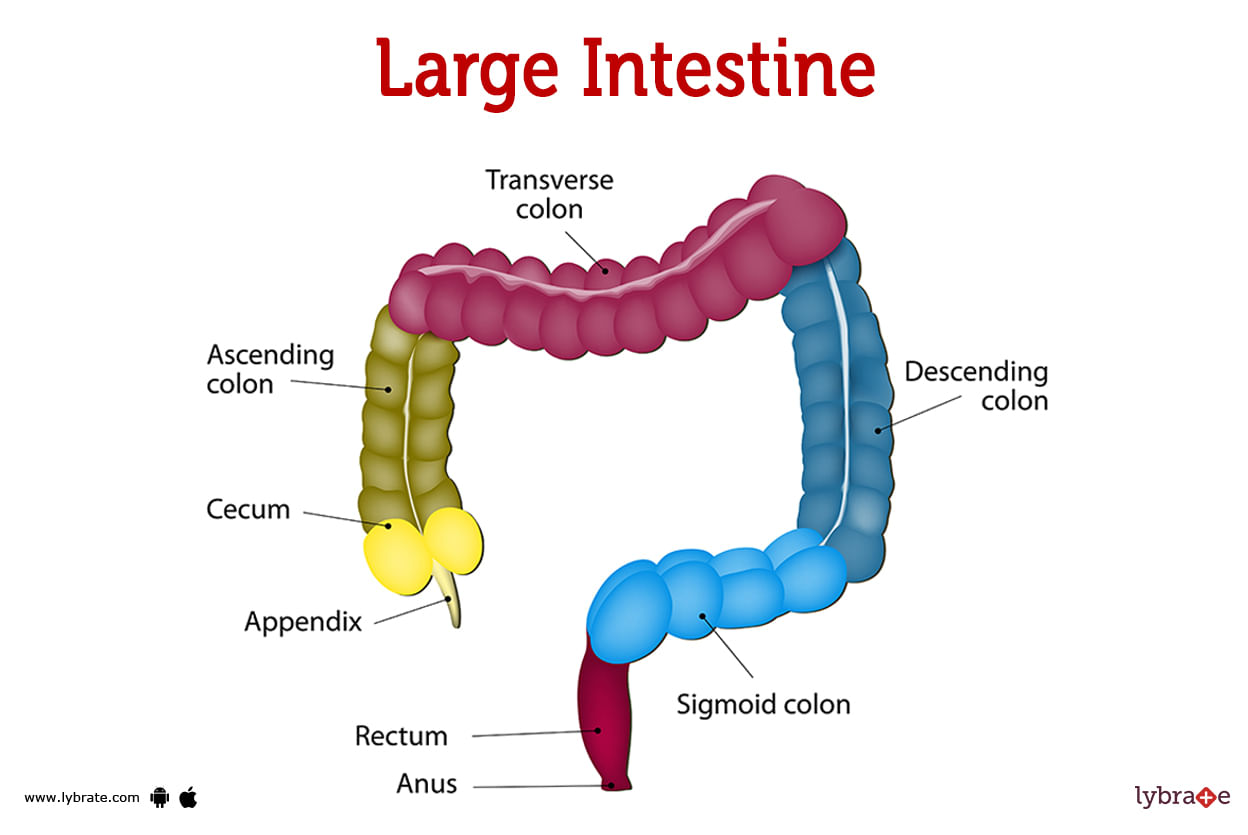
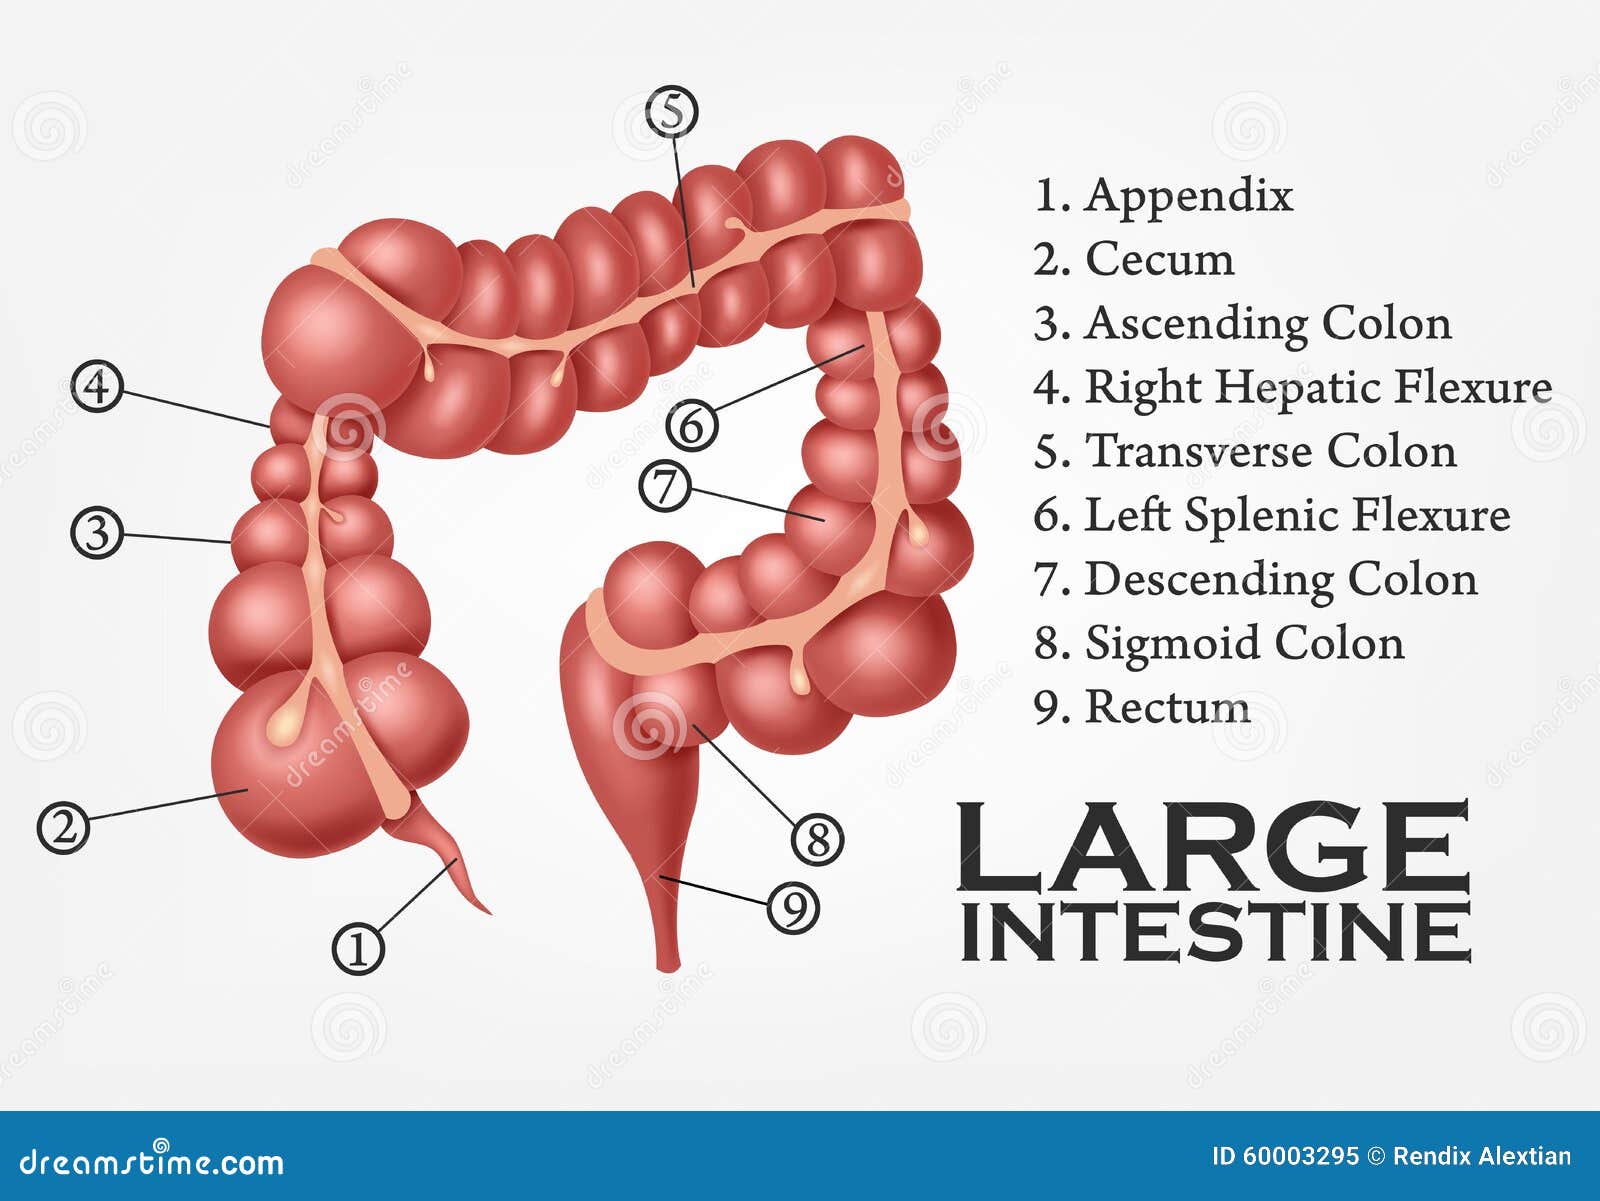
The organ measures roughly five feet long and is divided into the cecum, ascending colon, transverse colon, descending colon, sigmoid colon, and rectum. Food material enters through the ileocecal valve, which acts as a gatekeeper and normally stays closed to prevent backflow from the colon into the small intestine.
Water absorption is the primary mechanical job. The small intestine secretes about nine liters of fluid daily through digestive juices, saliva, and bile. By the time chyme reaches the colon, roughly eight liters of that water still needs to be reclaimed. The colon absorbs about seven to eight liters per day under normal conditions. What remains becomes the water content of formed stool, typically around 100 to 200 milliliters in the final output.
Electrolyte handling runs alongside water. Sodium is actively transported out of the lumen through epithelial channels, and chloride follows. Potassium moves in the opposite direction, which is why prolonged diarrhea depletes body potassium stores faster than people expect. The remaining fluid balances out into an isotonic state by the time it reaches the rectum.
Bacterial Fermentation and Short-Chain Fatty Acids
The colon houses approximately three hundred to five hundred billion bacteria, mostly anaerobic species like Bacteroides, Clostridium, and Firmicutes. These organisms ferment undigested carbohydrates that the small intestine could not break down. The primary products are short-chain fatty acids, mainly acetate, propionate, and butyrate.
Butyrate serves as the main energy source for colonocytes, the epithelial cells lining the colon. Without adequate butyrate production, the mucosal barrier weakens and permeability increases. This is not a theoretical concern. Patients with ulcerative colitis consistently show reduced butyrate concentrations in colonic contents compared to healthy controls.
The bacterial process also produces certain vitamins, particularly vitamin K and some B vitamins like biotin and folate. The amount absorbed from colonic synthesis is modest but meaningful for people with restricted diets or compromised small intestinal function. Gas production is a byproduct that most people experience as flatulence or bloating. Methanogens in some individuals convert hydrogen and carbon dioxide into methane, which explains why roughly one in three people pass methane-dominant gas rather than hydrogen-dominant gas.
Movement, Storage, and Expulsion
Colonic motility operates through two distinct patterns. Haustral churning mixes contents slowly within individual haustra, the small pouches created by taeniae coli contractions. This mixing allows extended contact time between the mucosa and luminal contents for absorption to occur. Mass peristalsis, by contrast, is a much stronger wave that pushes material forward in bulk, usually occurring two to four times per day and often triggered by the gastrocolic reflex after eating.
The rectum stores feces until defecation becomes socially appropriate. Stretch receptors in the rectal wall fire when the volume reaches roughly 25 to 50 milliliters, sending signals through the pelvic nerves to the spinal cord and brain. The internal anal sphincter, made of smooth muscle, contracts automatically in response to rectal distension. The external anal sphincter, composed of skeletal muscle, remains under voluntary control and can be consciously relaxed or tightened.
Defecation requires coordinated relaxation of both sphincters along with increased intra-abdominal pressure through Valsalva-like maneuvers. Straining too hard or too frequently can contribute to hemorrhoids and pelvic floor dysfunction over time.
Common Problems and What Actually Works
I dealt with a patient last year who had been taking psyllium husk for constipation every single day for three years without any improvement. The issue was not the type of fiber. The issue was that his transit time was severely delayed, likely from hypothyroidism that had gone undiagnosed for months. Psyllium adds bulk, but if the colon is not contracting properly, adding bulk only makes the problem worse. We ran a TSH panel, confirmed subclinical hypothyroidism, started levothyroxine, and his bowel movements normalized within six weeks. The psyllium was not the enemy, but it was also not the solution.
Here are a few things most people miss about colonic function:
Slow transit and rapid transit affect water absorption in opposite ways, but both can produce hard stool. In slow transit, water gets absorbed excessively because contents linger too long. In rapid transit, the colon simply does not have time to absorb water properly, which can paradoxically lead to small, pellet-like stools if the material is not moving fast enough to trigger the normal water-retention feedback loops. The stool appearance alone does not tell you whether the problem is upstream or downstream.
Opioid-induced constipation works through mu-opioid receptors located directly on enteric neurons in the colon wall, not just in the brain. These receptors suppress peristalsis and increase fluid absorption. Standard laxatives often fail here because the underlying mechanism is receptor-mediated inhibition of neural signaling. PEG-based osmotic laxatives or prescription agents like methylnaltrexone target this differently.
Irritable bowel syndrome involving the colon (IBS-C or IBS-D) is not a structural disease. The mucosa looks normal under endoscopy. The problem lies in visceral hypersensitivity and dysregulated motility patterns. Fiber supplementation helps some patients and worsens symptoms in others depending on whether their issue is primarily motility-related or fermentation-sensitive. Soluble fiber tends to help; insoluble fiber often aggravates.
When the System Breaks Down
Diverticular disease is extremely common and directly related to colonic pressure dynamics. When intraluminal pressure rises chronically, often from low-fiber diets and prolonged straining, the mucosa herniates through weak points in the muscular wall where blood vessels penetrate. This creates diverticula, mostly in the sigmoid colon where diameter is smallest and pressure is highest. Diverticulosis itself is asymptomatic in most people. Diverticulitis occurs when one or more diverticula become inflamed or infected, requiring antibiotics and sometimes surgical intervention.
Colonic ischemia affects older adults with vascular disease and presents with sudden abdominal pain and bloody stools. The watershed areas of the colon, particularly the splenic flexure, are vulnerable because they sit at the border zone between superior and inferior mesenteric artery supply. Reduced blood flow here causes mucosal injury and sloughing.
Colon cancer screening recommendations vary by country, but the principle is straightforward. Most colorectal cancers develop from adenomatous polyps over a period of ten to fifteen years. Detecting and removing polyps during colonoscopy prevents cancer from developing in the first place. The test is invasive and requires bowel preparation, which many people find unpleasant, but the alternative is late-stage diagnosis.
Practical Takeaways
Hydration matters more for colonic function than most people realize. Dehydration increases water absorption from the colon, producing harder and drier stool. Chronic mild dehydration is one of the most overlooked contributors to recurrent constipation.
Fiber type determines outcome, not just fiber quantity. Soluble fiber from oats, legumes, and peeled fruits absorbs water and forms gel, softening stool and feeding butyrate-producing bacteria. Insoluble fiber from wheat bran and raw vegetables adds bulk but can irritate a sensitive colon. A mixed approach works for most people, but if you have IBS or a history of diverticular disease, start with soluble fiber and introduce insoluble fiber cautiously.
Routine use of stimulant laxatives like senna or bisacodyl is not sustainable. These compounds irritate the colonic mucosa to trigger contractions. Long-term dependence can blunt the colon's natural motility response, making the organ less responsive to normal stimuli. Osmotic agents like polyethylene glycol do not carry the same risk of dependency but should still be used under medical guidance when constipation persists beyond two weeks.
Probiotics show mixed results for colonic health. Certain strains like Bifidobacterium lactis and Lactobacillus plantarum have modest evidence for improving transit time and reducing bloating in IBS patients. The effect is strain-specific and temporary. Stopping the probiotic usually returns symptoms to baseline. Diet modification through consistent fiber intake and fermented food consumption produces more durable changes in microbial composition.
The large intestine is not a passive pipe. It is an active metabolic organ that manages fluid balance, hosts a complex ecosystem, and regulates waste formation through coordinated neuromuscular activity. Understanding how each component works separately makes it easier to identify what goes wrong and which interventions actually address the root cause rather than just the symptom.
Gallery Function Of Large Intestine
Gkbooks - 🧠 Anatomy of the Large Intestine – Structure & Functions at a ...
Parts and functions of the large intestine – Artofit
Large Intestines Function _ Colon (Large Intestine): Anatomy, Function ...
Combining Form For The First Part Of The Large Intestine
Large Intestine Human Anatomy Stock Vector - Illustration of internal ...