Understanding Germline and Somatic Testing Workflow
The first thing most people get wrong about risk assessment is assuming the test result itself tells you what to do. It doesn't. The result is just data. Interpretation is where the actual work happens, and it's the part that takes time, patience, and enough exposure to clinical guidelines to know when an expert opinion is warranted versus when you can rely on automated scoring tools.
I spent about three years working in a molecular diagnostics lab before moving into clinical genetics counseling. One of the things I learned the hard way is that variant classification isn't binary. You can have a variant listed as likely pathogenic in one database and benign in another, depending on which population cohort was used for statistical weighting. This matters more than people realize.
The Genetic Cancer Risk Assessment Process in Practice
A proper assessment starts with pedigree analysis. Not the simplified family tree form you fill out at a pharmacy, but a structured three-generation interview. I remember one case where a woman came in with no apparent family history. She was 42, diagnosed with triple-negative breast cancer. Standard panels came back negative for BRCA1/2. On re-interview, I asked specifically about male relatives. Her maternal uncle had prostate cancer at 51, and his mother (her great-aunt) died of ovarian cancer at 58. That changed the pre-test probability dramatically.
The reason this matters is that risk models incorporate penetrance estimates by lineage. A variant in CHEK2 carries different lifetime risk depending on whether it's inherited from the mother or father in certain contexts. Not dramatically different, but enough that ignoring family structure introduces noise into the calculation.
After pedigree analysis, you select the appropriate gene panel based on personal and family history. The current standard panels cover around 30 to 50 genes for hereditary cancer predisposition. BRCA1, BRCA2, PALB2, ATM, CHEK2, TP53, PTEN, CDH1, STK11, and a dozen others. Each has a different evidence base for variant interpretation. Lynch syndrome genes (MLH1, MSH2, MSH6, PMS2, EPCAM) require different confirmation protocols because somatic hypermutation in the tumor can produce false positives if you don't do germline confirmation.
The testing itself is usually run as a next-generation sequencing panel with copy number variant detection. Most labs report turnaround times of two to four weeks. The bottleneck isn't the sequencing anymore, it's the bioinformatics pipeline and manual curation of variants of uncertain significance.
When the Data Gets Messy
VUS rates in hereditary cancer panels typically range from 15 to 30 percent, depending on the gene and the population being tested. A VUS means the lab has seen the variant but cannot confidently classify it as either pathogenic or benign. This is the most frustrating part of the process, and it's where most patients and even some clinicians feel stuck.
Here's what I found working in the lab: VUS rates are not randomly distributed. They cluster in certain genes and certain populations. For example, BRCA1 variants in Ashkenazi Jewish populations have much lower VUS rates because the founder mutations are well characterized. The same variant in a population of Southeast Asian ancestry might remain a VUS for years because there simply aren't enough sequencing data from that background in the databases.
I encountered a specific problem with a patient who had a BRCA2 variant classified as VUS at the time. The variant c.5946delT had been reported in a few cases of pancreatic cancer but lacked segregation data. The patient's family didn't want to participate in genetic studies. We ended up making management recommendations based on the clinical presentation rather than the variant classification alone, which meant prophylactic surgery discussions proceeded on the basis of family history and imaging findings, not the DNA result. It's not ideal, but it's how clinical genetics works when the evidence is incomplete.
The workaround we used was multiplexed PCR and Sanger sequencing of available relatives alongside the patient's original sample. This let us phase the variant and determine which parent it came from. In this particular case, it turned out the variant was inherited from the father's side, where no cancer history was documented. The absence of cancer in the paternal lineage didn't change the classification, but it did change the weight we gave it in counseling. We communicated this uncertainty clearly to the patient and recommended enhanced surveillance rather than risk-reducing surgery, pending further variant reclassification.
Risk Calculation Models and Their Limitations
Most risk assessment uses modified Gail, Tyrer-Cuzick, or BOADICEA models. Each has different input requirements and different performance characteristics. The Gail model, for example, doesn't include family history beyond first-degree relatives. It overestimates risk in women with strong familial predisposition and underestimates it in those without. The Tyrer-Cuzick model incorporates extended family history and polygenic risk scores, but requires more data input and can produce unstable estimates when family history is incomplete.
BOADICEA is the most comprehensive, incorporating multiple genes, polygenic scores, and detailed family history. It's also the most computationally intensive. Running a full BOADICEA assessment with polygenic risk scoring takes about 10 to 15 minutes on a standard workstation, compared to 2 to 3 minutes for Tyrer-Cuzick and 30 seconds for Gail.
The problem most people miss is that risk models are calibrated on specific populations. A Tyrer-Cuzick estimate derived from a UK cohort may not transfer accurately to an Asian or African population without recalibration. This isn't a theoretical concern. I've seen cases where a woman of South Asian descent received a lifetime risk estimate of 45 percent from a standard model, which then dropped to 28 percent after adjusting for population-specific penetrance data for the same variant.
Another issue is the handling of moderate-penetrance genes. Variants in ATM, CHEK2, and PALB2 confer risk that falls between high-penetrance BRCA variants and common low-penetrance SNPs. Risk models often treat these inconsistently. Some include them in the calculation, some don't. The evidence base for ATM and CHEK2 risk estimates has improved significantly since 2020, but many clinical decision support tools haven't caught up.
I recommend using at least two independent risk models when possible. If they produce concordant estimates, you can be more confident in the recommendation. If they diverge, you should flag the discrepancy and discuss it with the patient, explaining that the uncertainty comes from model limitations rather than test error.
What Happens After the Result
Management recommendations depend on the risk level and the specific gene involved. High-penetrance variants in BRCA1 or BRCA2 typically trigger enhanced surveillance starting at age 25, with risk-reducing surgery discussed between ages 35 and 40 depending on individual factors. CHEK2 and ATM variants usually recommend earlier mammography and possibly MRI, but risk-reducing surgery is not standard.
The gap between guideline recommendations and real-world implementation is where most system failures occur. I've reviewed charts where patients with confirmed pathogenic variants were never referred for genetic counseling. In some cases, the referring clinician didn't have access to the variant classification report. In others, the test was ordered through a direct-to-consumer service that didn't include confirmatory germline testing.
I encountered a case where a patient received a positive BRCA2 result from a commercial ancestry test. The variant was c.8753C>T, which is a known pathogenic mutation. But the commercial service had not performed confirmatory testing on a separate biological specimen. We had to repeat the test using a standard clinical laboratory before any management decisions could be made. This added approximately six weeks to the process and created unnecessary anxiety for the patient.
The takeaway is straightforward. Any variant found through non-clinical testing should be confirmed through a CLIA-certified or equivalent laboratory before clinical decisions are made. The turnaround time for confirmatory testing is typically two weeks, and the cost is usually covered by insurance when there's a documented family history.
One more thing that isn't widely discussed: risk assessment for cancer predisposition is not a one-time event. New variants are reclassified regularly, new genes are added to panels, and risk models are updated as penetrance data improves. A negative result today doesn't guarantee a negative result tomorrow if new evidence emerges about a gene that wasn't previously tested. I recommend periodic re-evaluation every three to five years for patients with incomplete panel results or variants of uncertain significance, and annually for those with high-penetrance pathogenic variants in the family.
Gallery Genetic Cancer Risk Assessment
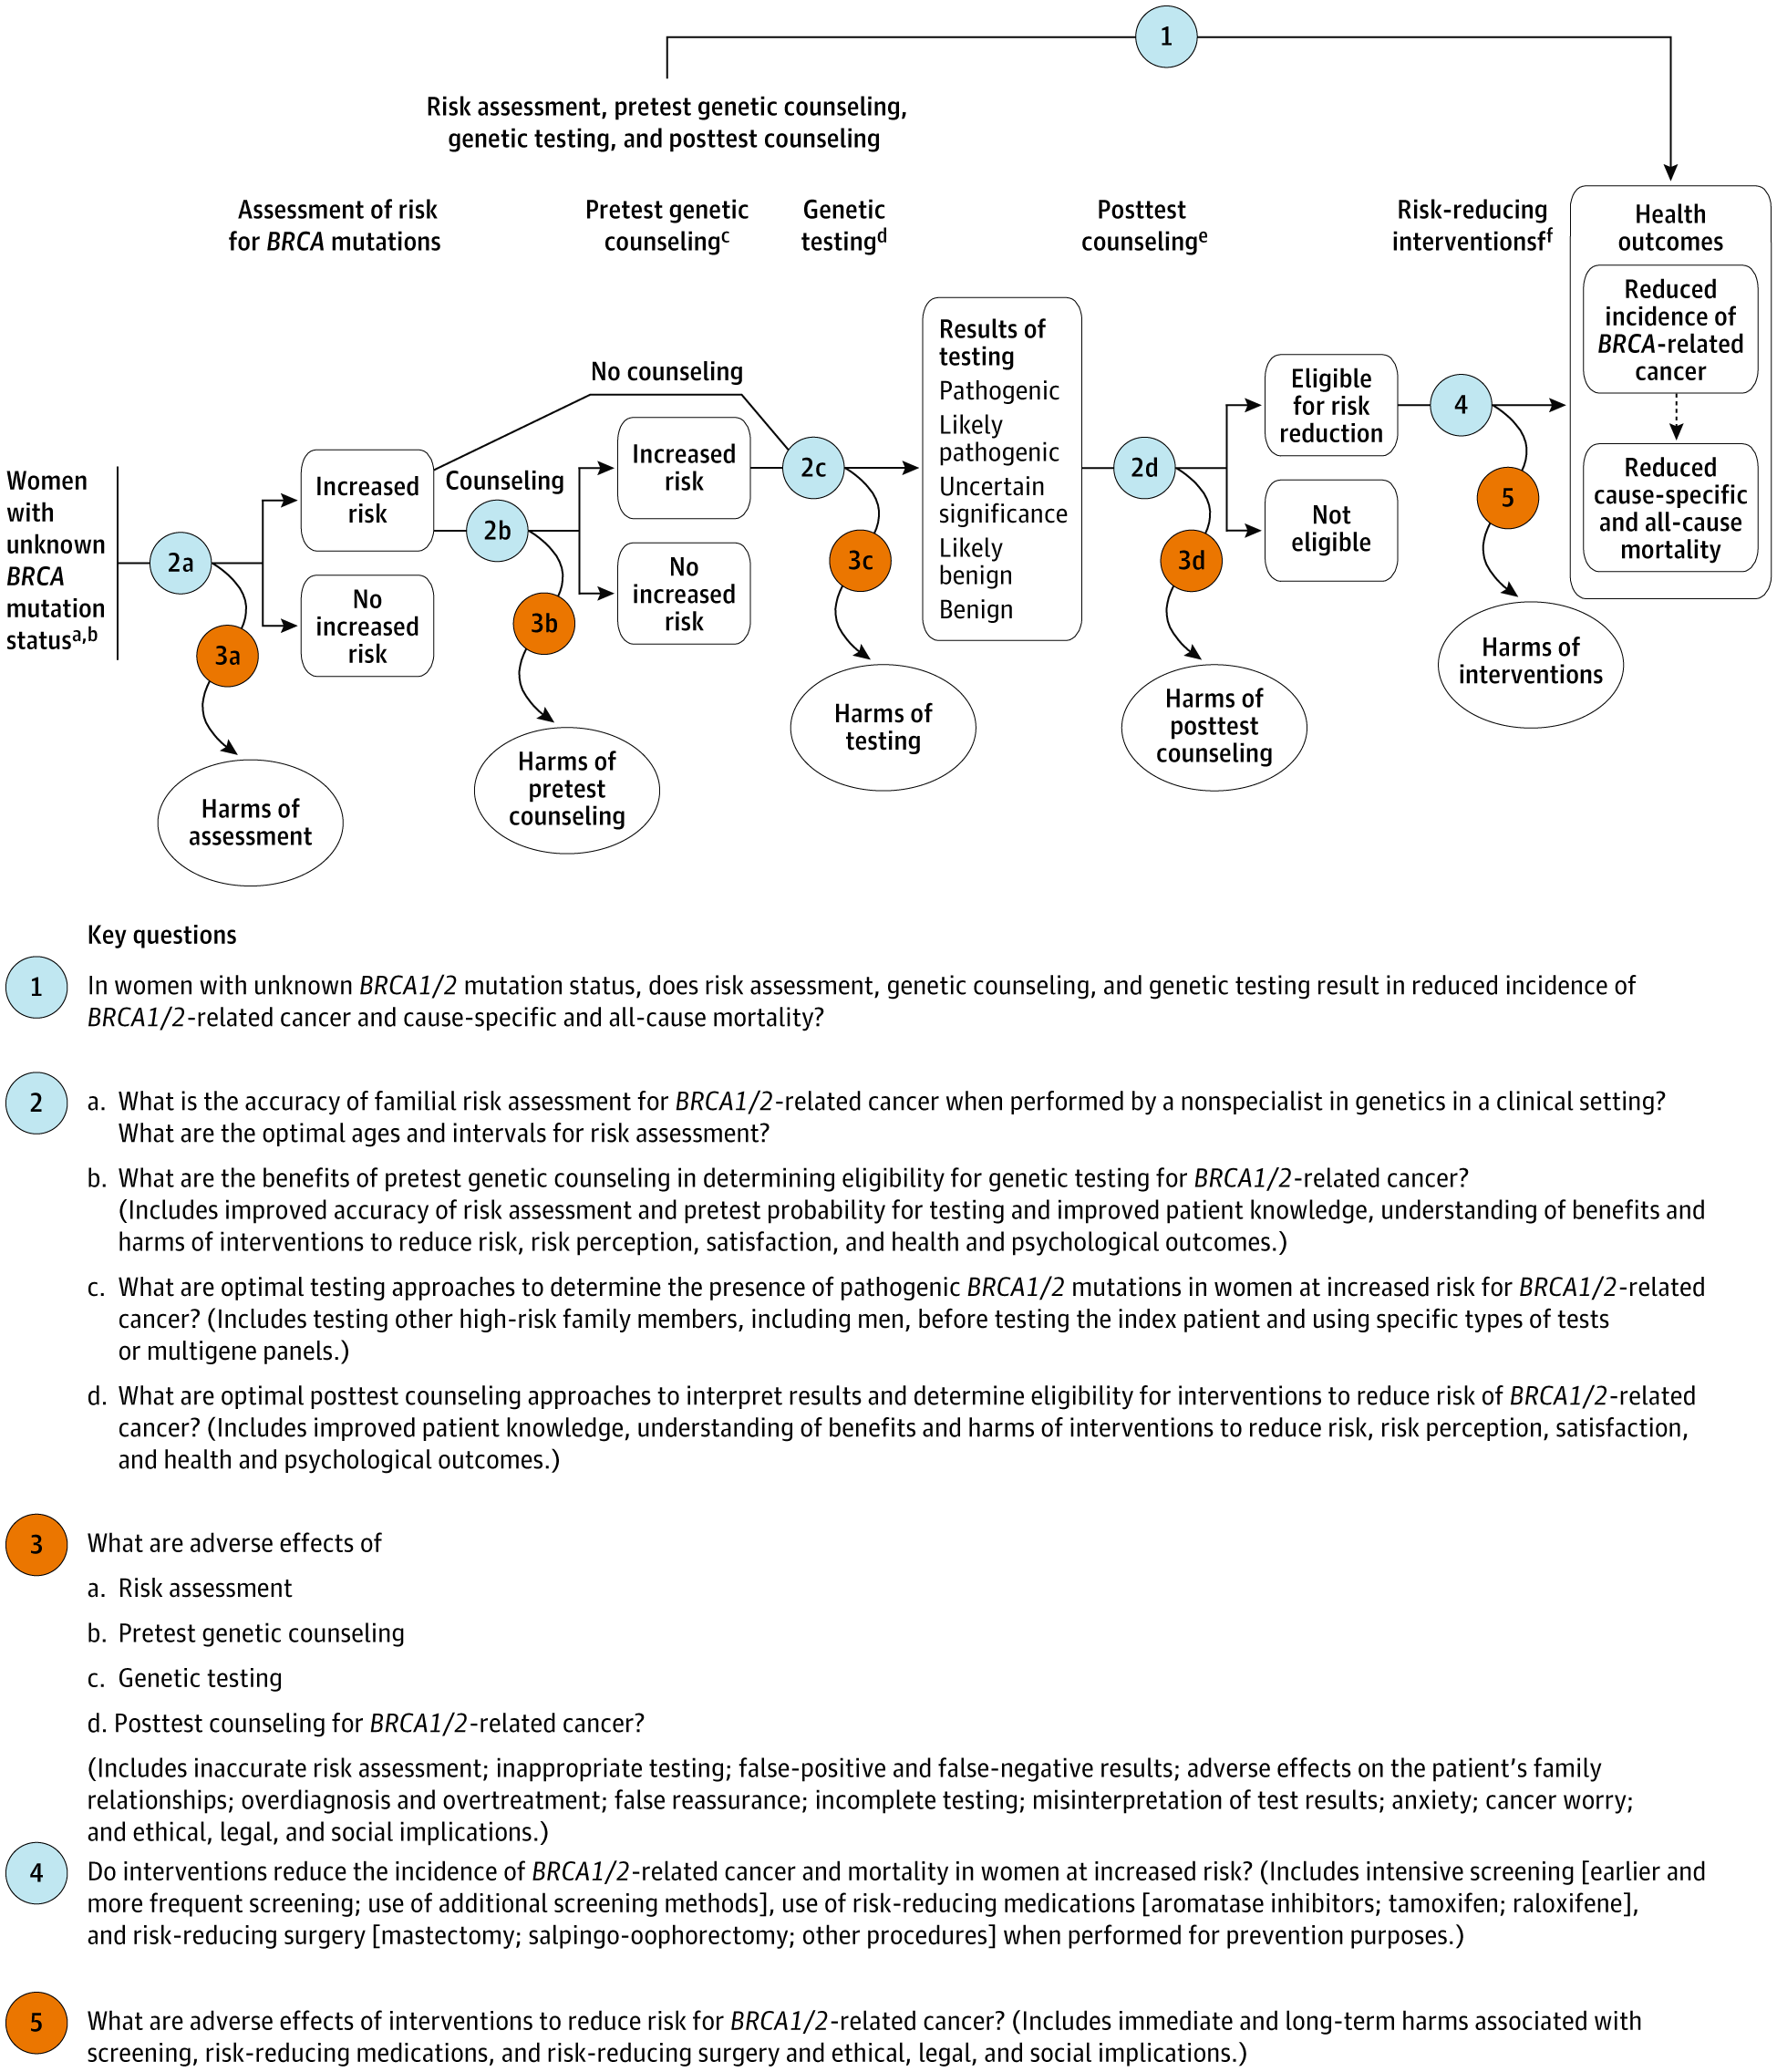
Risk Assessment, Genetic Counseling, and Genetic Testing for BRCA-Related Cancer in Women ...
Hereditary Cancer Genetic Risk Assessment, Testing, and Counseling: A Nurse Practitioner–Led ...
Draft Research Plan: BRCA-Related Cancer: Risk Assessment, Genetic Counseling, and Genetic ...
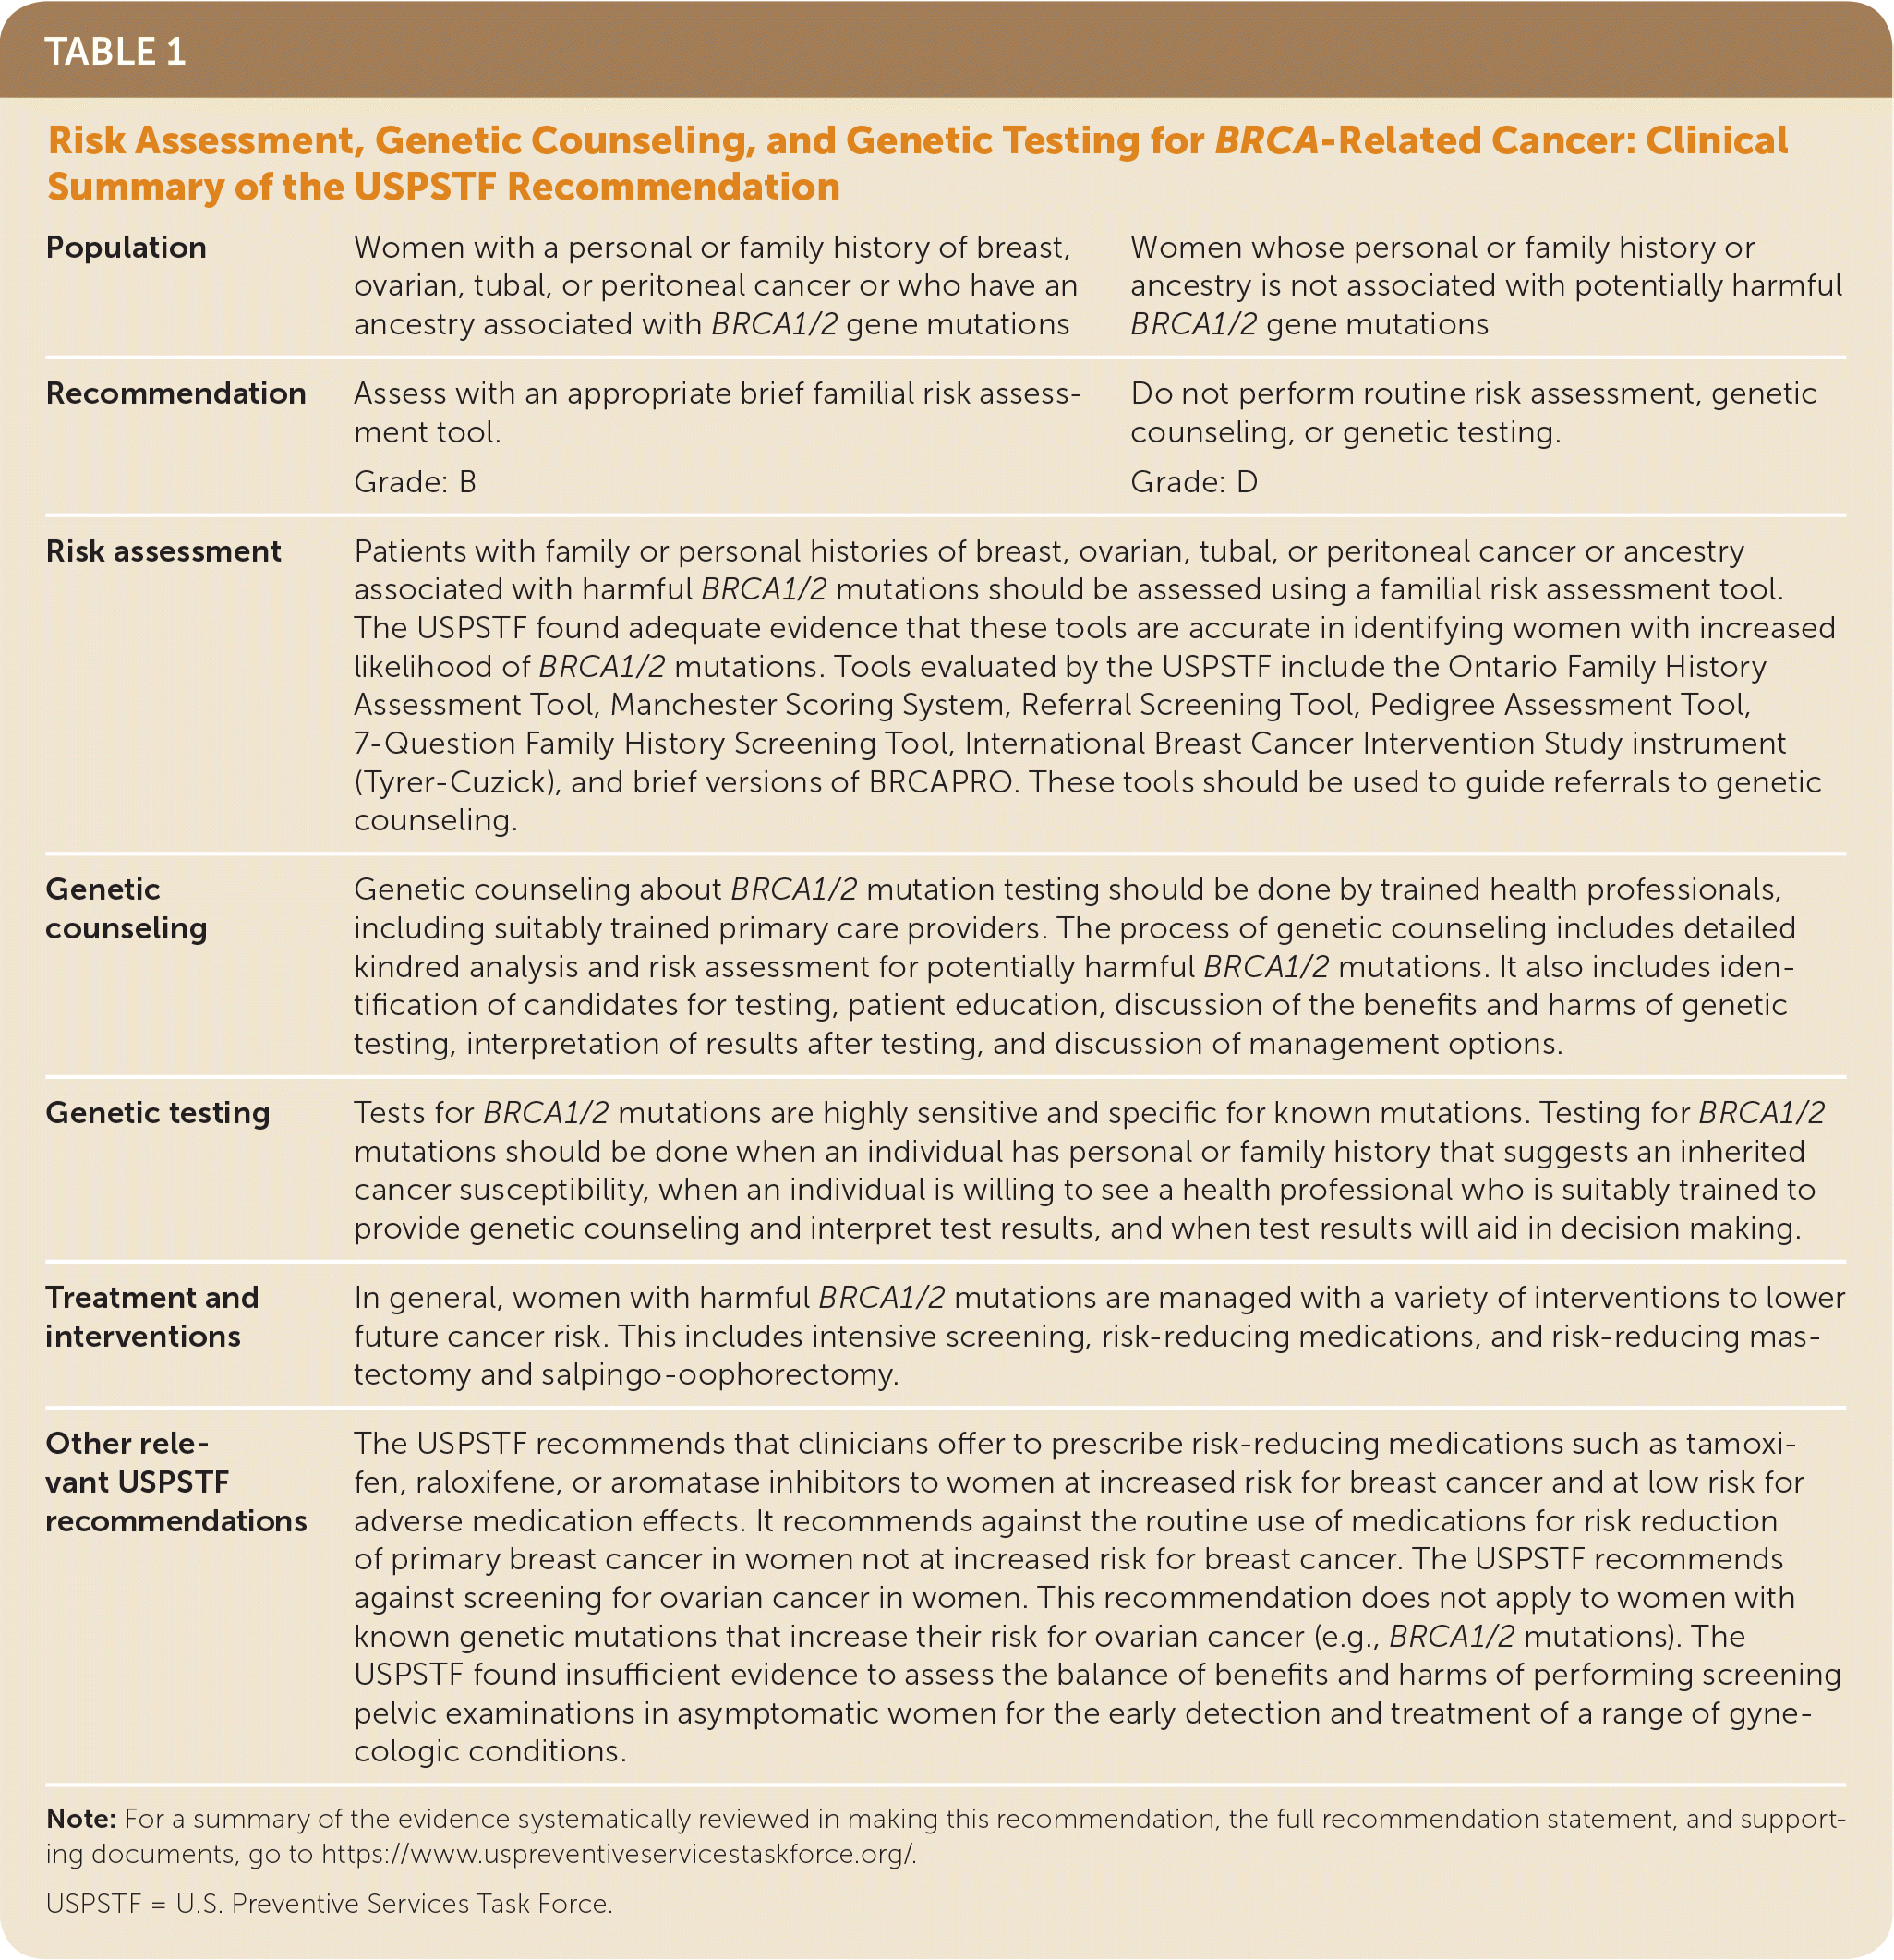
Risk Assessment, Genetic Counseling, and Genetic Testing for BRCA-Related Cancer: Recommendation ...
Cancer genetic risk assessment guidelines exp | EurekAlert!