What a GU Assessment Actually Looks Like on a Real Ward
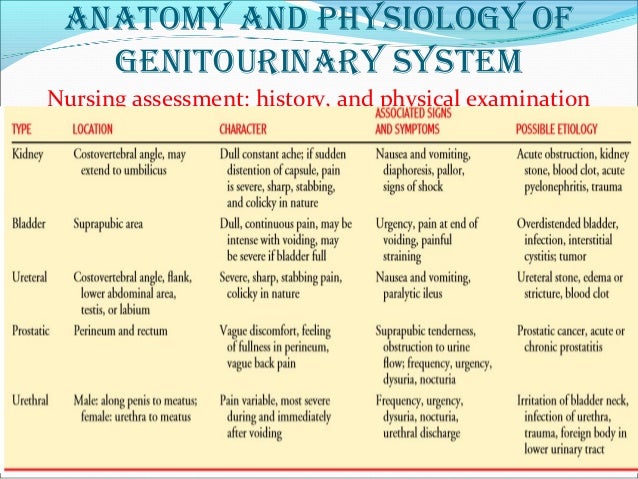
A genitourinary nursing assessment is a systematic evaluation of the patient's urinary and reproductive systems. It covers history, physical exam findings, and functional status. Most students get this wrong because they treat it like a checklist instead of a clinical reasoning process. I'll walk through how it actually works in practice. Start with the history. You need to ask about frequency, urgency, dysuria, hematuria, incontinence type, fluid intake patterns, and any history of UTIs or prostate issues. For female patients, include menstrual and obstetric history. For males, ask about erectile function and urinary stream changes. Don't skip bowel habits either. Constipation directly affects urinary retention and is one of the most commonly overlooked factors in my experience. Here's something most textbooks don't emphasize enough: when you're assessing for retention, asking the patient to drink 500ml of water and then timing their void isn't just a textbook exercise. I ran into this with an elderly male post-op hip replacement who was clearly holding urine but denying the sensation. The bladder scan showed 600ml. The whole "encourage fluids then monitor output" approach was missing the point because he had sensory neuropathy from undiagnosed diabetes. The workaround was straightforward: schedule straight catheterization at fixed intervals rather than waiting for him to report discomfort. He'd been sitting in 400ml increments for two days without telling anyone because he genuinely couldn't feel it.
Genitourinary Nursing Assessment Example
Take a 72-year-old female admitted with community-acquired pneumonia. Here's what a proper GU component looks like: Subjective data: Reports occasional stress incontinence with coughing (which is expected given her pneumonia). Denies dysuria, frequency, or hematuria. Last voided 4 hours ago. Drinks approximately 1.5 liters daily. No history of UTIs in the past year. Uses panty liners, changed every 4-6 hours per her report. Objective data: Abdomen soft, non-distended. Suprapubic region non-tender. No costovertebral angle tenderness bilaterally. Skin around perineal area intact, no signs of irritation or breakdown. Urine output in Foley bag approximately 30ml since insertion 6 hours ago during surgery - this is concerning. Urine appears cloudy with a strong odor. Patient's vital signs show temperature 38.1°C, heart rate 98 bpm. White blood cell count is elevated at 14,200.
The assessment here isn't just documenting findings. The low urine output combined with cloudiness and systemic signs points toward a possible catheter-associated UTI with some degree of obstruction or dehydration. The nursing diagnosis would include impaired urinary elimination related to catheterization and possible infection, along with risk for deficient fluid volume. Physical examination technique matters more than people realize. When doing a renal percussion, use the flat palm of one hand against the patient's costovertebral angle and tap it firmly with the fist of your other hand. Pain response indicates possible pyelonephritis or renal calculi. But here's the counter-intuitive part: absence of CVA tenderness doesn't rule out renal pathology in elderly or diabetic patients. Their pain perception is blunted. I had a diabetic patient with a renal abscess who had zero CVA tenderness. The fever and elevated inflammatory markers were the only clues. Always correlate physical findings with labs and imaging, never rely on percussion alone. For female patients, external genital inspection should note any lesions, discharge, or signs of atrophy. Postmenopausal women often have thinning mucosa that can be mistaken for infection when it's actually estrogen deficiency. A quick visual check followed by a discussion about vaginal symptoms can prevent unnecessary antibiotic prescriptions.
Get the Full Details

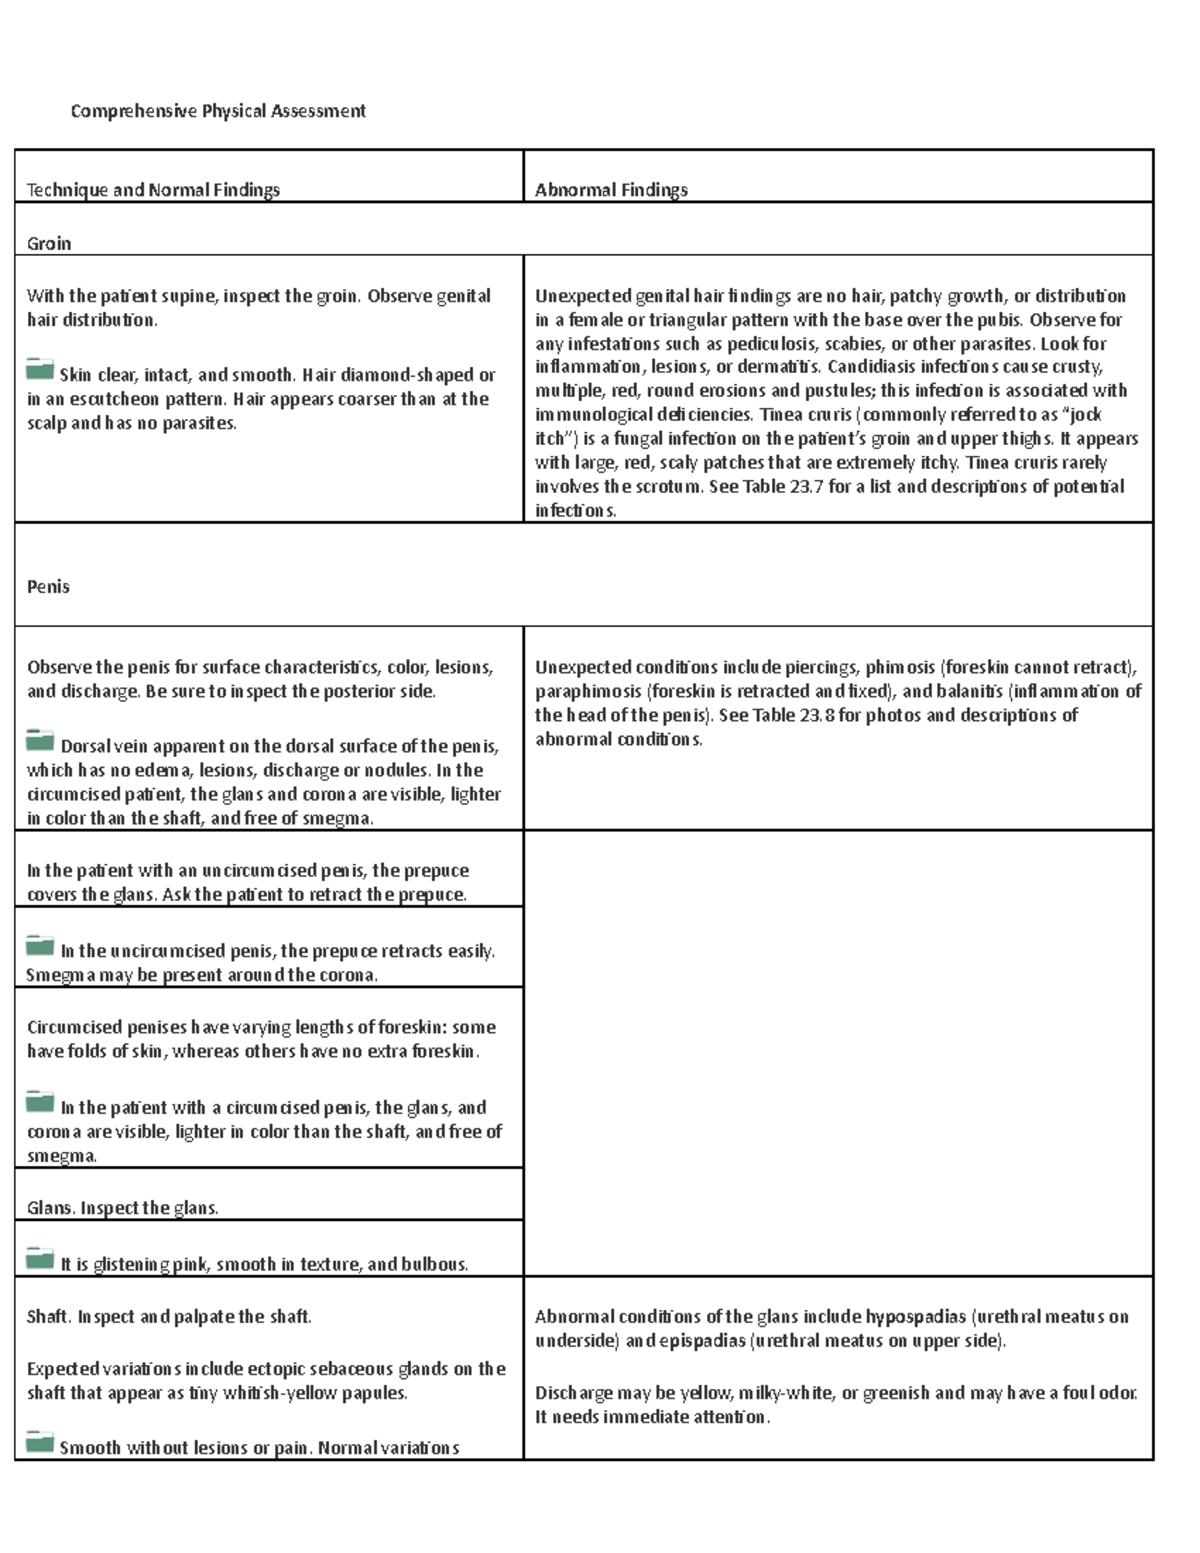
Male assessments require discussing testicular examination when clinically indicated. Most junior nurses avoid this entirely or rush through it. A proper testicular exam checks for masses, variability in consistency, and tenderness. Use both hands, gently rolling each testis between the thumb and fingers. The epididymis sits posteriorly and is normally palpable - don't mistake it for a mass. I once saw a resident refer a patient for ultrasound because he thought the epididymis was a tumor. The radiologist spent thirty seconds confirming it was normal anatomy. Documentation is where things fall apart most often. Write specific volumes, colors, and characteristics. "Cloudy urine" is acceptable. "Cloudy urine with visible sediment and foul odor" is clinically useful. Vague descriptions like "urine output adequate" are worthless. They tell nothing to the next clinician who picks up the chart. If you're using an electronic health record, don't let the drop-down menus replace actual descriptive writing. Those menus force you into categories that miss nuance. The biggest bottleneck in GU assessments is time pressure. On a busy medical-surgical floor, you might get twelve minutes for a full assessment including GU. That's enough if you're efficient, not if you're hunting for equipment or repositioning the patient repeatedly. Keep a focused GU assessment kit ready: lubricant, gloves, perineal care supplies, and a bladder scanner if available. Having everything within arm's reach cuts assessment time significantly. Without a bladder scanner, you're relying on percussion and palpation for volume estimation, which is unreliable above 150ml and basically guesswork below that threshold.
One more thing that isn't taught well: cultural and personal comfort considerations. GU assessments are invasive and embarrassing for many patients. Explain each step before you do it. Ensure proper draping. Offer a chaperone without making it feel like an afterthought. I've seen assessments delayed or refused because the nurse asked "do you need a chaperone?" in a tone that suggested it was a hassle rather than a standard of care. Frame it as routine safety practice and most patients appreciate it. When assessing urinary elimination patterns over time, consider keeping a simple voiding diary for patients with complex incontinence. Two days of documented intake and output with timing and leakage events often reveals patterns that a single assessment visit completely misses. This is particularly valuable for stress incontinence versus overflow incontinence differentiation, which can look identical in a brief exam but require opposite management approaches.