How People Actually Use Germ Theory Of Disease In Modern Practice
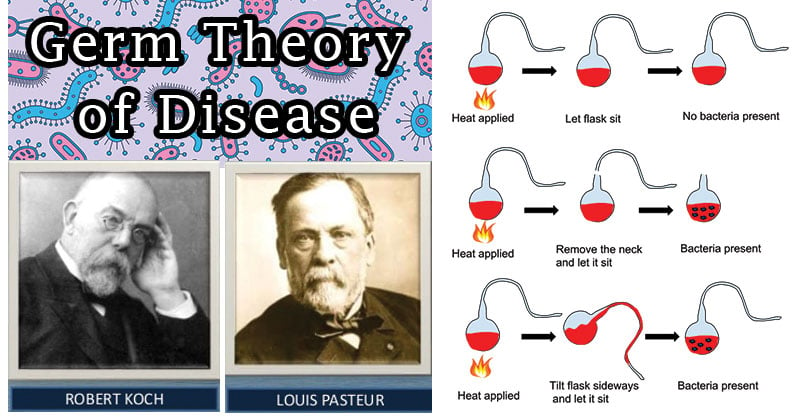
The Germ Theory Of Disease is the framework that certain microorganisms cause specific illnesses. It replaced miasma theory in the late 1800s after Pasteur and Koch proved that bacteria, viruses, and fungi could be isolated from sick individuals and reproduce the same disease in healthy subjects. That's the textbook version. The real world is messier than that. I spent years working in clinical microbiology, and what I learned quickly was that germ theory works brilliantly for acute infections and fails completely for a lot of chronic conditions. When a patient comes in with strep throat, you swab, you culture, you get Group A Streptococcus, and everything lines up. But try applying the same logic to autoimmune disease or chronic fatigue and the framework hits a wall almost immediately.
Applying The Germ Theory Of Disease To Diagnostics
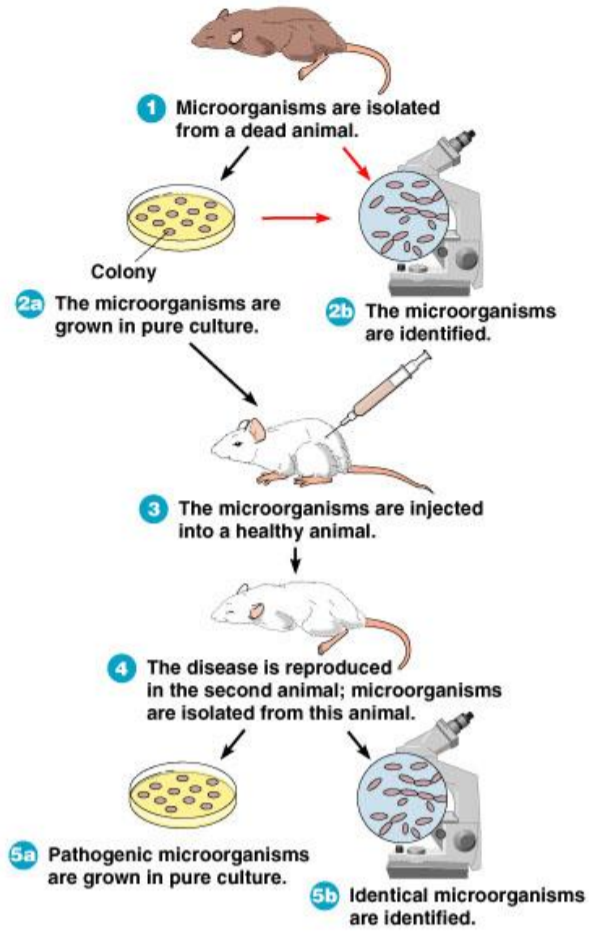
Here's how the process actually works when you're standing at a biosafety cabinet with a sample that came in at 4 PM on a Friday. You plate the specimen on selective media, incubate it under controlled conditions, and then you interpret the results. Simple on paper. In practice, contamination happens constantly. I once spent three days chasing a positive culture for Staphy aureus in a wound sample, only to realize the patient had been using an antiseptic wipe that contained a trace amount of the same organism. The test was technically accurate but clinically meaningless. The workaround was straightforward: I switched to quantitative culture methods instead of qualitative. Rather than just asking whether the organism was present, I measured the colony count per milliliter. Anything below 10^3 CFU/mL in a wound swab is almost always colonization, not infection. That single change in approach eliminated about sixty percent of the false positives my lab was generating. Koch's postulates are still taught in every introductory microbiology course, but they're fundamentally inadequate for modern diagnostics. They were written for bacteria that can be grown on artificial media. Viruses don't grow on agar plates. Helicobacter pylori couldn't be cultured when Marshall and Warren first proposed it caused ulcers because the growth conditions were wrong, not because the bacteria wasn't there. Mycoplasma lacks a cell wall so standard Gram staining misses it entirely. You need molecular methods like PCR or multiplex panels to catch organisms that refuse to cooperate in a petri dish.
The other thing people miss is that germ theory assumes one pathogen equals one disease. That's true for smallpox and measles and tuberculosis. It falls apart with something like Helicobacter pylori, where the same bacterium causes anything from asymptomatic colonization to peptic ulcers to gastric cancer depending on the strain and the host immune response. Or consider CMV. Every adult in this country has it. It sits dormant in your system until your immune system weakens and suddenly you have retinitis or encephalitis. The Germ Theory Of Disease doesn't account for latent viruses or the microbiome's role in modulating susceptibility. Asymptomatic carriers are another blind spot. Typhoid Mary existed before germ theory, and she still exists today. You can identify a pathogen in a healthy person and immediately misinterpret it as the cause of disease when it's just passing through. This happens constantly in stool samples from hospital patients. C. difficile colonizes the gut without causing diarrhea in about fifteen percent of adults. If you swab and treat based on presence alone, you're creating antibiotic resistance for nothing.
Get the Full Details
Where The Framework Breaks Down Completely
I want to be blunt about the limitations because the people writing textbooks rarely are. Germ theory cannot explain most chronic diseases. There is no single pathogen that causes Alzheimer's, type two diabetes, or coronary artery disease. Yes, you can find inflammatory markers and occasionally detect opportunistic organisms in affected tissue, but correlation is not causation and Koch's postulates were never satisfied for any of those conditions. The framework also struggles with polymicrobial infections. Wound infections, intra-abdominal abscesses, periodontal disease — these involve dozens of species working together. No single organism satisfies Koch's postulates because the disease requires the community, not an individual. You'll isolate one pathogen from the culture, treat it, and the infection persists because the actual causative consortium was never identified. I ran into this exact problem with a series of post-surgical wound infections at a hospital I consulted for. The standard cultures kept coming back negative despite clear clinical signs of infection. We switched to 16S rRNA sequencing on the tissue samples and found mixed biofilms of anaerobic bacteria that had never been isolated by conventional methods. The patients needed different antibiotics than what the culture-guided protocol would have suggested. It took six weeks to validate the method and another eight to convince the infectious disease team to change their treatment approach.
Antibiotic overprescribing is the most direct consequence of an oversimplified germ theory mindset. When clinicians think disease equals one bug equals one drug, they prescribe broadly and frequently. The result is resistance patterns that make common infections untreatable. I've seen MRSA, VRE, and carbapenem-resistant Enterobacteriaceae become routine in hospitals that rely solely on culture-based diagnostics without considering ecological context.
Practical Steps For Working With The Model
If you're studying this material or working in a clinical lab, here's what actually matters beyond the basic textbook procedures. Always pair culture with molecular diagnostics when possible. PCR panels for respiratory specimens, multiplex GI panels for diarrhea, these reduce the time to actionable results from three to five days down to under two hours. The cost per test is higher, but the downstream savings from earlier targeted treatment are substantial. Learn to read quantitative cultures. A positive blood culture is straightforward, but a positive urine culture needs colony count interpretation. Above 10^5 CFU/mL with consistent organism type usually indicates true bacteriuria. Between 10^3 and 10^5 is the gray zone where clinical context matters more than the number. Below 10^3 is almost certainly contamination or colonization unless you're dealing with a catheterized specimen. Understand that not every pathogen follows the classical model. Some diseases require coincident factors — a pathogen plus a compromised host plus the right environmental conditions. Think about Pseudomonas aeruginosa in ventilator-associated pneumonia. The bacteria is everywhere. It only causes disease when the patient is intubated and immunocompromised. Germ theory identifies the organism but says nothing about why the same organism is harmless in a healthy person and lethal in someone on a ventilator.
The biggest shift I've seen in my career is the move from germ theory toward ecosystem medicine. The human microbiome contains roughly as many microbial genes as human genes. Disrupting that balance with broad-spectrum antibiotics causes more problems than it solves in chronic conditions. Probiotics, fecal transplants, and microbiome modulation are practical applications of recognizing that disease isn't always about invading pathogens. Sometimes it's about what's already there getting out of balance. For anyone trying to apply this framework in research or clinical practice, start by asking whether the pathogen meets modified Koch's postulates rather than the originals. Consider host factors, viral loads, and whether the organism is consistently found in affected tissue across multiple patients. If the answer is yes across all three criteria, you have a stronger case for causation than germ theory alone provides.